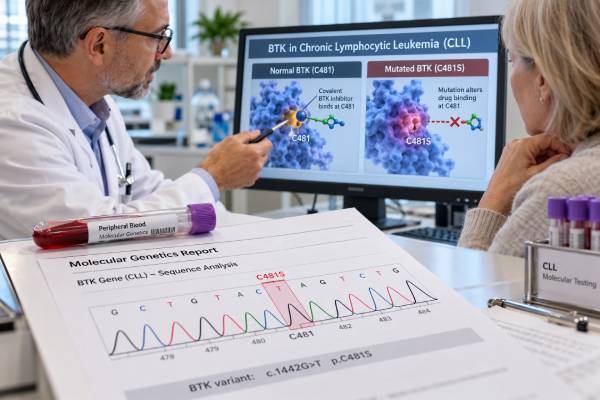
A BTK mutation test looks for acquired changes in the Bruton tyrosine kinase gene that can help explain resistance to BTK inhibitor treatment in chronic lymphocytic leukemia (CLL). The test is most relevant when CLL is progressing during or after a BTK inhibitor, not as a routine diagnostic test for every newly diagnosed patient. Covalent BTK inhibitors such as ibrutinib, acalabrutinib, and zanubrutinib bind the BTK protein at cysteine 481, so mutations affecting that site can reduce drug binding. Newer noncovalent inhibitors such as pirtobrutinib bind differently and can retain activity against some C481-mutated disease, although other BTK mutations can emerge under their selective pressure. A positive result can therefore clarify a mechanism of resistance, but a negative result does not prove that resistance is absent. CLL can progress through PLCG2 mutations, other signaling changes, clonal evolution, or mechanisms that current assays do not identify. The result should be interpreted with treatment history, disease behavior, and the exact sequencing method used.
- BTK mutation testing is mainly a resistance test for CLL that is progressing on or after BTK inhibitor therapy, rather than a standard test used to diagnose CLL.
- BTK C481 mutations are classic resistance changes for covalent inhibitors because these drugs rely on binding at cysteine 481.
- A BTK mutation can guide treatment reasoning, but it does not automatically name the next drug; the specific variant, prior therapies, clinical tempo, and other options matter.
- A negative BTK mutation result does not rule out drug resistance because PLCG2 mutations and non-genetic mechanisms can also drive progression.
- The specimen is usually blood when enough circulating CLL cells are present; tissue or other material may be considered when blood disease is limited.
Table of Contents
- What BTK does in CLL
- When a BTK mutation test is used
- What C481 and other BTK mutations mean
- How BTK mutations cause drug resistance
- How the test is performed and reported
- What positive, negative, and low-level results mean
- How results affect CLL management
What BTK does in CLL
BTK is an important signaling protein in the B-cell receptor pathway. Normal B cells use this pathway to receive survival and activation signals. CLL cells exploit the same network, and ongoing B-cell receptor signaling helps them survive, move between blood and lymphoid tissues, and interact with the supportive microenvironment.
BTK inhibitors interrupt this signaling. Covalent agents such as ibrutinib, acalabrutinib, and zanubrutinib form a durable bond with the BTK protein at amino-acid residue C481. Blocking BTK can produce long-lasting disease control, which is why the pathway has become a major therapeutic target in CLL.
A BTK mutation test does not ask whether a person has inherited a BTK disorder. In the CLL setting, laboratories are generally looking for acquired, or somatic, variants in the leukemia clone. These variants may be absent before treatment and become detectable later because therapy selects a resistant subclone. The test therefore differs from germline BTK testing used in inherited immune disorders.
It also differs from tests used to establish CLL biology at diagnosis. For example, an IGHV mutation test in CLL is a prognostic and biologic classifier that is usually stable over time, while resistance-associated BTK variants can evolve under treatment pressure. Similarly, CLL FISH testing identifies chromosome abnormalities such as del(17p), but it does not substitute for sequencing BTK when acquired inhibitor resistance is the question.
Because the clinical role is treatment-specific, a BTK result only becomes meaningful when the report is paired with the exact drug exposure. A mutation associated with resistance to one class of BTK inhibitor may not have the same effect on another class.
When a BTK mutation test is used
The clearest reason to order BTK mutation testing is suspected CLL progression during therapy with a BTK inhibitor. Progression may appear as steadily enlarging lymph nodes, increasing spleen size, a rising lymphocyte count accompanied by other evidence of disease activity, worsening marrow function, or transformation to a more aggressive lymphoma. The test can help determine whether a known molecular resistance mechanism has emerged.
Testing is less useful when a BTK inhibitor is being stopped solely because of intolerance. A patient who discontinues treatment because of atrial fibrillation, bleeding, hypertension, infection, or another toxicity has a different problem from a patient whose leukemia is escaping pathway inhibition. Mutation testing may still be considered in selected circumstances, but its main clinical value is resistance evaluation.
Routine serial screening in a clinically stable patient is not universally required. Sensitive assays can detect small resistant subclones before obvious progression in some patients, but finding a low-level clone does not necessarily mean treatment should be changed immediately. Clinical trials and specialized centers may use earlier molecular surveillance, yet treatment decisions are generally anchored to the whole disease course rather than the mere appearance of a variant.
The timing of testing matters. If a patient has already stopped the drug and received another therapy, the clonal composition can change. A resistance clone that was dominant at progression may shrink later. When possible, testing near the time of clinical progression provides the most direct link between genotype and drug exposure.
A hematologist may also request a broader next-generation sequencing panel rather than a BTK-only assay. This can identify BTK together with PLCG2 and other clinically relevant genes. The choice depends on local laboratory capabilities, the treatment history, and whether a specific resistance question or broader clonal evolution is being investigated.
What C481 and other BTK mutations mean
The best-known resistance hotspot is BTK C481. Covalent BTK inhibitors depend on cysteine at this position for their irreversible bond. A change such as C481S replaces cysteine with another amino acid and weakens the covalent interaction. The drug may still have some reversible inhibitory activity, but the sustained target blockade that characterizes covalent inhibition is lost.
C481S is not the only possible change. Different amino-acid substitutions at C481 can occur, and multiple BTK variants can coexist in the same patient. This reflects branching clonal evolution: several resistant subclones may independently gain a survival advantage under the same drug pressure.
With second-generation covalent inhibitors and especially noncovalent BTK inhibitors, resistance biology has become more varied. Mutations at sites such as T474 and L528 have been described, along with other kinase-domain changes. These variants can alter drug binding, kinase activity, or the structural role of BTK in ways that differ from classic C481 resistance.
That distinction is important because pirtobrutinib is a noncovalent inhibitor. It does not require the same C481 bond, so it can inhibit many C481-mutated CLL clones that have progressed on a covalent inhibitor. However, non-C481 BTK variants can emerge during noncovalent therapy and reduce its effectiveness. A report that simply states “BTK mutation positive” is therefore less useful than one that names the exact amino-acid change and its variant allele frequency.
Some variants are well established as resistance-associated; others may have uncertain significance. Laboratories typically classify findings using available clinical, functional, and literature evidence. A variant of uncertain significance should not be treated as proven resistance simply because it appears in BTK.
How BTK mutations cause drug resistance
Drug resistance is an evolutionary process. CLL is not genetically identical in every cell. Before treatment, a resistant subclone may already exist below the detection limit, or a new mutation may arise during ongoing cell division. When therapy suppresses sensitive cells, a clone that can signal despite the drug gains a relative advantage and may gradually expand.
For covalent BTK inhibitors, C481 mutation is the classic example. The inhibitor can no longer form its intended permanent bond efficiently, allowing BTK signaling to recover between doses. The resistant clone then receives survival signals that drug-sensitive cells do not.
Resistance can also arise downstream of BTK. PLCG2 is an immediate signaling partner, and activating PLCG2 mutations can allow B-cell receptor signaling to continue even when BTK itself is inhibited. A patient can have a BTK mutation, a PLCG2 mutation, both, or neither. This is why a negative BTK result is not equivalent to “no molecular resistance.”
Noncovalent inhibitor resistance can involve a different spectrum of BTK substitutions. Some reduce drug binding; others may make BTK catalytically impaired yet still capable of supporting signaling through scaffold functions. Additional bypass pathways and microenvironmental signals can also help the leukemia survive.
The biology helps explain an important clinical point: resistance to one BTK inhibitor does not automatically mean all BTK-directed approaches are identical. Drug class, binding mechanism, and mutation location matter. At the same time, simply switching from one covalent inhibitor to another after proven C481-mediated progression usually does not solve the underlying binding problem because the drugs share dependence on C481.
Resistance should also be distinguished from transient changes in blood lymphocyte counts. BTK inhibitors redistribute CLL cells from lymphoid tissues into blood, especially early in treatment, so an initial lymphocytosis can occur despite effective therapy. Clinical progression is defined by a broader pattern, not by a single count in isolation.
How the test is performed and reported
BTK mutation testing is usually performed by DNA sequencing. Next-generation sequencing is common because it can evaluate multiple hotspots or genes at once and detect variants present in a minority of cells. Some laboratories use highly sensitive allele-specific or digital methods for selected mutations. The report should identify the method and, when relevant, the assay’s limit of detection.
Peripheral blood is convenient when there are enough circulating CLL cells. If the disease is predominantly nodal and the blood has few leukemia cells, a blood test may be falsely uninformative simply because the resistant clone is concentrated elsewhere. In selected cases, tissue from an involved lymph node or another disease site may better represent the progressing clone.
A typical report may include the gene, nucleotide change, protein change, variant allele frequency, interpretation, and assay sensitivity. Variant allele frequency, or VAF, is the proportion of sequencing reads that contain the variant. It is not the same as the percentage of all CLL cells carrying the mutation because copy-number changes, sample purity, normal cells, and other factors affect the relationship.
There is no “normal range” for a BTK mutation test in the way there is for sodium or hemoglobin. The basic result is detected or not detected, with additional interpretation of the specific variant. A low VAF can be real if it exceeds the validated detection threshold, but its clinical significance depends on context.
Sequencing quality also matters. A negative result means no reportable mutation was identified within the regions and sensitivity of that assay. It cannot exclude a variant outside the covered region, a clone below the detection limit, or a non-BTK mechanism. This limitation should be visible in the laboratory’s methodology section.
If transformation to Richter syndrome is suspected, mutation testing does not replace tissue biopsy. Rapid lymph-node growth, new systemic symptoms, markedly increased lactate dehydrogenase, or a changing clinical pattern may require PET-directed biopsy because treatment and prognosis differ substantially from ordinary CLL progression.
What positive, negative, and low-level results mean
A positive resistance-associated BTK result means that an acquired variant linked to reduced sensitivity has been found in the tested sample. In a patient whose CLL is progressing on a relevant inhibitor, this can provide a coherent molecular explanation for treatment failure. The significance is strongest when the mutation-drug relationship is established and the clinical course matches.
For example, finding BTK C481S during progression on a covalent inhibitor is a classic pattern. The result supports the conclusion that a resistant clone has been selected. It does not, however, measure disease burden or predict exactly how quickly progression will continue.
A positive non-C481 mutation requires more specific interpretation. Some mutations are associated with resistance to noncovalent inhibitors, while others have different effects across drugs. The hematologist may rely on published evidence, laboratory annotation, and current treatment guidelines to decide how much weight to give the variant.
A negative test is common enough that it should not create false reassurance. Progression can occur through PLCG2, other genomic alterations, pathway rewiring, or mechanisms not captured by the panel. A negative result also may reflect low tumor content. Clinical evidence of progression remains clinically meaningful even when no known BTK variant is found.
Low-level positive results require restraint. A small C481-mutated subclone can sometimes be detected before overt progression. The clone may expand, remain stable for a period, or coexist with other clones. There is not a universal VAF threshold that automatically requires a treatment change in an otherwise stable patient. The trend, disease status, drug exposure, assay reproducibility, and available evidence should guide interpretation.
When several variants are reported, they may represent separate subclones rather than a single cell containing every mutation. Standard bulk sequencing often cannot fully reconstruct that clonal architecture. The practical goal is to identify resistance pathways, not to assume a simple one-mutation/one-clone model.
How results affect CLL management
BTK mutation results are most useful when they help explain why a treatment stopped controlling CLL and narrow the next therapeutic choices. A C481 mutation after a covalent inhibitor supports moving away from simple reliance on another drug with the same covalent binding mechanism. Noncovalent BTK inhibition can remain active against many C481-mutated clones because it does not require covalent attachment at that residue.
Clinical evidence supports pirtobrutinib in patients previously treated with covalent BTK inhibitors, including many with resistance mutations. But treatment selection is broader than one mutation. Prior venetoclax exposure, duration of response to earlier therapies, comorbidities, cytogenetic risk, TP53 status, drug availability, and whether the patient has CLL versus Richter transformation all influence the plan.
If progression occurs on a noncovalent BTK inhibitor, the mutation spectrum may be different. Non-C481 variants can be relevant, and repeating molecular profiling may be more informative than assuming the earlier resistance mechanism persisted unchanged. Newer approaches such as BTK degraders are being studied specifically because degradation may overcome some kinase-domain resistance patterns, but their role depends on regulatory status and evolving clinical data.
The mutation result can also clarify why continuing the same drug indefinitely is unlikely to restore a lost response. In contrast, a patient with stable disease who is merely intolerant of one covalent inhibitor may sometimes switch to another better-tolerated agent because intolerance is not the same as molecular resistance.
CLL treatment should not be changed based solely on an incidental low-level mutation without evidence that a change is clinically indicated. The most useful sequence is to confirm the disease state, review the treatment history, interpret the exact BTK and PLCG2 findings, and then choose an option with a mechanism appropriate to that resistance landscape.
Patients reading a report can ask four practical questions: Which exact BTK mutation was found? Which BTK inhibitor was I taking when it emerged? Was PLCG2 or a broader CLL panel tested as well? Does this result change the recommended next therapy now, or is it a finding to follow? Those questions make the molecular report actionable without giving it more certainty than the evidence supports.
References
– Resistance mechanisms and approach to chronic lymphocytic leukemia after BTK inhibitor therapy 2025 – Novel mechanisms of resistance in CLL: variant BTK mutations in second-generation and noncovalent BTK inhibitors 2025 – Resisting the Resistance: Navigating BTK Mutations in Chronic Lymphocytic Leukemia (CLL). 2023 – Pirtobrutinib after a Covalent BTK Inhibitor in Chronic Lymphocytic Leukemia 2023 – Covalent and Non-Covalent BTK Inhibition in Chronic Lymphocytic Leukemia Treatment 2025
Disclaimer
This article is for general education and does not replace individualized care from a hematologist or oncology team. BTK mutation findings depend on the assay, specimen, treatment history, and the exact variant detected, and a negative result does not exclude clinically important resistance. Do not stop or switch a CLL treatment based on a molecular report without discussing the full clinical context with the treating clinician.