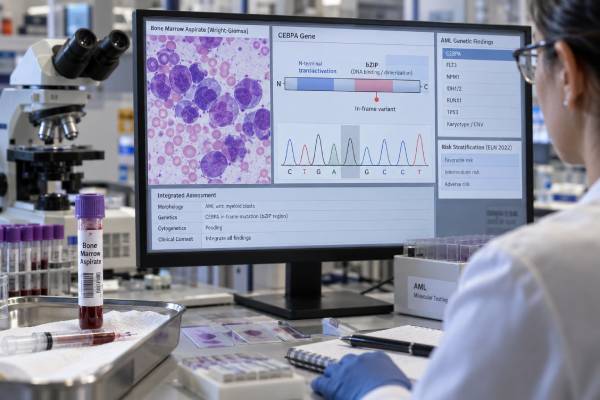
A CEBPA mutation test looks for acquired changes in the CEBPA gene that help classify acute myeloid leukemia (AML) and refine prognosis. CEBPA encodes a transcription factor that supports normal myeloid-cell differentiation. In AML, the most clinically important pattern today is an in-frame mutation affecting the basic leucine zipper, or bZIP, domain. This is more specific than the older concept of simply having two CEBPA mutations. Under modern AML classifications and the 2022 European LeukemiaNet risk system, an in-frame bZIP CEBPA mutation can define a favorable-risk molecular subgroup when other features do not override that interpretation. CEBPA testing is not used alone to diagnose AML, and a positive result does not guarantee cure. The result must be integrated with chromosome findings, other gene mutations, measurable residual disease, age, treatment intensity, and response. Rare germline CEBPA pathogenic variants can also cause familial AML, so the pattern and clinical history sometimes warrant hereditary evaluation.
- A CEBPA bZIP in-frame mutation can be a favorable-risk AML marker under current ELN criteria when interpreted with the full molecular and cytogenetic profile.
- “Double-mutated CEBPA” is no longer the main definition: modern classification emphasizes in-frame mutations in the bZIP region.
- A positive CEBPA result does not diagnose AML by itself: marrow blast percentage, morphology, flow cytometry, cytogenetics, and other molecular findings remain essential.
- A negative result does not mean high-risk AML: many other genetic subtypes exist and must be classified separately.
- Most CEBPA mutations in AML are acquired, but some are inherited: unusual family histories or variant patterns may prompt germline testing.
Table of Contents
- What CEBPA testing measures
- Why CEBPA matters in AML
- How the test is performed
- How to interpret results
- Risk stratification and prognosis
- Germline CEBPA and family risk
- Next steps after testing
What CEBPA testing measures
CEBPA encodes CCAAT/enhancer-binding protein alpha, a transcription factor that helps immature myeloid cells mature into granulocytes. Mutations can disrupt that differentiation program and contribute to leukemia.
CEBPA mutations occur in a minority of AML cases, often around 5%–10% depending on the population and classification used. Historically, AML with two CEBPA mutations was considered a distinct favorable-risk group. More recent data showed that the favorable biology is concentrated in in-frame mutations involving the bZIP domain, whether or not a second CEBPA mutation is present.
A report may list the exact DNA and protein change, mutation location, variant allele frequency, and whether the mutation is in-frame. The location matters because not every CEBPA variant carries the same prognostic meaning.
CEBPA testing is generally part of a broader AML molecular workup that may also include NPM1 testing, FLT3 mutation testing, IDH1, IDH2, TP53, RUNX1, and other myeloid genes.
Why CEBPA matters in AML
The main value of CEBPA testing is classification and prognosis. Modern AML care uses genetics to divide patients into biologically distinct groups that can differ in relapse risk and treatment strategy.
The 2022 European LeukemiaNet recommendations classify AML with an in-frame bZIP CEBPA mutation as favorable risk, provided there is no conflicting adverse-risk abnormality that changes the overall category. The World Health Organization and International Consensus Classification also recognize CEBPA-mutated AML using updated molecular definitions.
The test can therefore help answer several questions:
- Does this AML belong to a recognized molecular subtype?
- Does the genetic profile support favorable, intermediate, or adverse risk?
- Is allogeneic stem-cell transplantation likely to be considered in first remission, or can it be deferred depending on response and other factors?
- Is there a pattern that raises concern for inherited CEBPA predisposition?
CEBPA is not generally used as the main measurable residual disease marker in the way NPM1 can be. AML monitoring usually relies on validated flow-cytometric or molecular MRD methods suited to the individual leukemia.
How the test is performed
Testing usually uses DNA from bone marrow or peripheral blood containing enough leukemic blasts. No fasting is required. The sample may be collected at initial diagnosis, relapse, or occasionally during another molecular reassessment.
Methods include targeted next-generation sequencing and dedicated CEBPA sequencing. CEBPA is technically challenging because of its GC-rich sequence, so assay design and coverage matter. A high-quality test should reliably evaluate the full coding region and characterize the exact mutation.
The laboratory may report one CEBPA mutation or more than one. If two are present, the report should not stop at “biallelic” or “double-mutated.” The clinician needs to know whether at least one qualifying in-frame bZIP mutation is present.
Variant allele frequency can sometimes provide clues about whether a mutation might be germline, but it cannot prove inheritance. Germline confirmation requires testing an appropriate non-leukemic tissue source after specialist review.
How to interpret results
| Finding | General meaning | Important caution |
|---|---|---|
| In-frame bZIP CEBPA mutation | Defines a favorable-risk molecular feature in current ELN classification | Other adverse-risk genetics and clinical factors still matter |
| Two CEBPA mutations without a qualifying bZIP in-frame mutation | Does not automatically receive the older favorable-risk interpretation | Modern classification is domain-specific |
| Single non-bZIP CEBPA mutation | May be biologically relevant but does not by itself define favorable-risk CEBPA AML | Full molecular profile is required |
| No CEBPA mutation detected | CEBPA-mutated AML is not identified | AML risk depends on many other genes and chromosome findings |
The exact wording on a report matters. “CEBPA positive” is not specific enough for modern risk assessment. The treating team should identify the mutation’s protein effect and domain.
A variant of uncertain significance should not be treated as equivalent to a recognized pathogenic AML-associated CEBPA mutation. Laboratories classify variants using population data, functional evidence, recurrence in AML, and other criteria.
Risk stratification and prognosis
Patients with bZIP in-frame CEBPA-mutated AML often have better outcomes with intensive therapy than many other AML subtypes, which is why the lesion is placed in the favorable ELN group. Favorable does not mean low-risk in an everyday sense. AML is still a serious disease, and relapse can occur.
Recent studies have shown heterogeneity even within this subgroup. Co-mutations, age, white-cell count, treatment intensity, MRD response, and transplant strategy can all influence outcomes. More than 30% of patients in some cohorts may still experience treatment failure or death, underscoring why molecular risk is only one part of prognosis.
The favorable designation can affect transplant planning. In many patients who achieve a deep first remission, allogeneic transplant may not be automatically recommended in first complete remission solely because AML is present. However, persistent MRD, poor response, relapse, or additional high-risk features can change that approach.
Modern risk assessment also changes over time. A patient may begin in a favorable genetic group but later develop treatment-resistant disease. Response and MRD therefore remain critical after initial classification.
For broader molecular context, a RUNX1 mutation result and other myeloid-gene findings can carry very different implications from a qualifying CEBPA bZIP mutation.
Germline CEBPA and family risk
Most CEBPA mutations found in AML are somatic, meaning they arose in the leukemia. A small subset of patients have a germline CEBPA pathogenic variant, which can cause familial AML predisposition.
Clues include AML occurring in multiple relatives, unusually young onset, recurrence of AML in a family across generations, or a CEBPA variant pattern known to be associated with germline disease. Some germline variants occur in the N-terminal region, followed by acquisition of a second somatic CEBPA mutation when leukemia develops.
If hereditary disease is suspected, testing blood during active leukemia may be misleading because the blood contains malignant cells. Germline evaluation may use cultured skin fibroblasts or another appropriate non-hematopoietic specimen.
A confirmed germline result has implications for relatives and for stem-cell donor selection. A related donor should not unknowingly carry the same familial predisposition variant.
Next steps after testing
After a CEBPA result, the treating team should place it into the complete AML profile rather than reading it in isolation. Useful next steps are to confirm the exact mutation location, review cytogenetics and co-mutations, assign an ELN risk group, and establish an MRD strategy.
If the report contains an in-frame bZIP mutation, ask whether any adverse-risk genetic feature changes the overall classification. If the mutation is outside the bZIP domain, ask whether it has independent diagnostic or prognostic significance.
If the variant pattern or family history suggests inherited CEBPA predisposition, referral to a genetics service is appropriate before family testing or related-donor transplantation.
The most important practical point is that CEBPA status helps define the leukemia’s biology, but treatment decisions depend on the whole disease picture: age, fitness, cytogenetics, co-mutations, induction response, MRD, and patient goals.
Why the exact CEBPA mutation pattern matters
Older AML classifications often emphasized “biallelic CEBPA” mutations. Modern classification and risk systems focus more specifically on mutations affecting the basic leucine zipper, or bZIP, region. This change matters because not every CEBPA alteration carries the same biologic or prognostic meaning. A report should therefore be read at the variant level rather than reduced to a simple positive/negative label. The location of the mutation, whether it is an in-frame bZIP alteration, and whether other defining or adverse genetic features are present can change the interpretation.
The distinction also explains why older articles or reports may use terminology that does not line up perfectly with current practice. A patient described years ago as having “double-mutant CEBPA AML” may need reinterpretation under newer criteria. Conversely, a single qualifying bZIP in-frame mutation can be highly relevant even if the report does not describe two CEBPA variants. Current AML classification should be applied using the full contemporary molecular and cytogenetic profile.
Co-mutations and measurable residual disease
CEBPA is only one part of an AML genome. NPM1, FLT3, RUNX1, TP53 and other myeloid genes, along with cytogenetic abnormalities, may affect classification, risk, or treatment. A favorable association linked to a qualifying CEBPA pattern should not be assumed to override every adverse feature. This is why AML risk stratification is performed with an integrated model rather than one gene at a time.
Response to treatment is another major layer. Measurable residual disease, or MRD, assesses leukemia that remains below the threshold of routine morphology. Depending on the leukemia and local laboratory, MRD may be evaluated by multiparameter flow cytometry or a validated molecular method. CEBPA itself is not always the preferred marker for longitudinal MRD monitoring, so clinicians may choose another leukemia-associated marker or flow-based strategy. A patient with favorable baseline genetics but persistent MRD may face a different risk discussion from a patient with the same baseline genetics who achieves a deep remission.
CEBPA does not create a stand-alone targeted therapy indication
A CEBPA mutation can define disease biology and contribute to prognosis, but there is no routine CEBPA-specific targeted drug selected simply because the mutation is present. Initial AML treatment still depends on age, fitness, disease subtype, co-mutations, clinical urgency, and whether the patient is eligible for intensive or lower-intensity therapy. Targeted agents may be added when other actionable abnormalities are found.
The same principle applies to transplant decisions. A favorable-risk CEBPA profile may reduce the rationale for allogeneic transplantation in first remission for some patients, but transplant is not decided from the CEBPA line of the report alone. MRD, remission quality, relapse risk, donor options, treatment tolerance, and patient preferences all contribute.
When inherited CEBPA predisposition should be considered
Most CEBPA mutations detected in AML are somatic, meaning they are present in leukemia cells and were not inherited. A subset of patients, however, have a germline CEBPA pathogenic variant that predisposes to familial AML. Clues can include AML at a young age, multiple affected relatives, a variant pattern compatible with germline disease, or persistence of a CEBPA variant when the leukemia is in remission. Family history can be absent, so laboratory and clinical clues both matter.
Confirming germline status requires testing a specimen that is not contaminated by leukemia cells. Blood and bone marrow can be unsuitable at diagnosis, and even remission blood can be difficult to interpret in some myeloid settings. A genetics team may recommend cultured skin fibroblasts or another validated nonhematopoietic specimen. This distinction is especially important before testing relatives or choosing a related stem-cell donor.
If a germline pathogenic variant is confirmed, first-degree relatives may each have a 50% chance of carrying the familial variant because CEBPA-associated predisposition is typically inherited in an autosomal dominant pattern. Predictive testing should target the known familial variant and be paired with genetics counseling so relatives understand what a positive or negative result can and cannot tell them.
Specimen timing can change interpretation
At diagnosis, blood and bone marrow usually contain a high proportion of leukemia cells, making them appropriate for somatic AML profiling. After treatment, the same mutation may become undetectable as the leukemia responds. If a CEBPA variant remains at a near-germline allele fraction during a deep remission, that persistence can raise suspicion that it was present before the leukemia developed, although confirmation still requires a suitable nonhematopoietic specimen.
The reverse situation also deserves caution. A very low-level CEBPA variant detected with a highly sensitive panel may represent a small leukemia subclone and should not automatically be treated as the defining lesion of the whole disease. Variant allele fraction, read quality, assay limitations, and the presence of other AML-defining abnormalities all help determine whether a finding is central, subclonal, or uncertain.
How to read the laboratory report
A useful CEBPA report should identify the nucleotide and protein change, the affected region, the laboratory’s classification, and the approximate variant allele frequency when available. Because CEBPA can be technically challenging to sequence in some regions, the test method and coverage are relevant when the clinical suspicion is high but the result is negative. Laboratories may use next-generation sequencing, Sanger sequencing, or complementary methods designed to capture the full coding region and clinically important insertion/deletion changes.
Patients and clinicians should also distinguish a diagnostic classification from a prognostic label. “AML with CEBPA mutation” describes biology under defined classification criteria; “favorable risk” is a treatment-risk category that depends on current ELN rules and the complete genetic picture. A report can contribute to both, but the two terms are not interchangeable.
Why repeat molecular testing may be ordered at relapse
AML can evolve under treatment pressure. At relapse, the leukemia may retain the original CEBPA alteration, lose a subclone, or acquire additional mutations that were absent or below detection at diagnosis. Repeat profiling can therefore answer a new question: what is driving the current leukemia and are there newly actionable abnormalities? The value of repeat testing depends on the time since diagnosis, prior therapy, available tissue, and whether the result could change treatment or trial eligibility.
A relapse profile should be compared with the original report, but the current sample is interpreted on its own merits. Differences can reflect true clonal evolution, sampling, or assay sensitivity.
Because AML terminology and risk systems continue to evolve, a CEBPA report should be interpreted using the guideline version current at the time treatment decisions are made. Older labels can remain useful historically, but contemporary classification is what should guide present-day risk discussions and treatment planning.
References
- Diagnosis and management of AML in adults: 2022 recommendations from an international expert panel on behalf of the ELN. 2022 (Guideline)
- CEBPA mutations in acute myeloid leukemia: implications in risk stratification and treatment 2024 (Review)
- Validation of the revised 2022 European LeukemiaNet risk stratification in adult patients with acute myeloid leukemia 2024
- Comparison and validation of the 2022 European LeukemiaNet guidelines in acute myeloid leukemia 2022
Disclaimer
CEBPA results should be interpreted by a hematologist or hematopathologist together with the full AML molecular and cytogenetic profile. A favorable-risk CEBPA feature does not guarantee cure and does not replace response or MRD assessment. Suspected germline CEBPA findings require specialist genetic evaluation.