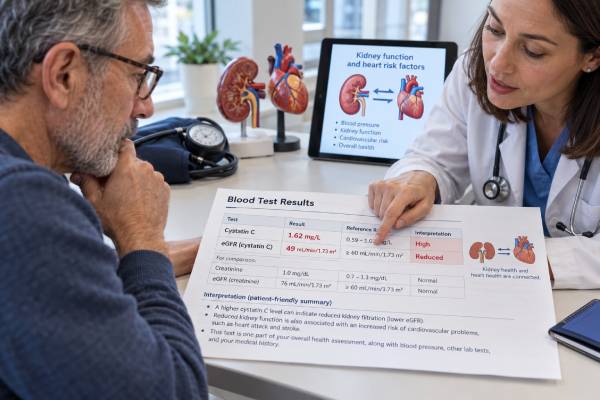
A cystatin C blood test measures a small protein produced by nearly all nucleated cells and cleared from the bloodstream mainly by the kidneys. When kidney filtration falls, cystatin C usually rises. The test is especially useful when serum creatinine may give a misleading picture because of unusually low or high muscle mass, frailty, amputation, intense bodybuilding, or other factors that change creatinine production. Cystatin C can be used by itself to estimate glomerular filtration rate (eGFR), but current kidney guidance often favors an equation that combines cystatin C with creatinine when greater accuracy is needed. A high cystatin C level is also associated with higher risks of cardiovascular events, kidney failure, and death in many populations. That association does not make cystatin C a stand-alone heart test: kidney function and other non-kidney factors influence the result, and the number must be interpreted in context.
- High cystatin C usually suggests lower kidney filtration, but steroids, thyroid disorders, inflammation, adiposity, and other non-GFR factors can also influence the level.
- Reference ranges vary by assay and laboratory; many adult reports place values roughly around 0.6–1.0 mg/L, but the lab’s own interval should be used.
- Cystatin C is less dependent on muscle mass than creatinine, making it useful when creatinine may overestimate or underestimate kidney function.
- The combined creatinine-cystatin C eGFR is often more accurate than an equation based on either marker alone.
- A high cystatin C is linked with higher cardiovascular risk, but it does not diagnose heart disease and should not be interpreted as a cardiac marker by itself.
Table of Contents
- What Cystatin C Measures
- Normal and High Cystatin C Levels
- Cystatin C vs. Creatinine
- Cystatin C and eGFR
- Non-Kidney Factors That Affect Cystatin C
- Cystatin C and Heart Risk
- When Testing Is Useful and What Happens Next
What Cystatin C Measures
Cystatin C is a low-molecular-weight protein produced at a relatively steady rate by cells throughout the body. It circulates in blood, passes through the kidney’s glomerular filters, and is then taken up and broken down in the proximal tubules. Very little intact cystatin C normally returns to the bloodstream after filtration.
Because its blood concentration rises as filtration falls, cystatin C functions as an endogenous filtration marker. In that sense, it serves a role similar to creatinine. The important difference is how the two markers are produced. Creatinine production depends heavily on muscle mass and diet, while cystatin C is far less influenced by muscle mass or recent meat intake.
A cystatin C result may be ordered as a direct blood concentration in mg/L. More often, its greatest clinical value comes from using it to calculate an estimated glomerular filtration rate. A cystatin C-based eGFR can be calculated from cystatin C alone, or a combined equation can use both cystatin C and creatinine.
The test does not measure kidney damage directly. It estimates filtration. A person may still have kidney disease with preserved filtration if there is persistent albumin in the urine, structural kidney disease, or another marker of kidney injury. Conversely, a single elevated cystatin C does not prove chronic kidney disease because acute illness and non-kidney factors can affect the result.
Normal and High Cystatin C Levels
Cystatin C reference intervals are assay-specific and can differ among laboratories. Many adult laboratories use a range near 0.6–1.0 mg/L, but values outside that range are not interpreted in isolation. Age, laboratory calibration, thyroid status, steroid exposure, inflammation, and other clinical factors can matter.
In general, a higher cystatin C concentration corresponds to lower filtration. For example, if two otherwise similar blood samples show cystatin C rising from 0.8 mg/L to 1.4 mg/L, the eGFR calculated from cystatin C would usually be lower in the second sample.
A high result may reflect:
- chronic kidney disease;
- acute kidney injury or reduced kidney perfusion;
- progression of known kidney disease;
- a non-kidney factor that raises cystatin C;
- a combination of reduced filtration and non-GFR influences.
A low cystatin C is usually less clinically important. It may be seen with higher filtration or certain physiologic states, but low values are rarely used as a stand-alone diagnosis.
The most useful question is often not whether cystatin C itself is “high,” but what eGFR it produces and whether that result agrees with the creatinine-based estimate. The pattern of agreement or disagreement can reveal when one marker is being distorted by factors unrelated to filtration.
Cystatin C vs. Creatinine
Creatinine remains the most widely used kidney filtration marker because it is inexpensive, routinely available, and automatically reported in common blood panels. Cystatin C is more specialized and may cost more or have a longer turnaround time.
The two markers have different strengths and weaknesses.
| Feature | Creatinine | Cystatin C |
|---|---|---|
| Main non-GFR influence | Muscle mass, diet, creatine intake, some medications | Steroids, thyroid function, inflammation, adiposity and other systemic factors |
| Availability | Very widely available | Less universally available |
| Effect of muscle wasting | Can make kidney function look better than it is | Much less affected |
| Use in routine panels | Common | Usually ordered separately |
| Best use | First-line estimation in most adults | Confirmation or refinement when creatinine may be misleading |
| Combined use | Useful first-line marker in most adults | Creatinine plus cystatin C generally provides a more accurate eGFR than either marker alone |
A creatinine blood test can underestimate the severity of kidney dysfunction in a person with very low muscle mass because the body produces little creatinine. The same person may have a cystatin C result that yields a lower and more plausible eGFR.
The opposite can happen in someone with unusually high muscle mass, heavy meat intake, or creatine supplementation. Creatinine may look elevated even when filtration is relatively preserved. Cystatin C can provide a second perspective.
Neither marker is biologically perfect. The advantage of combining them is that the non-GFR errors often differ. When both markers point to a similar eGFR, confidence in the estimate increases. When they disagree substantially, the discrepancy itself becomes clinically informative.
Cystatin C and eGFR
Cystatin C is most useful when translated into eGFR. Current adult equations can estimate GFR from creatinine alone, cystatin C alone, or both markers together. Modern equations do not require a race coefficient.
The eGFR test is reported in mL/min/1.73 m². The same chronic kidney disease GFR categories apply whether the estimate comes from creatinine, cystatin C, or both:
| GFR category | eGFR | General description |
|---|---|---|
| G1 | ≥90 | Normal or high |
| G2 | 60–89 | Mildly decreased |
| G3a | 45–59 | Mild to moderately decreased |
| G3b | 30–44 | Moderately to severely decreased |
| G4 | 15–29 | Severely decreased |
| G5 | <15 | Kidney failure category |
For G1 and G2, a low-risk eGFR alone does not establish chronic kidney disease. Another marker of kidney damage, such as persistent albuminuria, is needed. Chronicity also matters: CKD requires abnormalities present for at least three months.
The combined creatinine-cystatin C equation is particularly useful when the eGFR is close to an important decision threshold. Examples include certain medication doses, transplant evaluation, or deciding whether a person truly falls above or below a CKD category boundary.
Cystatin C may also help when creatinine-based eGFR appears inconsistent with the rest of the clinical picture. If the creatinine estimate is 75 but cystatin C estimate is 45, the difference is too large to ignore. The care team should look for reasons for discordance rather than simply averaging the two numbers informally.
Non-Kidney Factors That Affect Cystatin C
Cystatin C is less affected by muscle mass than creatinine, but it is not completely independent of non-kidney factors. Important influences include glucocorticoid treatment, thyroid dysfunction, adiposity, inflammation, and some chronic illnesses. Smoking has also been associated with higher levels in some studies.
Glucocorticoids can raise cystatin C without an equivalent fall in true GFR, especially at higher doses. Hyperthyroidism tends to increase cystatin C, while hypothyroidism can lower it. If thyroid disease is uncontrolled, a cystatin C-based eGFR may therefore misrepresent filtration.
Inflammation and adiposity are more complicated. They can correlate with higher cystatin C, and the same factors also increase cardiovascular risk. This overlap helps explain why cystatin C may carry prognostic information beyond a simple measure of GFR, but it also means a high level cannot always be attributed entirely to kidney filtration.
The practical point is to choose the filtration marker least distorted by the patient’s circumstances. In a person with major muscle wasting but no steroid exposure or thyroid disorder, cystatin C may be especially helpful. In someone taking high-dose steroids with stable muscle mass, creatinine may remain useful, and the combined result should be interpreted carefully.
If both markers are likely to be distorted or a highly accurate value is necessary, measured GFR using an external filtration marker may be considered.
Cystatin C and Heart Risk
Higher cystatin C levels are consistently associated with increased risks of cardiovascular disease, heart failure, kidney failure, and death. Studies often find that cystatin C-based eGFR and discrepancies between cystatin C- and creatinine-based eGFR provide prognostic information beyond creatinine alone.
However, cystatin C should not be treated as a direct heart-disease diagnostic test. A high result does not prove coronary artery disease, heart failure, or a future heart attack. It identifies a group with higher statistical risk, partly because lower kidney function itself is strongly associated with cardiovascular disease and partly because inflammation, metabolic factors, and other systemic influences can raise cystatin C.
A particularly important pattern is when eGFR based on cystatin C is much lower than eGFR based on creatinine. Large negative discordance has been associated with worse outcomes in observational studies. This may occur because creatinine is falsely reassuring in people with low muscle mass or because cystatin C captures other health risks not reflected in creatinine.
The clinical response is not to treat the cystatin C number directly. Instead, clinicians use the result to refine kidney staging and overall risk assessment. That can strengthen the case for careful blood-pressure control, diabetes management, smoking cessation, appropriate lipid treatment, medication review, and monitoring of kidney disease.
Cystatin C is therefore best understood as both a filtration marker and a risk marker. Its prognostic associations are useful, but they must be separated from causation. Lowering cystatin C itself is not a treatment goal unless the change reflects improved kidney function or correction of an underlying condition.
When Testing Is Useful and What Happens Next
Cystatin C is most useful when creatinine-based eGFR may be inaccurate or when greater precision would change care. Situations include:
- severe muscle wasting, frailty, paralysis, or amputation;
- unusually high muscle mass or intensive bodybuilding;
- a creatinine-based eGFR near an important treatment threshold;
- a need to confirm or refine CKD classification;
- a clinical picture that does not match the creatinine result;
- selected medication-dosing or transplant decisions.
A kidney function blood test panel may include creatinine, BUN, eGFR, electrolytes, and sometimes cystatin C. Urine albumin remains important because filtration and kidney damage are different dimensions of kidney health.
No special fasting is usually required for cystatin C alone. A routine venous blood sample is taken. If other blood tests are ordered at the same time, follow the preparation instructions for those tests. Tell the clinician about steroid use, thyroid disease, pregnancy, major inflammatory illness, and other factors that could affect interpretation.
If cystatin C is high, the next step is usually not to repeat it immediately without context. Clinicians compare it with creatinine, calculate eGFRcr-cys, review prior kidney results, check urine albumin, assess blood pressure and diabetes, and look for acute illness or medication effects.
When creatinine- and cystatin C-based estimates disagree substantially, the combined equation is generally preferred for routine estimation. If the decision is high stakes and uncertainty remains, a measured GFR may provide a more direct answer.
What it means when cystatin C changes over time
A trend in cystatin C can be more informative than one result, especially when the same laboratory method is used. If cystatin C rises and creatinine rises in parallel, a true decline in filtration becomes more likely. If cystatin C changes substantially while creatinine remains stable, clinicians look for both kidney and non-kidney explanations.
For example, a person starting high-dose glucocorticoid therapy may develop a higher cystatin C without an equivalent change in measured filtration. Someone with untreated hyperthyroidism may also have a higher cystatin C than expected. On the other hand, a frail patient losing muscle may show little change in creatinine despite worsening kidney function, while cystatin C rises and reveals the decline more clearly.
This is one reason a combined eGFR can be valuable: it reduces reliance on a single biological pathway. The combined number should still be compared with prior results and interpreted in the clinical setting rather than treated as a mathematically perfect answer.
How cystatin C can change CKD classification
Cystatin C can move a person into a different eGFR category than creatinine alone. This is most noticeable near category boundaries. A creatinine-based eGFR of 62 mL/min/1.73 m² may become a combined eGFR of 54, for example, moving the filtration category from G2 to G3a. The reverse can also occur when creatinine is elevated because of high muscle mass.
Reclassification matters when it changes medication dosing, referral decisions, risk estimates, or how strongly clinicians interpret an apparently borderline result. It should not be used mechanically. The urine albumin category, blood pressure, diabetes, cardiovascular disease, and rate of change remain important parts of CKD risk.
If a cystatin C result changes the apparent stage substantially, it is reasonable to review potential non-GFR influences before making major decisions. A stable combined estimate, repeated when appropriate, is more persuasive than one isolated discrepancy.
What cystatin C cannot tell you
Cystatin C does not identify the cause of kidney disease. It cannot distinguish diabetic kidney disease from glomerulonephritis, obstruction, inherited disease, or medication-related injury. It also does not measure urine protein, kidney anatomy, or electrolyte complications.
For those questions, clinicians use urine albumin, urinalysis, imaging, blood pressure, diabetes testing, medication review, and sometimes specialized blood tests or kidney biopsy. Cystatin C is most powerful when used for the narrow job it does well: improving the estimate of filtration when creatinine alone may be uncertain.
Preparing for and discussing the result
Cystatin C usually does not require fasting when ordered by itself. The blood draw is the same as for other routine chemistry tests. What matters more than fasting is giving the clinician context that can affect interpretation, including thyroid disease, steroid treatment, a major inflammatory illness, pregnancy, recent hospitalization, and large changes in weight or muscle mass.
When the result is available, ask which eGFR was calculated: creatinine-only, cystatin C-only, or the combined equation. If the estimates differ substantially, ask what factors might explain the gap and which number should guide the specific decision. A combined result may refine CKD staging, but urine albumin and the trend over time remain essential.
If cystatin C is elevated during an acute illness, repeating the marker after the illness resolves may be useful when the result would change management. Persistent elevation is more meaningful than a single abnormal value whose context includes temporary factors known to affect the marker.
References
- Cystatin C 2023
- Advantages, Limitations, and Clinical Considerations in Using Cystatin C to Estimate GFR 2022 (Review)
- Cystatin C should be routinely available for estimating kidney function 2024 (Review)
- Discordance between cystatin C-based and creatinine-based estimated glomerular filtration rate and health outcomes in adults: a systematic review and meta-analysis 2025 (Systematic Review)
- CKD Evaluation and Management 2024 (Guideline)
Disclaimer
Cystatin C and cystatin C-based eGFR are estimates of kidney filtration and can be affected by non-kidney factors. A high cystatin C does not by itself diagnose chronic kidney disease or heart disease. Results should be interpreted with creatinine, urine testing, medical history, medications, thyroid status, and the clinical situation.