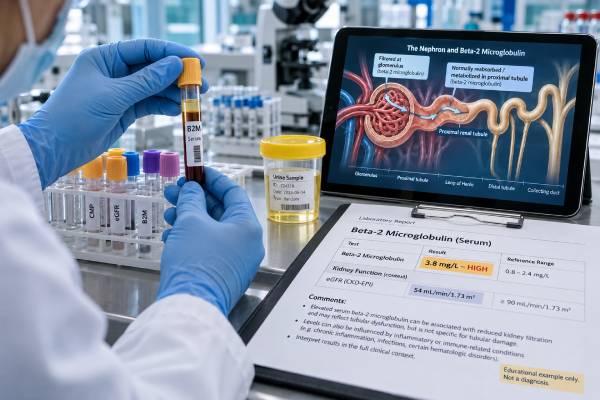
A beta-2 microglobulin (B2M or β2M) blood test measures a small protein that is continuously released by most nucleated cells. Healthy kidneys filter beta-2 microglobulin from the blood and proximal kidney tubules then reabsorb and break down almost all of the filtered protein. Because of this pathway, serum B2M often rises when kidney filtration declines. It can also rise when the body produces more B2M because of inflammation, immune activation, or certain blood cancers.
The blood test is therefore sensitive to kidney function but not specific for kidney disease. A high result does not prove that the kidney tubules are damaged, and it cannot identify the cause of kidney dysfunction by itself. In fact, urine beta-2 microglobulin is generally more directly linked to impaired proximal tubular reabsorption. Serum B2M is best interpreted with creatinine, eGFR, urine protein testing, clinical history, and—when relevant—hematology or inflammatory findings.
- High serum beta-2 microglobulin commonly occurs when kidney filtration is reduced, but inflammation and blood-cell disorders can also raise it.
- Serum B2M is not a stand-alone test for tubular damage; increased urine B2M is more directly associated with proximal tubular dysfunction.
- Reference ranges are assay-specific; one major clinical laboratory uses approximately 1.21–2.70 mg/L for serum B2M.
- B2M can become very high in advanced kidney failure and dialysis, partly because normal renal clearance is lost.
- A high result should be interpreted with creatinine/eGFR and the clinical context, especially if multiple myeloma, lymphoma, autoimmune disease, infection, or CKD is possible.
Table of Contents
- What Beta-2 Microglobulin Is
- Normal Range and High Levels
- Beta-2 Microglobulin and Kidney Function
- Blood Versus Urine B2M and Tubular Damage
- Other Causes of High Beta-2 Microglobulin
- How the Test Is Used and Interpreted
- Dialysis, Monitoring, and Follow-Up
What Beta-2 Microglobulin Is
Beta-2 microglobulin is a low-molecular-weight protein of about 11.8 kDa. It forms part of major histocompatibility complex class I molecules, which are present on the surface of nearly all nucleated cells. As cells normally turn over, small amounts of B2M are released into the bloodstream.
The kidneys play a major role in clearing it. B2M is small enough to pass through the glomerular filtration barrier. After filtration, proximal tubular cells reclaim almost all of it and break it down. That two-step process—glomerular filtration followed by tubular reabsorption—explains why B2M can provide information about kidney physiology.
However, serum B2M is influenced by both production and clearance. A high blood level may mean the kidneys are clearing less B2M, the body is producing more of it, or both. This is the central limitation of the test.
For routine kidney assessment, serum creatinine and estimated glomerular filtration rate remain more standardized and widely used. B2M is an additional biomarker that can be useful in selected settings, including kidney failure, research, dialysis assessment, and hematologic disease.
Normal Range and High Levels
There is no single universal serum B2M reference range because laboratories use different assays and calibration systems. One major reference laboratory reports approximately 1.21–2.70 mcg/mL, which is numerically the same as 1.21–2.70 mg/L. Other laboratories may use different limits.
The most important rule is to use the range printed on the actual laboratory report. A value that is mildly above one laboratory’s upper limit may fall within another assay’s range.
A high serum B2M result can reflect several broad mechanisms:
- reduced glomerular filtration from CKD or acute kidney dysfunction;
- increased immune-system activity or inflammation;
- increased cell turnover in hematologic cancers such as multiple myeloma, some lymphomas, or chronic lymphocytic leukemia;
- certain infections or autoimmune diseases;
- a mixture of impaired clearance and increased production.
Unlike creatinine, B2M is not mainly generated from muscle. That can make it informative when muscle mass makes creatinine harder to interpret. But B2M has its own non-kidney influences, so it is not automatically a “better creatinine.”
A single elevated value also does not tell whether kidney dysfunction is acute or chronic. That distinction depends on prior kidney results, the speed of change, symptoms, urine findings, and the clinical situation.
Low serum B2M is usually much less clinically important than a high level. Because the protein is continuously produced at low levels, a result below a laboratory range is rarely used to diagnose a specific kidney disorder. The clinical focus is usually on unexpected elevation, trends over time, and whether the value fits kidney function and the reason testing was ordered.
It is also important not to apply oncology cutoffs as if they were kidney reference limits. In multiple myeloma, specific B2M thresholds are used in prognostic staging, but those thresholds were developed for cancer risk classification, not for deciding whether kidney function is normal. A person can have a B2M value above the laboratory reference range because of reduced GFR without having a blood cancer, and a person with a hematologic disorder can have a high value partly because of tumor biology even when creatinine appears only mildly abnormal.
Beta-2 Microglobulin and Kidney Function
As glomerular filtration rate falls, serum beta-2 microglobulin usually rises because less of the protein is filtered and cleared. This relationship has been recognized for decades and is one reason B2M has been studied as an alternative endogenous filtration marker.
In CKD, higher serum B2M has also been associated with worse kidney and cardiovascular outcomes. A 2024 study in people with biopsy-proven diabetic nephropathy found that serum B2M added prognostic information for progression to kidney failure even after accounting for established clinical and histologic factors. Such findings support B2M as a risk marker, but they do not make it a routine replacement for eGFR.
B2M and creatinine differ in what influences them. Creatinine varies with muscle mass, meat intake, some medications, and secretion by kidney tubules. B2M is less dependent on muscle but is more affected by inflammation, immune activation, and hematologic disease. A cystatin C blood test is another alternative filtration marker that is more standardized for clinical eGFR calculations than B2M.
When serum B2M and creatinine both rise in a person with known CKD and no evidence of a high-cell-turnover disorder, reduced kidney clearance becomes a likely contributor. If B2M is strikingly elevated out of proportion to the degree of renal impairment, clinicians may consider whether increased production is also present.
The test is especially difficult to interpret in multiple myeloma because both tumor burden and kidney dysfunction can elevate B2M. In that setting, the result is used for prognosis and staging in combination with other information rather than as a pure kidney marker.
Age and chronic disease burden can also shift B2M upward because filtration tends to decline and inflammatory activity may increase. That is another reason a mild elevation should not be read in isolation. A clinician may repeat the test after an acute illness resolves or after kidney function stabilizes to see whether the elevation persists. Persistent unexplained elevation is interpreted in the context of blood counts, protein studies, inflammatory symptoms, and other findings rather than triggering one diagnosis automatically.
Blood Versus Urine B2M and Tubular Damage
The phrase “B2M test for tubular damage” needs an important clarification: urine B2M and serum B2M answer different questions.
Normally, filtered B2M is almost completely reabsorbed by proximal tubule cells. If these cells are damaged or cannot reabsorb low-molecular-weight proteins properly, more B2M can remain in the urine. Increased urinary B2M has therefore been used as a marker of proximal tubular dysfunction in conditions such as interstitial nephritis, Fanconi syndrome, certain toxic exposures, and some inflammatory kidney diseases.
A beta-2 microglobulin urine test is more directly aligned with that use. Even then, interpretation requires care because urinary B2M can degrade in acidic urine, so proper collection and sample handling matter.
Serum B2M is different. A high blood level most often reflects reduced clearance, increased production, or both. It does not demonstrate that proximal tubular cells are failing to reabsorb B2M. In some forms of isolated tubular dysfunction, urine B2M may be high while serum B2M is normal or relatively low.
| Test | What tends to raise it | Main kidney interpretation |
|---|---|---|
| Serum beta-2 microglobulin | Reduced GFR, inflammation, immune activation, blood cancers | Can reflect impaired kidney clearance but is not specific for tubular injury |
| Urine beta-2 microglobulin | Failure of proximal tubular reabsorption | Supports proximal tubular dysfunction when collection and pH handling are appropriate |
This distinction is clinically important because “high B2M” without specifying the specimen can lead to the wrong conclusion.
Other Causes of High Beta-2 Microglobulin
B2M is part of the immune system’s class I HLA complex, so conditions that increase lymphocyte activity or cellular turnover can increase its release into blood. That is why serum B2M is widely known as a tumor marker in certain blood cancers.
Multiple myeloma: Serum B2M is incorporated into widely used prognostic systems. Higher values can reflect greater disease burden, impaired kidney function, or both. A high B2M level cannot diagnose multiple myeloma; diagnosis requires monoclonal protein studies, bone marrow assessment, imaging, and other criteria.
Lymphoma and chronic lymphocytic leukemia: Some hematologic malignancies increase B2M through high cell turnover or immune-cell activity. The test may be used for prognosis or monitoring in selected patients.
Autoimmune and inflammatory disease: Chronic immune activation can increase B2M production. This means a person with preserved kidney function can still have an elevated result.
Infection: Some viral and systemic infections can raise B2M because immune-cell turnover and activation increase.
Liver disease and other chronic illness: Several nonrenal conditions can affect B2M levels, further reducing specificity.
This broad differential is why B2M should not be used as a screening test for one disease. It is most informative when ordered to answer a focused clinical question.
Because beta-2 microglobulin is affected by both production and clearance, interpretation starts with the clinical question. If the concern is kidney filtration, serum B2M is considered alongside creatinine, eGFR, and sometimes cystatin C. If the concern is proximal tubular injury, urine B2M may be more informative, but it still needs context from urinalysis, urine protein patterns, medications, and the suspected cause of tubular damage. The same numerical elevation can therefore have different implications in a person with chronic kidney disease, an inflammatory illness, or a hematologic disorder.
A trend can be more useful than an isolated result when the same test method and similar clinical conditions are used. Rising serum B2M may accompany worsening filtration, but it can also rise because the body is producing more of the protein. Falling levels may occur as kidney function or an inflammatory state improves. This is one reason B2M does not replace creatinine-based eGFR for routine CKD staging. Instead, it is a complementary marker used in selected situations where its biology can answer a more specific question.
The reference interval on the laboratory report should be used for the actual interpretation. Assays and populations differ, and a value close to a cutoff should not be treated as a sharp boundary between health and disease. Clinicians look for consistency with other findings before deciding whether an abnormal B2M result needs repeat testing, additional kidney studies, or evaluation for a non-kidney cause.
How the Test Is Used and Interpreted
A serum beta-2 microglobulin test usually requires a standard venous blood sample. Fasting is generally not required for B2M alone. The test may be ordered by nephrology, hematology, oncology, or other specialties depending on the clinical question.
For kidney interpretation, clinicians may review:
- creatinine and eGFR;
- cystatin C when greater filtration accuracy is needed;
- urine albumin or total protein;
- urinalysis and urine sediment;
- urine B2M or other low-molecular-weight proteins when proximal tubular dysfunction is suspected;
- medication and toxin exposures;
- inflammatory markers or blood counts when increased production is possible.
A renal function panel gives more routine information about filtration, electrolytes, bicarbonate, and mineral balance than B2M alone.
Several interpretation patterns are useful:
High B2M plus low eGFR: Reduced renal clearance is likely contributing. The degree of B2M elevation may still be influenced by inflammation or cell turnover.
High B2M with relatively preserved eGFR: Consider increased production, early kidney dysfunction not well captured by creatinine, or both. Additional testing depends on symptoms and clinical context.
High urine B2M with normal or modest serum B2M: Proximal tubular dysfunction becomes more plausible, especially if other tubular abnormalities are present.
Rising B2M over time in a hematologic disorder: The trend may reflect disease activity, kidney function, or both, so it should be interpreted with the cancer-specific monitoring plan.
Because assay methods vary, serial monitoring is easiest to interpret when performed by the same laboratory or a comparable method.
B2M should also be separated from other “microglobulin” tests. Alpha-1 microglobulin, for example, is another low-molecular-weight protein used mainly in urine as a marker of tubular handling. Neither is the same as urine albumin, which reflects glomerular leakage and is central to CKD risk classification. When a clinician orders a panel of low-molecular-weight proteins, the goal may be to identify a tubular pattern that would not be captured by albuminuria alone.
The pretest question matters. If the concern is routine CKD screening, creatinine/eGFR and urine albumin are usually more useful first-line tests. If the concern is a proximal tubule disorder, urinary low-molecular-weight proteins may be more informative. If the concern is myeloma prognosis, serum B2M has a different role entirely. The same numeric result can therefore carry different meaning depending on why it was measured.
Dialysis, Monitoring, and Follow-Up
B2M becomes particularly important in advanced kidney failure because normal renal elimination is greatly reduced. Conventional dialysis clears small molecules such as urea readily, but B2M is larger and is removed less efficiently. Modern high-flux hemodialysis and hemodiafiltration remove more B2M than older low-flux dialysis techniques, although residual kidney function remains a major determinant of predialysis B2M levels.
Over many years of kidney failure and dialysis, persistently high B2M can form amyloid deposits in tissues. This condition, called dialysis-related amyloidosis, can affect joints and bones and has historically been associated with carpal tunnel syndrome, shoulder pain, bone cysts, and destructive joint disease. Improved dialysis membranes and techniques have reduced the problem compared with earlier dialysis eras, but B2M remains central to its biology.
A high serum B2M result in a dialysis patient should not be interpreted using the reference range for people with normal kidney function. Instead, nephrologists consider dialysis modality, residual urine output, treatment adequacy, inflammation, and symptoms. Research has evaluated B2M as a marker of middle-molecule clearance and outcome risk, but routine targets vary and are not equivalent to standard measures such as Kt/V for urea.
For someone not on dialysis, follow-up depends on why the test was ordered. An unexpected elevation may lead to repeat kidney function testing, urine studies, review of inflammatory or hematologic conditions, and comparison with previous results. The next step is rarely based on B2M alone.
The most accurate way to read the test is to separate three questions: Is B2M production increased? Is kidney clearance reduced? Is there evidence of proximal tubular dysfunction in the urine? Keeping those questions distinct prevents a high blood B2M result from being mislabeled as proof of tubular damage.
References
- Beta 2 microglobulin in kidney failure: A review and an algorithm for renal replacement therapy 2022 (Review)
- Systematic Review of Kidney Injury Biomarkers for the Evaluation of CKD of Uncertain Etiology 2024 (Systematic Review)
- Comparative Prognostic Value of Glomerular Filtration Rate, Serum Cystatin C, Beta-2-Microglobulin and Albuminuria for Death and Chronic Kidney Disease Progression 2025 (Comparative Study)
- Acute kidney injury: Detection, risk stratification, and predictive biomarkers 2026 (Review)
- Beta 2 Microglobulin (B2M) Tumor Marker Test 2025 (Official)
Disclaimer
This article is for general education and does not diagnose kidney disease, tubular injury, or cancer. Beta-2 microglobulin can rise for several kidney and non-kidney reasons, and blood and urine B2M have different interpretations. Review an abnormal result with a clinician who can compare it with creatinine/eGFR, urine findings, medications, and the reason the test was ordered.