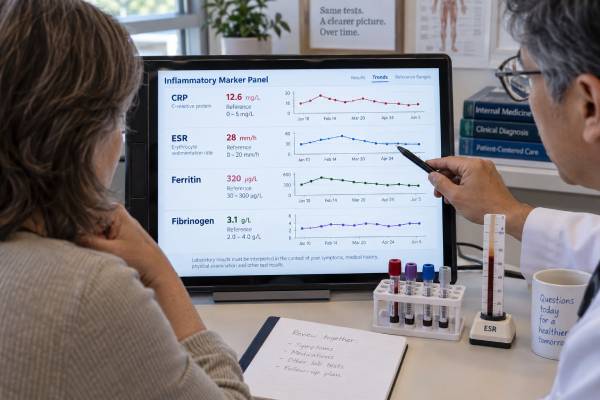
An inflammatory marker panel is not one universally standardized test. It is a group of laboratory measurements selected to answer a clinical question, often including C-reactive protein (CRP), erythrocyte sedimentation rate (ESR), ferritin, and sometimes fibrinogen. Each marker reflects a different part of the acute-phase response. CRP changes quickly, ESR is influenced by plasma proteins and red blood cells, ferritin combines iron storage with inflammation, and fibrinogen links the acute-phase response to coagulation. Abnormal results can support the presence of inflammation or help track a known disease, but they cannot locate the source or prove that vague symptoms come from “chronic inflammation.” Normal results also do not exclude every inflammatory condition. The panel is most useful when chosen deliberately and interpreted with symptoms, examination, a complete blood count, organ-function tests, and disease-specific studies. This guide shows how the four markers differ, what common result patterns mean, and how to avoid unnecessary testing or misleading conclusions.
- No universal panel: Laboratories and clinicians use different combinations depending on the suspected condition.
- Fastest common marker: CRP usually rises and falls more rapidly than ESR.
- Most confounded marker: ESR changes with age, anemia, pregnancy, immunoglobulins, and red-cell shape as well as inflammation.
- Dual-purpose markers: Ferritin reflects iron handling, while fibrinogen participates directly in clot formation.
- Core limitation: A panel can show an inflammatory pattern but usually cannot identify the disease without targeted evaluation.
Table of Contents
- What an inflammatory marker panel is
- How CRP, ESR, ferritin, and fibrinogen differ
- How to interpret common result patterns
- What the tests can say about chronic inflammation
- When a panel is useful—and when it is not
- Next tests, monitoring, and treatment decisions
- Warning signs that need prompt medical care
What an Inflammatory Marker Panel Is
Inflammation is a coordinated response to infection, tissue injury, immune activation, and other threats. Immune cells release cytokines that change blood vessels, recruit white cells, and signal the liver to alter protein production. Proteins that increase are called positive acute-phase reactants; those that decrease are negative acute-phase reactants. The response can be intense and brief, low-grade and persistent, localized to one organ, or systemic.
There is no single blood test that measures all of this biology. The phrase “inflammatory marker panel” is often used informally for two or more nonspecific markers ordered together. A common combination is CRP and ESR. Ferritin may be added when anemia, iron status, fever, liver disease, or a hyperinflammatory syndrome is relevant. Fibrinogen may be measured when coagulation, bleeding, pregnancy, cardiovascular disease, or severe systemic illness is part of the question.
Other tests are sometimes grouped under the same label:
- Complete blood count with differential
- Platelet count
- Albumin and total protein
- Procalcitonin for selected bacterial infection and sepsis decisions
- Serum amyloid A in specialized settings
- Calprotectin or lactoferrin for intestinal inflammation
- Cytokines such as interleukin-6, usually in specialized care or research
The value of a panel comes from complementary behavior, not from adding as many tests as possible. Ordering markers without a clinical question increases the chance of incidental abnormalities, repeated testing, and false reassurance. A small elevation in an otherwise well person may reflect a recent infection, obesity, smoking, pregnancy, dental inflammation, or laboratory variation. A normal panel may coexist with localized disease or an inflammatory condition that does not generate a strong systemic response.
The sample is usually venous blood. Fasting is not required for CRP or ESR alone, but other tests ordered at the same time may have preparation instructions. Recent infection, vaccination, surgery, exercise, pregnancy, medicines, supplements, and chronic conditions should be considered. Results are clearest when compared with the laboratory’s own reference intervals and prior values from the same method.
How CRP, ESR, Ferritin, and Fibrinogen Differ
The four markers do not answer the same question. Their timing, biological role, units, and confounders differ.
C-Reactive Protein
CRP is made by the liver, largely in response to interleukin-6. It can rise within hours of infection or tissue injury, often peaks within about two days, and falls relatively quickly when the stimulus resolves because it has a short and stable half-life. This makes the CRP test useful for following rapid change.
Standard CRP assays assess active systemic inflammation over a wide range. High-sensitivity CRP uses a more precise method at low concentrations and has a different role in cardiovascular risk assessment. The two should not be treated as interchangeable labels. CRP is nonspecific: infection, autoimmune disease, surgery, trauma, infarction, and cancer can all raise it.
Erythrocyte Sedimentation Rate
ESR measures how far red blood cells settle in a vertical tube over a set time. Inflammatory proteins—especially fibrinogen and immunoglobulins—reduce repulsion between red cells and promote rouleaux, allowing them to settle faster. ESR often changes more slowly than CRP and may remain elevated after acute inflammation improves.
The ESR test is strongly influenced by age, sex, pregnancy, anemia, kidney disease, red-cell size and shape, and plasma proteins. Sickle cells or marked polycythemia can lower it. ESR remains valuable in selected conditions and for trends, but an elevated value is not automatically evidence of active disease.
Ferritin
Ferritin stores iron inside cells and circulates in small amounts. A low value strongly supports depleted iron stores in many settings. A high value is much less specific because ferritin is also a positive acute-phase reactant and may rise with liver injury, metabolic dysfunction, infection, autoimmune disease, kidney disease, cancer, or iron overload.
The ferritin blood test must be interpreted with transferrin saturation and the blood count. Inflammation can raise ferritin enough to conceal absolute iron deficiency or contribute to functional iron restriction. Very high ferritin can occur in severe hyperinflammatory disorders, but no single threshold makes one diagnosis.
Fibrinogen
Fibrinogen is clotting factor I. Thrombin converts it to fibrin, which forms the structural mesh of a blood clot. The liver also increases fibrinogen during inflammation, and the rise contributes to a higher ESR. Pregnancy, smoking, estrogen exposure, metabolic disease, infection, and tissue injury can elevate it.
The fibrinogen blood test can connect coagulation and inflammatory assessment, but a high value does not diagnose a blood clot. In severe consumption such as disseminated intravascular coagulation, fibrinogen may fall; serial decline can matter even when the number is not yet below the standard range.
| Marker | What it primarily reflects | Major confounders | Typical strength |
|---|---|---|---|
| CRP | Rapid hepatic acute-phase response | Many infections, injuries, inflammatory and malignant conditions | Fast trend monitoring |
| ESR | Red-cell settling affected by plasma proteins | Age, anemia, pregnancy, kidney disease, immunoglobulins, red-cell shape | Slower inflammatory context |
| Ferritin | Iron storage plus acute-phase response | Liver disease, iron therapy, metabolic disease, inflammation | Iron assessment when interpreted with other iron tests |
| Fibrinogen | Clotting substrate plus acute-phase response | Pregnancy, smoking, estrogen, coagulation consumption | Coagulation-inflammatory overlap |
How to Interpret Common Result Patterns
Panels are most informative when the markers are interpreted together with timing and clinical context. Agreement increases confidence that a systemic acute-phase response is present, while disagreement can reveal confounders or different kinetics.
CRP and ESR Both High
This pattern supports systemic inflammation but remains nonspecific. Infection, active autoimmune disease, major tissue injury, and some cancers are possible. The degree and trend matter. A rapid fall in CRP with clinical improvement can occur while ESR remains high for weeks. Very high ESR may also be driven by anemia or increased immunoglobulins.
High CRP With Normal ESR
Early acute inflammation is one explanation because CRP rises faster. Tissue injury, recent surgery, and some infections may produce this pattern. ESR may remain normal because the inflammatory response is mild, red-cell factors counteract sedimentation, or not enough time has passed. A normal ESR should not overrule a strongly suggestive clinical picture.
High ESR With Normal CRP
The ESR may be elevated by age, anemia, pregnancy, kidney disease, or monoclonal and polyclonal immunoglobulins. It can also remain high after an inflammatory episode has resolved. Some diseases, including certain lupus presentations, may produce a muted CRP response. The pattern calls for review of the blood count, protein studies, kidney function, symptoms, and prior results rather than assuming active infection.
High Ferritin With High CRP or ESR
Inflammation is likely contributing to ferritin. This does not establish whether iron stores are adequate. Low transferrin saturation, anemia, and chronic inflammatory disease may indicate iron restriction or combined iron deficiency. Liver enzymes, metabolic factors, transfusion history, and alcohol exposure also need review.
High Ferritin With Normal Inflammatory Markers
Possible explanations include iron overload, fatty liver or other liver injury, alcohol exposure, metabolic dysfunction, recent resolved inflammation, or a condition that does not elevate CRP or ESR strongly. Transferrin saturation helps separate common inflammatory-metabolic patterns from likely iron loading. A single normal CRP cannot eliminate chronic or localized inflammation.
High Fibrinogen and ESR
Because fibrinogen promotes red-cell aggregation, these results often rise together. Pregnancy, infection, smoking, metabolic inflammation, and autoimmune disease can create the pattern. It does not prove thrombosis. If clot symptoms are present, clinical probability, D-dimer when appropriate, and imaging are used instead.
All Markers Normal
Normal values make a major systemic acute-phase response less likely at that moment, but they do not rule out localized inflammation, intermittent disease, early illness, some autoimmune conditions, or symptoms with a noninflammatory cause. Repeating a panel without a new clinical reason may add little. The next step should be guided by the symptom pattern.
What the Tests Can Say About Chronic Inflammation
“Chronic inflammation” is a biological description, not a single diagnosis. It can refer to sustained immune activity from autoimmune disease, persistent infection, obesity-related metabolic signaling, smoking, chronic organ injury, periodontal disease, cancer, or another process. It is also used loosely in wellness marketing to explain fatigue, weight changes, pain, or brain fog without establishing a medical cause.
A persistently abnormal marker can support ongoing systemic inflammation, but persistence must be demonstrated with appropriately timed results and a compatible clinical picture. One mildly high CRP after a cold does not establish chronic inflammation. Repeatedly high CRP over months may justify evaluation, yet the value still cannot identify the source. ESR may stay high for noninflammatory reasons, and ferritin or fibrinogen can reflect their primary iron and coagulation roles.
Low-grade elevations are especially difficult to interpret because common factors influence them:
- Higher body fat and insulin resistance
- Smoking and chronic lung irritation
- Reduced physical activity
- Poor sleep or obstructive sleep apnea
- Chronic dental or periodontal disease
- Pregnancy and estrogen exposure
- Recent minor infection or injury
- Age, anemia, and kidney disease, particularly for ESR
These factors may be clinically important, but the panel is not a score of “inflammatory toxicity.” Nor can it determine which food caused symptoms, diagnose “leaky gut,” or prove that a supplement is working. Changes in hydration, illness timing, assay method, and regression toward the mean can make repeat values improve even without a specific intervention.
High-sensitivity CRP has a validated role in selected cardiovascular-risk discussions, but it should not be confused with a generic chronic-inflammation panel. Cardiovascular decisions use the person’s full risk profile, including cholesterol, blood pressure, diabetes, smoking, kidney function, family history, and prior disease. hs-CRP is usually measured when the person is clinically stable; acute infection can make it unsuitable for risk classification.
The best evidence that inflammation is improving is often disease-specific: fewer swollen joints, healing intestinal mucosa, resolution of fever, better imaging, controlled infection, or restored organ function. Laboratory trends support these outcomes rather than replacing them.
When a Panel Is Useful—and When It Is Not
A clinician may order multiple markers when the differential diagnosis includes inflammatory, infectious, hematologic, or metabolic processes and the markers offer genuinely different information. Examples include prolonged fever, suspected rheumatic disease, unexplained anemia, possible inflammatory bowel disease, chronic infection, postoperative complications, or monitoring a diagnosed condition.
CRP and ESR together can be useful when their different kinetics and confounders matter. Ferritin is appropriate when iron deficiency, iron overload, liver disease, adult-onset Still disease, macrophage activation, or chronic inflammatory anemia is part of the question. Fibrinogen is useful when coagulation status or severe systemic illness is relevant. The exact combination should follow the clinical hypothesis.
A panel is less useful as broad screening in an asymptomatic person. Nonspecific testing can discover mild abnormalities that do not predict disease and can lead to repeated panels, imaging, or specialist referrals without benefit. Testing is also unlikely to identify the cause of vague symptoms when history and basic evaluation point elsewhere.
Before ordering, useful questions include:
- What diagnosis or decision would an abnormal result change?
- Could a normal result safely reduce further testing?
- Is the marker validated for monitoring this specific condition?
- Are acute illness, pregnancy, anemia, kidney disease, or medicines likely to confound it?
- Would a more specific test answer the question better?
Panels should not be used to distinguish bacterial from viral infection by a single cutoff. CRP, ferritin, and fibrinogen overlap widely between causes. Procalcitonin can assist selected antibiotic decisions, particularly in defined hospital protocols, but it also needs clinical interpretation. Similarly, inflammatory markers cannot screen effectively for all cancers or autoimmune diseases.
Home-ordered panels deserve caution. Results without pretest probability, examination, or a plan for follow-up can create anxiety. A qualified clinician can help decide whether a borderline result needs repeat testing, focused investigation, or no action.
Next Tests, Monitoring, and Treatment Decisions
When a panel is abnormal, the next step is not automatically a larger inflammatory panel. Clinicians first confirm timing, severity, symptoms, and whether the result is new. A repeat after recovery may be appropriate for a mild elevation found during a known acute illness. Markedly abnormal values or concerning symptoms prompt faster evaluation.
Common foundational tests include a complete blood count, kidney and liver panels, urinalysis, and targeted imaging or microbiology. Further tests should follow clues:
- Transferrin saturation and iron studies for abnormal ferritin or anemia
- Autoantibodies only when symptoms and examination suggest a particular rheumatic disease
- Blood cultures or other infection testing when fever and clinical severity support it
- Serum protein electrophoresis for unexplained high ESR, total protein, anemia, kidney dysfunction, or related features
- Stool calprotectin for appropriate chronic gastrointestinal symptoms
- D-dimer and imaging only within a validated pathway for suspected venous thromboembolism
Monitoring frequency depends on the disease and marker. CRP can be repeated over short intervals in acute illness when the trend affects management. ESR is usually less useful for day-to-day change. Ferritin may be monitored during iron therapy or iron-overload treatment, but inflammation can distort the trend. Fibrinogen may be repeated frequently in bleeding or DIC and much less often for a stable outpatient elevation.
Treatment is never based on the phrase “inflammation is high” alone. Infection, autoimmune disease, iron deficiency, liver disease, metabolic dysfunction, and coagulation disorders have different therapies. Anti-inflammatory drugs, corticosteroids, antibiotics, aspirin, or anticoagulants can cause harm when taken without a defined indication.
General measures such as not smoking, regular activity, adequate sleep, dental care, vaccination, and evidence-based management of weight, blood pressure, glucose, and lipids improve health and may reduce low-grade inflammatory burden. They should be pursued for their established benefits, not as a promise to normalize every marker. Extreme elimination diets and unregulated supplements can create deficiencies or interact with medicines.
Warning Signs That Need Prompt Medical Care
Laboratory panels should never delay care for severe symptoms. Seek urgent assessment for difficulty breathing, chest pain, new confusion, fainting, signs of stroke, a rapidly spreading rash, severe abdominal pain, persistent high fever with deterioration, uncontrolled bleeding, or signs of sepsis such as low blood pressure, rapid breathing, and altered alertness.
Prompt medical review is also appropriate for unexplained weight loss, drenching night sweats, persistent fever, swollen joints, new weakness, jaundice, dark urine, worsening anemia, very high ferritin, ESR above 100 mm/hr, or a rapidly rising CRP. These findings do not establish one diagnosis, but they increase the need for a focused evaluation.
In contrast, a small isolated elevation in a person recovering from a minor infection is often handled with routine follow-up. The number should be interpreted in proportion to symptoms and risk. The purpose of an inflammatory marker panel is to sharpen clinical reasoning—not to turn nonspecific proteins into a stand-alone diagnosis of chronic inflammation.
References
- Inflammatory Markers 2025
- C-Reactive Protein (CRP) Test 2024
- Erythrocyte Sedimentation Rate (ESR) 2024
- Ferritin Blood Test 2024
- Fibrinogen Blood Test 2025
- Complete Blood Count (CBC) 2024
Disclaimer
This article provides general education and cannot diagnose the cause of abnormal inflammatory markers or persistent symptoms. Reference ranges, testing combinations, and monitoring strategies vary, and results must be interpreted with medical history, examination, and condition-specific tests. Seek urgent care for severe symptoms even if a recent panel was normal.