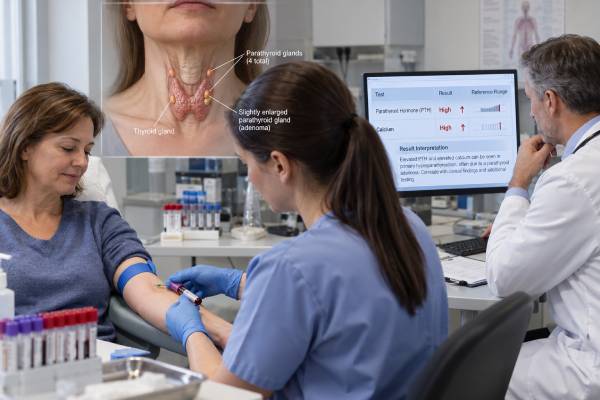
A parathyroid hormone (PTH) blood test measures the hormone that helps regulate calcium and phosphorus in the body. It is commonly used to investigate high calcium, low calcium, and suspected parathyroid disease. Although PTH is sometimes called a “tumor marker” in the context of parathyroid tumors, it is not a cancer-specific test. Most people with primary hyperparathyroidism have a benign parathyroid adenoma or multigland disease, not parathyroid cancer. The most useful interpretation comes from reading PTH together with the blood calcium level. High calcium with a PTH that is high—or even “normal” when it should be suppressed—supports PTH-dependent hypercalcemia. Very high calcium and markedly elevated PTH can increase concern for parathyroid carcinoma when other clinical features are present, but no PTH cutoff proves malignancy. Kidney function, vitamin D, magnesium, phosphorus, medications, urinary calcium, imaging, and sometimes pathology are needed to determine the cause.
- Most important pairing: PTH should be interpreted with calcium; the same PTH value can mean different things at different calcium levels.
- Primary hyperparathyroidism: Usually shows high calcium with high or inappropriately normal PTH and is most often caused by a benign adenoma.
- Parathyroid cancer: Often causes much more severe hypercalcemia and marked PTH elevation, but laboratory values alone cannot confirm carcinoma.
- High PTH with normal or low calcium: Often reflects secondary hyperparathyroidism from vitamin D deficiency, kidney disease, low calcium intake, or malabsorption.
- Typical adult range: One major laboratory uses 15–65 pg/mL, but the reference interval is assay-specific and the patient’s own report should be used.
Table of Contents
- What the PTH Blood Test Measures
- How to Interpret PTH and Calcium Together
- Common Causes of High PTH
- PTH in Parathyroid Adenoma and Parathyroid Cancer
- PTH Reference Range and Test Preparation
- Other Tests Used With PTH
- What Happens After an Abnormal Result
What the PTH Blood Test Measures
Parathyroid hormone is produced by the parathyroid glands, usually four small glands located behind the thyroid. PTH is one of the body’s main regulators of calcium balance. When ionized calcium falls, the parathyroid glands normally increase PTH secretion. PTH then acts on bone and kidneys and promotes activation of vitamin D, helping raise the calcium concentration back toward its normal range.
When calcium rises, normal parathyroid glands should reduce PTH secretion. This feedback relationship is the key to understanding the test. A PTH value that falls within the printed laboratory range may still be abnormal for the situation if calcium is high. For example, a PTH of 45 pg/mL may look numerically normal in a laboratory with a 15–65 pg/mL range, but if the patient has definite hypercalcemia, the expected normal response would be suppression of PTH. A nonsuppressed result can therefore support primary hyperparathyroidism.
Most modern blood tests measure “intact” PTH using antibodies directed at different parts of the molecule. PTH itself has a short biologic half-life, while inactive fragments last longer and are cleared partly by the kidneys. In advanced kidney disease, some fragments accumulate and may cross-react in intact PTH assays, which is one reason interpretation differs in chronic kidney disease.
PTH testing is commonly used for:
- Evaluating unexplained high calcium
- Diagnosing primary, secondary, or tertiary hyperparathyroidism
- Evaluating low calcium and suspected hypoparathyroidism
- Assessing mineral and bone disorders in chronic kidney disease
- Following patients after treatment for hyperparathyroidism
- Supporting evaluation of a suspected or known parathyroid tumor
Calling PTH a “tumor marker” can be misleading. A tumor marker usually implies an analyte that reflects a particular malignancy or tumor type. PTH is a normal human hormone, and most disorders that raise it are noncancerous. In parathyroid disease, it is better thought of as a functional hormone marker that shows whether parathyroid tissue is secreting hormone inappropriately.
How to Interpret PTH and Calcium Together
The calcium-PTH relationship often gives more information than either number alone.
| Calcium | PTH | Common interpretation |
|---|---|---|
| High | High or inappropriately normal | PTH-dependent hypercalcemia, commonly primary hyperparathyroidism |
| High | Low or suppressed | Look for non-parathyroid causes of hypercalcemia, including malignancy-related mechanisms |
| Normal or low | High | Often secondary hyperparathyroidism; consider vitamin D deficiency, kidney disease, low calcium intake, or malabsorption |
| Low | Low or inappropriately normal | Can suggest hypoparathyroidism, depending on magnesium and other factors |
High calcium with high or nonsuppressed PTH
This pattern is classic for primary hyperparathyroidism (PHPT). Current international guidelines define hypercalcemic PHPT by an elevated albumin-adjusted serum calcium with elevated or inappropriately normal intact PTH on repeated testing. The diagnosis is biochemical; imaging is used later to localize abnormal glands when surgery is being planned, not to prove PHPT in place of laboratory testing.
The most common cause is a single benign parathyroid adenoma. Some people have two abnormal glands or four-gland hyperplasia. Parathyroid carcinoma is rare.
Another important possibility is familial hypocalciuric hypercalcemia (FHH), an inherited condition in which lifelong mild hypercalcemia can coexist with normal or mildly high PTH. Urinary calcium and a calcium-to-creatinine clearance calculation may help distinguish FHH from PHPT, although overlap can occur.
High calcium with suppressed PTH
If calcium is high but PTH is appropriately low, the hypercalcemia is probably not being driven by the parathyroid glands. Causes include certain cancers, excess vitamin D activity, some medications, granulomatous disease, thyrotoxicosis, immobilization, and other conditions.
Some cancers produce parathyroid hormone-related peptide (PTHrP), which activates the same receptor as PTH but is measured by a different test. A PTHrP test for cancer-related high calcium may be appropriate when hypercalcemia is present with suppressed PTH and the clinical setting suggests humoral hypercalcemia of malignancy. PTH and PTHrP should not be treated as interchangeable results.
Normal calcium with high PTH
This pattern requires careful evaluation before labeling it normocalcemic primary hyperparathyroidism. Vitamin D deficiency, chronic kidney disease, low calcium intake, gastrointestinal malabsorption, and certain medications can stimulate PTH appropriately. These secondary causes should be identified or excluded first. Repeated total and sometimes ionized calcium measurements are also important because intermittent hypercalcemia can be missed by a single sample.
Common Causes of High PTH
An elevated PTH result has several possible explanations, and cancer is far from the most common.
Primary hyperparathyroidism occurs when one or more parathyroid glands secrete PTH without normal suppression by calcium. Most cases are sporadic and caused by a benign adenoma. PHPT can be discovered incidentally on routine blood work or present with kidney stones, osteoporosis, fractures, muscle weakness, fatigue, constipation, excessive urination, thirst, or neurocognitive complaints. Many patients have few obvious symptoms.
Secondary hyperparathyroidism is an appropriate response to a problem that lowers calcium availability or alters mineral metabolism. Common causes include vitamin D deficiency, chronic kidney disease, malabsorption, and inadequate calcium intake. In chronic kidney disease, phosphate retention, impaired vitamin D activation, skeletal resistance, and changes in calcium balance contribute to the rise in PTH.
Tertiary hyperparathyroidism develops when chronically stimulated parathyroid glands become autonomous, most often after longstanding severe secondary hyperparathyroidism in advanced kidney disease. PTH can be very high, and calcium may become elevated.
Medication effects and metabolic factors can also influence PTH. Lithium can shift the calcium-sensing set point and contribute to hyperparathyroidism. Antiresorptive treatments and some other drugs may raise PTH indirectly by changing calcium dynamics. Magnesium abnormalities can alter PTH secretion and action.
Parathyroid carcinoma can produce striking PTH elevations, but it accounts for less than about 1% of primary hyperparathyroidism in most series. Because benign PHPT is so much more common, a high PTH value by itself has poor specificity for cancer.
A useful practical rule is that the clinician should ask whether the PTH is appropriate for the calcium level before asking how far it is above the reference range. This prevents mild secondary elevations from being mistaken for a parathyroid tumor and prevents an “in-range” PTH from being dismissed when calcium is high.
PTH in Parathyroid Adenoma and Parathyroid Cancer
Most parathyroid tumors that cause primary hyperparathyroidism are benign adenomas. They can produce substantial PTH elevations and clinically important hypercalcemia without being malignant.
Parathyroid carcinoma is an exceptionally rare endocrine cancer. It usually produces PTH and often comes to attention because of the physiologic effects of severe hyperparathyroidism rather than because of a small asymptomatic neck lesion. Recent reviews describe markedly elevated calcium and PTH as common features.
Findings that may raise suspicion for carcinoma include:
- Severe hypercalcemia, especially when substantially above the upper reference limit
- Markedly elevated PTH, sometimes several-fold above the upper limit
- A palpable neck mass
- Hoarseness or recurrent laryngeal nerve dysfunction suggesting local invasion
- Very symptomatic bone and kidney disease
- A large, firm, irregular, or invasive-appearing parathyroid lesion on imaging or at surgery
- Persistent or recurrent hyperparathyroidism after prior surgery
- A personal or family history suggesting a CDC73-related syndrome such as hyperparathyroidism-jaw tumor syndrome
These features are warning signs, not diagnostic cutoffs. Benign adenomas can occasionally produce very high PTH and calcium, while some carcinomas present less dramatically.
Why PTH cannot diagnose parathyroid cancer
There is no validated PTH concentration that reliably separates adenoma from carcinoma. Imaging also cannot always make the distinction. Ultrasound, sestamibi imaging, 4D-CT, or fluorocholine PET may localize a lesion and show concerning features, but localization is not the same as proving malignancy.
Definitive parathyroid carcinoma diagnosis depends on tumor behavior and pathology, including evidence such as vascular invasion, lymphatic invasion, perineural invasion, invasion into adjacent structures, or metastasis. Molecular and immunohistochemical findings, including loss of parafibromin related to CDC73 abnormalities, can support risk assessment in selected tumors but do not reduce the diagnosis to one blood marker.
This distinction matters before surgery. If carcinoma is strongly suspected, the operative strategy may differ from a routine focused parathyroidectomy because complete initial en bloc resection offers the best chance for disease control. Patients with suspected carcinoma benefit from experienced endocrine surgeons and multidisciplinary care.
PTH remains valuable after treatment. If a functioning parathyroid carcinoma produced excessive PTH, falling PTH and calcium after successful surgery are expected. A later persistent rise, especially with recurrent hypercalcemia, can signal residual or recurrent functioning disease and prompt imaging. Because parathyroid carcinoma can recur years later, long-term biochemical follow-up is important.
PTH Reference Range and Test Preparation
Reference ranges differ by assay, age, laboratory population, and specimen type. Mayo Clinic Laboratories currently lists an adult serum intact PTH reference interval of 15–65 pg/mL for people age 18 and older. Pediatric ranges differ.
That interval should not be used as a universal “normal” range for every laboratory. Always compare the result with the range printed on the same report.
The test is usually a standard blood draw. At one major reference laboratory, a 12-hour fast is preferred but not required, and biotin-containing multivitamins or supplements are withheld for 12 hours before collection according to that laboratory’s instructions. Other laboratories may use different methods and preparation rules, so patients should follow the instructions they receive locally.
Calcium measurement needs equal attention
Total serum calcium can be influenced by albumin. Clinicians may use albumin-adjusted calcium or measure ionized calcium when the total calcium result is difficult to interpret. Repeating calcium and PTH is often appropriate before diagnosing a chronic disorder, particularly when abnormalities are mild.
PTH changes quickly in response to calcium. Differences in collection timing, acute illness, kidney function, supplements, and assay method can therefore affect comparisons over time. When monitoring a known condition, consistent laboratory methods and clinical context improve interpretation.
Kidney failure is a special case. PTH fragments accumulate, healthy-adult reference ranges do not apply in the same way, and nephrology guidelines use PTH together with calcium, phosphorus, alkaline phosphatase, vitamin D status, and the overall chronic kidney disease-mineral and bone disorder picture.
Other Tests Used With PTH
An abnormal PTH result is usually the beginning of interpretation, not the end. Common companion tests include:
- Total and/or ionized calcium: Defines whether the patient is hypercalcemic, normocalcemic, or hypocalcemic.
- Albumin: Helps interpret total calcium.
- Phosphorus: Often trends low in PTH-mediated hypercalcemia because PTH increases renal phosphate loss.
- Creatinine and estimated GFR: Identify kidney dysfunction that can raise PTH and change mineral metabolism.
- 25-hydroxyvitamin D: Vitamin D deficiency is a common cause of secondary PTH elevation and should be assessed in PHPT evaluation.
- Magnesium: Severe deficiency can impair PTH secretion and action.
- 24-hour urine calcium or calcium/creatinine clearance: Helps assess kidney stone risk and may help distinguish PHPT from FHH.
- Bone density testing: Evaluates skeletal effects of sustained PTH excess.
- Kidney imaging: Looks for nephrolithiasis or nephrocalcinosis when appropriate.
Once biochemical PHPT is established and surgery is planned, neck ultrasound, sestamibi-based imaging, 4D-CT, or other localization studies may be used. A negative localization study does not rule out PHPT because imaging is not the diagnostic test for the biochemical disorder.
During parathyroid surgery, intraoperative PTH can be measured because PTH has a short half-life. A substantial fall after removal of the abnormal gland can support that the hypersecreting tissue has been successfully removed. The exact protocol and cutoff depend on the surgical center.
If hypercalcemia is accompanied by suppressed PTH, the evaluation shifts away from parathyroid autonomy. PTHrP, vitamin D metabolites, serum or urine protein studies, imaging, and other tests are selected based on symptoms and suspected causes rather than ordered indiscriminately.
What Happens After an Abnormal Result
The appropriate next step depends on the calcium-PTH pattern and the severity of the abnormality.
For high calcium with high or nonsuppressed PTH, the clinician may repeat calcium and PTH, check albumin or ionized calcium, measure phosphorus, kidney function, vitamin D, and urinary calcium, and review medications. Once primary hyperparathyroidism is confirmed, the patient is evaluated for complications and for indications for parathyroid surgery.
For high PTH with normal or low calcium, the clinician usually looks for secondary causes first. Correcting vitamin D deficiency, addressing low calcium intake or malabsorption, and evaluating kidney disease may normalize or clarify the PTH pattern. Persistent high PTH with repeatedly normal total and ionized calcium after secondary causes are excluded may meet criteria for normocalcemic PHPT.
For very high calcium with markedly elevated PTH, especially with a neck mass, hoarseness, severe symptoms, or suspicious imaging, urgent specialist evaluation is appropriate because parathyroid carcinoma or severe benign PHPT may be present. The biochemical severity itself also matters: hypercalcemia can cause dehydration, kidney injury, arrhythmias, confusion, and neurologic deterioration regardless of whether the parathyroid lesion is benign or malignant.
Patients with suspected parathyroid cancer should generally be referred to an experienced endocrine surgery and endocrine oncology team. If surgery confirms carcinoma, follow-up usually includes serial calcium and PTH, clinical examination, and imaging when biochemical or clinical findings suggest recurrence.
Seek urgent medical care for confusion, severe weakness, repeated vomiting, inability to stay hydrated, fainting, significant heart-rhythm symptoms, or rapidly worsening illness in the setting of known severe hypercalcemia. The urgency is driven by the calcium-related clinical state, not by a particular PTH number.
Useful questions for the treating clinician include: Is my calcium truly high after albumin or ionized calcium is considered? Is my PTH appropriate for that calcium level? Could vitamin D deficiency or kidney disease explain the result? Do I need urine calcium testing? Is imaging being ordered to localize a confirmed parathyroid problem or to investigate something else? Are there features that make carcinoma a realistic concern, or is a benign adenoma much more likely?
References
- PTH2 – Overview: Parathyroid Hormone, Serum 2026 (Laboratory Reference)
- Evaluation and Management of Primary Hyperparathyroidism: Summary Statement and Guidelines from the Fifth International Workshop 2022 (Guideline)
- Primary hyperparathyroidism: from guidelines to outpatient clinic 2024 (Review)
- Diagnosis and Management of Parathyroid Carcinoma 2024 (Review)
- Parathyroid carcinoma: New insights 2025 (Review)
- Parathyroid Carcinoma: From Molecular Pathogenesis to Multidisciplinary Management 2026 (Review)
Disclaimer
This article provides general information about PTH testing and does not diagnose primary hyperparathyroidism, a parathyroid tumor, or parathyroid cancer. PTH must be interpreted with calcium, kidney function, vitamin D status, medications, symptoms, and the laboratory’s own reference interval. Severe hypercalcemia can be medically urgent even when the underlying parathyroid disorder is benign.