The PCA3 urine test measures prostate cancer gene 3 RNA shed from prostate cells into urine after the prostate is stimulated during a digital rectal examination. A higher PCA3 score is associated with a greater chance of finding prostate cancer on biopsy, while a lower score is associated with a lower chance. The best-known commercial assay, PROGENSA PCA3, was cleared for a narrow purpose: helping decide about repeat biopsy in men age 50 or older who already had at least one negative prostate biopsy but remained suspicious for cancer. Its historical decision point was 25, although many studies also evaluated thresholds such as 35. PCA3 is not a cancer diagnosis, does not reliably measure tumor aggressiveness, and does not replace PSA, MRI, or biopsy. Its role has also become smaller as prostate MRI and newer blood and urine biomarkers have entered practice. The FDA database now lists the PROGENSA PCA3 premarket approval as withdrawn in 2023, so current test availability and use depend on the laboratory and health system.
- What it measures: PCA3 testing measures prostate cancer-associated PCA3 RNA relative to PSA RNA in a first-catch urine sample collected after prostate stimulation.
- Score meaning: A higher score generally means a higher probability of a positive prostate biopsy; there is no score that proves cancer is present or absent.
- Historical cutoff: For the PROGENSA PCA3 assay, a score below 25 was associated with a decreased likelihood of a positive repeat biopsy.
- Main clinical use: PCA3 was developed mainly to refine the decision about repeat biopsy after a previous negative biopsy, not to replace biopsy.
- Current role: MRI and newer biomarkers often provide more clinically useful information about Grade Group 2 or higher cancer, so PCA3 is no longer a dominant prebiopsy test.
Table of Contents
- What PCA3 is and what the urine test measures
- How the PCA3 urine test is done
- PCA3 score ranges and result meaning
- PCA3 after a negative biopsy
- How PCA3 fits with PSA, MRI, and newer biomarkers
- Limitations and current clinical role
- What to do with a PCA3 result
What PCA3 is and what the urine test measures
PCA3 is a prostate-specific, non-protein-coding RNA that is markedly overexpressed in many prostate cancers. Unlike PSA, which is a protein made by both normal and cancerous prostate tissue, PCA3 is measured as RNA and was developed to improve cancer specificity when PSA alone leaves uncertainty.
The best-known assay calculates a PCA3 score using the amount of PCA3 RNA relative to PSA RNA in urine. PSA RNA serves as a reference for the amount of prostate-derived material in the sample. The laboratory applies a normalization factor to produce the final score.
This does not mean the PCA3 test measures blood PSA. It is a separate molecular urine assay. A person can have an elevated blood PSA and a low PCA3 score, or a modest PSA and a higher PCA3 score, because the two tests reflect different biology.
PCA3 became attractive because an elevated PSA level can result from benign prostate enlargement, inflammation, recent procedures, and cancer. A more prostate-cancer-associated signal could potentially help decide who actually needs another biopsy.
The test is still a risk-refinement tool. PCA3 RNA can be high without a subsequently positive biopsy, and a low score cannot rule out cancer. In particular, it cannot reliably exclude clinically significant Grade Group 2 or higher disease when other findings are concerning.
PCA3 also should not be confused with newer urine tests. The ExoDx Prostate test, for example, analyzes a different RNA signature in urinary exosomes and does not require a digital rectal examination before collection.
How the PCA3 urine test is done
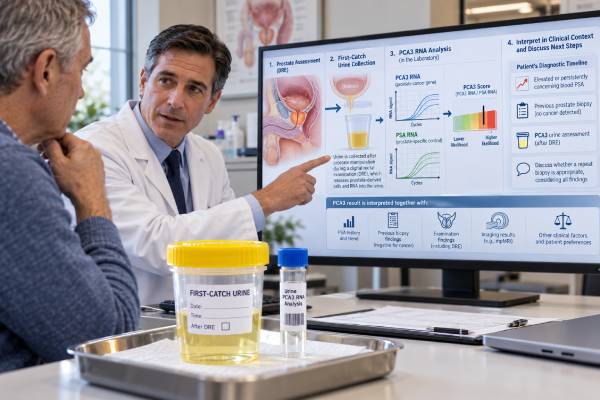
For the classic PROGENSA PCA3 method, urine is collected immediately after a clinician performs a digital rectal examination designed to move prostate cells and RNA into the urethra. The first portion of urine is important because it contains the highest concentration of prostate-derived material.
The traditional workflow is:
- The clinician performs several firm strokes over each prostate lobe during a digital rectal examination.
- The patient urinates soon afterward.
- The first-catch urine is collected in the appropriate container.
- The laboratory measures PCA3 RNA and PSA RNA using nucleic-acid amplification.
- A normalized PCA3 score is calculated and reported.
This collection method differs from a routine urinalysis. Simply providing a random urine specimen without the prescribed prostate stimulation may not be valid for an assay designed for post-DRE urine.
There is usually no fasting requirement. Medication changes generally are not made solely for PCA3 collection unless the treating clinician gives specific instructions. What matters most is following the laboratory’s specimen protocol, including timing after the examination, collection volume, transport, and storage.
The assay is noninvasive compared with biopsy, but the digital rectal examination may cause brief discomfort. The test itself does not sample tissue and therefore cannot provide a Gleason score, Grade Group, or histologic diagnosis.
Current availability deserves attention. The FDA originally approved the PROGENSA PCA3 assay in 2012 for a specific repeat-biopsy indication, but the FDA premarket-approval database lists that approval as withdrawn on April 12, 2023. This does not erase the scientific literature on PCA3, but it means patients should not assume that the historical FDA-approved product is currently available in the same form. Laboratories may offer other PCA3-containing tests under different regulatory pathways or as components of newer panels.
PCA3 score ranges and result meaning
A PCA3 score is a probability signal, not a normal-versus-abnormal cancer result. As the score rises, the likelihood of a positive biopsy generally rises, but the exact risk depends on the population, assay, cutoff, age, PSA, prior biopsy findings, MRI, and other clinical factors.
For the historical PROGENSA PCA3 indication, 25 was the key threshold. In the FDA validation study of men already recommended for repeat biopsy, scores below 25 were associated with a decreased likelihood of a positive biopsy. The labeling explicitly stated that biopsy was required for cancer diagnosis.
A useful way to understand common score language is:
| PCA3 result | Typical interpretation | Important caution |
|---|---|---|
| Below 25 | Historically associated with a lower likelihood of a positive repeat biopsy | Does not rule out cancer, including clinically significant cancer |
| 25 or higher | Historically supported greater concern about a positive repeat biopsy | Does not prove cancer is present |
| 35 or higher | A higher research cutoff used in many earlier studies | Not the FDA-labeled cutoff for the PROGENSA repeat-biopsy indication |
In the FDA clinical study used for the historical label, a score below 25 had a negative predictive value around 90% in that specific repeat-biopsy population. That number should not be carried over to every patient. Predictive value changes with the underlying prevalence of cancer, and contemporary practice now uses MRI and other biomarkers that were not part of the original pathway.
PCA3 is also less reliable for answering, “How aggressive is the cancer?” Research has found inconsistent relationships between PCA3 and Gleason grade, tumor volume, stage, or long-term outcomes. A very high PCA3 score should therefore not be interpreted as equivalent to a high-grade biopsy.
If a report uses another scale, cutoff, or multi-marker algorithm, follow the interpretation provided for that specific assay rather than applying the old PROGENSA threshold automatically.
PCA3 after a negative biopsy
PCA3’s classic use is helping refine repeat-biopsy decisions when a previous biopsy was negative but suspicion for prostate cancer remains. This is a difficult situation because a negative biopsy can be truly reassuring, but it can also miss a small or hard-to-reach tumor.
Persistent concern may come from:
- PSA that remains elevated or continues to rise.
- A suspicious prostate examination.
- A concerning MRI lesion.
- High PSA density.
- A strong family history or inherited risk.
- A prior biopsy that sampled the prostate incompletely.
- Certain abnormal pathology findings that require their own follow-up.
The historical PROGENSA indication was specifically for men 50 years or older with one or more previous negative biopsies for whom a urologist was already considering repeat biopsy based on standard clinical information. It was not designed as a general population screening test.
A lower PCA3 score could support delaying or avoiding another biopsy when the rest of the risk picture was reassuring. A higher score could add weight to repeating the biopsy. The decision still required clinical judgment because false-negative and false-positive results occur.
Modern repeat-biopsy practice increasingly starts with prostate MRI if a high-quality MRI has not already been performed. MRI can identify lesions for targeted sampling, while a biomarker estimates risk. A person with a low PCA3 result but a strongly suspicious MRI may still need biopsy.
Other options may also fit the repeat-biopsy question. A tissue epigenetic assay such as ConfirmMDx evaluates previously negative biopsy tissue for molecular changes near an occult cancer, whereas PCA3 evaluates RNA in urine. They therefore use different specimens and answer the repeat-biopsy question from different angles.
How PCA3 fits with PSA, MRI, and newer biomarkers
PCA3 should be interpreted as one part of a multivariable prostate cancer risk assessment, not as a replacement for PSA or MRI. Current guidelines emphasize the goal of detecting clinically significant cancer, generally Grade Group 2 or higher, while reducing unnecessary biopsy.
Blood PSA remains the starting point for many evaluations, but repeat PSA testing can be useful before escalating care because temporary elevations occur. The PSA pattern should be interpreted with age, prostate size, examination, medications, infections, and recent procedures.
A useful derivative is PSA density, which divides PSA by prostate volume. A large benign prostate can produce more PSA, so density can sometimes distinguish a size-related elevation from a more concerning pattern.
MRI adds an anatomic layer by showing suspicious lesions and helping guide targeted biopsy. Biomarkers add a statistical or molecular layer. Neither makes the others irrelevant.
The prebiopsy biomarker field has also evolved. Contemporary tests include the Prostate Health Index, 4Kscore, SelectMDx, ExoDx, MyProstateScore, and others. Many newer validation studies focus specifically on the detection of Grade Group 2 or higher disease and on how many unnecessary biopsies can be avoided while maintaining high sensitivity.
For example, SelectMDx urine testing uses a different gene-expression model, while the Prostate Health Index combines blood forms of PSA. A clinician may prefer one test over another based on local availability, prior biopsy status, MRI findings, evidence, cost, and whether the result would actually change the biopsy decision.
Ordering several overlapping biomarkers at once is rarely helpful. Their scores are not additive in a simple way, and combining them without a validated model can create more confusion rather than more certainty.
Another reason PCA3 has become less central is that the target of modern testing has changed. Earlier studies often focused on whether any prostate cancer would be found at biopsy. Current clinical decision-making places greater weight on detecting clinically significant cancer, commonly Grade Group 2 or higher, while avoiding diagnosis of small Grade Group 1 tumors that may never cause harm. A biomarker that predicts biopsy positivity is not automatically the best marker for that newer goal.
The sequence of testing also changes interpretation. A biomarker obtained before MRI is being used in a different population from the same biomarker obtained after a negative or equivocal MRI. Likewise, a man with a previous systematic biopsy but no MRI-targeted biopsy is not equivalent to someone whose suspicious MRI lesion was already adequately sampled. This “test pathway” effect is one reason published PCA3 performance numbers vary and why an isolated sensitivity, specificity, or cutoff should not be applied universally.
If PCA3 is offered today, the clinician should be able to explain what incremental information it adds beyond the patient’s MRI, PSA density, prior biopsy quality, and available contemporary biomarkers.
Limitations and current clinical role
The biggest limitation of PCA3 today is that its diagnostic performance is only moderate and its standalone clinical role has been overtaken by MRI and newer biomarkers in many settings. A 2025 systematic review of urine biomarkers found the PCA3 PROGENSA literature more extensive than that of several competitors, but described its sensitivity and specificity as underwhelming relative to newer approaches.
Other important limitations include:
- No cancer certainty: A high score does not establish cancer, and a low score does not exclude it.
- Limited aggressiveness information: PCA3 is better linked to biopsy positivity than to grade, metastasis, or mortality.
- Collection dependence: Classic testing requires correct post-DRE first-catch urine collection.
- Cutoff variability: Studies have used 25, 35, and other thresholds, complicating comparisons.
- Changing clinical pathways: MRI-targeted biopsy and newer biomarkers alter the baseline risk and decision process.
- Product availability: The original PROGENSA PCA3 FDA approval is listed as withdrawn in 2023.
- No role in treatment monitoring: PCA3 is not a standard marker for following response after prostate cancer treatment.
The test should also not be used as a reason to ignore strong clinical warning signs. A rapidly changing PSA, a suspicious MRI, abnormal examination, or substantial inherited risk can justify further evaluation despite a reassuring urine biomarker.
PCA3’s scientific importance remains substantial. It helped establish that prostate cancer-associated RNA in urine could provide clinically useful information and paved the way for more complex urinary molecular assays. Its current value is best understood in that historical and selective clinical context rather than as the default modern prostate cancer urine test.
What to do with a PCA3 result
The next step after a PCA3 result is to ask how much it changes the estimated need for biopsy when combined with the rest of the evidence. The number should never be acted on without knowing the assay, its intended use, and the patient’s baseline risk.
Useful questions for the urology visit include:
- Which PCA3 assay was used, and is its scoring system the same as the historical PROGENSA test?
- Was the urine collected according to the required post-DRE protocol?
- What was my latest PSA, and was an unexpected elevation repeated?
- What is my prostate volume and PSA density?
- Have I had a high-quality multiparametric MRI?
- Why was my previous biopsy negative, and was it systematic, MRI-targeted, or both?
- Does my PCA3 result meaningfully change the estimated chance of Grade Group 2 or higher cancer?
- Would another biomarker add information, or would it simply duplicate the same decision?
- If biopsy is deferred, what follow-up schedule will be used?
For someone with a low score and otherwise reassuring findings, shared decision-making may support continued PSA follow-up, MRI surveillance, or delayed biopsy. For someone with a higher score plus persistent PSA elevation or a suspicious lesion, repeat biopsy may remain appropriate.
The goal is not to chase a PCA3 number. The goal is to avoid unnecessary procedures without missing a cancer that is likely to matter. In contemporary care, that requires combining molecular risk with PSA trends, prostate size, MRI, prior pathology, family history, age, health, and personal preferences.
References
- The impact of urine biomarkers for prostate cancer detection-A systematic state of the art review. 2025 (Systematic Review)
- Blood- and urine-based biomarkers for the detection of clinically significant prostate cancer: a contemporary review 2025 (Review)
- Serum and Urine Biomarkers for Prostate Cancer: A Mini Review. 2025 (Review)
- Early Detection of Prostate Cancer: AUA/SUO Guideline Part II: Considerations for a Prostate Biopsy 2023 (Guideline)
- Accuracy of novel urinary biomarker tests in the diagnosis of prostate cancer: A systematic review and network meta-analysis. 2022 (Systematic Review)
- Premarket Approval (PMA) 2026
Disclaimer
PCA3 is a risk-assessment biomarker and cannot diagnose or exclude prostate cancer by itself. A biopsy decision should be made with a urologist using PSA, prior biopsy findings, MRI, examination, other risk factors, and the exact assay’s validated interpretation. The historical PROGENSA PCA3 approval status and test availability have changed, so patients should confirm what test is actually being offered.