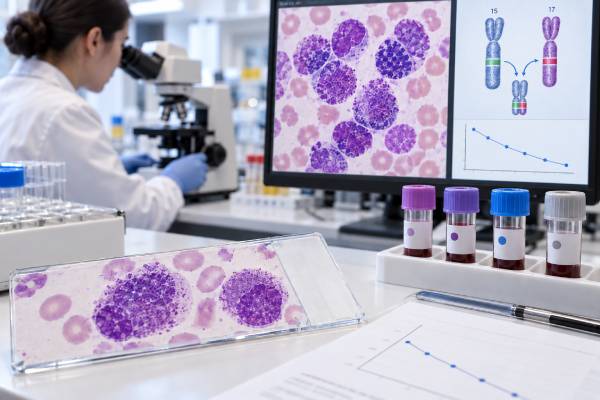
A PML-RARA fusion test detects the defining molecular abnormality of classic acute promyelocytic leukemia (APL), a medical emergency that can cause life-threatening bleeding early in its course. The fusion usually results from the chromosome translocation t(15;17), which joins the PML gene on chromosome 15 to RARA on chromosome 17. Detecting PML::RARA confirms the diagnosis in the appropriate clinical setting and identifies a leukemia that is highly sensitive to all-trans retinoic acid (ATRA) and arsenic trioxide (ATO). Because early hemorrhage can occur before complete laboratory confirmation, ATRA is generally started immediately when APL is strongly suspected rather than waiting for the final molecular result. After treatment begins, quantitative RT-PCR for the PML-RARA transcript can measure residual disease with far greater sensitivity than routine microscopy. The same marker therefore serves two distinct purposes: rapid diagnostic confirmation at presentation and highly sensitive molecular monitoring during and after therapy.
- A positive PML-RARA fusion result strongly supports classic APL and identifies the molecular target of ATRA and arsenic-based therapy.
- Suspected APL is an emergency: ATRA is usually started immediately on clinical suspicion because delaying treatment can increase fatal bleeding risk.
- RT-PCR or RT-qPCR detects the PML-RARA RNA transcript and is central for both diagnosis and measurable residual disease monitoring.
- A negative rapid test does not always end the evaluation if morphology and immunophenotype strongly suggest APL; rare RARA rearrangements and technical limitations must be considered.
- Persistent or recurrent PML-RARA positivity after therapy can indicate molecular residual disease or relapse before leukemia becomes obvious on routine blood counts.
Table of Contents
- What the PML-RARA Fusion Is
- Why PML-RARA Testing Is Urgent in Suspected APL
- How the Fusion Is Detected
- Positive, Negative, and Atypical Results
- How PML-RARA Changes Treatment
- PML-RARA for MRD Monitoring
- Follow-Up and Questions to Ask
What the PML-RARA Fusion Is
PML::RARA is an abnormal fusion gene created when genetic material from chromosomes 15 and 17 is rearranged. The classic event is written t(15;17)(q24;q21). It joins part of PML (promyelocytic leukemia) with RARA (retinoic acid receptor alpha), producing an abnormal fusion protein that disrupts normal retinoic-acid signaling and PML nuclear-body function.
The result is a block in maturation at the promyelocyte stage. Instead of developing into normal mature myeloid cells, abnormal promyelocytes accumulate in blood and bone marrow. These cells also contribute to a severe disturbance of coagulation and fibrinolysis, which explains why APL can present with bruising, mucosal bleeding, intracranial hemorrhage, pulmonary bleeding, or thrombosis.
PML-RARA is not simply one of many optional biomarkers in APL. It is the defining lesion in the vast majority of classic cases and is directly targeted by the treatments that transformed APL from one of the most dangerous leukemias into one of the most curable.
ATRA binds the altered retinoic-acid receptor component and helps release the differentiation block. Arsenic trioxide acts on the PML portion and promotes degradation of the fusion oncoprotein through complementary mechanisms. Together, these drugs can eradicate the leukemic clone in many patients without conventional chemotherapy in lower-risk disease.
The fusion transcript has several common breakpoint forms, often called bcr1, bcr2, and bcr3 or long, variant, and short isoforms. The exact isoform usually does not change the basic diagnosis, but identifying it at baseline is important because the laboratory needs a patient-specific detectable transcript for later molecular monitoring.
Unlike many solid-tumor gene fusions, PML-RARA is not mainly used to decide among several targeted options. Its presence establishes a distinct leukemia biology, triggers disease-specific emergency management, and creates a molecular marker that can be tracked to very low levels after treatment.
Why PML-RARA Testing Is Urgent in Suspected APL
APL is a hematologic emergency because early death can occur from hemorrhage before antileukemic therapy has time to work. The danger is greatest around diagnosis, when abnormal promyelocytes drive both procoagulant and hyperfibrinolytic activity. Low fibrinogen, thrombocytopenia, elevated D-dimer, prolonged clotting tests, and active bleeding may be present, but the coagulopathy can evolve quickly.
For that reason, clinicians do not generally wait for final molecular confirmation before starting ATRA when the blood smear, bone marrow, or immunophenotype strongly suggests APL. ATRA can rapidly begin reversing the underlying leukemic biology and is relatively safe to stop if testing later excludes APL.
At the same time, rapid PML-RARA confirmation is essential because treatment pathways for APL differ sharply from those for other forms of acute myeloid leukemia. A person with suspected APL may have hypergranular promyelocytes, bundles of Auer rods, or the microgranular variant with a high white blood cell count. Flow cytometry often shows a characteristic pattern, but morphology and immunophenotype alone are not enough to prove the fusion.
Supportive care begins in parallel. Platelets, cryoprecipitate or fibrinogen replacement, and plasma may be used aggressively to maintain hemostatic targets. Invasive procedures are minimized when possible until the coagulopathy is controlled. These measures are not a minor adjunct: reducing early hemorrhagic death is one of the most important goals in APL care.
A high white blood cell count at presentation is also used for risk stratification. Contemporary regimens commonly separate non-high-risk disease from high-risk APL using a white blood cell threshold of 10 × 10⁹/L. This risk group can influence the need for cytoreductive therapy in addition to ATRA and arsenic.
Because every hour can matter, many centers use a rapid assay such as FISH or a fast RT-PCR pathway while the full diagnostic workup continues.
How the Fusion Is Detected
Several laboratory methods can demonstrate PML-RARA, and they answer slightly different questions.
| Method | Main role | Important limitation |
|---|---|---|
| RT-PCR / RT-qPCR | Detects the fusion RNA; confirms diagnosis and enables sensitive MRD monitoring | Requires good-quality RNA and primers that cover the relevant transcript |
| FISH | Rapidly detects the PML/RARA rearrangement in cells | Less suitable than quantitative PCR for deep serial MRD measurement |
| Conventional cytogenetics | Shows t(15;17) and other chromosome findings | Slower and requires dividing cells; cryptic rearrangements can be missed |
| Immunofluorescence for PML | Can provide very rapid supportive evidence by showing an abnormal microspeckled PML pattern | Does not provide the same transcript information needed for molecular follow-up |
| RNA-based sequencing | Can identify unusual or cryptic RARA fusions when standard assays are inconclusive | Turnaround may be too slow for the initial emergency decision |
RT-PCR and RT-qPCR
Reverse-transcription PCR first converts RNA into complementary DNA, then amplifies the fusion sequence. At diagnosis, it confirms that a PML-RARA transcript is present and usually identifies the breakpoint type. Quantitative real-time PCR can then measure how much transcript remains during therapy.
The assay uses a control gene to verify that the sample contains adequate amplifiable RNA. A report can therefore distinguish a truly negative result from a technically poor specimen. Bone marrow is generally more sensitive than peripheral blood for MRD, although blood can be useful for some monitoring schedules.
FISH and cytogenetics
FISH uses fluorescent probes near PML and RARA and can return a rapid answer. Conventional chromosome analysis shows the t(15;17) visually and can identify additional chromosomal abnormalities. However, a small minority of PML-RARA cases are cryptic, meaning the fusion exists without an obvious classic translocation on routine karyotyping. Molecular methods remain important when morphology is convincing but chromosomes appear normal.
A separate PML-RARA MRD test focuses on the highly sensitive follow-up role after the diagnostic fusion has been established.
Positive, Negative, and Atypical Results
A positive PML-RARA result at diagnosis confirms the defining molecular lesion of classic APL when the clinical and pathologic findings fit. The report may state the transcript isoform and provide a baseline quantitative level. That baseline establishes the molecular target to follow later.
A negative result needs context. If morphology, flow cytometry, and coagulation findings do not strongly suggest APL, a negative PML-RARA assay can redirect the workup toward other AML subtypes. If the picture is highly suggestive, however, clinicians should consider technical failure, an uncommon breakpoint not covered by the assay, a cryptic rearrangement, or a rare RARA, RARB, or RARG fusion that mimics APL.
Variant acute leukemias can look like APL under the microscope but may respond differently to ATRA or arsenic. Examples of alternative RARA partners include ZBTB16 (formerly PLZF) and other rare genes. These cases require precise fusion identification because assuming that every APL-like morphology is PML-RARA-positive can lead to ineffective therapy.
An indeterminate result can occur if RNA quality is poor or too few leukemic cells are present. At initial diagnosis, leukemic burden is usually high, so an indeterminate result often prompts urgent repeat or orthogonal testing rather than watchful waiting.
During remission, interpretation changes. A very low positive RT-qPCR result can represent measurable residual disease, but laboratories use standardized thresholds, replicate testing, control-gene quality, and serial trends to avoid overreacting to technical noise. A newly positive result after prior molecular negativity generally needs prompt confirmation on a new sample according to the treating protocol.
The most clinically important post-treatment endpoint is molecular remission, meaning PML-RARA is no longer detectable at the required sensitivity after consolidation. Persistent positivity at that stage is much more concerning than positivity early during induction, when transcripts often remain detectable despite an eventual successful response.
How PML-RARA Changes Treatment
PML-RARA is unusual because the molecular diagnosis leads directly to disease-specific treatment. ATRA and ATO both target the fusion-driven biology and have produced cure rates above 90% in many modern series when early deaths are prevented.
For non-high-risk APL, commonly defined by presenting white blood cells at or below 10 × 10⁹/L, ATRA plus ATO is a widely used frontline approach. This avoids much of the myelosuppression and late toxicity associated with conventional cytotoxic chemotherapy.
For high-risk APL, additional cytoreduction is often added because leukocytosis increases complications and relapse risk. Depending on guideline and protocol, this can involve an anthracycline, gemtuzumab ozogamicin, or other risk-adapted therapy alongside ATRA and ATO.
Two complications deserve particular attention:
- Differentiation syndrome can occur after ATRA or ATO as leukemic cells mature and release inflammatory signals. Fever, weight gain, edema, low blood pressure, kidney dysfunction, and lung infiltrates or breathing difficulty can develop. Dexamethasone is started promptly when the syndrome is suspected, and severe cases may require temporary treatment interruption.
- Arsenic-related toxicity can include QT-interval prolongation, electrolyte abnormalities, liver-test elevations, peripheral neuropathy, and other effects. Potassium and magnesium are monitored and corrected, and electrocardiograms are used to reduce arrhythmia risk.
ATRA itself can cause headache, liver abnormalities, dry skin or mucosa, and pseudotumor cerebri, especially in younger patients. These toxicities are manageable in most cases but require active monitoring.
The remarkable treatment sensitivity also explains why rapid molecular diagnosis is so valuable. PML-RARA is not just a label attached after the fact; it identifies a leukemia for which the correct targeted therapy should begin at the moment the disease is suspected.
PML-RARA for MRD Monitoring
PML-RARA is one of the best-established molecular measurable residual disease markers in leukemia. RT-qPCR can detect leukemia far below the level visible by microscopy, often on the order of one leukemic cell among 10,000 to 100,000 or more normal cells depending on the validated assay.
The most important molecular checkpoint is typically after consolidation, when a patient should achieve molecular remission. A positive PCR during induction does not by itself indicate treatment failure because clearance of the transcript can lag behind morphologic remission. Acting too early on residual positivity can therefore expose a patient to unnecessary treatment changes.
Post-consolidation persistence is different. Confirmed molecular positivity at that point predicts a high risk of relapse and generally triggers additional evaluation and salvage planning. Molecular relapse can precede a fall in blood counts or visible marrow recurrence, creating an opportunity for preemptive treatment.
Monitoring schedules have become more individualized as modern ATRA-plus-ATO regimens have reduced relapse rates. Evidence suggests that prolonged frequent monitoring provides little additional value for many non-high-risk patients who achieve deep molecular remission. Higher-risk patients and those treated under protocols with greater relapse risk may receive serial marrow or blood PCR for a defined period.
Bone marrow has traditionally been considered the more sensitive specimen, particularly for confirming molecular remission. Peripheral blood is less invasive and can be sampled more often, but a negative blood test may not be as sensitive as a negative marrow test. The protocol should specify which specimen is expected at each milestone.
A rising transcript level is more informative than an isolated borderline signal. When molecular relapse is suspected, repeat testing should usually confirm the result before major treatment decisions, unless the clinical situation already shows overt relapse. Laboratories also need to use the same transcript target and standardized methodology over time so that serial values are comparable.
MRD is therefore not a simple “positive equals failure” test. Timing, specimen, assay sensitivity, and trend determine the meaning.
Follow-Up and Questions to Ask
After successful APL treatment, follow-up includes blood counts, assessment for treatment toxicity, and molecular monitoring according to the patient’s risk group and treatment protocol. The intensity of PCR surveillance may decrease over time because most relapses occur within the first few years and late molecular relapse is uncommon after modern therapy.
A history of APL also matters when new unexplained cytopenias develop later. These may reflect relapse, treatment effects, another marrow disorder, nutritional problems, infection, or an unrelated condition. PML-RARA testing can help distinguish relapse when clinically indicated.
Long-term follow-up also reviews late effects of therapy and general health rather than focusing only on the fusion test. Patients treated without conventional chemotherapy may have a different late-toxicity profile from those who received anthracyclines or other cytotoxic drugs, so survivorship care should reflect the actual regimen used.
Useful questions about a PML-RARA report include:
- Was PML-RARA confirmed by RT-PCR, FISH, cytogenetics, or more than one method?
- Which transcript isoform was identified at diagnosis?
- What was the white blood cell count at diagnosis, and is the disease considered high-risk or non-high-risk?
- Has ATRA already been started if APL is strongly suspected?
- What blood-product targets are being used to manage the coagulopathy?
- When will molecular remission be assessed after consolidation?
- Will MRD monitoring use bone marrow, blood, or both?
- If PCR becomes positive after remission, will a second sample confirm molecular relapse?
- If standard PML-RARA testing is negative despite APL-like morphology, should testing for an alternative RARA/RARB/RARG fusion be performed?
- What symptoms of differentiation syndrome or arsenic toxicity require immediate attention?
The most important message is that PML-RARA is both a diagnostic emergency marker and a highly sensitive follow-up marker. At presentation, it confirms a leukemia that needs immediate differentiation therapy and aggressive bleeding support. After treatment, the same fusion transcript provides a molecular fingerprint that can show whether the leukemic clone has been cleared or is returning before conventional tests become abnormal.
References
- Acute Promyelocytic Leukemia: Pathophysiology, Diagnosis and Clinical Management 2025 (Review)
- The treatment of acute promyelocytic leukemia in 2023: Paradigm, advances, and future directions 2023 (Review)
- Acute Promyelocytic Leukemia: Review of Complications Related to All-Trans Retinoic Acid and Arsenic Trioxide Therapy. 2024 (Review)
- The Coagulopathy of Acute Promyelocytic Leukemia: An Updated Review of Pathophysiology, Risk Stratification, and Clinical Management 2023 (Review)
- MRD in Acute Leukemias: Lessons Learned from Acute Promyelocytic Leukemia. 2024 (Review)
- Value of measurable residual disease monitoring in patients with acute promyelocytic leukemia in the era of frontline ‘chemotherapy-free’ therapy. 2021
Disclaimer
Suspected acute promyelocytic leukemia is a medical emergency because severe bleeding can occur early; urgent hematology evaluation and prompt treatment are required and should not be delayed for online information. PML-RARA results and MRD trends must be interpreted using the exact assay, specimen, treatment phase, and protocol. This article is educational and does not replace emergency or specialist medical care.