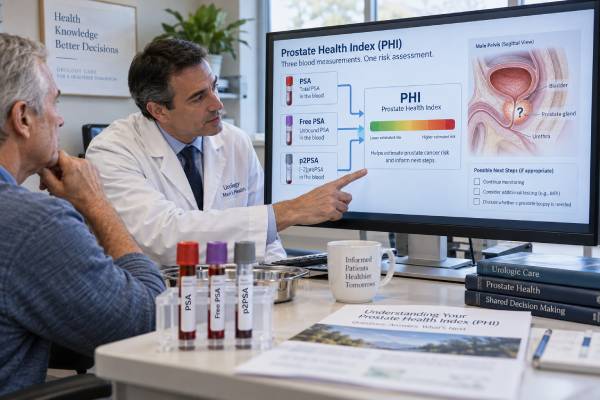
The Prostate Health Index (PHI, or phi) is a blood test that combines three prostate-specific antigen measurements—total PSA, free PSA, and [-2]proPSA (p2PSA)—into one score. Its main purpose is not to diagnose prostate cancer on its own. Instead, PHI helps estimate the likelihood that a man with an elevated or borderline PSA has clinically significant prostate cancer and may benefit from further evaluation. It can be especially useful when the next step is uncertain and a clinician is deciding whether to recommend prostate MRI, biopsy, continued observation, or another risk-assessment tool. A higher PHI generally means a higher probability of prostate cancer, but the meaning of any result depends on the laboratory method, PSA level, age, examination findings, family history, prior biopsy history, MRI findings, and other risk factors. Because benign prostate enlargement, inflammation, recent procedures, and normal biological variation can influence PSA-related measurements, PHI should be interpreted as part of a broader clinical assessment rather than as a stand-alone cancer test.
- PHI combines total PSA, free PSA, and p2PSA into a single prostate cancer risk score.
- A higher PHI is associated with a higher probability of prostate cancer, including clinically significant disease.
- PHI is most useful when PSA is elevated but the need for biopsy or MRI is not yet clear.
- PHI does not confirm or exclude cancer, and score cutoffs vary by assay, intended use, and clinical setting.
- Results should be interpreted with age, PSA trend, prostate examination, MRI, family history, and other risk factors.
Table of Contents
- What the PHI test measures
- How the PHI score is calculated
- Who may benefit from PHI testing
- PHI score ranges and what a high result means
- Factors that can affect PHI results
- PHI versus PSA, free PSA, MRI, and other tests
- What happens after a PHI result
What the PHI test measures
PHI is built from three related blood measurements. All three involve prostate-specific antigen, a protein produced by prostate tissue. PSA can be present in the blood in several molecular forms, and those forms provide somewhat different information about prostate cancer risk.
Total PSA is the overall amount of measurable PSA in the blood. It is the familiar PSA value used in prostate cancer screening and follow-up. Total PSA can rise because of prostate cancer, but also because of benign prostatic hyperplasia (BPH), prostatitis, urinary retention, age-related prostate growth, recent prostate manipulation, and other noncancerous causes. For that reason, total PSA is prostate-specific but not cancer-specific.
Free PSA is PSA that circulates without being bound to certain blood proteins. In men with a mildly or moderately elevated total PSA, a lower proportion of free PSA is generally associated with a higher probability of prostate cancer. The percentage of free PSA can therefore add information that total PSA alone does not provide.
p2PSA, also written as [-2]proPSA, is a precursor form of PSA that is more strongly associated with prostate cancer tissue than total PSA alone. PHI uses p2PSA together with free and total PSA to sharpen risk estimation.
The resulting score is intended to improve specificity. In practical terms, PHI can help separate some men whose elevated PSA is more likely to reflect benign prostate conditions from those whose pattern of PSA forms is more concerning for cancer. This can reduce unnecessary biopsies in selected patients while still identifying men who merit additional investigation.
PHI remains a risk-assessment test. A biopsy is required for tissue diagnosis, and MRI or other biomarkers may be used before biopsy depending on the clinical situation. A low PHI cannot guarantee that cancer is absent, and a high PHI cannot prove that cancer is present.
How the PHI score is calculated
The commonly used PHI formula is:
PHI = (p2PSA ÷ free PSA) × √total PSA
The laboratory performs this calculation using measurements obtained on a validated assay platform. Patients generally receive the final PHI value along with the component PSA results, although report formats differ among laboratories.
The formula matters because each component contributes to the risk estimate in a different way. A higher p2PSA relative to free PSA tends to increase PHI, while the square root of total PSA incorporates the overall PSA concentration without allowing it to dominate the score as strongly as a simple multiplication would.
PHI should not be recalculated from values produced by unrelated laboratories or different assay systems. PSA assays are not perfectly interchangeable, and manufacturers can use different calibrations, specimen requirements, reporting conventions, and validated cutoffs. The interpretation supplied with the laboratory report is therefore more important than a cutoff found on a general website.
Some reports place the score into risk categories. For example, one widely used manufacturer has published probability categories for certain men with PSA values in a defined range, with progressively higher cancer probability as PHI rises. Those percentages apply to the population and assay conditions in which they were established; they are not a personalized prediction for every patient.
A PHI score is also different from a pathology grade or cancer stage. It does not tell whether a tumor has spread, and it does not directly assign a Gleason score or Grade Group. Its role is to refine the probability of finding prostate cancer—particularly clinically significant disease—during subsequent evaluation.
Who may benefit from PHI testing
PHI is most often considered when total PSA is elevated enough to raise concern but not so informative that the next step is obvious. This is commonly called the diagnostic “gray zone.” The exact PSA interval depends on the assay, guideline, age, clinical context, and regulatory indication.
A clinician may consider PHI when a patient has a newly or persistently elevated PSA and is trying to decide whether prostate biopsy is warranted. It may also be used after a previous negative biopsy if concern remains, although prior testing, MRI findings, prostate volume, PSA density, and other biomarkers may influence whether PHI adds useful information.
The American Urological Association and Society of Urologic Oncology recommend selective use of adjunctive serum or urine biomarkers when the result is likely to change a biopsy decision. That principle is important: there is little value in ordering PHI if the result would not alter what happens next.
PHI may be particularly helpful when several features point in different directions. A man may have an elevated PSA but a reassuring digital rectal examination, no strong family history, and a desire to avoid an unnecessary biopsy. Another may have a similar PSA but a family history of aggressive prostate cancer or other risk factors that make even a moderately elevated PHI more important.
The test is not designed as a general screening test for every man regardless of PSA. It is also not appropriate as a substitute for clinical evaluation in someone with a suspicious prostate examination, concerning imaging, very high PSA, symptoms suggesting advanced disease, or other findings that already require prompt investigation.
Regulatory indications and laboratory eligibility criteria can be specific. Age, total PSA range, and digital rectal examination findings may be part of the intended-use definition for a particular commercial assay. Clinicians should therefore apply the test according to the validated platform and local guidance rather than treating PHI as universally interchangeable across all settings.
PHI score ranges and what a high result means
There is no single PHI number that means “cancer” and no universal value below which cancer is impossible. PHI is a continuous risk marker: as the score rises, the probability of prostate cancer generally rises as well.
In a commonly cited manufacturer interpretation for a defined group of men, PHI values are divided into categories such as below approximately 27, the upper 20s to mid-30s, the mid-30s to mid-50s, and 55 or higher. In that data set, the estimated probability of cancer on biopsy increased substantially across those categories. These values are useful for understanding the direction of risk, but they should not be copied onto results from another assay or population without checking the laboratory report.
Systematic-review evidence supports PHI as a useful discriminator. A 2022 meta-analysis found that PHI had meaningful diagnostic performance for prostate cancer and clinically significant prostate cancer, although it was not accurate enough to function as a stand-alone diagnostic test. More recent biomarker reviews likewise place PHI among tools that can refine the decision to pursue MRI or biopsy.
A high PHI means the combination of p2PSA, free PSA, and total PSA is more consistent with the pattern seen in men who have prostate cancer. It does not establish that a tumor is present. Some men with high scores have benign biopsy results, while some men with lower scores still have cancer.
A low PHI can support a more conservative approach when the rest of the risk assessment is also reassuring. That may include repeating PSA after an appropriate interval, monitoring PSA density or velocity, or using MRI rather than proceeding directly to biopsy. A low value should not override a strongly suspicious examination, MRI lesion, hereditary risk, or other significant clinical findings.
The most useful question is therefore not “Is my PHI normal?” but “How much does this PHI change my overall probability of clinically significant prostate cancer, and does that change what we should do next?”
Factors that can affect PHI results
Because PHI depends on PSA measurements, anything that changes PSA biology or measurement can affect the score. The size of the prostate is one important factor. BPH becomes more common with age and can increase total PSA even when cancer is absent.
Prostate inflammation or infection can also raise PSA. A patient with symptoms of prostatitis or urinary infection may need evaluation and, when appropriate, repeat testing after the acute problem has resolved. Urinary retention can produce another temporary increase.
Recent procedures involving the prostate or urinary tract may influence PSA. Prostate biopsy, catheterization in some circumstances, cystoscopy, or other manipulation can alter results. Ejaculation and vigorous cycling may cause modest temporary PSA changes in some men. Laboratories and clinicians differ in the pretest restrictions they recommend, so following the specific collection instructions is preferable to applying a rigid universal rule.
Medications matter as well. Drugs such as finasteride and dutasteride, which reduce prostate volume and are used for BPH or hair loss, can lower PSA substantially over time. Testosterone therapy and other hormonal interventions may also affect the clinical interpretation of PSA. Patients should tell the clinician about prescription drugs, over-the-counter products, and supplements, but should not stop medication solely to prepare for PHI unless the ordering clinician advises it.
Biological variation is another reason not to overreact to a single result. Prostate cancer guidelines commonly recommend repeating a newly elevated PSA before escalating to secondary biomarkers, imaging, or biopsy, because a meaningful proportion of elevated PSA results return to a lower level on repeat measurement.
Finally, assay differences matter. Total PSA, free PSA, and p2PSA should be measured using the validated combination required for the PHI calculation. Trending PHI over time is most interpretable when the same laboratory method is used.
PHI versus PSA, free PSA, MRI, and other tests
PHI is not a replacement for PSA; it is a refinement built from PSA-related measurements. Total PSA is usually the first blood test that triggers further risk assessment. When PSA is elevated, PHI may add specificity and help determine whether invasive testing is justified.
Percent free PSA is simpler and has long been used to refine risk in men with moderately elevated total PSA. PHI adds p2PSA and mathematically incorporates total PSA, which can improve discrimination compared with total PSA or free PSA alone in selected populations.
Multiparametric prostate MRI answers a different question. MRI looks for structural areas suspicious for clinically significant prostate cancer and can guide targeted biopsy. PHI estimates biochemical risk. The two can be complementary. A patient with an intermediate PHI may have MRI before biopsy, and the combination of MRI findings, PSA density, PHI, age, family history, and prior biopsy history can produce a more individualized decision.
Other blood and urine biomarkers are also available, including tests that use kallikreins, gene expression, or multiple molecular markers. No single test is best for every patient. Guidelines generally emphasize choosing a test that addresses the specific decision at hand and avoiding redundant biomarker testing that is unlikely to change management.
PHI also differs from risk calculators. Modern prostate cancer risk calculators can integrate age, PSA, digital rectal examination, family history, prior biopsy status, prostate volume, and sometimes MRI or biomarker results. PHI can become one input within that larger risk estimate.
The practical advantage of PHI is that it requires a blood sample and produces an objective numeric result. Its limitation is that even a well-performing biomarker cannot replace tissue diagnosis when the probability of significant cancer is high enough to warrant biopsy.
What happens after a PHI result
The next step depends on whether the result meaningfully raises or lowers the estimated risk of clinically significant prostate cancer.
If PHI is low and the overall assessment is reassuring, a clinician may recommend surveillance rather than immediate biopsy. Surveillance can include repeat PSA testing, review of PSA density if prostate volume is known, and reassessment of symptoms or examination findings. The interval depends on age, baseline PSA, risk factors, and the degree of concern.
If PHI is intermediate, MRI is often useful when it has not already been performed. MRI can identify lesions that merit targeted biopsy and can sometimes support continued observation when imaging is negative and the overall risk is low. A negative MRI does not completely exclude clinically significant cancer, so the decision still depends on the full risk profile.
If PHI is high, especially when accompanied by a rising PSA, abnormal digital rectal examination, high PSA density, suspicious MRI, strong family history, or a pathogenic hereditary cancer variant, biopsy may be more strongly considered. Prostate biopsy provides tissue that can confirm cancer and determine Grade Group, which is essential for treatment planning.
Patients should ask for the laboratory’s own interpretation of the score and whether the test was used within its validated PSA and age range. It is also reasonable to ask how the result changes the estimated chance of finding Grade Group 2 or higher disease, because avoiding both unnecessary biopsy and delayed diagnosis of clinically important cancer is the central goal.
PHI is most valuable when it improves a shared decision. It can reduce uncertainty, but it does not remove it. The safest interpretation combines the score with clinical history, repeated PSA when appropriate, prostate examination, imaging, and patient preferences about the tradeoffs of biopsy versus observation.
References
– Early Detection of Prostate Cancer: AUA/SUO Guideline Part I: Prostate Cancer Screening 2023 (guideline) – Early Detection of Prostate Cancer: AUA/SUO Guideline Part II: Considerations for a Prostate Biopsy 2023 (guideline) – Prostate health index (PHI) as a reliable biomarker for prostate cancer: a systematic review and meta-analysis 2022 (systematic review and meta-analysis) – Blood- and urine-based biomarkers for the detection of clinically significant prostate cancer: a contemporary review 2025 (review) – Advances in multiparametric magnetic resonance imaging combined with biomarkers for the diagnosis of high-grade prostate cancer 2024 (review) – Premarket Approval (PMA) 2026 (FDA device record)
Disclaimer
This article is for general educational purposes and does not diagnose prostate cancer or determine whether an individual should have a biopsy. PHI cutoffs and intended-use criteria vary by assay and laboratory, so results should be interpreted using the report from the performing laboratory and the patient’s full prostate cancer risk assessment. Decisions about MRI, biopsy, or follow-up should be made with a qualified clinician.