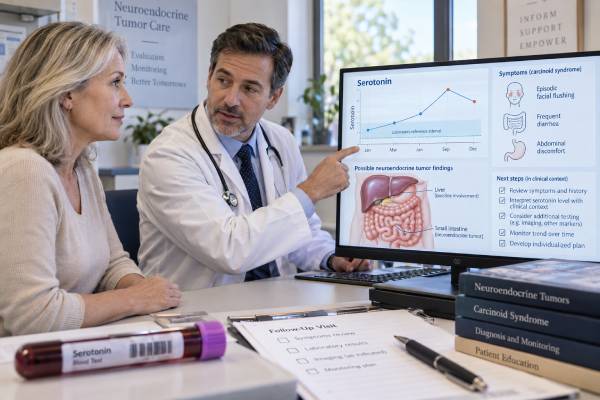
A serotonin blood test measures circulating serotonin and may be used as part of the evaluation of suspected carcinoid syndrome or a serotonin-producing neuroendocrine tumor (NET). Carcinoid syndrome can cause episodic flushing, chronic secretory diarrhea, wheezing, abdominal symptoms, and, over time, carcinoid heart disease. However, blood serotonin is not the preferred stand-alone test for most patients. Serotonin is largely stored in platelets, blood measurements can be affected by specimen type and platelet saturation, and some tumors release serotonin intermittently. Guidelines commonly favor 24-hour urinary 5-hydroxyindoleacetic acid (5-HIAA)—a serotonin metabolite—or validated plasma/serum 5-HIAA testing for biochemical assessment. A high blood serotonin level can support the diagnosis when symptoms and other findings fit, but it does not locate a tumor or prove cancer by itself. Food, medications, laboratory method, and the type of NET all influence interpretation. Serial results can sometimes help monitor disease, but 5-HIAA, imaging, symptoms, and treatment response are usually more informative.
- High blood serotonin can support a serotonin-producing NET or carcinoid syndrome but is not diagnostic by itself.
- 5-HIAA testing is generally more useful than whole-blood serotonin for diagnosis and follow-up of carcinoid syndrome.
- Reference ranges are laboratory-specific; one current whole-blood assay uses an upper limit near 330 ng/mL.
- Foods, medicines, platelet handling, and intermittent hormone secretion can affect biochemical testing.
- New severe flushing, breathing difficulty, marked blood-pressure changes, or cardiovascular instability in a patient with a NET may require urgent evaluation for carcinoid crisis.
Table of Contents
- What a serotonin blood test measures
- Serotonin, carcinoid syndrome, and neuroendocrine tumors
- What a high serotonin level means
- Why 5-HIAA is often preferred
- Test preparation, foods, medications, and other confounders
- Using serotonin and 5-HIAA for monitoring
- What happens after an abnormal result
What a serotonin blood test measures
Serotonin, also called 5-hydroxytryptamine or 5-HT, is a signaling chemical produced primarily by enterochromaffin cells in the gastrointestinal tract. It is best known for functions in the nervous system, but most of the body’s serotonin is outside the brain. In the circulation, platelets take up and store serotonin released from the gut.
A blood serotonin test may use whole blood, serum, or plasma depending on the laboratory. These specimen types are not interchangeable. Whole blood includes platelet serotonin and can produce much higher concentrations than platelet-poor plasma. The laboratory’s own reference interval must therefore be used.
One current whole-blood laboratory method reports an upper reference value of approximately 330 ng/mL. The same laboratory notes that substantially higher values can occur in carcinoid syndrome, but a single numerical threshold should not be applied to other methods.
Blood serotonin is usually ordered when there is clinical suspicion of a serotonin-secreting NET or when a clinician is trying to characterize a known NET. It is not a general blood test for cancer and is not used to screen healthy people for neuroendocrine tumors.
A high result cannot reveal where a tumor is located. Most classic serotonin-producing NETs arise in the midgut, particularly the small intestine, but serotonin secretion can occur in other NETs. Localization requires imaging and, when a lesion is found, pathology.
The result also does not measure brain serotonin and should not be used to diagnose depression, anxiety, or other psychiatric conditions. Peripheral serotonin biology is different from neurotransmitter activity within the central nervous system.
Serotonin, carcinoid syndrome, and neuroendocrine tumors
Neuroendocrine tumors arise from cells that can make peptide hormones or biogenic amines. Many NETs do not cause a hormone syndrome. When a tumor produces enough biologically active substances to create characteristic symptoms, it is called a functioning NET.
Carcinoid syndrome is most strongly associated with excessive serotonin and related mediators. Typical symptoms include recurrent flushing and chronic diarrhea. Some patients develop wheezing, abdominal cramping, or other vasomotor symptoms. Long-standing serotonin excess can injure heart valves, particularly on the right side of the heart, leading to carcinoid heart disease.
A gastrointestinal NET can produce serotonin without causing systemic carcinoid syndrome if the liver metabolizes the secreted hormones before they reach the general circulation. Classic syndrome often appears when a midgut NET has metastasized to the liver, allowing hormones to bypass first-pass metabolism. There are exceptions, including primary tumors that drain directly into the systemic circulation.
Not every episode of flushing or diarrhea is carcinoid syndrome. Menopause, medication effects, mast-cell disorders, infections, inflammatory bowel disease, pancreatic disorders, thyroid disease, and many other conditions can produce overlapping symptoms. This is why biochemical evidence and tumor imaging are important.
Similarly, not every NET produces serotonin. Pancreatic NETs may secrete insulin, gastrin, glucagon, vasoactive intestinal peptide, somatostatin, or no clinically active hormone. The biochemical workup should match the symptom pattern rather than ordering every possible hormone marker.
What a high serotonin level means
A high blood serotonin level is most meaningful when it is clearly above the laboratory’s reference range and occurs in a patient with symptoms or a known tumor compatible with serotonin secretion.
Marked elevations can support a diagnosis of carcinoid syndrome, particularly in metastatic midgut NETs. Some laboratory references note that whole-blood concentrations above several hundred ng/mL are suggestive in the correct clinical context and that levels can exceed 1,000 ng/mL in metastatic disease. These numbers are method-specific and should not be used as universal diagnostic cutoffs.
A mildly high result is less specific. Preanalytical factors, platelet count, diet, medication effects, and laboratory variation can contribute. If the value does not match the clinical picture, repeat testing or measurement of 5-HIAA may provide better confirmation.
A normal serotonin level does not exclude a NET or even carcinoid syndrome. Secretion can be intermittent, and some tumors preferentially produce serotonin precursors or other mediators. Whole-blood serotonin may also become less responsive at very high production rates because platelets can become saturated.
The degree of elevation does not directly stage the tumor. A high serotonin value can indicate substantial hormone production, but tumor burden and spread must be assessed with anatomic and functional imaging. Somatostatin receptor imaging, such as PET using an appropriate radiolabeled somatostatin analog, is frequently important for well-differentiated NETs.
When a patient already has a diagnosed serotonin-producing NET, a rising result may suggest increased secretory activity, but trends should be correlated with symptoms, 5-HIAA, imaging, and treatment changes.
Why 5-HIAA is often preferred
5-HIAA is the major metabolite produced when serotonin is broken down. Measuring 5-HIAA integrates serotonin production over time and avoids some of the problems created by platelet storage of serotonin itself.
The 2022 European Neuroendocrine Tumor Society guidance for carcinoid syndrome emphasizes 5-HIAA as a central biochemical marker. Traditionally, this has been measured in a 24-hour urine collection. More recent evidence supports validated serum or plasma 5-HIAA methods as convenient alternatives in some centers.
A 24-hour urine test has advantages and disadvantages. It captures secretion over an entire day, which helps with intermittent release, but accurate collection can be inconvenient. Missing urine, collecting for the wrong period, or improper storage can invalidate the result. Diet and medication restrictions may also be required.
Serum or plasma 5-HIAA avoids the collection burden, and a 2025 study found serum 5-HIAA useful for diagnosis and follow-up of carcinoid syndrome. However, the laboratory must use a validated method with its own cutoff, and kidney function may affect circulating metabolites.
Whole-blood serotonin can still be useful in selected situations, especially when obtained through a laboratory experienced with NET testing. But for serial monitoring, platelet saturation and specimen variability reduce its advantages. ENETS guidance specifically notes limitations of whole-blood serotonin for monitoring.
5-HIAA also has prognostic relevance. Persistently high serotonin metabolite exposure is associated with carcinoid heart disease risk. Patients with carcinoid syndrome may therefore require cardiac evaluation, including biomarkers and echocardiography, according to the degree of biochemical activity and clinical findings.
Test preparation, foods, medications, and other confounders
Preparation depends on whether the clinician orders blood serotonin, urine 5-HIAA, or blood 5-HIAA. Patients should follow the exact instructions from the performing laboratory because prohibited foods and medications differ by method.
Foods rich in serotonin or its precursors can interfere particularly with 5-HIAA testing. Commonly listed examples include bananas, pineapple, avocado, plums, eggplant, tomatoes, walnuts, and certain other fruits or nuts. The required avoidance period varies, and not every modern method is affected to the same degree.
Medications can cause false increases or decreases. Some cough medicines, pain medicines, psychiatric drugs, and other agents influence serotonin metabolism or analytical measurement. The medication list for older colorimetric assays is not necessarily the same as for modern chromatography or mass spectrometry.
Patients should not stop antidepressants or other prescription medicines on their own for a serotonin or 5-HIAA test. Abruptly stopping serotonergic medication can be harmful. The ordering clinician and laboratory should decide whether a drug needs to be withheld and whether it is safe to do so.
For whole-blood serotonin, platelet count and specimen handling matter because platelets store the analyte. The laboratory may require a specific tube and careful processing. Results from whole blood should not be compared directly with serum or plasma reference ranges.
Kidney impairment can alter the handling of serotonin metabolites and can complicate 5-HIAA interpretation. The clinician may therefore consider renal function when an unexpected biochemical result is found.
Using serotonin and 5-HIAA for monitoring
Biochemical monitoring is most informative when a marker was elevated before treatment. If a patient’s baseline 5-HIAA was clearly high and falls substantially after therapy, that supports reduced hormone production. If the marker was normal at diagnosis, repeating it may add less information.
Somatostatin analog therapy can reduce flushing and diarrhea and lower hormone secretion in many functioning NETs. Tumor-directed surgery, liver-directed therapy, peptide receptor radionuclide therapy, systemic therapy, or other treatments can also change marker levels depending on the disease setting.
Symptoms and biomarkers do not always move together. Diarrhea may persist because of bile-acid malabsorption, pancreatic insufficiency, bowel surgery, medication effects, or other conditions even after serotonin secretion improves. Conversely, biochemical levels can rise before symptoms become much worse.
For this reason, monitoring usually combines several domains: symptom frequency, body weight and hydration, 5-HIAA or another relevant marker, cross-sectional imaging, somatostatin receptor imaging when indicated, and assessment for carcinoid heart disease.
Cardiac surveillance is especially important in patients with sustained high serotonin exposure. Fibrotic injury of right-sided heart valves can progress even when symptoms are subtle. Shortness of breath, leg swelling, reduced exercise tolerance, or a new heart murmur should prompt assessment.
A change in blood serotonin alone should rarely trigger a major cancer-treatment decision without corroborating evidence. The most reliable follow-up compares like with like—same biomarker, same specimen type, and preferably the same laboratory method.
What happens after an abnormal result
If blood serotonin is high, the next step is usually confirmation that the finding fits a serotonin-producing NET. A clinician may order 24-hour urine 5-HIAA or a validated blood 5-HIAA test and review diet, medications, kidney function, platelet count, and specimen type.
If biochemical evidence and symptoms support carcinoid syndrome, imaging is used to locate and stage disease. CT or MRI evaluates anatomy, while somatostatin receptor PET can identify receptor-positive NET tissue throughout the body. Endoscopy or other targeted procedures may be needed depending on the suspected primary site.
Tissue biopsy confirms the diagnosis when feasible and determines tumor differentiation and grade. Pathology commonly reports markers of neuroendocrine differentiation and a proliferation index such as Ki-67, which helps classify the tumor and guide treatment.
Patients with established carcinoid syndrome may also be evaluated for carcinoid heart disease. The exact surveillance strategy depends on symptoms, 5-HIAA exposure, natriuretic peptide results, and specialist guidance.
A rare but important emergency is carcinoid crisis, which can involve profound flushing, bronchospasm, major blood-pressure changes, rapid heart rate, and cardiovascular instability. It may be triggered by surgery, anesthesia, tumor manipulation, or other stressors in susceptible patients. Acute severe symptoms require emergency care rather than waiting for outpatient marker testing.
For a nonurgent isolated high serotonin result, the safest approach is methodical: verify the specimen and preparation, confirm with a more established serotonin-metabolite test when appropriate, and integrate the result with symptoms and imaging. A blood serotonin number by itself should never be treated as a cancer diagnosis.
The relationship between serotonin excess and carcinoid heart disease is one reason biochemical follow-up matters even when flushing or diarrhea feels manageable. Chronic exposure can stimulate fibrotic changes on the tricuspid and pulmonary valves. Symptoms such as swelling in the legs, abdominal fluid accumulation, increasing breathlessness, or reduced exercise tolerance may appear only after significant valve dysfunction has developed. Patients with sustained biochemical activity may therefore undergo periodic cardiac assessment even when their gastrointestinal symptoms are stable.
Diarrhea severity also should not be judged only by the number of bowel movements. Large-volume watery stool can lead to dehydration, weight loss, electrolyte abnormalities, and kidney injury. In a known NET patient, a sudden major increase in diarrhea can reflect worsening hormone secretion, infection, treatment toxicity, bile-acid malabsorption, or pancreatic insufficiency. Distinguishing these causes is important because management differs.
For monitoring, clinicians often look for concordance among three streams of information: symptoms, biochemistry, and imaging. If 5-HIAA rises while scans remain stable and symptoms worsen, the biochemical change may prompt earlier reassessment. If imaging progresses while 5-HIAA remains unchanged, treatment decisions are still driven by the demonstrated tumor behavior. No single marker overrides the broader disease picture.
Patients collecting 24-hour urine should clarify exactly when the collection begins and ends and how the container must be stored. The first urine at the starting time is typically discarded, then all urine is collected for the next 24 hours, including the final specimen at the end time, according to laboratory instructions. Collection errors can produce more misleading results than small dietary variations.
Treatment can also change the meaning of a marker. Somatostatin analogs may lower serotonin production and 5-HIAA while leaving measurable tumor in place. Telotristat, used in selected patients with carcinoid-syndrome diarrhea that remains uncontrolled, directly reduces peripheral serotonin synthesis and can lower 5-HIAA. A falling marker after such treatment therefore reflects the pharmacologic effect as well as tumor biology. Imaging is still required to judge structural disease.
For the same reason, clinicians record the timing of marker collection relative to medication changes. Comparing a pre-treatment value with one obtained after a new serotonin-lowering drug without noting the intervention can create a misleading impression about tumor response.
References
– European Neuroendocrine Tumor Society (ENETS) 2022 Guidance Paper for Carcinoid Syndrome and Carcinoid Heart Disease 2022 (guidance paper) – Urinary 5-Hydroxyindolacetic Acid Measurements in Patients with Neuroendocrine Tumor-Related Carcinoid Syndrome: State of the Art 2023 (review) – Serum 5-Hydroxyindoleacetic Acid Measurements for the Diagnosis and Follow-up of Carcinoid Syndrome 2025 (diagnostic study) – What Is Carcinoid Syndrome? A Critical Appraisal of Its Proposed Mediators 2024 (review) – Biochemical Markers for Neuroendocrine Tumors: Traditional Circulating Markers and Recent Development—A Comprehensive Review 2024 (review) – SERWB – Overview: Serotonin, Blood 2026 (laboratory reference)
Disclaimer
This article is for general education and does not diagnose carcinoid syndrome or a neuroendocrine tumor. Serotonin and 5-HIAA reference ranges, preparation requirements, and medication restrictions vary by laboratory, and prescription drugs should never be stopped without medical guidance. Severe flushing with breathing difficulty, major blood-pressure changes, fainting, or cardiovascular instability requires urgent medical evaluation.