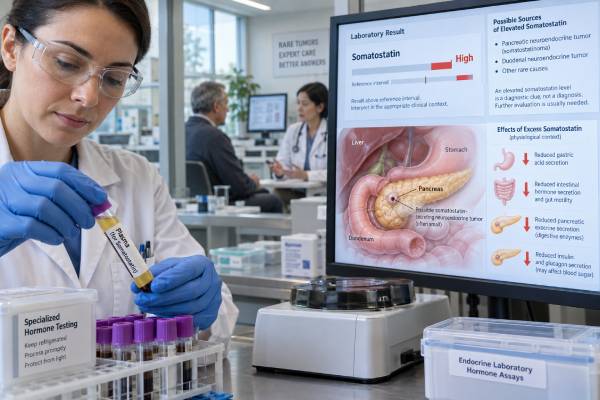
A somatostatin blood test measures the hormone somatostatin and is mainly used when a rare functioning neuroendocrine tumor called a somatostatinoma is suspected. Somatostatin normally acts as a broad inhibitory hormone, reducing the release of insulin, glucagon, growth hormone, gastrointestinal hormones, and digestive secretions. A tumor that releases excessive somatostatin can therefore produce a characteristic but often incomplete syndrome that includes diabetes or high glucose, diarrhea or fatty stools, gallstones, weight loss, and reduced stomach acid. Somatostatinoma is extremely rare, and many tumors that stain for somatostatin on pathology do not cause the full hormone syndrome. A high fasting blood somatostatin level supports the diagnosis when symptoms and imaging are compatible, but the test does not locate or stage a tumor. Sample handling is technically demanding, reference ranges are assay-specific, and other clinical conditions may influence results. Diagnosis normally requires biochemical evidence plus imaging and, when possible, tissue pathology.
- Somatostatin testing is used for suspected functioning somatostatinoma, not for general cancer screening.
- Classic symptoms include diabetes or high glucose, diarrhea or steatorrhea, gallstones, and weight loss, but many patients do not have the complete syndrome.
- Somatostatin reference intervals are laboratory-specific; one current assay uses an upper reference value of 25 pg/mL.
- Fasting and rapid specimen processing are often required because peptide-hormone measurements are sensitive to collection conditions.
- A high level supports hormone secretion but imaging and pathology are needed to confirm and stage a neuroendocrine tumor.
Table of Contents
- What somatostatin is and what the test measures
- Somatostatinoma and the hormone-excess syndrome
- What a high somatostatin level means
- Fasting, specimen handling, and test preparation
- How somatostatinoma is diagnosed
- Treatment and monitoring
- Important limitations and when to seek care
What somatostatin is and what the test measures
Somatostatin is a peptide hormone produced in several parts of the body, including the hypothalamus, pancreas, and gastrointestinal tract. It acts mainly as an inhibitor. In the pancreas, delta cells release somatostatin to restrain insulin and glucagon secretion. In the digestive system, it decreases gastrointestinal hormone release, slows some digestive processes, and reduces exocrine secretions.
A blood somatostatin test measures circulating hormone, usually in plasma. Because concentrations are low and the peptide is vulnerable to degradation, laboratories often require strict handling. The sample may need to be collected into a specified tube, chilled, separated rapidly, and frozen before transport.
The test is not useful as a broad screening marker for neuroendocrine tumors. Most NETs do not secrete enough somatostatin to cause a measurable syndrome, and somatostatinoma is one of the rarest functioning pancreatic or duodenal NETs.
A current reference from Mayo Clinic Laboratories lists a fasting plasma reference interval up to 25 pg/mL for its method. Other laboratories may use different methods, units, and limits. The result should therefore be judged only against the range printed on the same report.
Somatostatin testing also should not be confused with somatostatin receptor imaging. Receptor PET or scintigraphy detects tumor cells that express somatostatin receptors. A tumor can express those receptors even if the blood somatostatin level is normal. Similarly, somatostatin analog medications such as octreotide and lanreotide mimic hormone effects but are not the same as measuring endogenous somatostatin.
Somatostatinoma and the hormone-excess syndrome
Somatostatinoma is a neuroendocrine neoplasm that produces somatostatin. Most clinically functioning tumors arise in the pancreas or duodenum, although their presentation can differ by site.
The classic somatostatinoma syndrome reflects excessive inhibition of several normal digestive and endocrine pathways. Suppression of insulin contributes to glucose intolerance or diabetes. Inhibition of pancreatic and gastrointestinal secretions can cause diarrhea, fat malabsorption, and steatorrhea. Reduced gallbladder contraction can promote gallstones. Patients may lose weight because of malabsorption, reduced intake, or the cancer itself.
Other features can include abdominal pain, nausea, anemia, or low stomach acid. The complete textbook combination is uncommon. Symptoms may be vague for months or years, and many somatostatin-producing tumors are discovered because of a mass, obstruction, gastrointestinal bleeding, jaundice, or imaging rather than because the full hormone syndrome was recognized.
An important distinction is that somatostatin-positive pathology is not automatically somatostatinoma syndrome. Pathologists may identify somatostatin expression in a tumor without the patient having clinically meaningful hormone excess. The term functioning somatostatinoma is most useful when elevated circulating hormone is paired with a compatible syndrome.
Duodenal tumors are sometimes associated with genetic syndromes such as neurofibromatosis type 1. Pancreatic neuroendocrine tumors can also occur in inherited syndromes, including multiple endocrine neoplasia type 1, although the exact association depends on tumor type and family history.
What a high somatostatin level means
A clearly elevated fasting somatostatin level in a patient with diabetes or hyperglycemia, unexplained steatorrhea or diarrhea, gallstones, weight loss, and a suspected pancreatic or duodenal mass raises concern for a functioning somatostatinoma.
There is no universal numerical cutoff that proves the diagnosis. Some reviews describe somatostatinoma as a syndrome with a fasting hormone concentration several times the upper limit of normal, but assay differences make a fold-elevation more useful concept than copying a single value from one laboratory.
The magnitude of elevation does not reliably determine tumor size or stage. A small functioning tumor can produce symptoms, while a larger NET may release little active hormone. Conversely, a very high value can reflect substantial secretion but still cannot show whether disease has reached lymph nodes or the liver.
A normal result makes an actively functioning somatostatinoma less likely, particularly if the test was collected correctly, but it does not exclude a nonfunctioning NET. Some tumors release hormone intermittently, and a poorly handled peptide specimen can also produce falsely low values.
Unexpected elevations should be reviewed with the laboratory. Peptide-hormone immunoassays can be affected by analytical interference, and the clinical context matters. A result that is only slightly above range in an asymptomatic person is very different from a marked elevation in someone with the typical syndrome and an imaging abnormality.
The test is most informative when ordered to answer a specific clinical question rather than as part of an indiscriminate “tumor marker panel.”
Fasting, specimen handling, and test preparation
Somatostatin is commonly measured after an overnight fast. One major reference laboratory instructs patients to fast for about 10 to 12 hours before collection. The purpose is to reduce variation caused by food-related gastrointestinal hormone activity.
Medication preparation is more complicated. Some drugs alter insulin secretion, gastrointestinal motility, or neuroendocrine hormone release. A laboratory may recommend withholding certain medicines if medically possible, but this decision belongs to the treating clinician. Patients should never stop insulin, diabetes medicines, antidiarrheal drugs, somatostatin analogs, or any other prescription medication on their own simply to prepare for testing.
Somatostatin analog therapy is particularly important to document because it can change symptoms and endogenous hormone secretion and may affect the timing or purpose of measurement.
Specimen handling is critical. Peptide hormones can degrade after collection. The laboratory may require a prechilled tube, rapid centrifugation, plasma separation, freezing, and transport on dry ice. A sample processed incorrectly can be less reliable even when the blood draw itself was uncomplicated.
The clinician should also provide context such as fasting status, glucose level, kidney and liver function, known NET history, and current medications. If a result is inconsistent with symptoms, repeating the test under carefully controlled conditions may be appropriate before pursuing major decisions.
How somatostatinoma is diagnosed
Diagnosis begins with the clinical pattern. A combination of unexplained diabetes or worsening glucose control, chronic diarrhea or fatty stools, gallstones, abdominal symptoms, and weight loss can prompt evaluation, especially when imaging has identified a pancreatic or duodenal lesion.
Biochemical testing may include fasting somatostatin as well as tests for alternative functioning NET syndromes. Depending on symptoms, clinicians may measure insulin and C-peptide, gastrin, glucagon, vasoactive intestinal peptide, pancreatic polypeptide, or other markers. Broad nonspecific markers are interpreted cautiously because their diagnostic performance is limited.
Imaging then addresses tumor location and extent. Multiphasic CT or MRI can evaluate the pancreas, duodenum, liver, and regional lymph nodes. Endoscopic ultrasound is particularly useful for small pancreatic lesions and can facilitate biopsy.
Well-differentiated NETs often express somatostatin receptors. Somatostatin receptor PET with an appropriate radiotracer can identify primary and metastatic disease and also determine whether receptor-targeted therapy may be an option.
Pathology confirms neuroendocrine differentiation and reports tumor grade. The Ki-67 proliferation index and mitotic rate help classify a well-differentiated NET, while morphology distinguishes it from a poorly differentiated neuroendocrine carcinoma. Immunohistochemical staining may demonstrate somatostatin production, but biochemical syndrome and pathology are interpreted together.
Genetic evaluation may be considered when age, family history, multifocal disease, or associated clinical features suggest an inherited syndrome.
Treatment and monitoring
Treatment depends on whether the tumor is localized, whether it has spread, its grade, receptor expression, symptoms, and the patient’s overall health. Surgery offers the best chance of cure for a localized resectable somatostatinoma.
For metastatic or unresectable well-differentiated NETs, management may include somatostatin analogs, targeted therapies, peptide receptor radionuclide therapy, liver-directed treatment, chemotherapy in selected cases, or other systemic approaches. The exact strategy is individualized by a multidisciplinary NET team.
Symptom management is also important. Diabetes may require glucose-lowering therapy. Steatorrhea and malabsorption may improve with pancreatic enzyme replacement in selected patients. Diarrhea, nutritional deficiencies, gallstone complications, and dehydration require specific treatment rather than assuming every symptom will resolve with tumor control.
If fasting somatostatin was markedly elevated at baseline, serial measurements can sometimes provide supportive evidence of treatment response. A decline after successful surgery or effective systemic therapy is reassuring, while a sustained rise may prompt closer assessment.
Blood hormone trends should not replace imaging. Tumors can progress without a proportional hormone rise, and treatment can suppress secretion without eliminating all tumor cells. Follow-up therefore combines clinical symptoms, laboratory tests relevant to the original syndrome, cross-sectional imaging, and receptor imaging when indicated.
Using the same laboratory method for serial somatostatin measurements improves comparability.
Important limitations and when to seek care
Somatostatin testing has several limitations. The tumor is rare, the assay is technically sensitive, reference ranges are method-specific, and the clinical syndrome overlaps with common disorders. Diabetes, diarrhea, gallstones, and weight loss are far more often caused by conditions other than somatostatinoma.
A clinician should first evaluate common and urgent causes of these symptoms. Persistent greasy stools and weight loss may reflect pancreatic insufficiency or intestinal disease. New diabetes has many causes. Gallstones are common and usually unrelated to a NET.
More urgent evaluation is needed when symptoms include severe dehydration, repeated vomiting, inability to maintain nutrition, gastrointestinal bleeding, jaundice, severe abdominal pain, or rapidly worsening glucose abnormalities. These problems may reflect complications of a tumor or an unrelated illness and should not wait for a specialty hormone result.
If a somatostatin result is high, the most useful next question is whether the patient has a compatible hormone syndrome and an anatomic lesion. If both are present, specialist evaluation with endocrine oncology, gastroenterology, surgery, or a dedicated NET team can coordinate biochemical confirmation, imaging, tissue diagnosis, and treatment.
For patients without a suggestive syndrome or imaging finding, an isolated small elevation should be verified before it is treated as evidence of cancer. Somatostatin is a specialized diagnostic tool, and its strength comes from using it in the right clinical setting.
Because the syndrome is so rare, clinicians usually look for a pattern rather than one symptom. New diabetes by itself is common and almost never indicates somatostatinoma. Gallstones are also common. The combination becomes more informative when several features occur together—for example, difficult-to-explain hyperglycemia plus chronic fatty diarrhea, weight loss, and a pancreatic or duodenal lesion on imaging. This pattern-based approach reduces unnecessary specialty hormone testing.
Nutritional assessment can be important when steatorrhea is prominent. Chronic fat malabsorption may reduce absorption of fat-soluble vitamins A, D, E, and K and contribute to weight loss. Stool fat testing, pancreatic function assessment, or vitamin measurements may be considered when symptoms suggest significant malabsorption. Treating a deficiency can improve health even while the tumor workup continues.
Tumor location can influence presentation. Pancreatic somatostatinomas are often larger when discovered and are more likely to produce a systemic hormone syndrome. Duodenal somatostatin-producing tumors may be smaller and can present with local effects such as obstruction or bleeding rather than the complete endocrine syndrome. Some are associated with distinctive histologic features and inherited conditions, which is why pathology and family history can affect the next steps after diagnosis.
A specialist may also evaluate whether a pancreatic lesion is producing more than one hormone. Functioning NETs are classified by their dominant clinical syndrome, but hormone expression can overlap. If the symptoms do not fit somatostatin excess cleanly, testing for other peptides may prevent misclassification.
After surgery, follow-up focuses on recurrence risk as well as hormone normalization. The schedule is based on tumor size, grade, lymph-node status, metastases, resection margins, and the original biochemical pattern. A patient with a small localized low-grade tumor may need a different surveillance intensity than someone with liver metastases. Hormone measurement can supplement that plan when it was informative before treatment.
Somatostatin analogs deserve one additional clarification. Although these drugs mimic the inhibitory actions of somatostatin and are widely used in NET care, their presence does not mean that a patient has a somatostatin-secreting tumor. They are treatments used across many NET types because the tumors often express somatostatin receptors.
Another practical issue is that many patients reach specialty care after months of treatment for the individual symptoms. A person may already be taking insulin for diabetes, pancreatic enzymes for steatorrhea, or having undergone gallbladder surgery. Those treatments can blur the classic syndrome without eliminating the underlying tumor. Reviewing the timeline—what symptom appeared first, which treatments helped, and whether weight loss continued—can reveal the pattern more clearly than the current symptom list alone.
If a tumor is found, staging is separate from proving hormone excess. A fasting somatostatin level can support the functioning diagnosis, while CT, MRI, receptor PET, lymph-node assessment, and liver imaging determine where disease is present. This separation matters because treatment intensity depends more on stage and grade than on the hormone concentration itself.
Finally, a patient with a suspected inherited syndrome may need evaluation beyond the tumor. Genetic counseling can guide testing and may affect surveillance for other endocrine or neural tumors in the patient and relatives. Genetic assessment is not routine for every somatostatinoma, but it becomes more relevant with young age, multifocal disease, characteristic physical findings, or a strong family history.
References
– European Neuroendocrine Tumor Society 2023 guidance paper for functioning pancreatic neuroendocrine tumour syndromes. 2023 (guidance paper) – Somatostatinoma – Endotext – NCBI Bookshelf 2023 (Endotext review) – Somatostatinoma – StatPearls – NCBI Bookshelf 2025 (clinical review) – Management of Functional Pancreatic Neuroendocrine Neoplasms 2023 (review) – Role of Somatostatin Signalling in Neuroendocrine Tumours 2022 (review) – FSOM1 – Overview: Somatostatin (Somatotropin Release-Inhibiting Factor, SRIF) 2026 (laboratory reference)
Disclaimer
This article is for general educational purposes and does not diagnose somatostatinoma or any neuroendocrine tumor. Somatostatin assays require laboratory-specific preparation, handling, and reference intervals, and prescription medicines should not be stopped without clinician guidance. Persistent or severe gastrointestinal symptoms, dehydration, jaundice, bleeding, or major glucose abnormalities require direct medical evaluation.