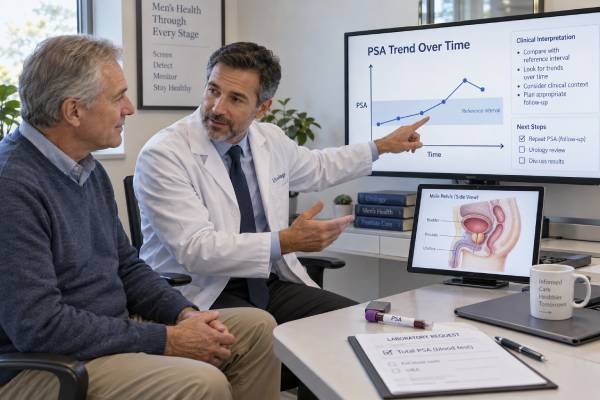
A total prostate-specific antigen (PSA) test measures the overall concentration of PSA circulating in the blood, including PSA that is protein-bound and PSA that is free. It is the standard PSA value used for prostate cancer screening, evaluation of an abnormal prostate finding, and follow-up after prostate cancer treatment. Total PSA is useful because prostate cancer can raise it, but the test is not cancer-specific. Benign prostate enlargement, inflammation, urinary retention, recent prostate procedures, age, and natural day-to-day variation can also increase the result. There is no single PSA number that is “normal” for every man or that can reliably confirm or exclude cancer. Modern practice uses total PSA as the starting point for a risk assessment that may include repeat testing, percent free PSA, PSA density, secondary biomarkers, prostate MRI, and biopsy. After prostate cancer treatment, total PSA takes on a different meaning: the expected level depends strongly on whether the prostate was surgically removed or remains in place after radiation or other therapy.
- Total PSA includes both free PSA and PSA bound to blood proteins.
- No universal cutoff separates benign prostate conditions from prostate cancer.
- A newly elevated PSA is commonly repeated before secondary biomarkers, MRI, or biopsy.
- Total PSA is used for screening only after discussion of potential benefits and harms.
- After prostatectomy, PSA should fall to a very low or undetectable level; after radiation, PSA usually declines more gradually because prostate tissue remains.
Table of Contents
- What total PSA measures
- Normal range, thresholds, and age
- Why total PSA can be high
- How total PSA is used for prostate cancer screening
- Free PSA, PSA density, biomarkers, and MRI
- Total PSA after prostate cancer treatment
- Repeat testing and next steps after an abnormal result
What total PSA measures
PSA is a protein enzyme produced primarily by prostate epithelial cells. In semen it helps liquefy seminal fluid. A small amount enters the bloodstream, where it circulates in several forms.
Total PSA is the sum of the PSA forms measured by the assay. Most circulating PSA is bound to blood proteins, while a smaller portion circulates unbound as free PSA. A routine laboratory report simply labeled “PSA” usually refers to total PSA unless another form is specified.
The test is performed on a blood sample and is generally reported in nanograms per milliliter (ng/mL). It does not require a prostate biopsy, imaging, or fasting. Its simplicity is one reason PSA became a widely used cancer screening test.
The biological limitation is equally important: PSA comes from prostate tissue, not specifically from prostate cancer. Any process that increases the amount of prostate tissue, irritates the gland, or disrupts its normal architecture can raise blood PSA. This includes BPH, prostatitis, urinary retention, and prostate procedures.
Total PSA has three main clinical roles. First, it can be used in screening before symptoms appear. Second, it helps evaluate men with urinary symptoms, an abnormal prostate examination, or another reason to suspect cancer. Third, after cancer is diagnosed, PSA becomes a highly useful marker for response and recurrence.
Those roles require different interpretations. A PSA of 1.0 ng/mL during screening, for example, has a very different meaning from the same value several months after radical prostatectomy, when nearly all PSA-producing tissue should have been removed.
Normal range, thresholds, and age
There is no universally accepted “normal total PSA range.” Historically, 4.0 ng/mL was widely used as a cutoff. Many modern screening pathways use lower values to trigger additional assessment, but professional guidelines increasingly discourage treating any one threshold as a yes-or-no cancer boundary.
Cancer can occur at PSA levels below 4.0 ng/mL. At the same time, many men with PSA above 4.0 have benign findings. The probability of prostate cancer rises as PSA rises, but the distributions overlap substantially.
Age matters because the prostate usually enlarges over time. Average PSA therefore tends to be higher in older men. Age-specific ranges have been proposed, but they are not applied consistently across guidelines or laboratories. A younger man with a PSA that is high for his baseline may deserve evaluation even if the number falls under a traditional cutoff.
The European Association of Urology notes that PSA is organ-specific but not cancer-specific and that there is no single agreed threshold defining abnormality. AUA/SUO guidance also emphasizes individualized risk and recommends confirming a newly elevated PSA before moving to secondary testing.
The laboratory reference interval is useful but should not be treated as a clinical verdict. Screening decisions consider the absolute PSA, prior values, age, family history, inherited risk, prostate volume, examination findings, and health status.
A trend can be helpful, but PSA velocity alone should not be used as the sole reason for biopsy. A rise may reflect infection or biological variation, and small changes can appear large when the baseline value is low.
Why total PSA can be high
Prostate cancer is one cause of high total PSA, but benign explanations are common.
Benign prostatic hyperplasia. BPH increases the volume of noncancerous prostate tissue. A larger gland often produces more PSA, so a stable elevation may be partly explained by prostate size.
Prostatitis or urinary infection. Inflammation can cause a large temporary increase, especially when accompanied by fever, pelvic pain, painful urination, or urinary frequency. PSA may take time to return toward baseline after the acute condition resolves.
Urinary retention. Acute inability to empty the bladder can raise PSA. Retention is a clinical problem requiring prompt treatment regardless of its effect on the tumor marker.
Recent prostate procedures. Prostate biopsy can markedly elevate PSA. Other instrumentation or manipulation may also affect the result, depending on the procedure and timing.
Ejaculation and vigorous cycling. These may cause small temporary increases in some men. The effect is usually modest but can matter near a decision threshold.
Natural biological variation. PSA fluctuates. AUA guidance notes that a meaningful proportion of men with a newly elevated test have a lower result when it is repeated. This is why confirmation is often the first step.
Some medications lower PSA. Finasteride and dutasteride, used for BPH and hair loss, can reduce PSA substantially after months of treatment. A clinician needs to know about these drugs because a seemingly “normal” value may need adjusted interpretation.
A high PSA should therefore be treated as a finding to explain, not as proof of cancer.
How total PSA is used for prostate cancer screening
PSA screening aims to detect clinically important prostate cancer before it causes symptoms or spreads. Randomized screening trials show that PSA-based programs can reduce prostate cancer mortality in some populations, but screening also produces harms.
An elevated test can lead to repeat blood work, biomarkers, MRI, and biopsy. Biopsy may cause bleeding, infection, urinary retention, or discomfort. Screening can also identify low-risk cancers that would never have threatened health. Detecting these tumors can lead to anxiety and, if overtreated, urinary incontinence, erectile dysfunction, or bowel effects.
For those reasons, major guidelines recommend shared decision-making. The most appropriate starting age and interval depend on baseline risk. AUA/SUO guidance supports offering screening discussions in midlife and starting earlier for men at increased risk, such as those with a strong family history or certain inherited pathogenic variants.
Screening is less likely to help when life expectancy is limited by advanced age or serious competing illness because prostate cancer often develops slowly. Health status and preferences matter more than age alone.
A low baseline PSA may justify a longer screening interval, while a higher value or stronger risk profile may lead to shorter intervals. The goal is not maximum testing. It is to detect Grade Group 2 or higher disease that could affect health while minimizing unnecessary procedures.
Total PSA is therefore the first step in a screening pathway, not an automatic biopsy trigger.
Free PSA, PSA density, biomarkers, and MRI
When total PSA is elevated, several tools can refine the probability of clinically significant cancer before biopsy.
Percent free PSA compares free PSA with total PSA. In men with mildly or moderately elevated total PSA, a lower percentage of free PSA is generally associated with greater cancer risk. This can help distinguish benign enlargement from a more concerning pattern.
PSA density divides total PSA by prostate volume. If a large prostate produces a moderate PSA elevation, the density may be reassuring. A relatively high PSA for a small gland can increase concern. MRI or ultrasound provides the prostate volume used for this calculation.
Secondary blood or urine biomarkers can combine multiple proteins, kallikreins, or genetic markers. PHI, for example, combines total PSA, free PSA, and p2PSA. Guidelines recommend using such tests selectively when the result is likely to change a biopsy decision.
Multiparametric MRI evaluates the prostate for lesions suspicious for clinically significant cancer. MRI can guide targeted biopsy and sometimes help avoid biopsy in men whose overall risk is low. A negative MRI reduces risk but does not eliminate it, especially when PSA density, family history, or other factors remain concerning.
Risk calculators can integrate age, PSA, digital rectal examination, family history, prior biopsy, prostate volume, MRI, and biomarkers. This multivariable approach is more informative than applying one PSA cutoff to every patient.
If the combined risk remains high, biopsy is required to establish the diagnosis and Grade Group.
Total PSA after prostate cancer treatment
After a prostate cancer diagnosis, PSA becomes a follow-up marker, but the expected pattern depends on treatment.
After radical prostatectomy, nearly all prostate tissue is removed. PSA should therefore fall to a very low or undetectable level within weeks, depending on assay sensitivity and timing. A persistently detectable PSA may suggest residual prostate tissue or cancer. A later confirmed rise can indicate biochemical recurrence.
Professional groups use defined criteria for biochemical recurrence after prostatectomy, but assay sensitivity and clinical context matter. An ultrasensitive PSA may detect tiny values below traditional recurrence thresholds. A very low detectable result does not automatically mean treatment has failed; the trend and confirmatory testing are important.
After radiation therapy, the prostate remains in the body. Normal prostate cells continue to produce PSA, so the expected value is not zero. PSA usually falls gradually over many months and can take years to reach its lowest point, called the nadir.
A temporary PSA bounce can occur after radiation, particularly brachytherapy. The value rises and then falls without representing recurrence. Biochemical recurrence after radiation is commonly defined using the Phoenix criterion: PSA rising at least 2 ng/mL above the post-treatment nadir. Clinical interpretation still considers timing and treatment details.
After androgen-deprivation therapy, PSA often falls because testosterone signaling is suppressed. If PSA rises while testosterone remains at castrate levels, clinicians evaluate for treatment-resistant disease using the full oncologic context.
Active surveillance for low-risk prostate cancer also uses serial PSA, but PSA alone does not determine progression. MRI and repeat biopsy may be part of surveillance protocols.
Repeat testing and next steps after an abnormal result
For a newly elevated screening PSA, repeating the test is often the first step. The timing can range from several weeks to a few months depending on the value, symptoms, recent procedures, and degree of concern.
Before the repeat test, the clinician reviews possible confounders. Active urinary infection or prostatitis should be evaluated. Recent biopsy or instrumentation may justify delaying measurement. Some clinicians advise avoiding ejaculation for 24 to 48 hours before testing if the result is near a threshold.
Prescription medicines and supplements should be documented. Patients should not stop finasteride, dutasteride, testosterone therapy, or other medication without medical advice simply to change a PSA result.
If the repeat remains elevated, the clinician may calculate PSA density, order percent free PSA or another biomarker, perform a digital rectal examination, or obtain prostate MRI. The decision depends on whether the added information is likely to change management.
Biopsy is recommended when the overall probability of clinically significant cancer justifies tissue diagnosis. Modern biopsy often includes MRI-targeted cores if a suspicious lesion is visible. Pathology then provides the information PSA cannot: whether cancer is present and, if so, its Grade Group.
Urgent evaluation is needed for acute urinary retention, fever with urinary symptoms, severe pelvic pain, or systemic illness. These symptoms may point to infection or obstruction rather than cancer but require prompt care.
A total PSA result is most useful when interpreted as part of a timeline. The baseline, the repeat value, the conditions around testing, prostate size, secondary risk markers, and—after treatment—the expected PSA behavior all matter more than labeling one number simply “normal” or “high.”
Two additional details can prevent common misunderstandings in follow-up. First, the numerical behavior of PSA after treatment is not comparable across treatment types. A value that would be abnormal after prostatectomy may be expected after radiation because benign prostate tissue remains. Patients should therefore avoid comparing their post-radiation PSA with another person’s post-surgery result.
Second, the lowest PSA reached after radiation—the nadir—can take a long time to establish. A gradual decline over 18 to 24 months may still be compatible with a good response, and temporary bounce patterns are especially common after brachytherapy. Clinicians look at the size, timing, and persistence of a rise rather than reacting to one increase.
For screening, the same principle of repeated context applies. If a PSA remains elevated but MRI is negative, the decision about biopsy may depend heavily on PSA density, hereditary risk, prior biopsy history, and the quality of the MRI. Some men can be followed safely with a defined repeat-testing plan; others still have enough residual risk to justify biopsy despite negative imaging.
Keeping a longitudinal record of total PSA values, laboratory dates, medications, and major prostate events such as infection, biopsy, surgery, radiation, or hormone therapy makes interpretation much more reliable than looking at a single result in isolation.
After a biopsy shows low-risk cancer, total PSA remains useful but becomes only one part of active surveillance. A rising value may lead to earlier MRI or repeat biopsy, yet treatment is usually triggered by a broader change in risk rather than PSA alone. Grade progression on biopsy, increasing tumor volume, MRI progression, age, health, and patient preferences all contribute.
This prevents two opposite errors: treating every PSA rise as cancer progression and ignoring a persistent rise because a previous biopsy was reassuring. The value of total PSA comes from repeated, contextual interpretation across the entire course of screening, diagnosis, and follow-up.
References
– Early Detection of Prostate Cancer: AUA/SUO Guideline Part I: Prostate Cancer Screening 2023 (guideline) – Early Detection of Prostate Cancer: AUA/SUO Guideline Part II: Considerations for a Prostate Biopsy 2023 (guideline) – Diagnostic Evaluation – EAU Guidelines on Prostate Cancer – Uroweb 2026 (guideline) – Prostate-specific antigen screening for prostate cancer: Diagnostic performance, clinical thresholds, and strategies for refinement 2024 (review) – The Effectiveness and Harms of PSA-Based Prostate Cancer Screening: A Systematic Review 2025 (systematic review) – Prostate-Specific Antigen (PSA) Test – NCI 2025 (National Cancer Institute fact sheet)
Disclaimer
This article is for general education and does not determine whether an individual has prostate cancer or whether screening, MRI, or biopsy is appropriate. PSA interpretation changes with age, prostate size, medications, laboratory method, and prior cancer treatment. A new or rising PSA should be reviewed with a qualified clinician using the patient’s full history and treatment context.