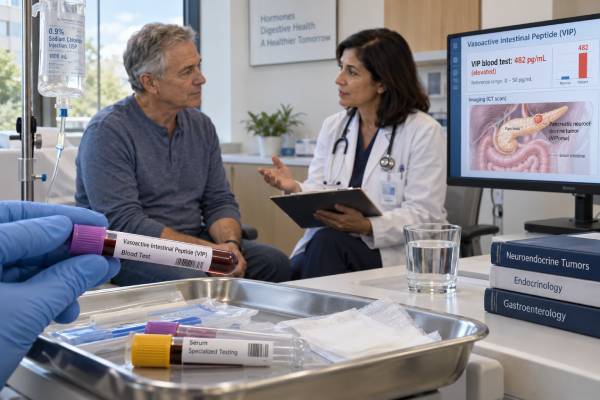
A vasoactive intestinal peptide (VIP) blood test is a specialized hormone test used mainly when a VIP-secreting neuroendocrine tumor, or VIPoma, is suspected. VIPoma classically causes large-volume watery diarrhea that continues despite fasting, leading to dehydration, low potassium, and acid-base disturbances. This pattern is often called WDHA syndrome—watery diarrhea, hypokalemia, and achlorhydria or hypochlorhydria. Most adult VIPomas arise in the pancreas, although VIP can be produced by neurogenic and other rare tumors. A high plasma VIP level during active secretory diarrhea strongly supports the diagnosis, but no single cutoff applies to every laboratory. The test is technically sensitive because VIP is a peptide that degrades unless the specimen is processed and frozen correctly. Mild elevations can be nonspecific, and a normal value obtained when symptoms are absent may not exclude intermittent secretion. Diagnosis requires the hormone result to fit the clinical syndrome, followed by imaging and usually pathology. Severe watery diarrhea with dehydration or low potassium can be medically urgent even before the tumor has been localized.
- VIP testing is used for suspected VIPoma in patients with otherwise unexplained secretory watery diarrhea.
- The classic syndrome includes watery diarrhea, hypokalemia, dehydration, and reduced gastric acid production.
- Reference ranges and diagnostic thresholds are assay-specific; one current plasma assay lists a reference value below 86 pg/mL.
- Samples often require immediate chilling, rapid separation, and freezing because VIP is unstable.
- Severe diarrhea, fainting, weakness, confusion, very low potassium, or inability to maintain fluids requires urgent medical care.
Table of Contents
- What VIP is and what the blood test measures
- VIPoma and watery diarrhea syndrome
- What a high VIP level means
- Other causes of watery diarrhea and elevated VIP
- Test preparation and specimen handling
- How VIPoma is diagnosed and treated
- Monitoring VIP levels and when symptoms are urgent
What VIP is and what the blood test measures
Vasoactive intestinal peptide is a peptide hormone and neurotransmitter found throughout the gastrointestinal and nervous systems. It relaxes smooth muscle, dilates blood vessels, stimulates intestinal water and electrolyte secretion, and reduces gastric acid production.
Under normal conditions, circulating VIP concentrations are low. A VIPoma releases excessive hormone into the bloodstream, causing the intestine to secrete very large amounts of water and electrolytes. The resulting diarrhea can become severe enough to cause life-threatening potassium depletion and dehydration.
The laboratory test generally measures VIP in plasma. A current Mayo Clinic Laboratories method lists a reference value below 86 pg/mL, but other laboratories use different assays and ranges. Older literature often cites higher diagnostic thresholds such as 200 pg/mL, while some contemporary reviews discuss lower values when the clinical syndrome is strong. These numbers should not be treated as interchangeable.
The most useful result is a clearly elevated VIP concentration obtained while the patient is experiencing active secretory diarrhea. A small isolated elevation without the typical syndrome has much less diagnostic weight.
VIP testing is not a screening test for pancreatic cancer or neuroendocrine tumors in general. Most pancreatic NETs do not secrete VIP, and common pancreatic adenocarcinoma is not diagnosed with this test.
VIPoma and watery diarrhea syndrome
VIPoma is a rare functioning neuroendocrine tumor. In adults, the primary tumor is usually located in the pancreas, often in the body or tail. In children, VIP excess can occasionally be associated with neurogenic tumors such as ganglioneuroma or neuroblastoma.
The hallmark symptom is profuse watery diarrhea. Unlike many food-related or inflammatory diarrheas, secretory diarrhea often continues during fasting and may persist overnight. Stool volumes can become very large.
Potassium is lost in the stool, producing hypokalemia. Low potassium can cause muscle weakness, cramps, constipation or ileus, palpitations, abnormal heart rhythms, and severe fatigue. Bicarbonate loss can cause metabolic acidosis.
VIP also suppresses gastric acid secretion, which explains the older term WDHA syndrome: watery diarrhea, hypokalemia, and achlorhydria. Not every patient has complete achlorhydria, so some clinicians use “pancreatic cholera syndrome” or simply VIPoma syndrome.
Other features can include dehydration, thirst, weight loss, abdominal discomfort, nausea, flushing, high blood glucose, and elevated calcium in some patients. Kidney injury can develop from prolonged volume depletion.
The syndrome can be mistaken for infection, irritable bowel syndrome, medication-induced diarrhea, inflammatory bowel disease, or laxative use. The persistence of high-volume diarrhea despite fasting, combined with major potassium loss, is what makes a secretory hormone syndrome more concerning.
What a high VIP level means
A markedly elevated plasma VIP level during active secretory diarrhea strongly supports VIPoma when other causes have been excluded. The result should be interpreted against the performing laboratory’s reference interval and with attention to specimen quality.
There is no universally valid diagnostic number. Earlier literature frequently used VIP concentrations above approximately 200 pg/mL in a patient with severe secretory diarrhea. Some current laboratories use lower reference limits and evaluate the degree of elevation relative to the upper limit of normal.
A very high value cannot determine whether the tumor is benign or malignant, where it is located, or whether it has metastasized. Imaging is required for localization and staging.
A modest elevation is less specific. It may result from assay variation, improper sample handling, kidney dysfunction, inflammatory or ischemic intestinal disease, or other uncommon conditions. If the clinical picture does not fit VIPoma, clinicians should avoid treating a borderline result as a cancer diagnosis.
A normal VIP value can also be misleading if the sample was obtained when diarrhea had temporarily improved, if hormone secretion is intermittent, or if the specimen was not processed correctly. Repeat testing during active symptoms may be considered when suspicion remains high.
Serial VIP measurements can be useful after treatment if the marker was clearly elevated at diagnosis. A fall can support biochemical response, while a rise may prompt reassessment. Imaging remains essential because tumor progression and hormone secretion do not always change in parallel.
Other causes of watery diarrhea and elevated VIP
VIPoma is rare, while chronic diarrhea is common. A careful differential diagnosis is therefore essential before attributing symptoms to a neuroendocrine tumor.
Common causes include medications, infections, lactose or other carbohydrate intolerance, celiac disease, microscopic colitis, inflammatory bowel disease, pancreatic insufficiency, bile-acid diarrhea, and functional bowel disorders. Laxative use and certain supplements can also produce persistent watery stool.
Other endocrine causes of secretory diarrhea include carcinoid syndrome, gastrinoma in selected circumstances, medullary thyroid carcinoma, and rare hormone-secreting tumors. Hyperthyroidism can increase bowel frequency but usually does not produce the extreme secretory pattern typical of VIPoma.
Clinicians can distinguish osmotic from secretory diarrhea partly by history, fasting response, stool electrolytes, and the stool osmotic gap. Secretory diarrhea tends to continue despite not eating and can occur at night.
VIP can be mildly elevated in conditions other than VIPoma. Reduced renal clearance, short bowel or severe intestinal disease, and other neuroendocrine or neural conditions have been reported. The degree of elevation and the symptom pattern matter.
The diagnostic workup may include stool studies, metabolic panel, thyroid tests, celiac testing, medication review, endoscopy, and other hormone assays before or alongside VIP testing. The goal is to identify common treatable causes while recognizing the small number of patients with a functioning NET.
Test preparation and specimen handling
VIP is unstable after blood collection, so preanalytical handling is a major part of test accuracy. Laboratories typically require collection into a chilled EDTA tube, prompt centrifugation, separation of plasma, and immediate freezing. The frozen specimen is then transported under controlled conditions.
A sample left at room temperature or processed late can lose measurable peptide and produce a falsely low result. For that reason, VIP testing is best performed through a laboratory familiar with peptide-hormone assays.
Fasting may be requested. More importantly, the sample should ideally be obtained during active diarrhea because VIP secretion may fluctuate. The clinician should document whether symptoms were present at the time of collection.
Medication history matters. Antidiarrheal drugs, somatostatin analogs such as octreotide or lanreotide, and other therapies can alter symptoms or hormone secretion. Patients should not stop prescribed treatment on their own before the test. The ordering clinician should determine whether the timing of medication relative to sampling is important.
Kidney function and electrolyte results should be checked at the same time because dehydration and hypokalemia can be clinically more urgent than the hormone measurement. A comprehensive metabolic panel can reveal potassium depletion, kidney injury, glucose abnormalities, and bicarbonate changes.
If a VIP result is inconsistent with the clinical picture, confirming proper collection and repeating the test under controlled conditions may be more useful than immediately escalating to invasive procedures.
How VIPoma is diagnosed and treated
The diagnosis begins with a convincing clinical syndrome: persistent high-volume secretory diarrhea, often with hypokalemia and dehydration. A clearly elevated VIP level provides biochemical confirmation.
After that, imaging is used to find the tumor. Multiphasic CT or MRI can evaluate the pancreas and liver. Endoscopic ultrasound may detect small pancreatic lesions and can provide tissue sampling.
Well-differentiated pancreatic NETs frequently express somatostatin receptors. Somatostatin receptor PET with an appropriate radiotracer can help identify the primary tumor and metastases and can determine whether receptor-targeted treatment may be useful.
Pathology confirms neuroendocrine differentiation and reports tumor grade, commonly using the Ki-67 proliferation index and mitotic rate. Staging assesses lymph nodes, liver, and other sites of spread.
Treatment starts with fluid and electrolyte replacement when diarrhea is severe. Potassium correction can be urgent. Somatostatin analogs often reduce VIP secretion rapidly and can markedly improve diarrhea.
Surgery is the preferred potentially curative treatment for a localized, resectable tumor. For metastatic or unresectable disease, options can include long-acting somatostatin analogs, peptide receptor radionuclide therapy, targeted agents, chemotherapy in selected cases, and liver-directed treatments. Management is best coordinated by a multidisciplinary neuroendocrine tumor team.
Monitoring VIP levels and when symptoms are urgent
When VIP was substantially elevated before treatment, it can serve as a useful personalized marker. After surgery, a fall into the laboratory’s reference range supports successful removal of the hormone-secreting tissue. Persistent elevation may suggest residual disease, although imaging is needed to confirm it.
During medical therapy, falling VIP can parallel symptom improvement. However, diarrhea can have more than one cause. A patient may continue to have loose stools because of pancreatic insufficiency, bile-acid malabsorption, bowel surgery, infection, or treatment effects even when VIP production is controlled.
Similarly, a biochemical rise should be confirmed and correlated with imaging before a major treatment change. Using the same laboratory method helps make serial values comparable.
The immediate danger in VIPoma is often the metabolic effect of diarrhea. Seek urgent medical evaluation for fainting, confusion, severe weakness, inability to drink enough fluid, very low urine output, repeated vomiting, chest palpitations, or signs of severe dehydration. Profound hypokalemia can trigger dangerous heart-rhythm disturbances.
Patients with established VIPoma should have a plan for managing recurrent diarrhea and monitoring potassium and kidney function. Rapid symptom escalation may need hospital treatment even if a follow-up VIP result is not yet available.
VIP is therefore both a diagnostic clue and a monitoring marker, but it should always be interpreted in the context of the clinical syndrome. A number alone does not diagnose the tumor; the combination of secretory diarrhea, biochemical excess, imaging, and pathology does.
The severity of fluid loss can be underestimated because stool may look like ordinary watery diarrhea even when the daily volume is several liters. Clinicians may quantify stool output in hospitalized patients and repeatedly measure potassium, bicarbonate, magnesium, creatinine, and other electrolytes. Rapid replacement can be lifesaving while the endocrine diagnosis is still being confirmed.
Acid-base findings can help support the physiology. Unlike vomiting, which often causes metabolic alkalosis, severe VIPoma diarrhea commonly causes bicarbonate loss and metabolic acidosis. This is not unique to VIPoma, but the combination of persistent secretory diarrhea, hypokalemia, and acidosis helps distinguish the syndrome from many common gastrointestinal disorders.
Calcium and glucose can also be abnormal. Some patients develop hypercalcemia, and VIP can influence glucose regulation through several mechanisms. These findings are supportive rather than diagnostic and should not distract from correcting the major water and potassium losses first.
When somatostatin analog treatment begins, diarrhea can improve quickly—sometimes before a tumor has been definitively treated. That rapid response supports a hormone-mediated mechanism but still does not substitute for localization and pathology. Long-acting formulations are often used for sustained control after an initial response, while surgery or other tumor-directed treatment is planned according to stage.
Patients with metastatic disease may have hormone symptoms that do not track perfectly with tumor size. A therapy can suppress VIP secretion and control diarrhea even when measurable tumors remain. Conversely, secretory symptoms can recur before a large anatomical change is obvious. This is why follow-up combines symptom logs, electrolytes, VIP trends, and imaging rather than relying on a single endpoint.
Long-term nutritional recovery also matters. Months of severe diarrhea can cause weight loss, muscle depletion, and micronutrient deficiencies. Once the secretory syndrome is controlled, dietitian support and assessment for ongoing malabsorption can help rebuild nutrition and distinguish residual gastrointestinal problems from recurrent VIP excess.
A specialist may also measure stool volume and calculate a stool osmotic gap when the diagnosis is unclear. A low osmotic gap supports secretory diarrhea because the stool water is being driven by measured electrolytes rather than unabsorbed substances. This finding is not specific to VIPoma, but it can justify an endocrine secretory-diarrhea workup when common infections and medication causes have been excluded.
The distinction between secretory and osmotic diarrhea also explains why fasting history matters. Lactose intolerance and many malabsorption syndromes improve when the triggering food is removed. VIP-mediated secretion generally continues even when the patient stops eating, which can make dehydration worse because oral intake falls while fluid loss persists.
If the tumor cannot be removed, symptom control remains a major treatment goal even when cure is not possible. Preventing recurrent hypokalemia, kidney injury, and hospital admissions can substantially improve quality of life. Patients and caregivers may be taught to recognize early warning signs, track stool frequency or volume, and obtain electrolyte testing promptly when symptoms accelerate.
After successful surgery, both symptom resolution and biochemical normalization are expected, but neither eliminates the need for oncologic follow-up. Recurrence risk depends on tumor grade, stage, margins, and metastatic history. Periodic imaging and clinical review remain necessary even when VIP stays normal.
References
– European Neuroendocrine Tumor Society 2023 guidance paper for functioning pancreatic neuroendocrine tumour syndromes. 2023 (guidance paper) – Vasoactive Intestinal Peptide-Secreting Tumor (VIPoma) – Endotext – NCBI Bookshelf 2023 (Endotext review) – All you need to know about VIPoma: Review on the latest studies 2024 (review) – Management of Functional Pancreatic Neuroendocrine Neoplasms 2023 (review) – A review of functional pancreatic neuroendocrine tumors: Exploring the molecular pathogenesis, diagnosis and treatment 2023 (review) – VIP – Overview: Vasoactive Intestinal Polypeptide, Plasma 2026 (laboratory reference)
Disclaimer
This article is for general education and does not diagnose VIPoma or another neuroendocrine tumor. VIP reference ranges, fasting instructions, and specimen-processing requirements vary by laboratory, and prescription medicines should not be stopped without clinician guidance. Severe watery diarrhea with dehydration, fainting, confusion, marked weakness, or suspected low potassium requires prompt medical evaluation.