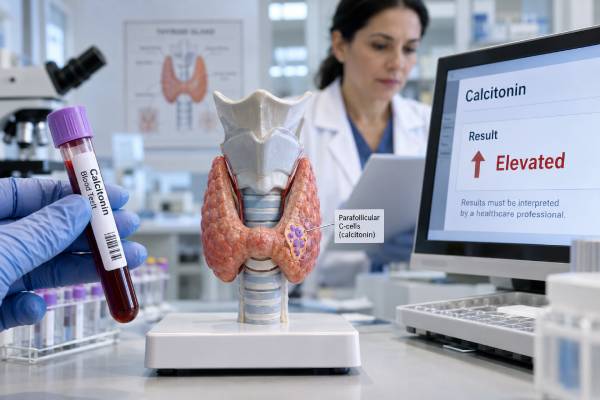
Calcitonin is a hormone made mainly by the thyroid’s parafollicular C cells. A blood calcitonin test is most important as a tumor marker for medullary thyroid carcinoma (MTC), a cancer that arises from those C cells. Calcitonin can help detect C-cell disease, estimate tumor burden, assess whether surgery removed all detectable MTC, and monitor for persistent or recurrent disease. However, the test is not perfectly specific. Mild elevations can occur with chronic kidney disease, smoking, medications or conditions that increase gastrin, other neuroendocrine disorders, and laboratory interference. Reference ranges also vary by assay and sex, so there is no single universal “normal” or cancer cutoff. Markedly elevated calcitonin is more concerning for MTC than a borderline result, but diagnosis still depends on the full thyroid evaluation. After MTC treatment, serial calcitonin and carcinoembryonic antigen (CEA) measurements are especially useful because persistent levels and marker doubling times can provide prognostic information.
- Calcitonin is the key blood tumor marker for medullary thyroid carcinoma: it reflects activity of thyroid C cells.
- Normal ranges are assay- and sex-specific: many laboratories use low single-digit or roughly under 10 pg/mL limits, but the report’s own reference interval should be used.
- Values above roughly 60–100 pg/mL are highly suspicious in many studies: no cutoff is perfectly universal across assays and populations.
- Mild elevations have many noncancer causes: kidney impairment, smoking, hypergastrinemia, medications, and assay interference can matter.
- After MTC surgery, calcitonin should fall very low if biochemical cure is achieved: persistent or rising levels require specialist interpretation with CEA and imaging.
Table of Contents
- What Calcitonin Measures
- Normal Range and High Calcitonin Levels
- Calcitonin and Medullary Thyroid Cancer
- C-Cell Hyperplasia and Thyroid Nodules
- Calcitonin After Surgery and During Follow-Up
- False-Positive and Misleading Results
- What to Do After an Abnormal Calcitonin Result
What Calcitonin Measures
Calcitonin is a peptide hormone produced primarily by parafollicular C cells in the thyroid. Its normal physiologic role is related to calcium regulation, although it is not the main day-to-day regulator of calcium balance in adults. Clinically, its most important use is as a biomarker of C-cell activity.
Medullary thyroid carcinoma develops from C cells rather than the follicular thyroid cells that give rise to papillary and follicular thyroid cancers. This distinction is important because MTC behaves differently, has different genetic associations, and produces different tumor markers.
Papillary and follicular thyroid cancers are usually followed with thyroglobulin after appropriate treatment. MTC is followed primarily with calcitonin and CEA. A thyroglobulin tumor marker therefore answers a different clinical question and should not be substituted for calcitonin in MTC.
Most calcitonin assays are immunoassays that measure the hormone in serum or plasma. The number may be reported in pg/mL or equivalent units depending on the laboratory. Because assays differ in calibration and antibodies, values from different laboratories are not always directly interchangeable.
The concentration tends to rise as the amount of active C-cell tissue increases. Very small MTCs can cause modest elevations, while bulky or metastatic disease can produce much higher levels. There is considerable overlap, so the test is best viewed as a continuum of risk rather than a simple positive-or-negative cancer switch.
Calcitonin can also be measured after stimulation with calcium in selected specialist settings. Historically, pentagastrin was used in some countries. Current reviews note that stimulated testing may help in borderline cases, but lack of universally reproducible cutoffs and changing assay performance mean basal calcitonin is the main test in many centers.
Normal Range and High Calcitonin Levels
There is no single worldwide normal range. Reference limits depend on the assay, sex, age, and laboratory population. Men often have somewhat higher basal calcitonin concentrations than women because they typically have a larger C-cell mass.
Many laboratories use upper reference limits in the low single digits for women and somewhat higher limits for men; others use a general threshold near 10 pg/mL. The value printed on the laboratory report is the correct starting point.
A useful way to think about results is by degree of elevation:
| Result pattern | General interpretation |
|---|---|
| Within assay reference range | MTC less likely, but rare calcitonin-negative MTC exists |
| Mildly above range | Often nonspecific; repeat and assess benign causes |
| Persistent intermediate elevation | C-cell hyperplasia or small MTC becomes more relevant; specialist evaluation needed |
| Marked elevation, especially above about 60–100 pg/mL | Strongly raises concern for MTC in many published series |
| Very high level | Often associated with larger tumor burden or metastatic disease, but imaging/pathology remain necessary |
A numerical threshold such as 100 pg/mL should not be treated as an absolute diagnostic border. Contemporary reviews emphasize assay-dependent cutoffs. A value of 75 pg/mL may be highly abnormal for one method, while interpretation of a value near the upper limit requires much more nuance.
Calcitonin can rise for reasons other than MTC. Chronic kidney disease reduces clearance and alters hormone metabolism. Smoking can raise basal levels. Hypergastrinemia, which may occur with long-term acid-suppressing therapy or atrophic gastritis, can stimulate C cells in some patients. Other neuroendocrine tumors and inflammatory states have also been associated with elevations.
The most concerning pattern is a persistent result that is clearly above the assay’s normal range and remains unexplained after benign causes and analytical issues are considered.
Calcitonin and Medullary Thyroid Cancer
MTC accounts for a small minority of thyroid cancers but is clinically important because it may occur sporadically or as part of hereditary multiple endocrine neoplasia type 2, or MEN2. Germline pathogenic variants in the RET gene are responsible for hereditary MTC.
Calcitonin is useful at several points in MTC care. Before surgery, it can support the diagnosis and give a rough indication of disease burden. Higher preoperative values are associated with a greater chance of lymph-node and distant metastatic disease, although the number alone does not determine surgical extent.
Fine-needle aspiration cytology of a thyroid nodule can sometimes miss or misclassify MTC. Measuring calcitonin in the blood, and in selected cases in needle-washout fluid, can strengthen the diagnostic evaluation when MTC is suspected.
CEA is the other major serum marker for MTC. The CEA blood test is commonly associated with colorectal cancer, but CEA is also produced by medullary thyroid carcinoma. Calcitonin is generally more specific to C-cell biology, while CEA can add information about tumor burden and differentiation.
A discordant pattern can matter. In advanced MTC, a rapidly rising CEA with less impressive calcitonin secretion may sometimes be seen with less differentiated disease. On the other hand, both markers often rise together.
Once MTC is diagnosed, genetic counseling and RET germline testing are important because finding a hereditary variant affects the patient and potentially family members. It can also prompt screening for other MEN2-associated conditions, particularly pheochromocytoma and primary hyperparathyroidism.
Calcitonin should not be confused with calcium. A patient can have MTC and a normal blood calcium level because calcitonin excess usually does not cause dramatic hypocalcemia. The tumor-marker role is far more important than the hormone’s calcium-lowering effect in this context.
C-Cell Hyperplasia and Thyroid Nodules
C-cell hyperplasia means an increased number of thyroid C cells. It can occur as a precursor lesion in hereditary MTC, particularly in RET-associated disease, and it can also be seen in nonhereditary settings.
Mild or intermediate calcitonin elevation creates a difficult clinical zone because both C-cell hyperplasia and small MTC are possible, but benign causes are common as well. This is where repeat testing, laboratory method, medication review, kidney function, ultrasound findings, and specialist assessment become most useful.
Routine calcitonin screening for every thyroid nodule remains controversial internationally. Some European practices use calcitonin more routinely because it can detect MTC at an earlier stage. Other guidelines have historically considered evidence insufficient to recommend for or against universal testing. Local standards therefore vary.
If calcitonin is ordered in someone with a thyroid nodule, the test should ideally be interpreted before surgery rather than discovered incidentally afterward. A clearly elevated result may change the surgical and genetic workup because the operation for confirmed MTC differs from surgery for a typical differentiated thyroid cancer.
Thyroid ultrasound cannot diagnose MTC based on appearance alone. MTC can share suspicious features with other thyroid cancers, such as hypoechogenicity, irregular margins, calcifications, and abnormal lymph nodes. Cytology, calcitonin, and pathology work together.
A mildly high calcitonin with a benign-looking nodule does not automatically mean surgery is required. Depending on the value and clinical context, the clinician may repeat the assay, stop or review potential interfering drugs when safe, assess renal function, measure gastrin, use another assay, or perform additional thyroid evaluation.
In hereditary RET syndromes, the situation is different because the baseline risk of C-cell neoplasia is high. Management may include prophylactic or early thyroidectomy according to the specific RET variant, age, calcitonin level, and specialist guidelines.
Calcitonin After Surgery and During Follow-Up
After complete removal of localized MTC, calcitonin should fall to very low or undetectable levels. The exact timing of the postoperative measurement varies, but clinicians usually allow enough time for hormone clearance and recovery before defining biochemical status.
A normal or undetectable postoperative calcitonin is a favorable sign. Persistent elevation suggests residual C-cell tumor somewhere in the body, although the location may not be immediately visible on imaging if the tumor volume is small.
The absolute value helps guide the search. Very low persistent levels may be followed serially, while higher or rapidly rising concentrations increase concern for structural disease and may prompt neck ultrasound, cross-sectional imaging, or other targeted studies.
One of the most useful concepts is doubling time. Instead of looking only at whether calcitonin is high, clinicians examine how quickly it increases across several measurements. Shorter calcitonin and CEA doubling times are associated with more aggressive disease and worse prognosis. Reliable calculation requires multiple values over an adequate interval, ideally measured with the same assay.
A single result should not be used to calculate a doubling time or make major treatment decisions. Biological variation and assay imprecision can create small fluctuations. A sustained pattern is what matters.
Calcitonin and CEA should be read together
Calcitonin and CEA often move in the same direction, but they are not redundant. Calcitonin reflects C-cell secretory activity, while CEA is a broader tumor-associated glycoprotein that may become particularly informative in more advanced disease. A patient can have a modest calcitonin change with a more pronounced CEA rise, or the reverse. The clinical team therefore follows both rather than converting one marker into the other.
Doubling times can also differ. A consistently short doubling time for either marker is more concerning than a stable value over many years. The calculation is most reliable when the same assay is used and there are enough measurements over time to distinguish a true slope from normal laboratory variation.
Importantly, biochemical progression and structural progression are not identical. Imaging may remain negative even when calcitonin is detectable, particularly at low tumor burden. Conversely, a visible lesion may change only slowly while marker levels fluctuate. Follow-up plans are based on the combined pattern rather than forcing the blood test and scan to match perfectly at every visit.
Treatment of recurrent or metastatic MTC is not triggered by marker rise alone in every patient. Some people have detectable calcitonin for years without radiographically progressive disease. Management depends on tumor location, symptoms, growth rate, RET or other molecular findings, and whether disease can be surgically treated or requires systemic therapy.
Serial calcitonin is therefore both sensitive and limited: it can reveal biochemical persistence earlier than imaging, but it cannot by itself show where the disease is or whether immediate treatment will improve outcomes.
False-Positive and Misleading Results
Borderline calcitonin results are where errors are most likely. Several factors deserve review before a patient is labeled as having MTC.
Kidney impairment: Reduced renal function can raise calcitonin, particularly in advanced chronic kidney disease. The result should be interpreted with creatinine and estimated glomerular filtration rate.
Smoking: Smokers can have higher basal calcitonin than nonsmokers, contributing to sex- and population-related reference differences.
Hypergastrinemia: Proton pump inhibitors, autoimmune atrophic gastritis, and other causes of high gastrin have been associated with increased calcitonin in some patients. Medication changes should only be made with the prescribing clinician.
Other tumors and endocrine conditions: Some neuroendocrine neoplasms and rare nonthyroid cancers may produce calcitonin or calcitonin-related peptides.
Assay interference: Heterophile antibodies, biotin effects in susceptible assay formats, and other immunoassay problems can create results that do not fit the clinical picture. Repeating the test with another method can sometimes resolve an unexplained elevation.
Rare calcitonin-negative MTC: A normal calcitonin makes typical secretory MTC much less likely but does not make it impossible. Rare tumors secrete little measurable calcitonin, so a suspicious thyroid mass still requires standard diagnostic evaluation.
Another common mistake is comparing values from different laboratories as if they were identical. Because assay methods vary, a change from 18 pg/mL to 25 pg/mL after switching platforms may not represent true disease progression. Consistent longitudinal testing is especially important when calculating doubling times.
What to Do After an Abnormal Calcitonin Result
If calcitonin is mildly elevated, the usual next step is confirmation and context. Review the laboratory’s reference range, sex-specific cutoff, kidney function, smoking, medications, gastrin-related conditions, and whether the patient has a thyroid nodule or known MTC.
A repeat sample may be appropriate, especially when the result is unexpected. The clinician may use the same assay for reproducibility or a different validated platform if analytical interference is suspected.
If a thyroid nodule is present and calcitonin remains clearly elevated, referral to an endocrinologist, endocrine surgeon, or thyroid cancer specialist is appropriate. Ultrasound, cytology review, CEA, and sometimes additional imaging or stimulated testing may be considered according to the degree of elevation.
When MTC is confirmed, RET germline testing and assessment for hereditary MEN2 are central parts of care. Family implications should be handled through genetic counseling rather than informal testing of relatives.
For someone previously treated for MTC, a rising calcitonin should be compared with prior values and CEA. The oncology or endocrine team may calculate marker doubling times and decide whether structural imaging is needed. A biochemical rise does not necessarily mean immediate systemic treatment, but it should not be ignored.
Seek prompt medical attention for a rapidly enlarging neck mass, new trouble breathing or swallowing, severe diarrhea with dehydration, unexplained fainting or palpitations in someone with possible MEN2, or other acute symptoms. These issues require direct evaluation regardless of the calcitonin number.
Calcitonin is one of the most disease-linked serum tumor markers in endocrinology, but precision matters. Its best use is not simply deciding whether a value is “high”; it is identifying a persistent, biologically plausible C-cell signal and then combining that signal with thyroid imaging, pathology, genetics, CEA, and serial change.
References
- Calcitonin as Biomarker for the Medullary Thyroid Carcinoma. 2025 (Review)
- Progastrin-Releasing Peptide and Procalcitonin as Additional Markers in the Diagnostic Workup for Medullary Thyroid Carcinoma 2025
- Serum Biochemical Markers for Medullary Thyroid Carcinoma: An Update 2024 (Review)
- Fundamentals and recent advances in the evaluation and management of medullary thyroid carcinoma. 2024 (Review)
- Update on Calcitonin Screening for Medullary Thyroid Carcinoma and the Results of a Retrospective Analysis of 12,984 Patients with Thyroid Nodules 2023
- Diagnostic tests for medullary thyroid carcinoma: an umbrella review 2023 (Umbrella Review)
Disclaimer
Calcitonin results cannot diagnose or exclude medullary thyroid carcinoma by themselves. Mild elevations can have noncancer causes, and reference ranges vary by assay and sex. Abnormal or changing results should be reviewed by a qualified clinician with thyroid imaging, CEA, kidney function, pathology, and genetic evaluation when appropriate.