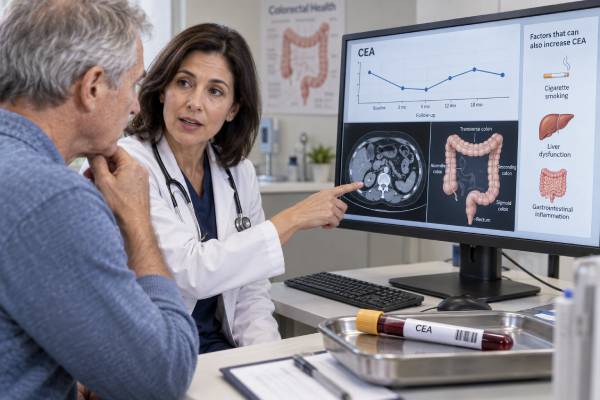
Carcinoembryonic antigen, or CEA, is a blood tumor marker used mainly to monitor colorectal cancer and several other cancers after diagnosis. It is not a reliable stand-alone test for finding cancer in healthy people because many cancers do not raise CEA and several non-cancer conditions can. Smoking, liver disease, inflammatory bowel disease, pancreatitis, lung inflammation, and other benign problems may cause mild elevations. In someone with colorectal cancer whose CEA was elevated before treatment, repeated measurements can help show whether the marker is falling after surgery or chemotherapy and whether a later rise deserves investigation for recurrence. The trend usually matters more than one isolated number. Laboratories also use different reference intervals, so the result should be compared with the range printed on the report and, when possible, with prior values from the same laboratory. A high CEA is a clue that needs context—not a diagnosis of cancer or proof that cancer has returned.
- Many laboratories use about 5 ng/mL as an upper reference limit, while some use a lower cutoff for nonsmokers; always use the range on your own report.
- A mild CEA elevation is often non-specific: cigarette smoking, liver disease, inflammation, and several benign gastrointestinal conditions can increase it.
- CEA is most useful for colorectal cancer follow-up when it was elevated before treatment and is tracked over time.
- A rising CEA can prompt imaging or other evaluation, but recurrence should not be diagnosed from CEA alone.
- CEA is not recommended as a general cancer-screening blood test because its sensitivity and specificity are too limited.
Table of Contents
- What the CEA Blood Test Measures
- CEA Normal Range and High-Level Meaning
- Benign Causes of High CEA
- How CEA Is Used for Colon and Rectal Cancer
- Testing, Timing, and Interpreting CEA Trends
- Other Cancers, Screening Limits, and False Results
- What to Do After an Abnormal CEA Result
What the CEA Blood Test Measures
CEA is a glycoprotein involved in cell adhesion. It is produced in larger amounts during fetal development and is normally present only at low concentrations in most healthy adults. Certain cancers can reactivate CEA production and release measurable amounts into the bloodstream.
The laboratory reports CEA in nanograms per milliliter (ng/mL), which is numerically equivalent to micrograms per liter (µg/L). The test is usually performed on serum or plasma using an immunoassay.
CEA is most strongly associated with colorectal adenocarcinoma, but it is not specific to the colon. It can also rise with cancers of the pancreas, stomach, lung, breast, ovary, and other organs. That broad expression is why CEA belongs in the same general family as other blood tumor markers: useful in the right setting, but rarely diagnostic by itself.
The most important distinction is screening versus monitoring. Screening asks whether an apparently healthy person has an undetected cancer. CEA performs poorly for that purpose because early cancers may produce no elevation and benign conditions can produce false positives. Monitoring asks whether a known cancer is responding, stable, or possibly returning. In that setting, a patient’s own baseline and serial pattern make the marker much more informative.
CEA may also carry prognostic information. A higher preoperative level in colorectal cancer is associated, on average, with a greater risk of advanced disease or recurrence. However, prognosis depends on tumor stage, pathology, molecular features, treatment response, and many patient factors; the CEA number is only one piece of that picture.
CEA Normal Range and High-Level Meaning
There is no universal CEA cutoff that means the same thing in every laboratory. Many laboratories use approximately 5 ng/mL as the upper reference limit. Some report a lower upper limit—often around 2.5 to 3 ng/mL—for people who do not smoke because smokers tend to have higher baseline CEA concentrations.
A result just above the reference range is generally less specific than a substantial, persistent elevation. Still, no single CEA value proves cancer.
| CEA pattern | Possible interpretation | Typical next consideration |
|---|---|---|
| Within the laboratory range | Reassuring in some contexts but does not exclude cancer | Use symptoms, imaging, pathology, and other tests as indicated |
| Mild elevation | May reflect smoking, inflammation, liver disease, or malignancy | Review benign causes and consider repeat testing |
| Persistent or progressively rising values | More concerning than one isolated high result | Evaluate the trend and consider imaging in a cancer survivor |
| Falling after treatment | Often supports response if CEA was elevated before treatment | Continue planned clinical and radiologic follow-up |
| Marked elevation | Raises concern for substantial tumor burden in the right setting, but remains non-specific | Prompt clinical assessment rather than diagnosis from the marker alone |
Clinicians sometimes view values above roughly 10 ng/mL as less likely to be explained by minor benign variation, and very high levels can occur with metastatic disease. These are not diagnostic thresholds. Severe benign disease, assay interference, smoking, and organ dysfunction can complicate interpretation, while some advanced cancers produce little CEA.
Changes also need to be judged against analytical variation. A move from 3.8 to 4.4 ng/mL may not be meaningful, especially if different laboratories or assay systems were used. A repeated rise over several measurements is usually more informative than a small one-time shift.
Benign Causes of High CEA
CEA can rise without cancer, particularly when the elevation is mild. Understanding those causes is essential before interpreting an unexpected result.
Smoking is one of the best-known influences. Current cigarette smokers often have higher CEA values than nonsmokers. Older research also showed that elevated values can fall after smoking cessation. This does not mean a high CEA in a smoker should automatically be dismissed; it means smoking status belongs in the interpretation.
Other non-cancer causes include:
- Liver disease, including cirrhosis and hepatitis. The liver helps clear CEA, so impaired liver function can raise circulating levels.
- Biliary obstruction or cholangitis, especially when inflammation is present.
- Inflammatory bowel disease, such as active ulcerative colitis or Crohn disease.
- Pancreatitis and other inflammatory gastrointestinal conditions.
- Chronic lung disease or infection, including some forms of bronchitis and pneumonia.
- Kidney dysfunction, which can alter clearance of several tumor markers.
- Benign polyps and other gastrointestinal disorders, which may occasionally produce small increases.
Temporary inflammation can make a repeat test useful. If a patient has an acute infection or a flare of inflammatory disease, a clinician may wait for that condition to settle before deciding whether a borderline CEA needs more investigation.
A particularly important point is that liver abnormalities can affect CEA whether or not cancer is present. A person with colorectal cancer and liver dysfunction may therefore have a level influenced by both tumor biology and impaired clearance. Interpretation should incorporate liver tests and imaging rather than assuming the marker reflects tumor burden alone.
Laboratory interference is another uncommon but real explanation. Immunoassays can occasionally be affected by heterophile antibodies or other substances that create an apparently abnormal result. When the number is inconsistent with the clinical picture, repeating the test with another method or laboratory may help resolve the discrepancy.
How CEA Is Used for Colon and Rectal Cancer
CEA has its clearest role in colorectal cancer management, especially after a diagnosis has already been established. It may be measured before surgery, during treatment, and during follow-up when surveillance is appropriate.
Before and after surgery
A baseline preoperative CEA provides a useful comparison point. If it is high before complete tumor removal, clinicians generally expect it to fall afterward. CEA has a biologic half-life of only several days, so persistent elevation weeks after surgery may raise concern for residual disease, metastatic disease, another CEA-producing condition, or a benign cause that was present before surgery.
A normal preoperative CEA does not mean surveillance is unnecessary; it means the marker may be less sensitive for that particular patient. Someone whose tumor never produced much CEA may develop recurrence without a meaningful rise.
Why the pre-treatment baseline matters
CEA monitoring works best when clinicians know how the patient’s tumor behaved before treatment. If the cancer produced a clearly elevated CEA at diagnosis, a later return toward the reference range provides a useful personal benchmark. If the level was normal even with a visible tumor, future normal values carry less reassurance because that tumor may simply be a low CEA producer.
Postoperative timing also matters. CEA does not disappear from the bloodstream instantly after a tumor is removed. Because its circulating half-life is measured in days, clinicians generally allow time for the level to fall before deciding that a persistently high value is abnormal. A result drawn too soon after surgery can therefore be difficult to interpret. The same principle applies after major treatment changes: one number is rarely as informative as a short series of values obtained at clinically appropriate intervals.
A useful comparison is the patient’s nadir, or lowest stable value after treatment. If a survivor’s CEA settled around 2 ng/mL and later rises steadily to 4, 7, and 11 ng/mL, the change from that personal baseline may matter even before the level becomes dramatically high. Conversely, a long-term smoker whose CEA remains stable around 5 to 6 ng/mL may have a very different risk pattern than someone whose value has newly climbed from 1.5 to 6 ng/mL. Context and direction make the number clinically meaningful.
During systemic treatment
In metastatic colorectal cancer, serial CEA can complement imaging and symptom assessment. A sustained decline may support response, while a sustained increase can raise concern for progression. Early in chemotherapy, however, marker fluctuations can occur, so oncologists avoid changing effective therapy based on one unexpected value alone.
CEA is also only one part of modern colorectal cancer assessment. Treatment decisions increasingly depend on molecular features such as RAS, BRAF, mismatch repair, and HER2 status. A colorectal cancer biomarker panel addresses these tumor-specific questions, whereas CEA mainly reflects disease activity and prognosis rather than a targetable mutation.
Surveillance for recurrence
After potentially curative treatment, CEA may be checked periodically in patients for whom finding a recurrence could lead to additional treatment. Guidelines differ in exact schedules and how strongly they recommend CEA when high-quality CT surveillance is already planned. Many follow-up programs use CEA every few months during the first several years, when recurrence risk is highest, then less often later.
The key limitation is sensitivity. Recent systematic reviews have found that a commonly used cutoff around 5 ng/mL misses a meaningful proportion of recurrences. CEA therefore should not replace CT imaging, colonoscopy, or clinical evaluation. A normal result does not prove that a colorectal cancer survivor is recurrence-free.
Testing, Timing, and Interpreting CEA Trends
CEA requires a routine blood draw and usually does not require fasting. The most useful preparation is accurate context: tell the care team about smoking, recent infections, inflammatory disease, liver problems, and whether the sample was drawn at a different laboratory than previous tests.
Serial values should ideally be measured with the same assay. Different commercial tests are not perfectly harmonized, and small differences may appear when laboratories change methods.
When monitoring cancer, clinicians often think in terms of trajectories rather than isolated cutoffs. For example:
- A patient’s CEA is 42 ng/mL before colon-cancer surgery and falls to 3 ng/mL afterward. That pattern is consistent with removal of the major CEA-producing tumor burden.
- A survivor has stable values around 2 to 3 ng/mL, then one measurement of 5.6 ng/mL during a respiratory infection. A repeat after recovery may be more informative than immediate conclusions about recurrence.
- A patient has serial values of 4, 7, 12, and 19 ng/mL over several months. A consistent upward trend is more concerning and commonly triggers imaging or other evaluation.
This is why “CEA velocity” is sometimes discussed informally even though routine clinical decisions are not based on a single universally accepted rate-of-change threshold. Direction, persistence, and magnitude matter.
It is also useful to compare the marker with known treatment events. CEA may fall after effective surgery, radiation, chemotherapy, or targeted therapy. If imaging clearly shows response but the marker briefly behaves differently, the oncology team may repeat the test rather than assuming the treatment has failed.
Other Cancers, Screening Limits, and False Results
CEA can rise in several malignancies besides colorectal cancer, including pancreatic, gastric, lung, breast, ovarian, and medullary thyroid cancers. However, a high blood CEA cannot identify where a cancer originated. If a person without a known malignancy has an unexplained elevation, the workup is guided by symptoms, examination, age-appropriate screening, and clinical risk factors—not by chasing every cancer associated with CEA.
CEA is also not a substitute for established screening. For colorectal cancer, stool tests, colonoscopy, and other guideline-approved strategies detect precancerous lesions or early cancers more effectively than CEA. A person with a normal CEA can still have colorectal cancer, including an early tumor.
The marker’s limitations can be summarized in three ways:
- False negatives: some colorectal cancers and many early tumors produce little CEA.
- False positives: smoking, inflammatory disease, liver dysfunction, and other benign causes can raise it.
- Non-specific positives: multiple cancer types can increase CEA, so the result does not locate the disease.
For broader gastrointestinal oncology, clinicians may combine CEA with imaging, pathology, and other markers. A GI cancer biomarker profile can include very different tests with distinct purposes; they should not be treated as interchangeable blood-screening tests.
What to Do After an Abnormal CEA Result
If you do not have a cancer diagnosis and CEA is unexpectedly high, ask first why the test was ordered. CEA is sometimes obtained during broad blood testing even when it is unlikely to help. A clinician may review smoking status, liver and kidney function, inflammatory symptoms, recent infections, and whether the value is only slightly outside the reference range.
A reasonable next step may be to repeat the test, especially when the elevation is mild and a temporary benign cause is likely. Persistent or substantial elevation usually deserves a more focused medical evaluation, but there is no single CEA number that automatically requires a particular scan.
If you are a colorectal cancer survivor, contact your oncology or surveillance team about a new rise. They may compare it with prior values, repeat the measurement, review symptoms, and order CT or other imaging according to your follow-up plan. Do not assume recurrence from an online cutoff, and do not ignore a rising trend simply because you feel well.
Seek prompt medical care for significant new symptoms such as persistent abdominal pain, unexplained weight loss, blood in the stool, a major change in bowel habits, jaundice, shortness of breath, or progressive weakness. These symptoms have many possible causes, but they deserve clinical assessment regardless of the CEA result.
The most useful question is not “Is my CEA high?” but “How does this value fit with my baseline, trend, smoking status, health conditions, treatment history, and imaging?” That context turns a non-specific laboratory marker into information that can actually guide care.
References
- Current opinions on CEA in the diagnosis and prognosis of colorectal cancer 2026 (Review)
- Advances in carcinoembryonic antigen detection: a review of clinical applications and standardization 2025 (Review)
- The prognostic role of circulating CA19-9 and CEA in patients with colorectal cancer 2025 (Review)
- Significance of carcinoembryonic antigen detection in the early diagnosis of colorectal cancer: A systematic review and meta-analysis 2023 (Systematic Review)
- An Evidence-Based Guideline for Surveillance of Patients after Curative Treatment for Colon and Rectal Cancer 2022 (Guideline)
Disclaimer
This article is for general education and cannot diagnose cancer or interpret an individual CEA result. CEA must be assessed with your medical history, smoking status, treatment history, imaging, and other clinical findings. Discuss a persistent or rising CEA with a qualified clinician, especially after colorectal cancer treatment.