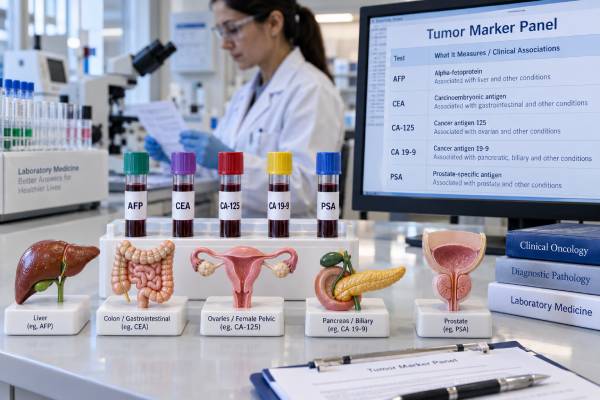
A blood tumor marker panel can include tests such as alpha-fetoprotein (AFP), carcinoembryonic antigen (CEA), cancer antigen 125 (CA-125), cancer antigen 19-9 (CA 19-9), and prostate-specific antigen (PSA). These markers are linked with different organs and cancers, but they do not function as a universal blood test for cancer. Most have limited specificity because benign disease, inflammation, normal physiology, and organ dysfunction can also change their levels. Their strongest uses are targeted: AFP can support liver cancer surveillance in selected high-risk patients and germ cell tumor care; CEA is used mainly in colorectal cancer monitoring; CA-125 is used in ovarian cancer evaluation and monitoring; CA 19-9 is most useful in pancreatic and biliary cancers; and PSA is used in prostate cancer risk assessment and follow-up. A result is meaningful only when matched to the correct clinical question, reference range, imaging, and diagnosis.
- There is no standard five-marker panel that can reliably screen healthy people for all cancers.
- AFP, CEA, CA-125, CA 19-9, and PSA measure different proteins or antigens: each has different cancer and noncancer causes of elevation.
- Reference limits are assay-specific: common cutoffs are useful guides, not universal diagnostic thresholds.
- Tumor-marker trends are often more useful than one isolated result: especially after a cancer diagnosis and during treatment or surveillance.
- An abnormal panel does not prove cancer: benign liver, bowel, pancreatic, biliary, ovarian, prostate, inflammatory, and other conditions can raise these markers.
Table of Contents
- What a Blood Tumor Marker Panel Can and Cannot Do
- AFP: Alpha-Fetoprotein
- CEA: Carcinoembryonic Antigen
- CA-125: Cancer Antigen 125
- CA 19-9: Cancer Antigen 19-9
- PSA: Prostate-Specific Antigen
- How to Interpret a Panel Result
What a Blood Tumor Marker Panel Can and Cannot Do
Tumor markers are substances measured in blood, urine, tissue, or other samples that can provide information about a cancer. The term sounds more specific than it is. Many serum tumor markers are also produced by healthy tissue or become elevated in benign disease.
For that reason, ordering AFP, CEA, CA-125, CA 19-9, and PSA together does not create a reliable general cancer-screening test. A marker can have acceptable performance in a carefully selected population yet perform poorly in healthy people where cancer prevalence is low. Even a fairly specific test can generate more false positives than true positives when used indiscriminately.
The markers in this panel have different established uses:
| Marker | Common clinical association | Typical role |
|---|---|---|
| AFP | Hepatocellular carcinoma; germ cell tumors | HCC surveillance in selected high-risk patients; germ cell tumor diagnosis/monitoring |
| CEA | Colorectal cancer; several other adenocarcinomas | Baseline prognosis and monitoring, especially colorectal cancer |
| CA-125 | Epithelial ovarian cancer | Evaluation of an adnexal mass and monitoring known disease |
| CA 19-9 | Pancreatic and biliary cancers | Monitoring, prognosis, and support for diagnosis in the right context |
| PSA | Prostate tissue and prostate cancer | Risk assessment, screening discussions, diagnosis pathway, and follow-up |
The exact number must also be interpreted using the laboratory’s method. Tumor-marker assays are not perfectly harmonized across manufacturers. A result obtained on one platform may not be numerically interchangeable with a result from another platform. This is one reason long-term monitoring is easier when the same laboratory and assay are used.
When a clinician orders a blood tumor marker panel, the most useful question is not “Which markers are high?” but “Why was each marker ordered, and does this result change the probability of a specific disease?”
AFP: Alpha-Fetoprotein
AFP is a fetal protein produced mainly by the yolk sac and fetal liver. Levels are high during fetal development and fall to very low concentrations after birth. In nonpregnant adults, many laboratories use an upper reference limit around 8–10 ng/mL, although the exact interval varies.
AFP has two major cancer-related uses: hepatocellular carcinoma, or HCC, and germ cell tumors. In people at increased HCC risk, particularly selected patients with cirrhosis or chronic hepatitis B, liver surveillance may combine ultrasound with AFP. The 2023 AASLD guidance uses an AFP level of 20 ng/mL or an increasing trend as one possible trigger for diagnostic imaging, but AFP alone does not diagnose HCC.
The AFP blood test is also central to testicular and ovarian germ cell tumor assessment. Yolk sac tumor and embryonal components can produce AFP. Pure seminoma should not significantly elevate AFP; an unexplained AFP elevation in a presumed seminoma raises concern for a nonseminomatous component.
Common noncancer causes include pregnancy and active liver injury. Chronic hepatitis, cirrhosis, and liver regeneration can produce mild or moderate elevations. This is why an AFP result is interpreted with liver enzymes, imaging, underlying liver disease, and the trend over time.
A very high AFP can increase concern for HCC or a germ cell tumor, but no single concentration is perfectly diagnostic. Some HCCs make little or no AFP, while benign liver disease can occasionally produce substantial increases.
CEA: Carcinoembryonic Antigen
CEA is a glycoprotein involved in cell adhesion and is produced in fetal gastrointestinal tissue. Adults normally have low circulating levels. Many laboratories use an upper limit near 3 ng/mL in nonsmokers and around 5 ng/mL in smokers, but ranges vary.
CEA is most strongly associated with colorectal cancer in routine clinical practice. It is often measured before surgery or systemic treatment to establish a baseline and can be followed afterward in patients for whom surveillance is appropriate. A rising CEA in a person previously treated for colorectal cancer can trigger additional evaluation for recurrence.
The CEA blood test is not sufficiently sensitive or specific to screen the general population for colon cancer. Colonoscopy and evidence-based stool tests have very different roles in colorectal cancer screening.
CEA can also be elevated in pancreatic, gastric, lung, breast, ovarian, and other cancers, but this broad association reduces its ability to identify where a cancer is located. Benign causes include cigarette smoking, inflammatory bowel disease, pancreatitis, liver disease, biliary inflammation, and some pulmonary conditions.
In known cancer, serial CEA values can be more informative than a single result. A sustained rise, especially when it agrees with symptoms or imaging, deserves investigation. A small isolated increase should be confirmed and interpreted for smoking, inflammation, liver function, and laboratory variation before it is treated as recurrence.
CA-125: Cancer Antigen 125
CA-125 measures an epitope associated with MUC16, a large cell-surface protein. A commonly used upper reference limit is 35 U/mL, but the assay and clinical setting matter.
CA-125 is best known as an ovarian cancer marker, particularly for epithelial ovarian cancers. It can support evaluation of an adnexal or pelvic mass and is commonly followed when ovarian cancer is known to produce it. Falling levels during treatment often correlate with response, while a confirmed rise after treatment may indicate recurrence.
However, the CA-125 blood test is not a stand-alone screening test for average-risk, asymptomatic people. Many early ovarian cancers have normal CA-125, while many benign conditions cause elevations.
The peritoneum, pleura, endometrium, and other tissues can contribute to CA-125. Levels may rise with menstruation, pregnancy, endometriosis, uterine fibroids, pelvic inflammatory disease, liver disease with ascites, heart failure with serosal fluid, and other inflammatory states. Postmenopausal status changes the meaning of an abnormal result because many benign gynecologic causes are less common after menopause.
When an ovarian mass is present, CA-125 may be combined with ultrasound findings, menopausal status, clinical risk factors, and sometimes other biomarkers. The result contributes to risk assessment; it does not establish histology or substitute for pathology.
CA 19-9: Cancer Antigen 19-9
CA 19-9 is a carbohydrate antigen related to the Lewis blood-group system. Many laboratories use an upper reference limit near 37 U/mL. It is most often used in pancreatic ductal adenocarcinoma and biliary tract cancers.
The CA 19-9 blood test may support the overall assessment of a pancreatic or bile duct mass, provide prognostic information, and help monitor treatment when the cancer produces the marker. It should not be used by itself to diagnose pancreatic cancer, and it is not recommended as general-population screening.
A major limitation is biliary obstruction. Cholestasis and cholangitis can push CA 19-9 high even without cancer. In a jaundiced patient, clinicians often interpret the value after biliary drainage and treatment of infection when possible. Pancreatitis and other benign hepatobiliary diseases can also elevate it.
Another limitation is biology: people who lack functional Lewis antigen synthesis may produce little or no CA 19-9. This means a normal CA 19-9 cannot exclude pancreatic or biliary cancer, even in advanced disease. A person whose tumor never produced CA 19-9 will not gain much from serial monitoring.
As with other markers, the trajectory matters. A substantial fall during effective systemic therapy can support response, while a sustained rise can raise concern for progression. Imaging and clinical status remain essential because CA 19-9 can move for noncancer reasons.
PSA: Prostate-Specific Antigen
PSA is a serine protease made by prostate epithelial cells. Unlike many markers in a broad panel, it is organ-specific rather than cancer-specific. Benign prostate tissue makes PSA, and conditions that disrupt prostate architecture can increase the amount entering the bloodstream.
Historically, 4.0 ng/mL was often treated as a cutoff, but modern prostate cancer assessment does not rely on one universal threshold. Age, prostate volume, family history, ancestry, prior values, medications, examination, MRI findings, and personal preferences all influence decisions.
The PSA test is used for risk-adapted early detection and is central to follow-up after prostate cancer treatment. Screening recommendations vary by organization and country, but generally emphasize informed or shared decision-making rather than automatic population testing at one fixed age.
Benign prostatic hyperplasia, prostatitis, urinary retention, recent prostate manipulation, and ejaculation can affect PSA. Medications such as 5-alpha-reductase inhibitors can lower it substantially. A moderately elevated PSA therefore does not mean prostate cancer is present.
When PSA is elevated, additional tools may refine risk before biopsy. These can include repeat PSA, PSA density, percent free PSA, MRI, the free PSA test, or multivariable biomarker tests. After prostatectomy, PSA has a different interpretation because very little prostate tissue should remain, so low-level recurrence thresholds are much lower than screening thresholds.
How to Interpret a Panel Result
A panel can look alarming when several numbers are flagged, but interpretation should proceed marker by marker.
First, confirm the clinical purpose. Was the test ordered to monitor a known cancer, evaluate a specific mass, assess a high-risk liver patient, or investigate symptoms? A marker that is appropriate for monitoring a diagnosed cancer may be inappropriate as an untargeted screening test.
Second, use the laboratory’s own reference interval. Common limits such as AFP 10 ng/mL, CA-125 35 U/mL, CA 19-9 37 U/mL, or PSA 4 ng/mL are not universal diagnostic boundaries. CEA reference limits also vary with method and smoking status.
Third, look for benign explanations. Liver inflammation can affect AFP and CEA. Bile duct obstruction can markedly raise CA 19-9. Menstruation, endometriosis, pregnancy, and serosal inflammation can raise CA-125. Smoking can raise CEA. Benign prostate enlargement or inflammation can raise PSA.
Fourth, compare with previous results obtained on the same assay when possible. A stable mild elevation over years may have a different meaning from a rapid upward trend. Marker harmonization studies show that different commercial assays can yield meaningfully different values, so an apparent jump after changing laboratories deserves caution.
Fifth, correlate the panel with disease-specific tests. A high AFP in a cirrhotic patient may call for liver CT or MRI; a rising CEA after colon cancer treatment may lead to recurrence imaging; high CA 19-9 with jaundice requires evaluation for biliary obstruction; elevated PSA may lead to repeat testing, MRI, or urologic assessment; high CA-125 with a pelvic mass is interpreted with ultrasound and gynecologic risk factors.
What if more than one marker is high?
Multiple abnormal results can occur for reasons that have nothing to do with having multiple cancers. A patient with advanced liver disease, for example, may have altered AFP from hepatic regeneration, CEA from impaired hepatic clearance or smoking, and CA-125 from ascites irritating the peritoneum. A person with pancreatitis and biliary obstruction may have an elevated CA 19-9 and a modest CEA increase. The shared noncancer condition can therefore be more important than the number of flagged tests.
The pattern becomes more meaningful when it matches a known tumor. In a person with a pancreatic mass, CA 19-9 may be the most relevant marker, while a slightly high CA-125 may simply reflect peritoneal irritation or advanced disease and does not independently diagnose ovarian cancer. In a man with a prostate nodule and high PSA, an incidental borderline CEA has little diagnostic value unless there is a separate gastrointestinal indication to investigate it.
The opposite problem also occurs: a panel may be entirely normal despite cancer. A Lewis-antigen-negative person may not produce CA 19-9. Some ovarian cancers produce little CA-125. Many hepatocellular carcinomas have AFP below traditional thresholds. Prostate cancer can occur at PSA levels below historical cutoffs. This is why tumor markers should not be used as a “rule-out panel.”
Why repeat testing can be useful
When an unexpected result is only mildly abnormal, repeating it under more stable conditions can prevent unnecessary procedures. Clinicians may first treat cholangitis, allow acute hepatitis to improve, wait for menstruation-related CA-125 changes to pass, or repeat PSA after urinary infection resolves. A persistent abnormality is generally more informative than a one-time value obtained during an acute illness.
Repeat testing should not delay evaluation when there is a concerning mass, progressive symptoms, very abnormal imaging, or a strong disease-specific signal. The purpose of repetition is to distinguish biologic trend from temporary noise, not to postpone appropriate diagnosis.
The timing of a repeat should match the likely cause. PSA may be repeated after a urinary infection or transient prostate irritation has settled; CA 19-9 may be rechecked after biliary drainage; CA-125 may be reconsidered after an acute inflammatory or gynecologic event; and liver-related AFP changes may need to be compared with liver enzymes and imaging. There is no single repeat interval that fits every marker.
Do not use a negative panel as reassurance that cancer is absent. Many cancers do not release these markers, early disease may be marker-negative, and some people cannot produce a specific antigen. Conversely, do not assume that multiple mild elevations represent metastatic cancer. Systemic inflammation or organ dysfunction can affect more than one marker at once.
The most clinically useful tumor-marker strategy is targeted rather than broad: choose a marker with a validated role for the patient’s disease or risk state, establish a reliable baseline, and interpret serial values with imaging and clinical findings. That approach reduces false alarms while preserving the real value of serum biomarkers in oncology.
References
- Carcinoembryonic Antigen, Carbohydrate Antigen 19-9, Cancer Antigen 125, Prostate-Specific Antigen and Other Cancer Markers: A Primer on Commonly Used Cancer Markers 2023 (Review)
- Factors influencing blood tumor marker concentrations in the absence of neoplasia 2024 (Review)
- Investigating the Current Harmonization Status of Tumor Markers Using Global External Quality Assessment Programs: A Feasibility Study. 2024
- AASLD Practice Guidance on prevention, diagnosis, and treatment of hepatocellular carcinoma 2023 (Practice Guidance)
- EAU-EANM-ESTRO-ESUR-ISUP-SIOG Guidelines on Prostate Cancer-2024 Update. Part I: Screening, Diagnosis, and Local Treatment with Curative Intent. 2024 (Practice Guideline)
- An Evidence-Based Guideline for Surveillance of Patients after Curative Treatment for Colon and Rectal Cancer. 2022 (Guideline)
Disclaimer
Blood tumor markers cannot diagnose or exclude cancer as a group. Abnormal AFP, CEA, CA-125, CA 19-9, or PSA results need interpretation in the context of symptoms, benign conditions, imaging, pathology, and the laboratory method. Discuss unexpected or changing results with a qualified clinician rather than using a panel as a self-screening test.