Cancer antigen 125, usually called CA-125, is a protein measured in blood that is most useful for following certain ovarian, fallopian tube, and primary peritoneal cancers over time. A high CA-125 result does not by itself mean cancer. Menstruation, endometriosis, pregnancy, uterine fibroids, pelvic inflammation, liver disease, heart failure, and other conditions can raise the marker, sometimes substantially. The test also has important limits: some ovarian cancers produce little CA-125, and early-stage disease may occur with a normal result. For those reasons, clinicians interpret CA-125 alongside symptoms, imaging, examination findings, pathology, and the pattern of results over time. In someone already diagnosed with CA-125-producing ovarian cancer, serial measurements can help show whether treatment is working or whether disease may be returning. For an unexplained pelvic mass, CA-125 may contribute to risk assessment, but it cannot diagnose or exclude cancer on its own.
- A common reference cutoff is about 35 U/mL, but the laboratory’s own reference interval is the one that applies to your result.
- A high CA-125 is not cancer-specific: benign gynecologic, inflammatory, liver, heart, and pregnancy-related conditions can increase it.
- CA-125 is most useful as a trend: falling levels during treatment often support a response, while a sustained rise may prompt further evaluation.
- A normal CA-125 does not rule out ovarian cancer, especially in early-stage disease or tumor types that release little CA-125.
- No special preparation is usually needed, but timing around menstruation and relevant medical conditions can affect interpretation.
Table of Contents
- What the CA-125 Blood Test Measures
- CA-125 Normal Range and What High Levels Mean
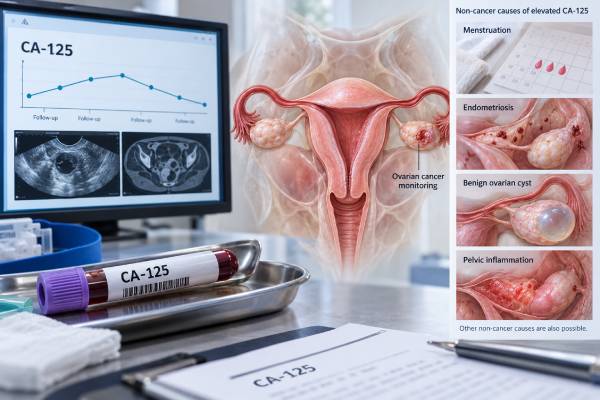
- Non-Cancer Causes of a High CA-125
- How CA-125 Is Used in Ovarian Cancer
- How the Test Is Done and How to Read Trends
- Why CA-125 Is Not a Stand-Alone Screening Test
- Limitations, Follow-Up, and When to Seek Care
What the CA-125 Blood Test Measures
CA-125 measures a circulating form of MUC16, a large protein found on the surface of several tissues and many epithelial ovarian cancer cells. The number reported by the laboratory reflects how much CA-125 is present in a blood sample, usually in units per milliliter (U/mL) or an equivalent unit such as kU/L.
The marker is often described as an “ovarian cancer blood test,” but that description can be misleading. CA-125 is not made only by ovarian cancer. Tissues lining the abdomen, chest, uterus, fallopian tubes, and other surfaces can release CA-125 when they are irritated or inflamed. That is why the result must be interpreted in context.
The test has three main clinical roles:
- Monitoring treatment in people whose ovarian, fallopian tube, or primary peritoneal cancer produces CA-125.
- Following for possible recurrence after treatment in selected patients, usually together with symptoms, examination, and imaging when indicated.
- Helping assess a pelvic or adnexal mass, especially after menopause, as one part of a broader risk evaluation.
CA-125 is only one member of a larger group of blood tumor markers. Tumor markers are best thought of as clues. They can add useful information, but most cannot establish a cancer diagnosis by themselves.
A single CA-125 value can be less informative than a sequence of values measured under similar conditions. If a patient begins treatment with a clearly elevated CA-125, the direction and size of change may help the oncology team judge response. If the tumor never raised CA-125 in the first place, the test may have little value for monitoring that individual.
CA-125 Normal Range and What High Levels Mean
Many laboratories use 35 U/mL or lower as a reference cutoff, but reference intervals can differ by assay. A result slightly above 35 U/mL is not automatically abnormal in a clinically meaningful sense, and a value below 35 U/mL is not a guarantee that cancer is absent.
A practical way to read the number is to ask four questions: How high is it? Is it changing? What is happening clinically? Is there another plausible cause?
| Finding | What it may mean | What usually matters next |
|---|---|---|
| Within the laboratory reference range | Reassuring in some settings, but does not exclude ovarian cancer | Symptoms, imaging, risk factors, and tumor type |
| Mild elevation | Can occur with many benign conditions or cancer | Repeat testing or clinical evaluation if appropriate |
| Marked elevation | Raises concern in the right clinical setting but is still not diagnostic | Imaging, specialist assessment, and tissue diagnosis when indicated |
| Falling serial values during treatment | Often supports treatment response when CA-125 was elevated at baseline | Compare with symptoms and imaging |
| Sustained or confirmed rise after treatment | May precede clinically detectable recurrence | Discuss confirmatory evaluation rather than acting on one result alone |
There is no CA-125 level that proves cancer. Very high values are more concerning when a person has a suspicious pelvic mass, ascites, weight loss, or other features of malignancy, but benign conditions can occasionally produce large increases. The reverse is also true: some people with ovarian cancer have only a modest elevation or a normal CA-125.
Menopausal status changes how clinicians interpret the result. Benign causes of elevation are more common in premenopausal people, so the specificity of CA-125 is lower. In a postmenopausal person with a suspicious adnexal mass, an elevated result generally carries more concern and may be incorporated into formal risk tools. Tests such as HE4 and the ROMA score may also be considered in some clinical settings, but none replaces imaging or tissue diagnosis.
Non-Cancer Causes of a High CA-125
A high CA-125 frequently comes from conditions other than cancer. This happens because CA-125 can rise when tissues lining body cavities or reproductive organs are inflamed, stretched, or otherwise irritated.
Common non-cancer explanations include:
- Menstruation. Levels can rise around the menstrual period, especially in people with endometriosis.
- Endometriosis. Ectopic endometrial tissue can produce substantial CA-125 elevations, particularly with extensive disease or an endometrioma.
- Pregnancy. CA-125 may be higher in early pregnancy and around delivery.
- Uterine fibroids or adenomyosis. These benign uterine conditions can increase the marker.
- Pelvic inflammatory disease or other pelvic inflammation. Inflammation can stimulate CA-125 release.
- Benign ovarian cysts. Some cysts and torsion-related inflammation can raise levels.
- Liver disease. Cirrhosis, especially with ascites, is a well-recognized cause of elevation.
- Fluid in body cavities. Ascites or pleural effusion from non-cancer causes may raise CA-125 because mesothelial surfaces release the protein.
- Heart failure. Congestion and serosal fluid can increase CA-125.
- Recent surgery or significant inflammation. Tissue irritation may temporarily influence the result.
A useful clinical distinction is whether the result is isolated and unexpected or occurs in a person with known cancer. In an otherwise well premenopausal person, a mild elevation during menstruation may be interpreted very differently from a steadily rising marker in someone receiving ovarian cancer follow-up.
Other cancers can also elevate CA-125, including cancers of the endometrium, fallopian tube, pancreas, lung, breast, and gastrointestinal tract. This is another reason the test should not be used to determine where a cancer started without additional evaluation.
When a benign explanation is plausible, a clinician may choose to repeat CA-125 after the temporary factor has resolved. For example, repeating the test outside menstruation can sometimes clarify a borderline result. The decision to repeat, image, or refer depends on the whole clinical picture rather than a fixed number.
How CA-125 Is Used in Ovarian Cancer
CA-125 is most valuable after ovarian cancer is suspected or diagnosed, not as a stand-alone screening test for the general population. Its usefulness depends on the cancer subtype and whether that individual tumor releases the marker.
Assessing a pelvic mass
When imaging shows an ovarian or adnexal mass, CA-125 may help estimate the chance that the mass is malignant. It is particularly informative after menopause, when benign causes of elevation are less frequent. Clinicians may combine CA-125 with ultrasound features, menopausal status, HE4, or other variables.
This is risk assessment, not diagnosis. A suspicious mass generally requires specialist evaluation, and a definitive cancer diagnosis usually depends on pathology from surgery or biopsy. A broader ovarian cancer biomarker panel may be relevant after diagnosis because inherited and tumor DNA markers can influence treatment, but those molecular tests answer different questions from CA-125.
Monitoring treatment response
If CA-125 is high before treatment, serial measurements can show whether the marker is falling. A substantial, sustained decline often parallels a reduction in tumor burden. Conversely, a rising value during therapy may raise concern that treatment is not controlling the disease.
Oncology teams do not usually make major treatment decisions from CA-125 alone. Symptoms, physical findings, imaging, treatment timing, and sometimes other laboratory data are considered together. A marker can change before scans do, but it can also fluctuate for reasons unrelated to tumor growth.
Follow-up after treatment
A rising CA-125 can precede symptoms or imaging evidence of recurrence by weeks or months in some patients. That sounds like an obvious advantage, but earlier detection does not automatically mean earlier treatment improves survival. Clinical trials have shown that starting chemotherapy solely because CA-125 rises, before symptoms or radiologic evidence of relapse, does not necessarily improve overall survival and may expose patients to treatment sooner.
For that reason, follow-up strategies differ. Some patients and clinicians choose routine CA-125 testing; others emphasize symptoms and examinations, with imaging or marker testing when clinically indicated. Decisions are individualized based on cancer type, treatment options, potential eligibility for surgery or targeted therapy, and the patient’s preferences about knowing a marker has risen before disease is otherwise visible.
How the Test Is Done and How to Read Trends
CA-125 requires a standard blood draw. Most people do not need to fast. There is no special preparation comparable with some hormone or metabolic tests, but interpretation may be improved when the clinician knows about menstruation, pregnancy, recent surgery, liver disease, heart failure, endometriosis, and other conditions that can change the level.
Results are most comparable when follow-up samples are measured by the same laboratory method. Different assays can produce small systematic differences, so an apparent change after switching laboratories may not reflect a true biological change.
When CA-125 is being used for cancer monitoring, the pattern is usually more important than a single measurement. Consider these examples:
- A patient begins chemotherapy with CA-125 at 620 U/mL, then falls to 180, 65, and 28 U/mL. That steady decline supports response if the clinical and imaging findings agree.
- A patient has remained around 18–24 U/mL for months, then has one result of 39 U/mL. The small isolated increase may justify repeat testing rather than an immediate conclusion of recurrence.
- A patient has confirmed serial increases from 40 to 70 to 130 U/mL after treatment. The trend is more concerning and may prompt imaging or other evaluation, particularly if symptoms are developing.
Formal research criteria sometimes define CA-125 response or progression using percentage reductions, doubling rules, or confirmation on repeat samples. In routine care, clinicians may use those frameworks but still interpret them alongside the individual patient’s baseline and treatment course.
Because CA-125 is not a general screening marker, an asymptomatic person should not order repeated tests simply to “check for ovarian cancer.” Screening average-risk people with CA-125 has not been shown to provide the combination of sensitivity, specificity, and survival benefit needed for routine use. If hereditary risk is a concern, family history and genetic counseling are more appropriate starting points than serial tumor-marker testing.
Why CA-125 Is Not a Stand-Alone Screening Test
CA-125 is not recommended as a stand-alone screening test for people at average risk who have no symptoms. A screening test must do more than find some cancers. It needs to detect disease early enough to improve outcomes while keeping false-positive results low enough to avoid unnecessary scans, procedures, and surgery. CA-125 has not met that standard by itself.
One problem is that early-stage ovarian cancer may produce little or no CA-125. Another is that benign conditions are common, especially before menopause, so many elevated results would not represent cancer. Even combining CA-125 with ultrasound has not established a routine population-screening strategy that clearly reduces ovarian-cancer mortality.
People with a strong hereditary risk need a different kind of discussion. A family history of ovarian, fallopian tube, primary peritoneal, breast, pancreatic, or aggressive prostate cancer may raise concern for inherited cancer-predisposition genes such as BRCA1 or BRCA2. In that setting, genetic counseling and risk-reduction planning generally provide more actionable information than repeatedly checking CA-125. A normal marker cannot reassure someone that a hereditary risk has disappeared.
Symptoms also change the situation. Testing a person with persistent bloating, pelvic pressure, early satiety, or a newly discovered adnexal mass is diagnostic evaluation, not population screening. CA-125 may be useful as part of that workup. The same number can therefore have very different significance depending on why the test was ordered.
The distinction matters because unnecessary tumor-marker testing can start a cascade: a borderline result leads to repeat blood tests, then imaging, then invasive procedures that may ultimately show a benign cause. Using CA-125 where it has demonstrated clinical value helps preserve its usefulness while reducing avoidable harm.
Limitations, Follow-Up, and When to Seek Care
The biggest mistake is treating CA-125 as a yes-or-no cancer test. It has important false positives and false negatives, and the meaning changes with age, menopausal status, symptoms, imaging findings, and whether cancer is already known.
Key limitations include:
- Low specificity in many benign conditions. A raised value can create anxiety and unnecessary testing if interpreted without context.
- Limited sensitivity for early ovarian cancer. Some early cancers do not raise CA-125 enough to cross the usual cutoff.
- Variation by tumor subtype. High-grade serous ovarian cancers often produce CA-125, while some mucinous and other tumors may not.
- Biological and laboratory variability. Small changes can occur without meaningful change in disease.
- No proven value as stand-alone population screening. The test should not substitute for evaluation of persistent symptoms or appropriate hereditary-risk assessment.
If your CA-125 is high and you do not have a cancer diagnosis, the next step is usually to look for the clinical reason it was ordered. A clinician may review symptoms, menstrual timing, pregnancy possibility, medical history, pelvic examination findings, and ultrasound or other imaging. Depending on the setting, repeating the test after a short interval may be reasonable.
Seek prompt medical assessment for persistent or worsening symptoms that can accompany ovarian disease, such as new abdominal or pelvic pain, increasing abdominal size or bloating, early fullness with meals, urinary urgency or frequency, unexplained weight loss, or persistent changes in bowel habits. These symptoms are common and often have benign causes, but persistence deserves evaluation even when CA-125 is normal.
If you are already being treated for ovarian cancer, contact your oncology team about a meaningful marker rise rather than trying to interpret the number in isolation. Urgent care is more appropriate for severe abdominal pain, repeated vomiting, inability to keep fluids down, shortness of breath, rapidly increasing abdominal swelling, fainting, or other acute symptoms. The safest interpretation of CA-125 is always one that connects the laboratory value to the person, the timeline, and the rest of the medical evidence.
References
- Newly diagnosed and relapsed epithelial ovarian cancer: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up 2023 (Guideline)
- Evaluation of follow-up strategies for women with epithelial ovarian cancer following completion of primary treatment 2023 (Systematic Review)
- Factors influencing blood tumor marker concentrations in the absence of neoplasia 2024 (Review)
- CA-125:CA72-4 ratio – towards a promising cost-effective tool in ovarian cancer diagnosis and monitoring of post-menopausal women under hormone treatment 2024 (Review)
- Clinical Use of Cancer Biomarkers in Epithelial Ovarian Cancer: Updated Guidelines From the European Group on Tumor Markers 2016 (Guideline)
Disclaimer
This article is for general educational information and does not diagnose ovarian cancer or interpret an individual CA-125 result. CA-125 should be assessed with your symptoms, medical history, imaging, and other clinical findings. Contact a qualified clinician for personalized advice, especially if you have a pelvic mass, persistent symptoms, or a changing tumor-marker trend.