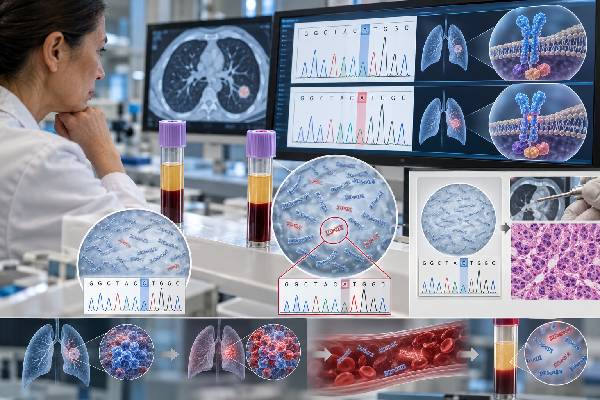
An EGFR T790M liquid biopsy looks for a specific resistance mutation in tumor DNA circulating in the blood of someone with non-small cell lung cancer (NSCLC). T790M became especially important because it is a common mechanism of resistance after first- or second-generation EGFR tyrosine kinase inhibitors such as erlotinib, gefitinib, or afatinib, and it can identify tumors that are sensitive to the third-generation EGFR inhibitor osimertinib. Today, osimertinib is commonly used earlier in EGFR-mutated lung cancer, so T790M testing is not the dominant resistance question in every patient.
A blood test can detect T790M without an invasive biopsy and can sample DNA released from more than one tumor site. Its main limitation is false-negative testing when little circulating tumor DNA, or ctDNA, is present. A negative plasma result therefore does not reliably exclude T790M or another resistance mechanism, and tissue testing may still be needed when feasible.
- A positive EGFR T790M liquid-biopsy result means the resistance mutation was detected in plasma ctDNA and should be interpreted with the patient’s prior EGFR treatment and current drug options.
- A negative T790M blood result does not rule out the mutation because some lung cancers shed too little ctDNA for reliable plasma detection.
- T790M is most classically associated with resistance after first- or second-generation EGFR inhibitors; resistance after first-line osimertinib often involves other mechanisms.
- No fasting is usually required for the blood draw, but the test must use the collection and handling method specified by the laboratory.
- When plasma testing is negative or non-informative and treatment depends on the answer, tumor tissue or another appropriate specimen may be recommended.
Table of Contents
- What EGFR T790M Is
- When a Liquid Biopsy Is Used
- How the Blood Test Works
- Positive, Negative, and Low-ctDNA Results
- How T790M Affects Treatment Decisions
- Limitations and Resistance Beyond T790M
- What to Discuss After Testing
What EGFR T790M Is
EGFR is a gene that encodes the epidermal growth factor receptor, a protein that helps regulate cell growth. Some lung adenocarcinomas contain activating EGFR mutations, most commonly exon 19 deletions or the exon 21 L858R mutation. These changes can make the cancer dependent on EGFR signaling and sensitive to EGFR-targeted tyrosine kinase inhibitors, or TKIs.
T790M is a secondary EGFR mutation in which threonine is replaced by methionine at amino-acid position 790. It changes the receptor’s kinase domain in a way that reduces the effectiveness of many older EGFR inhibitors. Historically, T790M accounted for a large share of acquired resistance after treatment with first-generation agents such as erlotinib or gefitinib and second-generation agents such as afatinib.
The mutation can exist in only part of the cancer at first and become more prominent under drug pressure. That is why a tumor that originally tested only for an EGFR sensitizing mutation can later acquire T790M after months or years of therapy.
A broad lung cancer liquid biopsy can search for T790M together with other genomic changes. A focused assay may test only a smaller set of EGFR variants. The right test depends on the clinical question, prior treatment, available tissue, and whether a broad resistance profile is needed.
T790M should not be confused with an inherited EGFR variant in routine interpretation. In this setting it is usually a somatic tumor alteration. Rare germline T790M variants have been described, but a plasma cancer test is not designed by itself to diagnose an inherited cancer syndrome.
When a Liquid Biopsy Is Used
Liquid biopsy is most useful when the cancer needs molecular reassessment and obtaining fresh tumor tissue would be difficult, slow, risky, or incomplete. It can also complement tissue because DNA in the bloodstream may represent more than one metastatic site.
For T790M specifically, the classic scenario is an EGFR-mutated NSCLC that has progressed after a first- or second-generation EGFR TKI. The clinician may order plasma testing to determine whether T790M emerged and whether an appropriate T790M-directed treatment strategy is available.
The landscape has changed because osimertinib is now widely used as a preferred first-line EGFR TKI and in other settings. When disease progresses on osimertinib, repeating a test that looks only for T790M can miss more relevant resistance changes. A broader lung cancer resistance mutation panel may be more informative because post-osimertinib resistance can involve EGFR C797S and other EGFR changes, MET amplification, HER2 alterations, gene fusions, pathway mutations, or histologic transformation.
Liquid biopsy may also be ordered at the time of initial advanced NSCLC diagnosis when tissue is insufficient or rapid molecular information is needed. In that setting, the main goal is usually to identify an actionable driver mutation rather than specifically to find T790M.
Testing can also be useful when a previous tissue specimen is old. Resistance is an evolutionary process, so a diagnostic biopsy obtained before years of therapy may no longer represent the dominant clones at progression. Plasma sampling can provide a current molecular snapshot without depending on archival tissue. If the blood result identifies a new resistance alteration, it may help prioritize the next biopsy site or treatment discussion.
The timing of testing should match a real clinical decision. Repeating T790M testing at very short intervals without evidence of progression is usually less useful than testing when resistance is suspected. In selected research or monitoring programs, serial ctDNA may be used more frequently, but routine practice is guided by the disease setting and the available validated assays.
Plasma testing is not a substitute for histology. A tissue biopsy establishes cancer type and can reveal transformation to small-cell lung cancer or another histologic pattern that ctDNA alone cannot diagnose reliably.
How the Blood Test Works
The test begins with a peripheral blood draw. Plasma is separated from blood cells, and cell-free DNA is extracted. The tumor-derived portion of that material is ctDNA. Laboratories then use a molecular method such as digital PCR, real-time PCR, or next-generation sequencing (NGS) to search for EGFR variants.
PCR-based assays can be highly sensitive for predefined mutations such as T790M. NGS panels examine many genes at once and may identify alternative resistance mechanisms in the same sample. This broader approach is often valuable when the cause of progression is unknown.
A typical result may include:
- whether the original activating EGFR mutation is detected;
- whether T790M is detected;
- variant allele frequency, when reported;
- additional resistance or co-occurring alterations;
- comments about assay sensitivity or insufficient ctDNA;
- companion-diagnostic information for specific drugs, when applicable.
Variant allele frequency is not the same as the percentage of tumor in the body. It describes how frequently a variant appears among sequencing reads at that genomic location. A ctDNA tumor fraction estimate, if reported, is a broader measure of how much of the plasma cfDNA appears tumor-derived.
When both the original sensitizing EGFR mutation and T790M are detected, their relative allele frequencies can sometimes offer clues about clonal composition, but they should not be converted into a simple percentage of resistant cancer cells. Copy-number changes, subclonality, DNA shedding from different metastatic sites, and assay characteristics all affect those numbers. Clinical interpretation therefore relies on the presence and pattern of alterations more than on a homemade ratio between two VAFs.
No special diet is generally required before sampling. The laboratory’s collection tube and shipping instructions are more important because breakdown of normal blood cells can release genomic DNA and dilute the tumor signal.
The ordering clinician should also tell the laboratory the cancer type and relevant treatment history when the requisition requests it, because those details can influence report annotation and companion-diagnostic interpretation.
Positive, Negative, and Low-ctDNA Results
A positive T790M result means the assay found the mutation in plasma at or above its validated detection threshold. In a patient whose clinical history fits acquired resistance after an earlier-generation EGFR TKI, this can be a clinically actionable finding. The full report still matters because the original sensitizing EGFR mutation, other resistance changes, and the exact companion-diagnostic labeling can affect treatment decisions.
A positive result is generally more informative than a negative one because plasma assays can miss mutations when the tumor does not release enough DNA. This asymmetry is central to liquid-biopsy interpretation.
A negative T790M result has several possible meanings:
- the cancer truly does not contain T790M;
- T790M is present in tissue but below the plasma assay’s detection limit;
- the tumor is shedding little or no ctDNA at the time of sampling;
- resistance is caused by another genomic mechanism;
- resistance is non-genomic, such as a histologic transformation that requires tissue assessment.
Low ctDNA is more common with lower-volume disease and some patterns of metastatic spread. Disease confined mainly to the brain or thorax may produce less detectable plasma ctDNA than extensive extracranial metastatic disease. Sensitivity also varies by platform and mutation type.
If the test reports the original EGFR driver mutation but not T790M, the sample clearly contains some tumor DNA, making the negative T790M finding more informative than a sample in which no tumor-associated alterations are found at all. It still does not make the negative result absolute.
When a plasma result is non-informative, guidelines and expert recommendations support reflex tumor testing when feasible. This principle applies broadly to ctDNA testing: a negative blood test should not be treated as proof that the tumor is genomically negative when the amount of tumor DNA is uncertain.
How T790M Affects Treatment Decisions
T790M became clinically important because osimertinib was developed to inhibit sensitizing EGFR mutations and T790M while sparing wild-type EGFR more effectively than earlier TKIs. It was first established in patients whose EGFR-mutated NSCLC progressed after earlier EGFR TKIs and tested positive for T790M.
Today, treatment decisions require more context. Osimertinib is commonly used as first-line therapy for advanced NSCLC with common sensitizing EGFR mutations, so many patients never enter the historical sequence of older TKI followed by T790M testing. A person already receiving osimertinib who develops progression usually needs evaluation for post-osimertinib resistance, not simply another confirmation of T790M.
For someone who has not previously received osimertinib and who develops T790M after an older EGFR inhibitor, a positive validated test can still be highly relevant. The treating oncologist will consider current drug labeling, prior therapies, disease sites, central nervous system involvement, performance status, and other molecular findings.
Some FDA-authorized plasma companion diagnostics include T790M among the EGFR biomarkers they can detect for osimertinib selection. Their labeling also warns that a negative plasma result does not ensure that the tumor is negative and may call for tissue testing when feasible. Platform-specific instructions matter because not every laboratory-developed assay carries the same regulatory status or drug-selection claim.
Treatment should not be selected by the word “positive” alone. A report may contain several alterations, and the oncologist must determine which change is driving resistance. If a broad NSCLC biomarker profile identifies a different actionable resistance mechanism, a clinical trial or another targeted strategy may be more relevant than a T790M-centered approach.
Limitations and Resistance Beyond T790M
The biggest limitation of plasma T790M testing is imperfect sensitivity. Earlier studies found that a substantial fraction of tissue-positive T790M cases were missed by plasma assays. Modern methods have improved, but biology still imposes a limit: a test cannot detect tumor DNA that never reaches the sampled bloodstream in sufficient quantity.
A second limitation is tumor heterogeneity. Different metastases can contain different resistance clones. Blood may capture some of this diversity better than a single tissue core, but the mix of DNA in plasma is weighted toward lesions that shed more strongly. A small but clinically important resistant clone can therefore be underrepresented.
A third limitation is the changing treatment landscape. After osimertinib, resistance can include:
- EGFR-dependent mechanisms, including C797S and other tertiary EGFR mutations;
- MET amplification, one of the more common bypass mechanisms;
- HER2 amplification or mutation and other receptor-pathway changes;
- BRAF, KRAS, PIK3CA, or other pathway alterations;
- gene fusions, including acquired oncogenic rearrangements;
- histologic transformation, particularly transformation to small-cell lung cancer.
Broad NGS can detect many genomic changes, but tissue remains especially important when transformation is suspected. Rapid growth, changing clinical behavior, or a discordance between imaging and plasma findings may prompt biopsy even when a liquid biopsy has already been performed.
Another mistake is comparing numerical VAFs from two different platforms as though they were directly interchangeable. Assay depth, filtering, background correction, and reporting thresholds differ. Serial molecular monitoring is easiest to interpret when the same validated platform is used at clinically consistent time points.
Pre-analytical quality also matters. Plasma should be processed or stabilized in a way that limits white-blood-cell breakdown. If excess normal genomic DNA enters the sample, it dilutes the ctDNA signal and can reduce sensitivity. Laboratories build collection requirements around their validated workflow, so using the specified tube and transport conditions is part of the test rather than a minor logistical detail.
Clinical context can also change the meaning of a low-level call. A very low T790M signal detected together with the original EGFR driver may represent a real resistant subclone, but the treating team may consider whether the alteration is reproducible, whether the assay has a companion-diagnostic claim, and whether other resistance mechanisms are present. This is especially important when a treatment decision carries substantial consequences.
Finally, T790M status does not by itself describe prognosis. It is primarily a resistance and treatment-selection biomarker. Outcomes depend on the full disease context and available therapies.
What to Discuss After Testing
After receiving an EGFR T790M liquid-biopsy report, the most useful questions focus on whether the sample was informative and how the result changes the next treatment decision.
Ask the oncology team:
- Was my original activating EGFR mutation detected in the plasma sample?
- Was T790M detected, and by an assay validated for the treatment decision being considered?
- If T790M was not detected, was there enough ctDNA to trust that negative result?
- Should I have a tissue biopsy because the plasma test was negative or because transformation is possible?
- Did the panel identify another resistance mechanism such as MET amplification or EGFR C797S?
- Am I progressing after an older EGFR inhibitor or after osimertinib, and how does that change the significance of T790M?
- Do the findings support an approved therapy, a combination strategy, chemotherapy, or a clinical trial?
- Is another disease site more appropriate for biopsy than the site originally sampled?
The most important distinction is between a true negative molecular result and a non-informative negative blood sample. Liquid biopsy is powerful because it is fast and minimally invasive, but its reliability still depends on tumor shedding, assay design, and clinical context. When those limitations are recognized, T790M testing can be a precise part of resistance evaluation rather than a stand-alone answer.
References
- Integrating ctDNA testing for EGFR analysis in advanced non-small cell lung cancer: strategies for clinical laboratories. 2025 (Review)
- Clinical Utility of ctDNA Analysis in Lung Cancer-A Review 2025 (Review)
- ctDNA for the Evaluation and Management of EGFR-Mutant Non-Small Cell Lung Cancer 2024 (Review)
- Oncogene-addicted metastatic non-small-cell lung cancer: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up 2023 (Guideline)
- ESMO recommendations on the use of circulating tumour DNA assays for patients with cancer: a report from the ESMO Precision Medicine Working Group 2022 (Guideline)
- Recommendations for a practical implementation of circulating tumor DNA mutation testing in metastatic non-small-cell lung cancer 2022 (Review)
Disclaimer
EGFR T790M liquid-biopsy results must be interpreted by the treating oncology team using the specific assay, prior EGFR therapy, tissue findings, imaging, and current treatment indications. A negative plasma result does not rule out T790M or another resistance mechanism. Do not start, stop, or change lung-cancer therapy based on a blood-test result without specialist guidance.