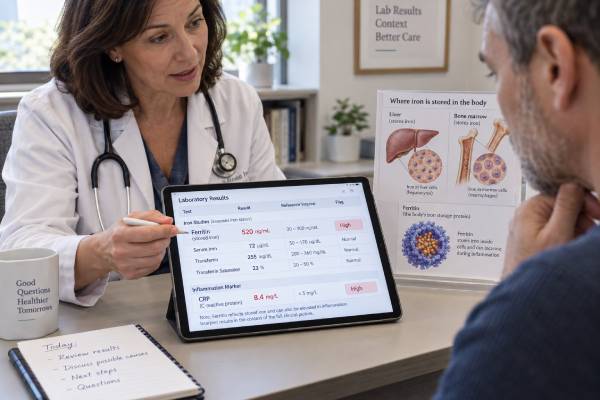
A ferritin blood test is often described as a measure of stored iron, but that description is only part of the story. Ferritin is a protein that stores iron inside cells, and a small amount circulates in the blood. Low ferritin usually supports depleted iron stores. High ferritin is less specific: it may reflect increased iron, inflammation, liver-cell injury, metabolic disease, alcohol use, infection, kidney disease, cancer, or a combination of these factors. Because ferritin rises during the acute-phase response, a person can have iron deficiency even when the result is normal or elevated. The number therefore needs to be read with transferrin saturation, a complete blood count, liver tests, inflammatory markers, symptoms, medicines, and clinical history. This article explains how clinicians separate iron overload from inflammatory hyperferritinemia, what common result patterns mean, and when a high value deserves prompt follow-up.
- What ferritin measures: A circulating marker related to iron storage that also rises with inflammation and cell injury.
- What a high result means: High ferritin is a finding, not a diagnosis, and most routine elevations are not caused by iron overload alone.
- Most useful companion test: Transferrin saturation helps show whether unusually large amounts of circulating iron are available.
- Important limitation: Inflammation can raise ferritin enough to hide depleted usable iron stores.
- Next step: Confirm persistence, review the whole iron panel, and investigate the clinical context rather than treating the number by itself.
Table of Contents
- What the ferritin blood test measures
- Ferritin ranges and result patterns
- Why ferritin levels become high
- Inflammation, ferritin, and hidden iron deficiency
- How clinicians evaluate a high ferritin result
- Treatment and follow-up
- When high ferritin needs urgent attention
What the Ferritin Blood Test Measures
Ferritin is the body’s main intracellular iron-storage protein. It packages iron in a form that cells can use while limiting the damage that unbound iron can cause. Most ferritin is found in the liver, spleen, bone marrow, and other tissues. The concentration measured in serum or plasma generally tracks iron stores when a person is otherwise well and does not have active inflammation or significant liver injury.
The test is usually ordered for one of several reasons:
- To investigate fatigue, anemia, restless legs, hair loss, or other possible signs of iron deficiency
- To assess suspected iron overload or hereditary hemochromatosis
- To monitor iron replacement, repeated transfusions, or treatment for iron overload
- To help interpret chronic inflammatory, kidney, liver, or metabolic disease
- To investigate an unexpectedly high result found on routine testing
Ferritin is not the same as serum iron. Serum iron measures iron circulating on transferrin at one moment and varies with time of day, meals, supplements, and illness. Ferritin changes more slowly and is usually a better first marker of depleted stores. However, ferritin is also a positive acute-phase reactant. Cytokines released during inflammation stimulate ferritin production and alter the movement of iron between the blood and storage cells. That dual role explains why ferritin can be highly informative at the low end but ambiguous at the high end.
A standard blood draw is used. Fasting is often unnecessary for ferritin alone, although a clinician or laboratory may request a morning fasting sample when transferrin saturation is being repeated after an abnormal result. Recent iron tablets, intravenous iron, blood transfusion, acute illness, strenuous exercise, and heavy alcohol intake may affect interpretation and should be mentioned.
Ferritin Ranges and Result Patterns
Reference intervals vary by laboratory, assay, age, sex, menstrual status, pregnancy, and local population. Units are commonly micrograms per liter (µg/L) or nanograms per milliliter (ng/mL); these are numerically equivalent for ferritin. The range printed on the laboratory report should be used instead of a universal cutoff.
Broadly, a clearly low result is strongly suggestive of iron deficiency. An elevated result indicates that ferritin is being produced or released in greater amounts, but it does not identify the cause. Values just above the upper limit are common and often have more than one contributor. Very high values narrow the differential diagnosis but still do not prove iron overload.
| Pattern | Possible interpretation | Helpful context |
|---|---|---|
| Low ferritin | Depleted iron stores are likely | Hemoglobin, mean cell volume, menstrual or gastrointestinal blood loss |
| Normal ferritin with low transferrin saturation | Early deficiency or iron restriction from inflammation | CRP, kidney disease, chronic infection, reticulocyte hemoglobin |
| High ferritin with normal or low transferrin saturation | Inflammation, liver injury, metabolic dysfunction, alcohol use, malignancy, or kidney disease | Liver enzymes, metabolic measures, symptoms, trend |
| High ferritin with persistently high transferrin saturation | Iron overload becomes more likely | Family history, transfusions, HFE testing when appropriate, liver assessment |
| Markedly or rapidly rising ferritin | Severe inflammation, acute liver injury, iron overload, or hyperinflammatory illness | Clinical urgency depends on symptoms and associated laboratory abnormalities |
The magnitude matters, but thresholds are guideposts rather than stand-alone diagnoses. A ferritin of 350 µg/L can be important in one person and readily explained in another. A value above 1,000 µg/L generally deserves timely evaluation because it is associated with a greater chance of significant liver disease, iron loading, severe systemic inflammation, or another serious disorder. Yet even at that level, the next question remains “why is it high?” rather than “how do we lower ferritin?”
Ferritin trends are often more informative than a single measurement. A temporary rise during influenza, surgery, or a flare of inflammatory disease may fall after recovery. Persistent elevation over months points toward an ongoing driver. Comparisons are clearest when the same laboratory method is used.
Why Ferritin Levels Become High
High ferritin, also called hyperferritinemia, has many causes. In routine practice, inflammation, fatty liver and other liver disorders, alcohol exposure, metabolic dysfunction, and chronic disease are more common explanations than hereditary iron overload.
Inflammation and Infection
Inflammatory cytokines increase ferritin synthesis and the hormone hepcidin. Hepcidin traps iron inside macrophages and reduces absorption from the intestine. This response may help limit iron available to microbes, but it also reduces iron delivery to developing red blood cells. Ferritin may rise with autoimmune disease, inflammatory bowel disease, chronic infection, acute bacterial or viral illness, tissue injury, and cancer. Comparing ferritin with a CRP result can help identify an active acute-phase response, although a normal CRP does not exclude every inflammatory condition.
Liver Disease and Alcohol
The liver stores substantial ferritin. Injury to liver cells can release ferritin into blood, while inflammation and reduced clearance may add to the elevation. Metabolic dysfunction-associated steatotic liver disease, viral hepatitis, alcohol-related liver disease, and advanced fibrosis are common considerations. Ferritin can fluctuate with alcohol intake and may improve after sustained reduction or abstinence. Liver enzymes, platelet count, imaging, and fibrosis assessment may be more informative about liver health than ferritin alone.
Metabolic Dysfunction
Insulin resistance, central adiposity, type 2 diabetes, high triglycerides, and fatty liver often cluster with modest or moderate ferritin elevation. This pattern does not necessarily mean excess iron is damaging organs. It may reflect low-grade inflammation, liver stress, altered iron handling, or all three. Cardiometabolic risk should be addressed directly rather than assuming that blood removal is required.
True Iron Overload
Iron overload occurs when absorbed or transfused iron exceeds the body’s ability to regulate and safely store it. Causes include HFE-related hereditary hemochromatosis, less common genetic iron disorders, repeated red-cell transfusions, ineffective red-cell production, and excessive iron administration. Transferrin saturation is often elevated because more transferrin binding sites carry iron. Persistent saturation around or above 45% commonly triggers further assessment, but exact thresholds and testing pathways vary.
Genetic susceptibility does not always produce organ damage. HFE variants are most informative in the appropriate ancestry and biochemical setting. Testing every person with mildly high ferritin can produce confusing results and miss more common causes. Conversely, a strong family history, high transferrin saturation, liver abnormalities, or characteristic complications may justify focused genetic or specialist evaluation.
Less Common but Important Causes
Marked ferritin elevations can occur in adult-onset Still disease, macrophage activation syndrome, hemophagocytic lymphohistiocytosis, severe infection, major tissue injury, acute hepatitis, and some blood cancers. Ferritin can also rise in chronic kidney disease, after transfusion, and with some malignancies. These diagnoses are not made from ferritin alone; they are considered when the degree of elevation fits the clinical picture and other findings support them.
Inflammation, Ferritin, and Hidden Iron Deficiency
One of the most important ferritin pitfalls is assuming that a normal or high value rules out iron deficiency. During inflammation, hepcidin reduces intestinal iron absorption and locks stored iron away from the bone marrow. Ferritin rises because it is an acute-phase protein, even though the iron available for red-cell production may be inadequate. This is called functional iron deficiency or iron-restricted erythropoiesis. Absolute deficiency and inflammatory restriction can also exist together.
The distinction matters because the treatment and search for a cause may differ. Absolute deficiency means total body iron stores are depleted, often through menstrual loss, gastrointestinal bleeding, increased needs, low intake, or malabsorption. Functional deficiency means iron is present but poorly accessible. Chronic kidney disease, heart failure, inflammatory bowel disease, infection, and autoimmune illness are common settings.
Clues that help include:
- Transferrin saturation: A low percentage suggests that little circulating iron is available, whether from absolute deficiency or inflammatory restriction.
- CRP or ESR: Elevated inflammatory markers make ferritin harder to interpret. An ESR test may add longer-range context but is also nonspecific.
- Complete blood count: Hemoglobin, mean cell volume, red-cell distribution width, and platelet count can show consequences but may be normal early.
- Soluble transferrin receptor: This may help because it is less affected by inflammation, although availability and interpretation vary.
- Reticulocyte hemoglobin: This estimates recent iron delivery to new red cells and can identify restricted erythropoiesis.
- Clinical source of loss: Heavy periods, pregnancy, gastrointestinal symptoms, blood donation, surgery, and dietary history remain essential.
World Health Organization guidance uses higher ferritin thresholds to identify possible deficiency in people with infection or inflammation than in otherwise healthy people. These population and clinical cutoffs should not be applied mechanically to every patient, but they reinforce the principle: inflammation can conceal depleted stores.
Do not start long-term iron solely because fatigue is present, and do not avoid needed iron solely because ferritin is high. Excess iron can be harmful, while untreated deficiency has consequences. The iron panel and clinical cause should guide therapy.
How Clinicians Evaluate a High Ferritin Result
Evaluation begins by confirming the result and looking for common, reversible explanations. The pace depends on the ferritin level, symptoms, transferrin saturation, liver tests, blood count, and whether the person is acutely unwell.
A focused history may cover:
- Recent infection, fever, surgery, inflammatory flare, or strenuous exercise
- Alcohol amount and pattern
- Diabetes, weight change, blood pressure, sleep apnea, and fatty liver risk
- Iron supplements, intravenous iron, transfusions, and multivitamins
- Liver disease, kidney disease, autoimmune illness, and cancer history
- Family history of hemochromatosis, cirrhosis, diabetes, heart disease, or unexplained bronze skin
- Joint pain, abdominal symptoms, reduced libido, fatigue, palpitations, or skin changes
Common follow-up tests include a repeat ferritin, transferrin saturation, serum iron, transferrin or total iron-binding capacity, complete blood count, creatinine, alanine aminotransferase, gamma-glutamyl transferase, glucose or A1c, and lipids. CRP may be included when inflammation is suspected. Testing should be tailored; a broad panel without a clinical question can create incidental abnormalities.
The combination of ferritin and transferrin saturation is particularly useful. High ferritin with saturation below about 45% makes substantial HFE-related iron overload less likely in many settings, though it does not exclude every iron-loading disorder. Persistently high saturation supports further evaluation. Depending on ancestry, family history, and local guidance, this may include HFE genetic testing. A positive genotype is interpreted with the biochemical findings, not in isolation.
Liver ultrasound can identify steatosis or structural disease but does not quantify iron reliably. Magnetic resonance imaging can estimate liver iron without biopsy and may be used when biochemical results, transfusion history, or genetics suggest significant loading. Liver fibrosis assessment helps determine risk. Biopsy is now reserved for selected cases when diagnosis or staging remains uncertain.
A ferritin result should also be interpreted as part of protein and inflammatory physiology. Low albumin, for example, can accompany severe inflammation or liver dysfunction; the albumin blood test provides different information and should not be treated as a substitute for ferritin.
Treatment and Follow-Up
Treatment targets the cause, not ferritin itself. When a recent infection or inflammatory flare is the likely explanation, ferritin may be repeated after recovery. For metabolic fatty liver, management may include gradual weight reduction when appropriate, physical activity, diabetes care, lipid control, blood-pressure treatment, and reducing alcohol. Liver disease needs cause-specific assessment.
Confirmed iron deficiency is treated with oral or intravenous iron based on severity, absorption, ongoing loss, comorbidity, and tolerance. The source of deficiency should be addressed. In inflammatory disease, controlling the underlying condition may improve iron availability; some patients still need iron replacement. Response is monitored with symptoms, hemoglobin, ferritin, transferrin saturation, and sometimes reticulocyte measures.
Confirmed iron overload may be treated with therapeutic phlebotomy, which removes iron-containing red cells. The schedule and target are individualized. Phlebotomy is not an appropriate treatment for every high ferritin result: it can cause iron deficiency and anemia when excess stored iron is not present. People with transfusional iron overload may need chelation rather than phlebotomy because they cannot safely lose red cells.
Practical steps while evaluation is underway include avoiding unnecessary iron supplements and high-dose vitamin C supplements, which can increase iron absorption, unless prescribed. There is usually no need to eliminate all iron-containing foods. Alcohol advice depends on the liver findings and overall health; significant liver disease or iron overload strengthens the reason to avoid it. Raw shellfish can pose a serious infection risk in iron overload and advanced liver disease.
Follow-up intervals depend on cause and severity. A mildly elevated stable value with normal saturation and a clear metabolic explanation may be rechecked after risk factors are addressed. A rising value, high saturation, abnormal liver tests, anemia, constitutional symptoms, or ferritin above roughly 1,000 µg/L generally warrants more timely review or specialist input. An inflammatory marker panel can provide context, but no panel replaces a focused diagnostic assessment.
When High Ferritin Needs Urgent Attention
Most isolated high ferritin results are evaluated in routine outpatient care. Urgency comes from the person’s condition and accompanying abnormalities, not from the ferritin number alone.
Seek prompt medical assessment for high ferritin accompanied by persistent high fever, confusion, severe weakness, shortness of breath, chest pain, fainting, jaundice, dark urine, rapidly worsening abdominal pain, bleeding, or signs of severe infection. Acute liver failure, sepsis, and hyperinflammatory syndromes require immediate care and usually produce multiple abnormal findings.
Timely specialist evaluation is also appropriate when ferritin is markedly elevated or rising, transferrin saturation remains high, liver enzymes are abnormal, imaging suggests liver injury, there is a history of many transfusions, or close relatives have confirmed hereditary hemochromatosis. People with unexplained anemia, low platelets, enlarged liver or spleen, weight loss, night sweats, or persistent inflammation need a broader evaluation.
A high ferritin result should not prompt panic, and a normal ferritin should not end the investigation when the rest of the picture suggests iron deficiency. The safest interpretation is pattern-based: establish whether iron is depleted, restricted, or excessive; identify inflammation or organ injury; and treat the underlying problem.
References
- Use of Ferritin Concentrations to Assess Iron Status in Individuals and Populations 2023
- High Ferritin and Iron Overload – Investigation and Management 2021
- FERR1 – Overview: Ferritin, Serum 2026
- HFE-Related Hemochromatosis 2024
- Updating the Diagnosis and Management of Elevated Serum Ferritin Levels in the Context of Increasing Clinical Experience 2025
- Hyperferritinemia—A Clinical Overview 2021
Disclaimer
This article provides general education and cannot diagnose the cause of a ferritin result. Reference intervals, testing pathways, and treatment thresholds vary, so discuss personal results with a qualified clinician who can review the complete iron panel and medical history. Seek urgent care for severe symptoms or signs of acute illness.