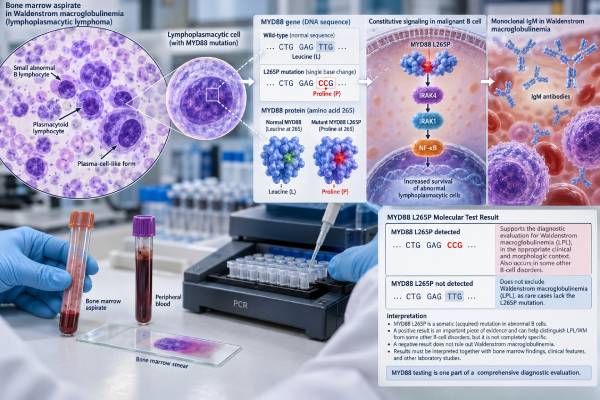
A MYD88 mutation test looks for acquired changes in the MYD88 gene in abnormal B cells. The best-known result is MYD88 L265P, a hotspot mutation found in more than 90% of people with Waldenström macroglobulinemia (WM), which is an IgM-producing lymphoplasmacytic lymphoma. The same mutation can also occur in IgM monoclonal gammopathy of undetermined significance (MGUS), some diffuse large B-cell lymphomas, and several lymphomas arising in immune-privileged sites. For that reason, a positive MYD88 result can strongly support a diagnosis but does not establish one by itself. A negative result also does not completely rule out WM. Testing is usually performed on bone marrow and may use allele-specific PCR, droplet digital PCR, or next-generation sequencing. The result can help distinguish WM from related disorders, refine molecular classification, and sometimes inform the expected response to Bruton tyrosine kinase (BTK) inhibitors, especially when CXCR4 status is considered at the same time.
- MYD88 L265P is detected in more than 90% of Waldenström macroglobulinemia cases, but it is not required for the diagnosis.
- A positive L265P result is not specific to WM because it can occur in IgM MGUS and other B-cell lymphomas.
- Bone marrow is the preferred specimen for routine WM molecular testing because blood can miss low-level disease.
- A negative MYD88 test does not exclude lymphoplasmacytic lymphoma or WM, particularly if the assay has limited sensitivity or the tumor burden is low.
- MYD88 and CXCR4 are often interpreted together in WM because the combined genotype can influence disease biology and response patterns with BTK inhibitors.
Table of Contents
- What the MYD88 Test Detects
- Why MYD88 L265P Matters in Waldenström Macroglobulinemia
- How the MYD88 Test Is Performed
- How to Interpret MYD88 Results
- MYD88 in Other Lymphomas
- Treatment and Prognosis Meaning
- Next Steps and Common Questions
What the MYD88 Test Detects
MYD88 encodes an adaptor protein used by Toll-like receptors and interleukin-1 receptors to transmit signals inside immune cells. The common p.Leu265Pro, usually written L265P, change makes MYD88 signaling abnormally active. This can promote assembly of the MYD88 signaling complex, activation of IRAK proteins, BTK, and NF-κB, and continued survival of malignant B cells.
In WM, MYD88 L265P is usually a somatic mutation. That means it developed in the abnormal B-cell clone rather than being an inherited change present in every cell of the body. A positive result therefore usually does not imply that relatives need hereditary testing for the same variant.
The test may be ordered as a targeted assay that looks only for L265P or as part of a broader sequencing panel. A broader panel can identify less common MYD88 variants and changes in other genes, but the sensitivity for a low-level L265P clone can vary by method.
L265P is a hotspot, not a blood level
A MYD88 report does not give a “high” or “low” MYD88 concentration. It reports whether a DNA variant was detected and may provide a variant allele fraction (VAF), which is the proportion of sequencing reads or DNA molecules carrying the variant.
VAF is affected by tumor content, sample purity, assay method, and whether the specimen was enriched for B cells. It should not be treated as a direct measure of total disease burden without context.
MYD88 testing is often part of a wider hematologic cancer biomarker evaluation that includes morphology, flow cytometry, immunophenotyping, serum studies, cytogenetics, and other molecular findings.
Why MYD88 L265P Matters in Waldenström Macroglobulinemia
MYD88 L265P is one of the most useful molecular clues in WM because it is present in the great majority of cases. However, WM remains an integrated clinicopathologic diagnosis, not a one-mutation diagnosis.
Waldenström macroglobulinemia is a lymphoplasmacytic lymphoma involving bone marrow that produces a monoclonal immunoglobulin M (IgM) protein. A typical evaluation therefore combines:
- Bone marrow morphology showing lymphoplasmacytic infiltration
- Flow cytometry and immunophenotyping showing a compatible clonal B-cell population
- Serum testing confirming an IgM monoclonal protein
- MYD88 mutation status
- Other molecular or cytogenetic tests when clinically appropriate
A serum immunofixation test helps identify the immunoglobulin type, while MYD88 testing examines the tumor’s molecular profile. The tests answer different questions.
Why MYD88 helps with the differential diagnosis
Several disorders can produce IgM monoclonal protein or lymphoplasmacytic cells. MYD88 L265P supports WM/LPL when the morphology and immunophenotype fit, and it can help separate WM from some mimics.
For example, IgM plasma cell myeloma is usually MYD88 wild-type and has a plasma-cell phenotype rather than the typical lymphoplasmacytic B-cell pattern of WM. Marginal zone lymphoma can occasionally carry MYD88 mutations, so a positive result does not automatically distinguish every case. Chronic lymphocytic leukemia and other small B-cell lymphomas can also enter the differential diagnosis based on morphology and immunophenotype.
MYD88 L265P also occurs in many patients with IgM MGUS, a precursor condition. Therefore, finding L265P in someone with a small IgM monoclonal protein does not automatically mean symptomatic WM. Bone marrow findings and clinical criteria remain essential.
How the MYD88 Test Is Performed
For suspected or established WM, bone marrow is generally the preferred sample for MYD88 testing. The aspirate contains the clonal lymphoplasmacytic cells that carry the mutation. Some laboratories test whole marrow, while others enrich for CD19-positive B cells to improve sensitivity for molecular or cytogenetic studies.
Several methods are used:
Allele-specific PCR
Allele-specific polymerase chain reaction is designed to detect the L265P hotspot with high sensitivity. International WM consensus recommendations have supported allele-specific PCR as a practical minimum method for MYD88 L265P assessment in appropriate bone marrow samples.
Droplet digital PCR
Droplet digital PCR, or ddPCR, partitions the DNA into many small reactions and can detect low-frequency mutant molecules. It can be more sensitive than routine sequencing in samples with low tumor content. It may also be used in research or specialized monitoring settings.
Next-generation sequencing
NGS can assess MYD88 together with other genes. Its advantage is breadth: one assay can identify multiple variants that may matter for diagnosis, prognosis, or treatment. Its limitation is that a routine panel may have a higher detection threshold than a dedicated hotspot PCR or ddPCR assay. A low-level L265P mutation can therefore be missed if the sequencing depth, bioinformatics, or specimen tumor content is insufficient.
A separate CXCR4 mutation test is often considered alongside MYD88 in WM because CXCR4 variants are the second major recurrent molecular finding.
Can blood be used?
Peripheral blood can contain enough clonal DNA in some patients, and highly sensitive assays or cell-free DNA methods may detect MYD88 L265P. However, blood is generally less reliable than marrow when circulating tumor cells are sparse. A negative blood result should not be treated as equivalent to a sensitive negative marrow test when clinical suspicion remains high.
Testing may also be performed on lymphoma tissue or cerebrospinal fluid in selected diseases, especially when MYD88 status is being used to support another lymphoma diagnosis.
Preparation, turnaround time, and sample quality
There is usually no special preparation for a MYD88 mutation test itself. Fasting is not required, and routine medicines do not alter the DNA sequence. If the test is performed from bone marrow, the preparation and aftercare are determined by the marrow aspiration or biopsy procedure rather than by MYD88 analysis.
Turnaround time varies from a few days for a targeted PCR assay to one or more weeks for a broader NGS panel, especially when the specimen is sent to a reference laboratory. An urgent clinical problem such as symptomatic hyperviscosity is managed on clinical grounds while molecular results are pending; care should not be delayed solely to wait for MYD88 status.
Sample quality matters. A marrow aspirate heavily diluted with peripheral blood may contain fewer clonal cells than expected. Very low tumor burden can also push the mutation below the assay’s detection limit. When a negative result conflicts with strong pathology evidence, the laboratory may recommend testing a different sample, enriching B cells, or using a more sensitive method.
Reports may use terms such as “detected,” “positive,” “not detected,” “wild-type,” or “below limit of detection.” These phrases are not always interchangeable. “Not detected” means the assay did not find the targeted alteration above its validated sensitivity. It does not prove that every tumor cell carries completely normal MYD88, and it does not exclude an uncommon MYD88 variant outside the regions tested.
How to Interpret MYD88 Results
The basic result categories are detected, not detected, or occasionally indeterminate, but their meaning depends on the disease being evaluated and the assay used.
| Result | Usual meaning | Important limitation |
|---|---|---|
| MYD88 L265P detected in compatible WM/LPL | Strongly supports the diagnosis and provides molecular information relevant to therapy | Still requires compatible marrow and clinical findings |
| MYD88 L265P detected with IgM MGUS | Shows a common molecular feature of the clonal B-cell population | Does not by itself establish WM or indicate that treatment is needed |
| MYD88 not detected | No mutation covered by the assay was found above its detection limit | Does not exclude WM, especially with low tumor burden or a hotspot-only assay |
| Non-L265P MYD88 variant detected | An uncommon MYD88 alteration is present | Its diagnostic and treatment significance may differ from L265P |
What MYD88 wild-type means
“Wild-type” usually means the tested MYD88 alteration was not detected. It is not the same as “no lymphoma.” A minority of otherwise well-characterized WM cases are MYD88 wild-type. These cases deserve careful pathologic review because the absence of L265P raises the possibility of a mimic and may also have treatment implications.
A targeted L265P assay can also miss a different activating MYD88 mutation. If the clinical and pathologic features strongly support WM but L265P is negative, broader sequencing or repeat testing with an adequately sensitive method may be considered.
The laboratory report should also be read for the stated analytical sensitivity. An assay validated to detect variants down to 1% VAF can identify a smaller clone than an assay with a 5% threshold, assuming specimen quality is comparable. This is one reason two laboratories can occasionally produce different results from samples collected at different times or with different tumor content.
Variant allele fraction is not a treatment threshold
A report may show MYD88 L265P at 5%, 20%, or another VAF. There is no universal VAF cutoff that determines when WM should be treated. Treatment is driven by symptoms and disease-related problems such as anemia, hyperviscosity, neuropathy, symptomatic organ enlargement, or other clinically significant complications.
MYD88 in Other Lymphomas
MYD88 L265P is not exclusive to WM. Its frequency varies greatly across lymphoma types, which is why the disease context must always be stated.
The mutation is found in a subset of activated B-cell-type diffuse large B-cell lymphoma (DLBCL) and is particularly enriched in certain extranodal or immune-privileged sites, including primary central nervous system lymphoma and primary testicular lymphoma. In those settings, MYD88 often occurs with other pathway alterations such as CD79B mutations.
Detection of MYD88 L265P in cerebrospinal fluid or circulating tumor DNA is being studied and used in specialized diagnostic settings for CNS lymphoma, but such testing does not replace tissue diagnosis when tissue can be safely obtained.
Other B-cell lymphomas can occasionally carry MYD88 variants as well. Therefore, a positive test should be interpreted with cell lineage, site of disease, immunophenotype, morphology, and the rest of the molecular profile.
The same principle applies to a bone marrow containing small B cells: MYD88 L265P makes WM/LPL more likely in the right setting, but it cannot override findings that clearly support another lymphoma.
Treatment and Prognosis Meaning
MYD88 status has practical treatment relevance in WM because the mutant pathway signals through BTK, the target of drugs such as ibrutinib, zanubrutinib, and other BTK inhibitors. However, the result is not a simple yes-or-no drug eligibility test.
Patients with MYD88-mutated WM generally show strong activity with covalent BTK inhibitors. Response characteristics can differ when CXCR4 mutations are also present. CXCR4-mutated disease may show slower or less deep responses with some BTK-inhibitor approaches, which is why current consensus recommendations support evaluating both genes when molecular information will guide therapy.
MYD88 wild-type WM can behave differently and may have lower response rates to some BTK-inhibitor monotherapy strategies. The treatment choice still depends on symptoms, comorbidities, prior therapy, drug availability, toxicity, and the complete genotype.
MYD88 is also relevant to prognosis, but its meaning is context-dependent. In WM, wild-type status has been associated in several studies with less favorable biology or a higher transformation risk, while in some DLBCL settings MYD88 L265P itself can be associated with an adverse molecular subtype. The same mutation should therefore not be assigned one universal prognosis across all lymphomas.
A BTK mutation test answers a different question. BTK mutations are usually assessed in the setting of acquired resistance after BTK-inhibitor therapy, whereas MYD88 helps define the upstream disease biology present at diagnosis.
Next Steps and Common Questions
After a MYD88 result, the useful next step is to integrate it with the reason the test was ordered. In suspected WM, that usually means reviewing the bone marrow, IgM monoclonal protein, flow cytometry, symptoms, and CXCR4 status rather than acting on MYD88 alone.
Does MYD88 L265P prove Waldenström macroglobulinemia?
No. It strongly supports WM/LPL in the right setting, but the mutation is also common in IgM MGUS and can occur in other lymphomas. A diagnosis of WM requires compatible lymphoplasmacytic lymphoma involving bone marrow together with an IgM monoclonal gammopathy and the appropriate clinical context.
Can MYD88 be negative in real WM?
Yes. A minority of WM cases are genuinely MYD88 wild-type. False-negative results can also occur because of low tumor content, an insensitive assay, a poor specimen, or a rare non-L265P MYD88 variant not covered by a hotspot test.
Is MYD88 testing used to monitor minimal residual disease?
Highly sensitive PCR and ddPCR methods can quantify low levels of MYD88-mutated DNA, and molecular monitoring is an active area of study. Routine WM response criteria still rely heavily on clinical status, serum IgM, marrow or imaging when appropriate, and standardized response definitions. A detectable mutation after therapy is not interpreted in isolation as treatment failure.
Does a positive result mean treatment should start?
No. Many people with asymptomatic WM are observed without immediate therapy. Treatment begins when disease causes clinically meaningful symptoms or complications, not simply because MYD88 L265P is present.
The key distinction is that MYD88 is a molecular marker that strengthens diagnosis and refines treatment planning, not a stand-alone diagnosis, stage, or treatment trigger. Its value is greatest when the sample is appropriate, the assay sensitivity is understood, and the result is interpreted with marrow pathology and the broader WM or lymphoma workup. When results are discordant, expert hematopathology review can prevent both overdiagnosis and missed disease.
References
- Waldenström Macroglobulinemia: 2025 Update on Diagnosis, Risk Stratification, and Management 2025 (Review)
- Report of Consensus Panel 3 from the 11th International workshop on Waldenström’s Macroglobulinemia: Recommendations for molecular diagnosis in Waldenström’s Macroglobulinemia 2023 (Position Statement)
- Diagnostics in Waldenström’s macroglobulinemia: a consensus statement of the European Consortium for Waldenström’s Macroglobulinemia 2023 (Position Statement)
- Report of consensus Panel 4 from the 11th International Workshop on Waldenstrom’s macroglobulinemia on diagnostic and response criteria 2023 (Position Statement)
- Diagnostic next-generation sequencing to detect MYD88 L265P in Lymphoplasmacytic lymphoma compared to ddPCR 2025
Disclaimer
This article provides general information about MYD88 mutation testing and is not a substitute for individualized hematology or pathology advice. MYD88 results must be interpreted with the specimen type, assay sensitivity, bone marrow findings, IgM studies, other mutations, symptoms, and final lymphoma diagnosis. Do not start, stop, or select treatment based on a MYD88 result alone.