The Oncotype DX Genomic Prostate Score test, now commonly called the Genomic Prostate Score (GPS), is a tissue-based gene-expression test used after prostate cancer has been found on biopsy. It measures the activity of 17 genes in the tumor and produces a score from 0 to 100. In general, a higher score means the cancer has molecular features associated with more aggressive disease, while a lower score supports a lower estimated risk. GPS does not diagnose prostate cancer, replace the Gleason Grade Group, or tell with certainty whether a cancer will spread. Its main value is adding biologic information when standard findings such as PSA, biopsy grade, stage, MRI, and tumor volume leave an important treatment decision uncertain. It has been studied most extensively in localized prostate cancer, including men deciding between active surveillance and treatment, and newer evidence also supports prognostic use in selected higher-risk and radiation-treated patients.
- What it measures: GPS analyzes expression of 12 cancer-related genes and 5 reference genes in prostate biopsy tissue.
- Score range: Results run from 0 to 100; higher scores generally indicate greater biologic aggressiveness and higher risk of adverse outcomes.
- Main use: The test can refine prognosis after a positive biopsy, especially when choosing between active surveillance and definitive treatment.
- A score is not a diagnosis: There is no universal “normal” GPS value, and the result must be interpreted with Grade Group, PSA, stage, MRI, and other clinical factors.
- Current name: The assay is now marketed as the Genomic Prostate Score (GPS), formerly Oncotype DX GPS.
Table of Contents
- What the Genomic Prostate Score measures
- Who may benefit from GPS testing
- How the test is done
- How to interpret a GPS result
- How GPS can affect treatment decisions
- Evidence, strengths, and limitations
- What to do after receiving a GPS result
What the Genomic Prostate Score measures
GPS measures gene activity inside prostate cancer tissue to estimate how biologically aggressive the tumor appears. It is a prognostic test, not a screening test and not a hereditary cancer test.
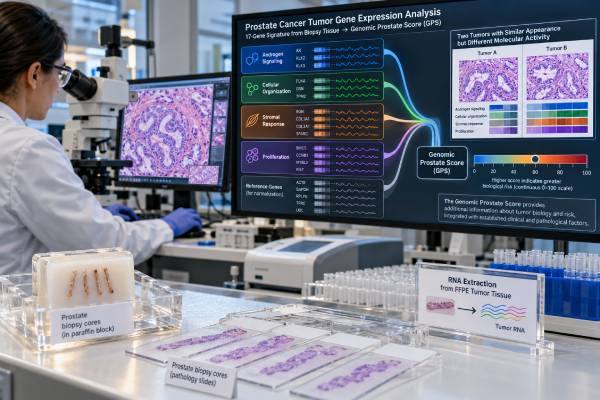
The assay uses reverse-transcription polymerase chain reaction, or RT-PCR, to measure RNA from a small amount of formalin-fixed prostate biopsy tissue. It evaluates 17 genes. Twelve are related to prostate cancer biology, and five serve as reference genes that help normalize the measurement.
The cancer-related genes represent four biologic pathways:
- Androgen signaling, which reflects how tumor cells respond to male-hormone signaling.
- Cellular organization, which relates to the structure and behavior of prostate cells.
- Stromal response, which reflects interactions between cancer and the surrounding tissue.
- Cell proliferation, which reflects signals associated with tumor-cell growth.
The final calculation converts these expression patterns into a GPS value from 0 to 100. A higher result means the tested tissue has a molecular pattern associated with less favorable pathology or outcomes. A lower result suggests more favorable biology, but it cannot prove that the entire prostate contains only low-risk cancer.
This differs from the PSA test, which measures a protein in blood and can be elevated for cancerous and noncancerous reasons. GPS is performed only after cancer tissue is available.
It also differs from germline genetic testing. GPS examines tumor gene expression rather than inherited DNA changes such as BRCA2 or HOXB13 variants. It therefore does not tell relatives whether they inherited a cancer-risk mutation.
Who may benefit from GPS testing
GPS is most useful when a person has localized prostate cancer and an important management choice remains uncertain after standard clinical assessment. It is not necessary for every newly diagnosed patient.
Historically, the assay was used most often in very-low-, low-, and favorable intermediate-risk disease. In those settings, a major question is whether the cancer appears indolent enough for active surveillance or whether its biology supports earlier surgery or radiation. GPS may be especially useful when the biopsy looks favorable but the patient or clinician wants another independent measure of risk.
A doctor may consider the test when:
- Biopsy has confirmed localized prostate adenocarcinoma.
- The choice between active surveillance and definitive treatment is genuinely close.
- Standard features give mixed signals, such as a favorable Grade Group but a relatively high PSA density or greater tumor volume.
- A person with intermediate-risk disease is discussing how much treatment may be appropriate.
- Additional prognostic information could realistically change the plan.
The test may add less value when the clinical decision is already clear. For example, a person with obvious metastatic disease does not need a localized-tumor GPS result to establish that the cancer has spread. Likewise, a person with very favorable disease who is firmly committed to active surveillance may reasonably decide that the result would not change management.
MRI also matters. Multiparametric MRI can identify suspicious areas, estimate local extent, and guide targeted biopsy, whereas GPS evaluates molecular behavior in the sampled tissue. These tools answer different questions. A genomic result should not be used to dismiss a highly concerning MRI lesion or important adverse pathology.
Other tissue-based classifiers, including the Decipher genomic classifier and Prolaris, use different gene sets, scoring systems, and evidence bases. They should not be treated as interchangeable numbers.
How the test is done
GPS usually requires no new biopsy because the laboratory can test tissue already collected during the diagnostic prostate biopsy. The ordering clinician selects an appropriate tumor-containing specimen and sends or requests the preserved tissue for analysis.
The basic process is:
- A pathologist confirms prostate cancer in the biopsy and identifies suitable tumor tissue.
- The laboratory isolates RNA from the selected specimen.
- RT-PCR measures expression of the 17 genes.
- The assay algorithm produces the GPS result and associated risk information.
- The clinician interprets the report with the patient’s PSA, Grade Group, clinical stage, biopsy findings, imaging, age, health, and goals.
A small biopsy sample can be enough because the assay was designed for prostate needle-biopsy material. However, tissue quantity and quality still matter. A sample with too little tumor or degraded RNA may not produce a reportable result.
There is usually no special patient preparation because no new blood draw or urine sample is required. The test is performed on stored tissue. Turnaround time, insurance authorization, and out-of-pocket cost vary by laboratory, health plan, and location, so those practical details are worth checking before ordering.
One important limitation is biopsy sampling. Prostate cancer is often multifocal, meaning different areas can have different grades and molecular features. GPS was developed partly to provide information despite this heterogeneity, but no biopsy-based assay can guarantee that an unsampled, more aggressive focus is absent.
If the original biopsy was limited, discordant with MRI, or otherwise questionable, repeat pathology review or additional sampling may sometimes be more important than obtaining a genomic score.
How to interpret a GPS result
A GPS result is best interpreted as a continuous risk measure: higher values generally mean higher risk, and lower values generally mean lower risk. There is no single universal cutoff that divides every patient into “safe” and “dangerous” groups.
The score ranges from 0 to 100. Current reports may pair the score with individualized estimates for outcomes relevant to the patient’s clinical risk category. Depending on the report and indication, these may include the likelihood of adverse pathology, development of metastasis, or prostate cancer-specific death over a defined period.
A practical way to read the result is:
| Result pattern | General meaning | What it does not prove |
|---|---|---|
| Lower GPS | Tumor expression pattern is associated with more favorable biology | That surveillance is automatically safe or that higher-grade cancer is absent elsewhere |
| Intermediate GPS | Molecular risk falls between the lower and higher ends of the assay range | That a specific treatment is required |
| Higher GPS | Tumor expression pattern is associated with greater risk of aggressive pathology or adverse outcomes | That metastasis will definitely occur |
Some studies and current reports for unfavorable intermediate- or high-risk disease have used 40 as a reference point, with values of 41–100 representing higher likelihood of progression than values of 0–40. That threshold should not be applied mechanically to every patient or to every low-risk report. In favorable-risk disease, the score is commonly interpreted continuously and in the context of the patient’s baseline clinical risk.
For example, a GPS of 18 and a GPS of 48 are meaningfully different pieces of molecular information, but neither number can be interpreted in isolation. A person with Grade Group 1 disease, a small amount of cancer, reassuring MRI, and a low GPS may feel more comfortable with surveillance. A person with Grade Group 2 disease, several positive cores, a concerning lesion, and a high GPS may lean more strongly toward treatment.
Clinical measures such as PSA density remain important because they capture information the genomic assay does not.
The outcome named on the report matters as much as the numeric score. Adverse pathology usually refers to unfavorable findings that would be discovered if the whole prostate were examined after surgery, such as higher-grade or more locally advanced disease than expected from biopsy. Metastasis risk and prostate cancer-specific mortality are longer-term outcomes. A percentage for one endpoint should not be mistaken for the probability of another.
Risk estimates also depend on the clinical group used to generate them. Two men with the same GPS can have different absolute risks if one starts with Grade Group 1, low-volume disease and the other has unfavorable intermediate-risk features. This is why the report should be read as “GPS plus baseline clinical risk,” not as a stand-alone molecular verdict.
When discussing the result, ask whether the displayed percentage is based on untreated natural history, surgery cohorts, radiation cohorts, or a model combining several sources. Understanding the endpoint and comparison group prevents a precise-looking number from being given more certainty than the underlying evidence supports.
How GPS can affect treatment decisions
GPS can change a treatment discussion by moving estimated risk up or down, but it should support shared decision-making rather than dictate a treatment. The most useful question is not “Is my score good or bad?” but “Does this result change what makes sense for me?”
For men considering active surveillance, a lower score can add reassurance when the rest of the clinical picture is favorable. Surveillance is still an active management strategy, with periodic PSA testing, examinations, MRI when appropriate, and repeat biopsy or other reassessment. A genomic test does not replace that monitoring.
A higher GPS may prompt closer evaluation before surveillance is chosen. Depending on the circumstances, that could include expert pathology review, attention to MRI findings, confirmation of the amount of Gleason pattern 4, or discussion of surgery or radiation.
Evidence also extends beyond the original favorable-risk setting. Studies have found associations between higher GPS values and biochemical recurrence after prostatectomy in intermediate- and higher-risk disease. In a retrospective cohort of men treated with external-beam radiation, higher GPS was also associated with biochemical failure, distant metastasis, and prostate cancer-specific death.
Those findings are prognostic: they show that the score is associated with outcomes. They do not automatically prove that changing a treatment because of GPS improves survival. That distinction matters. A strong prognostic marker can identify risk without necessarily identifying the exact therapy that will provide the greatest benefit.
A randomized study showed that providing GPS information can influence urologists’ treatment preferences in favorable-risk disease. This demonstrates clinical impact on decision-making, but it also highlights why the result should be discussed carefully. More treatment is not always better, and avoiding treatment is not always safer.
Evidence, strengths, and limitations
GPS provides independent prognostic information, but the overall evidence for tissue-based genomic classifiers is stronger for risk refinement than for proving that test-guided treatment improves long-term outcomes. That is the central limitation to keep in mind.
Systematic reviews of Decipher, GPS, and Prolaris have found that these tests can modestly improve prognostic discrimination beyond standard clinical risk groups. At the same time, much of the underlying evidence is retrospective, treatment eras differ, and study populations are heterogeneous. Recent reviews continue to call for prospective trials that show whether using the results to choose treatment improves outcomes that matter to patients.
Important strengths of GPS include:
- It uses tissue already collected during biopsy.
- It provides biologic information that is different from PSA, Grade Group, and stage.
- It has been evaluated across multiple localized-risk settings.
- It can help quantify risk when standard findings leave uncertainty.
Important limitations include:
- The tested biopsy may not represent every tumor focus in the prostate.
- The score is not a direct measurement of growth rate or a guarantee of future behavior.
- It does not detect inherited cancer susceptibility.
- It cannot substitute for accurate pathology, staging, or imaging.
- A result may add little when the management decision is already obvious.
- Insurance coverage and patient cost vary.
It is also important to distinguish prognostic from predictive information. A prognostic test estimates the chance of an outcome regardless of a specific treatment. A predictive biomarker identifies whether a particular treatment is more likely to help. GPS is primarily used as a prognostic tool.
When a broader comparison is needed, a clinician may discuss GPS alongside the prostate cancer biomarker panel used before biopsy and other tissue classifiers used after diagnosis. Tests used at different stages of care should not be compared as though they answer the same question.
What to do after receiving a GPS result
The next step is to place the GPS result beside the clinical findings that already define your prostate cancer risk and ask whether the combined picture changes management. A useful appointment focuses on absolute risks and choices, not the score by itself.
Questions to review with the treating clinician include:
- What is my Grade Group, clinical stage, PSA level, and PSA density?
- How much cancer was present in the biopsy cores?
- Was MRI concordant with the biopsy, and is there any concern that a more aggressive area was missed?
- What outcomes does my specific GPS report estimate, and over what time period?
- Would a result this high or low actually change your recommendation?
- If I choose active surveillance, what is the exact monitoring schedule?
- If I choose treatment, does the GPS change the type or intensity of therapy?
- Are there competing health issues or life-expectancy considerations that matter more than a small difference in genomic risk?
A second opinion can be useful when pathology, imaging, and genomic results point in different directions. For example, a low genomic score should not automatically outweigh a clearly high-grade biopsy, and a high score should not erase the potential benefits of surveillance when the total clinical picture remains favorable.
The most useful interpretation is therefore integrated. GPS can sharpen the estimate of tumor aggressiveness, but the final decision should reflect the cancer’s clinical features, the quality of the biopsy and imaging, expected benefits and harms of treatment, and the patient’s preferences.
References
- Impact of Genomic Classifiers on Risk Stratification and Treatment Intensity in Patients With Localized Prostate Cancer : A Systematic Review. 2025 (Systematic Review)
- Genomic classifiers and prognosis of localized prostate cancer: a systematic review. 2025 (Systematic Review)
- Tissue-based gene expression testing in localized prostate cancer 2025 (Review)
- Integration of Genomic Tests in Prostate Cancer Care: Implications for Clinical Practice and Patient Outcomes 2024 (Review)
- Impact of genomic testing on urologists’ treatment preference in favorable risk prostate cancer: A randomized trial. 2023 (RCT)
- The 17-Gene Genomic Prostate Score Test Is Prognostic for Outcomes After Primary External Beam Radiation Therapy in Men With Clinically Localized Prostate Cancer 2023
Disclaimer
The Genomic Prostate Score is a prognostic aid and cannot determine by itself whether active surveillance, surgery, radiation, or another approach is best for an individual. Results should be interpreted by a qualified prostate cancer clinician together with pathology, PSA, imaging, stage, overall health, and personal treatment goals. This information is educational and is not a substitute for individualized medical advice.