A BCR-ABL1 test detects the BCR::ABL1 fusion gene or its RNA transcript, the defining molecular abnormality in chronic myeloid leukemia (CML) and an important finding in some acute lymphoblastic leukemias (ALL). The fusion usually results from t(9;22)(q34;q11.2), the chromosome exchange known as the Philadelphia chromosome. BCR::ABL1 produces an abnormally active tyrosine kinase that drives leukemia-cell growth. Testing has two major roles: establishing the diagnosis and measuring how much leukemia remains during treatment. At diagnosis, laboratories may use chromosome analysis, FISH, reverse-transcription PCR, or a combination of methods. During CML treatment, quantitative reverse-transcription PCR is the standard molecular monitoring tool, and results are usually reported on the BCR::ABL1 International Scale (IS). A positive diagnostic result does not by itself describe disease phase, while a changing quantitative result must be interpreted against treatment time points, prior results, transcript type, adherence, and current CML guidelines.
- BCR::ABL1 is the molecular hallmark of CML and usually comes from the Philadelphia chromosome translocation t(9;22).
- At diagnosis, testing confirms the fusion; during treatment, quantitative PCR measures the BCR::ABL1 transcript level over time.
- For typical CML transcripts, major molecular response (MMR) is BCR::ABL1 ≤0.1% on the International Scale.
- Common favorable milestones are ≤10% at 3 months, ≤1% at 6 months, and ≤0.1% at 12 months, although decisions are individualized.
- A rising or persistently high result may lead to adherence review, repeat testing, kinase-domain mutation testing, or a treatment change.
Table of Contents
- What BCR-ABL1 and the Philadelphia Chromosome Mean
- When BCR-ABL1 Testing Is Used
- How BCR-ABL1 Is Tested
- How to Read a Quantitative BCR-ABL1 Result
- Molecular Response Milestones in CML
- Rising Levels, Resistance, and Kinase-Domain Mutations
- Deep Response and Treatment-Free Remission
What BCR-ABL1 and the Philadelphia Chromosome Mean
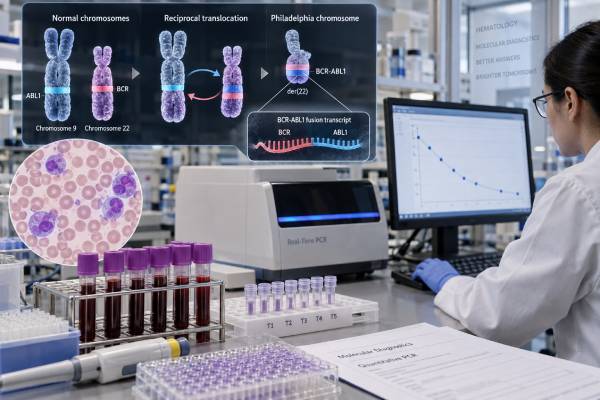
BCR::ABL1 is created when parts of chromosomes 9 and 22 exchange places, bringing ABL1 next to BCR and forming a continuously active tyrosine kinase. The classic cytogenetic shorthand is t(9;22)(q34;q11.2). The shortened chromosome 22 produced by this exchange is called the Philadelphia chromosome.
The fusion protein sends persistent growth and survival signals to blood-forming cells. In CML, this abnormality arises in a hematopoietic stem or progenitor cell, allowing a large clone of myeloid cells to expand. BCR::ABL1 is therefore not merely associated with CML; it is central to the disease definition and the target of tyrosine kinase inhibitor (TKI) therapy.
The exact RNA transcript depends on where BCR breaks. Most people with CML have e13a2 or e14a2 transcripts, historically called b2a2 and b3a2. Both encode the p210 BCR::ABL1 protein. A smaller p190 form, commonly associated with the e1a2 transcript, is frequent in Philadelphia chromosome-positive B-cell ALL and occurs only rarely in CML. Other atypical transcripts exist.
Knowing the transcript type matters because molecular monitoring must use an assay capable of detecting that patient’s fusion. Standard International Scale monitoring is designed primarily for the common p210 transcripts. Rare transcripts may require a personalized assay and may be reported relative to the patient’s own baseline rather than with standard IS percentages.
BCR::ABL1 is acquired in leukemia cells. It is not usually an inherited variant, so a positive result does not mean children or siblings automatically carry the fusion.
When BCR-ABL1 Testing Is Used
BCR-ABL1 testing is used both to diagnose Philadelphia chromosome-positive leukemia and to monitor the molecular response after treatment starts. The clinical question determines which method and specimen are most useful.
At initial evaluation, testing may be ordered for unexplained marked leukocytosis, left-shifted granulocytes, basophilia, splenomegaly, thrombocytosis, or other findings suspicious for CML. Bone marrow morphology and conventional chromosome analysis remain useful because they establish disease features and can reveal additional chromosome abnormalities. A BCR-ABL1 molecular diagnosis test can confirm the fusion even when the chromosome abnormality is cryptic.
BCR::ABL1 testing is also part of the workup for B-cell ALL because Philadelphia chromosome-positive ALL has specific treatment implications. In that setting, the testing strategy, transcript distribution, disease monitoring, and treatment approach differ from CML.
Once CML treatment begins, serial BCR-ABL1 quantitative PCR testing becomes the key laboratory measure of response. Blood is generally suitable for routine molecular monitoring, making repeated bone marrow procedures unnecessary for most stable patients after the initial diagnostic phase.
Testing is repeated at defined intervals and when there is concern for treatment failure, loss of response, progression, or an unexpected change in blood counts. The value comes from the trend. One number is useful, but a series of standardized measurements shows whether the leukemia burden is falling as expected, stable, or rising.
A diagnostic positive result also has to be matched to the blood and marrow picture. BCR::ABL1 can occur in CML and in Philadelphia chromosome-positive ALL, and rare patients can have other myeloid neoplasms with a BCR::ABL1 finding. In CML, the marrow typically shows granulocytic proliferation across multiple stages of maturation, often with basophilia and characteristic megakaryocyte changes. In B-ALL, the disease is dominated by lymphoblasts. The fusion is the same general molecular concept, but the diagnosis, drug combinations, response criteria, and monitoring strategy are not interchangeable.
At diagnosis, laboratories should identify the transcript type before serial monitoring begins. If a patient has an atypical transcript that a standard p210 assay does not amplify, subsequent results can appear falsely negative. Establishing the exact transcript at baseline prevents that problem and lets the laboratory select a suitable quantitative method.
How BCR-ABL1 Is Tested
Different BCR-ABL1 methods answer different questions, so diagnosis often uses complementary tests while follow-up relies mainly on quantitative molecular testing.
Chromosome analysis
Conventional karyotyping examines dividing marrow cells and can directly show the Philadelphia chromosome. It also identifies additional chromosome abnormalities that may have prognostic significance. Its sensitivity is lower than PCR, so it is not the preferred method for measuring very small amounts of residual disease.
FISH
FISH uses fluorescent probes to detect BCR::ABL1 at the DNA level. It can work on interphase cells and is useful when rapid confirmation is needed or when metaphase chromosome analysis is unsuccessful. FISH is more sensitive than routine karyotyping but less suitable than standardized quantitative PCR for deep molecular monitoring.
Reverse-transcription PCR
Because BCR::ABL1 is expressed as RNA, laboratories convert RNA to complementary DNA and amplify the fusion sequence. A qualitative or transcript-typing assay can establish which fusion is present. Quantitative reverse-transcription PCR, often written RT-qPCR, measures the amount of BCR::ABL1 relative to a control gene and reports the result on a standardized scale when possible.
The minimal residual disease approach in leukemia depends on the disease and marker. In CML, BCR::ABL1 PCR is unusually powerful because the same driver that defines the disease can be measured over many orders of magnitude.
Digital PCR is increasingly used in specialized settings and can improve precision at very low transcript levels, but validated RT-qPCR remains the most common standard. Assay quality matters, especially when judging deep molecular responses near the limits of detection.
A result of “not detected” does not prove that every leukemia cell is gone. It means no BCR::ABL1 transcript was detected within the sensitivity and quality limits of that specimen and assay.
How to Read a Quantitative BCR-ABL1 Result
For patients with typical p210 CML transcripts, quantitative results are usually reported as BCR::ABL1% on the International Scale, allowing response levels to be compared across validated laboratories. Lower percentages generally mean a smaller molecular disease burden.
| Response term | BCR::ABL1 on the International Scale | General meaning |
|---|---|---|
| Approximate complete cytogenetic response equivalent | ≤1% | Low disease level corresponding approximately to complete cytogenetic response |
| MMR / MR3 | ≤0.1% | Major molecular response |
| MR4 | ≤0.01% | Deep molecular response |
| MR4.5 | ≤0.0032% | Very deep molecular response when assay quality is sufficient |
| MR5 | ≤0.001% | Extremely deep molecular response when technically measurable |
These thresholds are logarithmic. A fall from 10% to 1% is a tenfold decrease; a fall from 1% to 0.1% is another tenfold decrease. Small fluctuations at very low levels can reflect sampling and analytical variation, so clinicians focus on confirmed trends rather than reacting to every minor change.
The report should also show whether the sample had enough control-gene transcripts to support a deep response claim. For example, calling MR4.5 requires greater analytical sensitivity than simply reporting MMR. If the control signal is inadequate, “BCR::ABL1 not detected” may not qualify as a validated deep molecular response.
Results from atypical transcripts should not be forced onto the standard International Scale. The laboratory may instead calculate an individual molecular response from a baseline measurement.
Molecular Response Milestones in CML
CML management uses BCR::ABL1 levels at defined treatment time points to judge whether a TKI is controlling the disease as expected. The 2025 European LeukemiaNet recommendations retain familiar molecular milestones while emphasizing clinical context before changing therapy.
For typical transcripts, favorable response levels include:
- 3 months: BCR::ABL1 ≤10% IS
- 6 months: BCR::ABL1 ≤1% IS
- 12 months: BCR::ABL1 ≤0.1% IS, which is MMR
- Any later time: maintaining ≤0.1% IS is generally favorable
A level above 10% at 3 months is a warning and becomes unfavorable when it remains above 10% on a confirmatory test within roughly one to three months. At 6 months, more than 10% is considered an unfavorable response; levels between more than 1% and 10% require closer assessment. At 12 months, more than 1% is unfavorable, while more than 0.1% to 1% falls into a warning range.
These categories are decision aids, not automatic commands. The oncology team considers the exact trend, TKI used, dose interruptions, side effects, adherence, drug interactions, comorbidities, disease risk, and patient goals. A person whose result is improving rapidly after a temporary interruption may be managed differently from someone with a steadily rising level despite uninterrupted therapy.
Regular testing is essential because molecular relapse can be detected before overt hematologic progression. Monitoring frequency is usually greater early in treatment and around treatment changes; stable patients with durable response may be tested at longer intervals according to guideline and local practice.
Monitoring intervals also matter. In the first year of CML therapy, PCR is commonly obtained about every three months so early molecular milestones are not missed. After a stable response is established, the interval may be lengthened according to the guideline, treatment phase, and local practice. Extra testing is reasonable after a treatment interruption, dose change, unexpected blood-count change, or a result that rises enough to threaten a previously achieved response.
Comparing results is easiest when the same validated laboratory and International Scale-calibrated method are used over time. A change between laboratories can introduce analytical differences, especially at very low transcript levels. When a surprising result would alter treatment, repeating the measurement before a major decision can help separate a true biological change from pre-analytic or assay variation.
Rising Levels, Resistance, and Kinase-Domain Mutations
A confirmed rise in BCR::ABL1 can signal loss of response, but the first step is to determine whether the change reflects biological resistance, medication exposure, or laboratory variation. Clinicians commonly review adherence, dose reductions, interacting medications, gastrointestinal absorption issues, and the pattern of previous results before concluding that a TKI has failed.
When response is clearly inadequate or a previous response is lost, testing for BCR::ABL1 kinase-domain mutations can be clinically important. These are secondary mutations within the fusion gene that alter TKI binding or signaling. They are different from the original BCR::ABL1 fusion and usually emerge under treatment selection pressure.
Specific mutations can influence drug choice. The classic example is T315I, which is resistant to several ATP-competitive TKIs but can be targeted by drugs with activity against that mutation. Modern mutation testing often uses next-generation sequencing because it can detect lower-level mutant clones than traditional Sanger sequencing.
A mutation is found in only a portion of resistant cases. Other causes include poor drug exposure, activation of alternative pathways, additional genomic changes, or progression biology not explained by an ABL1 mutation. Therefore, a negative kinase-domain mutation test does not rule out treatment resistance.
A sudden molecular rise may also prompt repeat PCR to confirm the change, blood counts, marrow examination, chromosome analysis for additional abnormalities, or other genomic testing. The workup depends on whether the concern is simple loss of MMR, persistent failure to meet milestones, or progression toward advanced-phase disease.
Deep Response and Treatment-Free Remission
Deep molecular response makes treatment-free remission possible for selected patients with CML, but stopping a TKI is a structured medical strategy rather than a consequence of one undetectable PCR result. Current guidance generally requires chronic-phase CML, a long period of effective TKI therapy, a sustained deep molecular response, access to high-quality frequent PCR monitoring, and a plan to restart treatment promptly if molecular relapse occurs.
Deep molecular response is usually defined as MR4 or deeper, meaning BCR::ABL1 ≤0.01% IS when the assay has sufficient sensitivity. Many treatment-free remission protocols use sustained MR4 or MR4.5 over a period of years before discontinuation is considered. Exact eligibility differs by guideline, country, treatment history, transcript type, and individual risk.
After stopping therapy, PCR monitoring becomes especially frequent because most molecular relapses occur early. Loss of MMR, meaning BCR::ABL1 rises above 0.1% IS, is a widely used trigger to restart TKI therapy. Most patients who restart after molecular relapse regain MMR, but the process requires disciplined follow-up.
An isolated “not detected” result is therefore not permission to stop medication. The laboratory result must be viewed as part of a sustained pattern, and stopping therapy should be planned with a CML specialist.
For patients who remain on treatment, the same PCR test continues to provide reassurance that disease control is durable. It can also guide dose adjustment, treatment changes, and investigation of unexplained rises. Few cancer biomarkers are as tightly integrated with long-term management as BCR::ABL1 in CML: it confirms the molecular target, measures treatment depth, identifies loss of response, and helps determine whether carefully selected patients can attempt life without continuous TKI therapy.
The direction of change is often more informative than a single decimal value. For example, a patient whose BCR::ABL1 level falls from 12% to 2% over a short interval is on a different trajectory from someone whose level rises from 0.08% to 2%, even though both have a 2% result today. The first pattern may represent continuing response; the second represents loss of MMR and demands prompt evaluation. Clinicians therefore review the complete molecular curve, not just whether one result sits above or below a cutoff.
The same longitudinal record also helps when care moves between hospitals. Bringing prior PCR reports, transcript type, and TKI history prevents a new team from misreading a low-level result without its baseline and treatment context.
References
- European LeukemiaNet laboratory recommendations for the diagnosis and management of chronic myeloid leukemia 2023 (Guideline)
- A review on characterization of BCR – ABL transcript variants for molecular monitoring of chronic myeloid leukemia phenotypes 2023 (Review)
- Resistance mutations in CML and how we approach them 2023 (Review)
- Beyond BCR::ABL1-The Role of Genomic Analyses in the Management of CML 2024 (Review)
- 2025 European LeukemiaNet recommendations for the management of chronic myeloid leukemia 2025 (Guideline)
- Evolving Therapeutic Algorithms in Chronic Myeloid Leukemia: Integrating Efficacy, Safety, and Survivorship 2026 (Review)
Disclaimer
This article is for general educational information and does not replace medical advice or individualized leukemia care. BCR::ABL1 targets, monitoring schedules, and treatment decisions depend on transcript type, treatment history, laboratory quality, and current clinical guidelines; results should be reviewed with a hematologist or CML specialist.