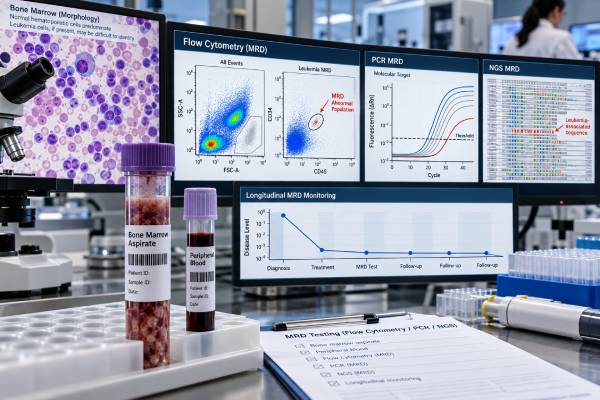
A measurable residual disease (MRD) test looks for leukemia cells that remain after treatment at levels far below what a routine blood count or microscope can reliably detect. The older phrase “minimal residual disease” is still widely used, but “measurable residual disease” better reflects what the test actually does. MRD is one of the most important response markers in acute lymphoblastic leukemia (ALL) and acute myeloid leukemia (AML) because a positive result after therapy generally signals a higher risk of relapse than a negative result, although the meaning depends on the leukemia subtype, test method, timing, specimen, and sensitivity.
MRD can be measured with multiparameter flow cytometry, polymerase chain reaction (PCR), or next-generation sequencing (NGS). Each method tracks a different biological feature. Flow cytometry recognizes abnormal cell phenotypes, PCR measures a specific fusion transcript or mutation when a suitable target exists, and NGS can identify very small amounts of a leukemia-associated sequence or immune-receptor clone. Results should always be interpreted with the treatment plan and disease genetics rather than as a stand-alone “cancer present/cancer absent” answer.
- What MRD measures: It detects residual leukemia below routine morphologic detection, often at sensitivities around 10⁻⁴ to 10⁻⁶ depending on the method and sample quality.
- What MRD positive means: Detectable disease usually indicates a higher relapse risk, but the clinical action depends on leukemia type, level, timing, and whether the signal is rising or falling.
- What MRD negative means: No disease was detected above the assay’s validated limit; it lowers risk but does not prove that every leukemia cell is gone.
- Best specimen: Bone marrow is preferred for many AML and ALL MRD assessments, while blood may be appropriate for some molecular targets or monitoring situations.
- Why timing matters: MRD after induction, during consolidation, before or after transplant, and during surveillance can answer different clinical questions.
Table of Contents
- What MRD testing means
- Flow cytometry MRD
- PCR-based MRD
- NGS-based MRD
- When MRD is tested
- How to interpret MRD results
- Limitations and next steps
What MRD testing means
MRD testing asks whether treatment has reduced leukemia to a level that is not visible by conventional morphology. A marrow may look like a complete remission under the microscope while a more sensitive assay still finds one abnormal cell among 10,000, 100,000, or even 1,000,000 normal cells.
Sensitivity is often written as a power of ten:
- 10⁻⁴ means the assay can detect approximately 1 abnormal cell among 10,000 cells under suitable conditions.
- 10⁻⁵ means approximately 1 in 100,000.
- 10⁻⁶ means approximately 1 in 1,000,000.
These are analytical goals, not guarantees for every specimen. A test cannot achieve its stated sensitivity if too few cells or DNA molecules are available. For example, a flow assay intended to reach 10⁻⁵ cannot demonstrate that level of sensitivity if the laboratory acquires only 20,000 usable cells.
MRD is especially powerful because it measures treatment response directly. Baseline genetics tell clinicians what kind of leukemia is present and how risky it may be; MRD shows how much leukemia remains after therapy. The two types of information complement one another.
The exact target depends on the disease. In AML, common strategies include flow cytometry and molecular tracking of selected abnormalities such as NPM1 or fusion transcripts. In B-ALL, flow cytometry, immunoglobulin/T-cell receptor–based molecular assays, BCR::ABL1 testing in Philadelphia chromosome–positive disease, and NGS may be used.
A diagnostic leukemia flow cytometry panel establishes the original phenotype that may later assist MRD monitoring. A broader hematologic cancer biomarker panel helps define the genetic targets and risk features available for molecular follow-up.
Flow cytometry MRD
Flow cytometry MRD identifies residual leukemia by comparing cells with the abnormal immunophenotype seen at diagnosis and by searching for patterns that differ from normal marrow maturation. Modern assays use multiple antibody markers at once and can evaluate hundreds of thousands to millions of cells.
The approach has two complementary ideas:
- Leukemia-associated immunophenotype: the laboratory looks for the same unusual antigen combination present at diagnosis.
- Different-from-normal analysis: the laboratory searches for populations whose maturation pattern is inconsistent with normal or regenerating marrow.
Using both approaches is important because leukemia cells can change phenotype during treatment. A clone may lose or gain markers after chemotherapy, targeted therapy, or immunotherapy.
Strengths of flow cytometry
Flow MRD is fast, broadly applicable, and does not require a unique gene target. It can evaluate many AML and ALL cases and may return results relatively quickly once a high-quality specimen reaches the laboratory.
Important limitations
The main limitation is specimen quality. Bone marrow hemodilution—mixing of marrow aspirate with peripheral blood—can falsely lower the apparent disease burden. Poor viability and low cell numbers also reduce sensitivity. Interpretation requires experienced laboratories because regenerating marrow contains immature cells that may resemble leukemia.
Results are often reported as a percentage, such as 0.02% abnormal blasts, together with an assay sensitivity statement. A number like 0.02% is equivalent to 2 × 10⁻⁴, or about 2 abnormal cells per 10,000 analyzed cells. That does not mean exactly two cells were observed; it expresses the estimated frequency of the abnormal population.
Flow MRD is distinct from simply counting CD34-positive cells. CD34 can be expressed by normal progenitors and is absent in some leukemias, so MRD depends on a multi-marker pattern rather than one blast marker.
PCR-based MRD
PCR MRD can be extremely sensitive when leukemia contains a stable, specific molecular target. Quantitative reverse-transcription PCR is particularly useful for fusion transcripts, while quantitative or digital PCR can track selected mutations in appropriate settings.
Examples include:
- PML::RARA in acute promyelocytic leukemia;
- BCR::ABL1 in Philadelphia chromosome–positive ALL or chronic myeloid leukemia;
- NPM1 mutations in many patients with AML; and
- recurrent fusion transcripts in selected AML subtypes.
A PML-RARA fusion test for MRD is a disease-specific example in which molecular monitoring is central to follow-up. Similarly, NPM1 mutation testing can provide a trackable AML marker when the mutation is present at diagnosis.
PCR results may be expressed as a transcript level, ratio, log reduction from baseline, or positive/negative result relative to a validated threshold. Because assays differ, the report’s method and laboratory-specific interpretation matter.
Why molecular target selection matters
Not every mutation found at diagnosis is suitable for MRD. Some mutations associated with clonal hematopoiesis can persist in nonleukemic blood-forming cells after successful AML treatment. Mutations in genes such as DNMT3A, TET2, and ASXL1 may therefore be poor stand-alone MRD targets in many AML settings. Persistent detection may reflect a preleukemic clone rather than active leukemia.
This is a major reason MRD interpretation should be target-specific. A detectable NPM1 signal after therapy does not carry the same meaning as a persistent low-level DNMT3A mutation.
NGS-based MRD
Next-generation sequencing can detect residual leukemia by deeply sequencing DNA or RNA targets. In B-ALL, one important strategy tracks patient-specific immunoglobulin or T-cell receptor rearrangements identified from the original leukemia. In AML, error-corrected sequencing can track selected leukemia-associated mutations, although target choice remains critical.
NGS can reach very high sensitivity, often around 10⁻⁵ and in optimized settings 10⁻⁶. That ability can identify residual disease in some samples that are negative by lower-sensitivity methods.
A clonal-sequence MRD test is an example of an NGS approach that can track an immune-receptor sequence over time in suitable leukemias.
Does a more sensitive test always give a better answer?
Not automatically. Greater analytical sensitivity is useful only when the detected signal has validated clinical meaning. Ultra-low-level positivity may have different implications depending on the leukemia subtype, treatment platform, timing, and whether the result is confirmed on repeat testing.
In B-ALL, NGS may identify patients with residual disease below the detection threshold of conventional flow cytometry. In AML, NGS interpretation can be more complicated because age-related or preleukemic clones may persist even when leukemia is in remission.
For this reason, clinicians often consider concordance between methods. A patient who is negative by both high-quality flow and a leukemia-specific molecular test may have a different risk profile from someone with a low-level positive molecular result but negative flow.
When MRD is tested
The value of an MRD result depends heavily on when it is measured. A positive test early in treatment can have a different meaning from persistent positivity after several treatment phases.
Common time points include:
- after induction therapy: assesses the early depth of response;
- after consolidation or additional treatment blocks: shows whether disease continues to clear;
- before hematopoietic stem cell transplantation: helps estimate relapse risk entering transplant;
- after transplantation: can provide an early warning of molecular or cellular recurrence; and
- during surveillance: selected molecular targets may be followed serially to identify re-emergence before overt hematologic relapse.
In ALL, MRD is deeply integrated into risk stratification and may influence whether treatment is intensified, whether targeted or immune therapy is added, or whether transplant is considered. In AML, MRD also carries strong prognostic information, but the best way to change therapy based solely on some MRD findings is still evolving and depends on disease genetics and treatment setting.
A single result should therefore be read as part of a trajectory. Falling disease from 1% to 0.02% shows a major response but still leaves measurable leukemia. A stable or rising low-level result may be more concerning than one isolated borderline signal that becomes negative on repeat testing.
How to interpret MRD results
The most useful MRD report answers four questions: Was disease detected? At what level? How sensitive was the assay? Was the specimen adequate?
| Report wording | What it generally means | Important caution |
|---|---|---|
| MRD negative | No leukemia detected above the assay’s validated detection capability | Does not prove zero leukemia cells remain |
| MRD positive | Residual leukemia detected and quantified or qualitatively identified | Clinical significance depends on level, timing, and subtype |
| Detected below quantifiable range | A signal is present but too low for reliable precise measurement | Repeat or confirmatory testing may be useful |
| Inadequate or limited | Cell number, DNA quantity, hemodilution, or quality limits sensitivity | A negative result may be less reassuring |
MRD negativity is associated with lower relapse risk in many leukemia settings, but it is not the same as cure. Leukemia can exist below the detection threshold or in a site not sampled by the test. Conversely, a low positive result is not always an immediate relapse. Some molecular signals require confirmation, serial assessment, or interpretation against known clonal hematopoiesis.
The number should also be matched to the method. A flow result of 0.01% cannot be directly treated as equivalent to an NGS result at the same numerical level unless the assays have comparable biological targets, validation, and specimen quality.
Limitations and next steps
The most common MRD pitfalls are methodological rather than conceptual. Bone marrow can be diluted, too few cells can be collected, a molecular target can disappear through clonal evolution, or a mutation can persist in a nonleukemic clone. Treatment can alter antigen expression and make flow detection harder. Laboratories also differ in panel design, sequencing depth, reporting thresholds, and validation.
If an MRD result is unexpectedly positive or negative, clinicians may ask whether:
- the specimen was technically adequate;
- the result agrees with another MRD method;
- the same target was present at diagnosis;
- the assay reached its stated sensitivity;
- repeat testing confirms the trend; and
- marrow morphology, blood counts, and other disease markers support the result.
Patients should not change therapy based on an isolated number without discussing the disease-specific meaning with the treating hematology team. In some ALL settings, MRD directly informs treatment decisions. In AML, an MRD-positive result may affect transplant planning, surveillance, or trial eligibility, but management remains individualized.
The most practical way to read the report is to ask: What was the assay’s detection limit, how much disease was found, how does this compare with the last test, and what action is recommended for this leukemia subtype? Those questions distinguish a useful MRD interpretation from a simple positive/negative label.
How timing changes the meaning of an MRD result
MRD is a time-point-specific measurement. A positive result at diagnosis is not called MRD because the disease is already known to be present; the term becomes meaningful after therapy has reduced the leukemia burden. Common checkpoints include after induction, after consolidation, before or after stem-cell transplantation, and during longer-term surveillance, but the clinically important time points depend on the leukemia subtype and treatment protocol.
The same numerical result can carry different implications at different checkpoints. Detectable disease early in therapy may still clear with subsequent treatment, whereas persistence or reappearance later can signal a higher relapse risk. Trends are therefore often more informative than one isolated value. A falling molecular level, stable low-level detection, and a newly rising level are not interchangeable patterns.
What to do when MRD methods disagree
Flow cytometry, PCR, and NGS do not measure exactly the same target. Flow recognizes an abnormal cell phenotype, PCR tracks a defined molecular sequence, and NGS may identify a leukemia-specific rearrangement or mutation with very high analytic sensitivity. Discordant results can occur because of different detection limits, sampling error, clonal evolution, target loss, or marrow dilution.
When one method is positive and another is negative, clinicians first ask whether both assays were technically appropriate for that leukemia and specimen. They also consider the absolute level, whether the finding is reproducible, and whether the target is known to remain stable through relapse. Repeat testing or confirmation with an orthogonal method may be appropriate before a major treatment decision, particularly for a borderline result near an assay cutoff.
Detection limit and quantification limit are not the same
MRD reports may distinguish the limit of detection, the smallest amount an assay can reliably notice, from the limit of quantification, the smallest amount it can measure with acceptable precision. A result described as “detected below the quantifiable range” can therefore be genuinely positive even though the laboratory cannot assign a robust numerical level. The clinical meaning depends on the leukemia type, treatment checkpoint, assay target, and whether the finding persists on repeat testing.
MRD should also be reported with the specimen source. Bone marrow is preferred for many leukemia MRD assessments because disease may be less abundant in peripheral blood. For some molecular targets, blood can still be useful for serial monitoring, but the relative sensitivity differs by disease and method. Comparing a blood result with a prior marrow result as though they were equivalent can create a misleading trend.
References
- 2021 Update on MRD in acute myeloid leukemia: a consensus document from the European LeukemiaNet MRD Working Party 2021 (Guideline)
- Diagnosis, prognostic factors, and assessment of ALL in adults: 2024 ELN recommendations from a European expert panel 2024 (Guideline)
- Clinical use of measurable residual disease in adult ALL: recommendations from a panel of US experts 2025 (Review)
- Measurable Residual Disease Detection in Acute Myeloid Leukemia: Current Challenges and Future Directions 2024 (Review)
- Challenges of detecting measurable/minimal disease in acute leukemia 2023 (Review)
- Measurable residual disease testing by next generation sequencing is more accurate compared with multiparameter flow cytometry in adults with B-cell acute lymphoblastic leukemia 2024
Disclaimer
This article is for general education and does not replace interpretation by a hematologist or specialized laboratory. MRD results depend on leukemia subtype, specimen quality, assay sensitivity, treatment timing, and the molecular or immunophenotypic target being measured. Do not change treatment based on an MRD result without discussing it with the treating cancer team.