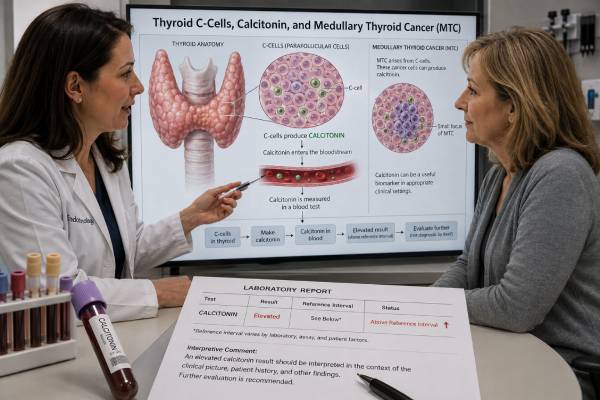
A calcitonin blood test measures a hormone made mainly by the thyroid gland’s parafollicular cells, better known as C-cells. The test is most useful when a clinician is looking for medullary thyroid cancer, evaluating a suspicious thyroid nodule, or monitoring someone who has already been treated for that cancer. A high result does not prove cancer by itself. Calcitonin can rise because of kidney disease, certain medicines, smoking, other neuroendocrine conditions, C-cell hyperplasia, laboratory interference, and several less common causes. Interpretation also depends on the assay, sex-specific reference limits, the size and behavior of any thyroid nodule, and whether the value is stable or increasing over time. Low or undetectable calcitonin is usually not a health concern. The most informative next step is often a repeat measurement under controlled conditions, combined with thyroid imaging, clinical history, and other tests rather than a single cutoff viewed in isolation.
- Calcitonin mainly reflects thyroid C-cell activity and is a key tumor marker for medullary thyroid cancer.
- A mildly high value is not diagnostic; repeat testing and review of medicines, kidney function, smoking, and assay factors are often needed.
- Marked elevations—especially persistent values around 60–100 pg/mL or higher—raise much stronger concern, but laboratory-specific interpretation still applies.
- After medullary thyroid cancer treatment, calcitonin trends and doubling time help assess residual disease, recurrence risk, and disease pace.
- Fasting is not always required, but consistent preparation and testing at the same laboratory can make serial results easier to compare.
Table of Contents
- What the Calcitonin Test Measures
- Why the Test Is Ordered
- Preparation and Test Procedure
- Normal Ranges and High Results
- Causes of Elevated Calcitonin
- Calcitonin and Medullary Thyroid Cancer
- Low or Undetectable Calcitonin
- Next Steps After Your Results
What the Calcitonin Test Measures
Calcitonin is a 32-amino-acid peptide hormone. In adults, most circulating calcitonin comes from C-cells scattered between the thyroid follicles. These cells are different from the follicular cells that make thyroxine, or T4, and triiodothyronine, or T3. That distinction explains why calcitonin is not a routine measure of whether the thyroid is underactive or overactive. A person can have normal TSH and thyroid hormone levels while having an abnormal calcitonin result.
Calcitonin can reduce blood calcium in experimental settings by limiting bone breakdown and increasing calcium loss through the kidneys. In everyday adult physiology, however, it is not the main controller of calcium balance. Parathyroid hormone and vitamin D have much larger roles. People who have their thyroid removed generally do not develop a clinically important calcitonin-deficiency syndrome.
The test is valuable because medullary thyroid cancer develops from C-cells. As those cells multiply, they often release increasing amounts of calcitonin into the bloodstream. The measurement therefore serves as a biochemical marker of C-cell mass and activity. It can contribute to diagnosis, help plan the extent of evaluation before surgery, and reveal persistent or recurrent disease after treatment.
Calcitonin is measured with an immunoassay. Different manufacturers use different antibodies, calibration systems, and detection limits. As a result, a value from one laboratory may not be directly interchangeable with a value from another. Modern assays are sensitive, but they can still be affected by heterophile antibodies, biotin in some platforms, “macrocalcitonin,” sample handling, or uncommon assay effects at very high concentrations.
A calcitonin result should therefore be read alongside the laboratory’s own reference interval. When follow-up depends on small changes, using the same laboratory and assay is often more useful than comparing numbers produced by different methods. This principle also applies to other thyroid blood test panels, although calcitonin answers a different clinical question from TSH, T4, or T3.
Why the Test Is Ordered
Clinicians most often order calcitonin when medullary thyroid cancer is possible or already known. The exact reason changes how the result should be interpreted.
Common situations include:
- A thyroid nodule with suspicious ultrasound features or indeterminate needle-biopsy findings
- A personal history of medullary thyroid cancer
- A family history of medullary thyroid cancer or multiple endocrine neoplasia type 2, called MEN2
- A known disease-causing variant in the RET gene
- Follow-up after thyroid surgery for medullary thyroid cancer
- Unexplained flushing or secretory diarrhea in a person with other findings that suggest advanced medullary thyroid cancer
- Investigation of a cervical lymph node or thyroid mass when routine cytology is inconclusive
Whether every person with a thyroid nodule should receive a calcitonin test remains debated. Some European guidance supports testing in selected nodule settings and before surgery or minimally invasive treatment. Other practice settings use it more selectively because medullary thyroid cancer is uncommon, mildly elevated results can trigger extensive evaluation, and reference limits vary. Local guidelines, clinician experience, and the patient’s risk profile all influence the decision.
Calcitonin is especially important for people with inherited risk. MEN2 syndromes result from pathogenic RET variants and can include medullary thyroid cancer, pheochromocytoma, and parathyroid disease. Genetic testing—not calcitonin alone—identifies inherited susceptibility. Calcitonin may then help assess C-cell activity and guide timing decisions within a specialist plan. Relatives should not use a normal result as a substitute for recommended genetic counseling and RET testing.
After medullary thyroid cancer has been treated, calcitonin becomes a surveillance marker. A level that falls to very low or undetectable values after surgery is reassuring. A persistently measurable or rising level can indicate remaining thyroid tissue, residual cancer, or recurrence. The trend is more useful than one isolated result, especially when paired with carcinoembryonic antigen, or CEA.
Calcitonin is not generally ordered to evaluate common symptoms of hypothyroidism, such as fatigue, constipation, or cold intolerance. Those concerns usually begin with a TSH test and often free T4. It is also not a general cancer-screening test for people without a thyroid finding, inherited risk, or relevant clinical indication.
Preparation and Test Procedure
The test requires a standard blood sample, usually taken from a vein in the arm. Collection takes only a few minutes. Bruising, brief soreness, or lightheadedness may occur, but serious complications are uncommon.
Preparation instructions differ among laboratories. Some clinicians request an overnight fast because meals can produce small or inconsistent changes and because fasting reduces avoidable variation. Others do not require fasting for a basal calcitonin measurement. Follow the instructions printed on the order or supplied by the laboratory rather than applying a universal rule.
Before the test, tell the clinician about:
- Proton pump inhibitors such as omeprazole, pantoprazole, or esomeprazole
- Biotin supplements, including high-dose hair, skin, and nail products
- Smoking or recent nicotine use
- Chronic kidney disease
- Pregnancy or breastfeeding
- Recent major illness, infection, surgery, or hospitalization
- A history of thyroid surgery or medullary thyroid cancer
- Previous calcitonin results and the laboratory that performed them
Do not stop a prescribed medicine solely to change a laboratory result. A clinician may decide that a medicine can be paused safely, may repeat the test without changing treatment, or may interpret the result in context. Proton pump inhibitors can raise gastrin and may be associated with mild C-cell stimulation in some circumstances, but the effect is not predictable enough to make unsupervised medication changes appropriate.
Biotin deserves specific attention because it can interfere with some immunoassays. The direction and size of interference depend on the test platform. A laboratory may recommend stopping nonessential high-dose biotin for a defined period before collection. People taking biotin for a medical reason should ask the prescriber first.
For serial monitoring, consistency improves interpretation. Try to use the same laboratory, similar fasting status, and similar timing relative to medicines. Record the assay’s reference interval because a change in laboratory method can look like a biological change when it is actually analytical.
Most testing uses an unstimulated, or basal, calcitonin level. Calcium or pentagastrin stimulation tests were historically used when basal results were borderline. Pentagastrin is unavailable in many countries, and recent evidence has not shown a clear routine advantage over modern basal assays. A specialist may still use calcium stimulation in selected cases, but interpretation requires method-specific and often sex-specific thresholds.
Normal Ranges and High Results
There is no single universal normal range. Laboratories may report results in picograms per milliliter (pg/mL) or nanograms per liter (ng/L); these units are numerically equivalent. Reference limits are commonly higher in men than in women because men tend to have greater C-cell mass. Assay design, age, smoking, and kidney function also contribute to variation.
A report might use upper limits roughly in the range of 5–10 pg/mL for women and 8–15 pg/mL for men, but some assays use different cutoffs. The laboratory’s interval is the correct starting point. Values below the assay’s detection limit may be reported as “less than” a number rather than as zero.
The table below describes broad patterns, not diagnostic rules.
| Pattern | General interpretation | Common next step |
|---|---|---|
| Below or within the laboratory range | Usually no biochemical evidence of increased C-cell activity | Interpret with the reason for testing and any inherited risk |
| Slightly above the upper limit | Often nonspecific; medicines, smoking, kidney disease, assay variation, or early C-cell disease may be considered | Repeat under controlled conditions and review confounders |
| Persistently elevated but below about 60 pg/mL | Indeterminate zone in which benign causes, C-cell hyperplasia, and medullary thyroid cancer can overlap | Endocrinology review, repeat testing, ultrasound, and selective additional evaluation |
| Around 60–100 pg/mL or higher | Increasingly suspicious for medullary thyroid cancer, particularly if persistent | Prompt specialist evaluation and anatomical assessment |
| Very high or rapidly rising | Strong concern for substantial C-cell tumor burden or progressive disease in the right clinical setting | Urgent coordinated evaluation by an experienced thyroid cancer team |
The often-cited 60–100 pg/mL range is not a universal diagnostic boundary. A value above it is highly concerning in many modern assays, but sensitivity and specificity vary. Smaller medullary cancers can produce lower levels. Rare tumors produce little calcitonin. Conversely, noncancer causes can occasionally produce substantial elevations.
Clinicians pay attention to the magnitude of elevation, whether it persists, and whether the number changes. For example, a result of 14 pg/mL with an upper limit of 10 pg/mL is a different problem from a result of 800 pg/mL. A repeat value that returns to normal suggests transient or analytical variation. A steady increase across comparable tests deserves more investigation.
Laboratory sex markers may not fully account for transgender hormone therapy, variations in sex development, or changes in C-cell mass after thyroid surgery. In these situations, the raw value, assay method, anatomy, prior results, and clinical history may be more informative than a binary male/female flag.
Causes of Elevated Calcitonin
Medullary thyroid cancer is the most important cause to exclude, but it is not the only explanation. A careful review prevents both delayed diagnosis and unnecessary alarm.
C-cell conditions
C-cell hyperplasia means an increased number of C-cells. It can occur as a precursor in hereditary MEN2-related disease, but reactive or secondary forms also occur. C-cell hyperplasia and very small medullary cancers may produce overlapping calcitonin values. Pathology, genetics, imaging, and the biochemical pattern help distinguish them.
Medullary thyroid cancer may be sporadic or hereditary. Sporadic disease usually appears as a single thyroid tumor, while inherited disease can be multifocal and occur at younger ages. Calcitonin often rises with tumor burden, yet it cannot define stage by itself.
Noncancer medical causes
Chronic kidney disease can increase calcitonin because of altered clearance and changes in hormone metabolism. Severe illness, sepsis, and some inflammatory states may raise calcitonin or related peptides. Hypergastrinemia, autoimmune thyroid disease, multinodular goiter, and other thyroid disorders have also been linked with mild elevations, though the strength of these associations varies.
Other neuroendocrine tumors can occasionally produce calcitonin. These may arise in the lung, pancreas, or gastrointestinal tract. This possibility is uncommon and usually investigated only when thyroid evaluation does not explain a convincing elevation.
Medicines, habits, and analytical factors
Smoking is associated with higher average calcitonin levels, particularly in men. Proton pump inhibitors may contribute indirectly through elevated gastrin. Glucocorticoids, beta-blockers, and other drugs have been reported as possible influences, but effects are inconsistent and rarely explain a markedly high value without other context.
Laboratory interference can create a false elevation. Heterophile antibodies may bind assay antibodies and produce signal despite little true calcitonin. Macrocalcitonin occurs when calcitonin forms a large complex with an immunoglobulin; the assay detects it even though its biological meaning differs from ordinary circulating hormone. A laboratory can investigate suspected interference with dilution studies, blocking reagents, polyethylene glycol precipitation, or an alternative assay.
A falsely low result is also possible. Extremely high analyte concentrations can rarely saturate an immunoassay and produce a “hook effect.” Modern laboratories reduce this risk through assay design and dilution protocols, but clinicians may contact the laboratory when a low value conflicts sharply with pathology or imaging.
The thyroglobulin blood test should not be used as a substitute. Thyroglobulin tracks differentiated thyroid cells and cancers, whereas calcitonin tracks C-cell disease. The two markers come from different cell types and answer different follow-up questions.
Calcitonin and Medullary Thyroid Cancer
Calcitonin can support every major phase of medullary thyroid cancer care, but each phase uses it differently.
Before diagnosis and surgery
When a thyroid nodule is present, a clearly elevated calcitonin level raises suspicion even if fine-needle aspiration cytology is nondiagnostic. Medullary cancer can be missed on cytology because its appearance varies and it is much less common than papillary thyroid cancer. Measuring calcitonin in the washout fluid from a needle sample may improve detection in selected nodules or lymph nodes.
The preoperative level gives a rough indication of tumor burden and the likelihood of lymph-node disease, but it cannot replace neck ultrasound or other imaging. Surgeons may use the level along with tumor size, ultrasound findings, cytology, CEA, RET testing, and clinical examination. Higher values generally correlate with more extensive disease, yet individual overlap is substantial.
Anyone diagnosed with medullary thyroid cancer should usually be offered germline RET testing, even without a known family history. Finding a pathogenic variant can affect surgical planning, screening for pheochromocytoma, and testing of relatives. Before thyroid surgery in MEN2, clinicians must assess for pheochromocytoma because an unrecognized catecholamine-producing tumor can create severe anesthetic risk.
After surgery
Calcitonin does not fall instantly. It has a short biological half-life, but clinicians commonly wait about two to three months after surgery before using the postoperative result to define biochemical response. Testing too early can confuse residual circulating hormone with persistent disease.
An undetectable or very low postoperative calcitonin suggests a complete biochemical response. A measurable value may indicate residual normal C-cells, remaining thyroid tissue, lymph-node disease, or distant metastasis. The meaning depends on the absolute level, surgical details, imaging, and whether the value falls, stabilizes, or rises.
CEA is measured with calcitonin because the two markers provide complementary information. In some advanced tumors, calcitonin production becomes less prominent while CEA rises. A discordant pattern can signal tumor dedifferentiation and deserves specialist review.
Doubling time
Doubling time estimates how long it would take a marker to double if the observed growth rate continued. It requires several measurements collected over a meaningful period using comparable methods. A short calcitonin or CEA doubling time is associated with more aggressive disease; a long doubling time suggests slower progression.
Doubling time should not be calculated from two closely spaced results or from values near the assay’s detection limit. Minor analytical noise can produce a misleading estimate. Clinicians generally use validated calculators and at least three or four results over roughly two years when possible, although urgent clinical circumstances may require earlier decisions.
A rising marker does not always reveal where disease is located. Imaging sensitivity depends on the calcitonin level, disease volume, and site. Neck ultrasound, contrast-enhanced CT or MRI, and selected nuclear imaging may be used. Treatment is not started solely because a number is detectable; the pace, location, symptoms, resectability, and radiographic progression all matter.
Low or Undetectable Calcitonin
A low calcitonin result is usually normal. Unlike low thyroid hormone, low calcitonin does not typically cause fatigue, weight gain, bone disease, or abnormal calcium levels. No calcitonin-replacement treatment is needed after thyroidectomy.
In a person being evaluated for a thyroid nodule, a value within the reference range makes a calcitonin-secreting medullary cancer less likely but does not reduce the risk to zero. Rare medullary tumors are calcitonin-negative or secrete only small amounts. Ultrasound findings and biopsy results still require appropriate follow-up.
In someone treated for medullary thyroid cancer, undetectable calcitonin is generally favorable. Interpretation is strongest when CEA is also appropriate, imaging is reassuring, and the result remains stable over time. The exact follow-up schedule depends on the original stage, pathology, RET status, and previous marker levels.
A sudden drop from a previously high level can reflect successful treatment, but it can also reflect a new assay, sample problem, interference, or rarely reduced secretion by a changing tumor. Clinicians often repeat an unexpected result and compare it with CEA and imaging before drawing conclusions.
Calcitonin should not be confused with procalcitonin. Procalcitonin is a related precursor widely used as an infection marker, especially in severe bacterial illness. Some medullary thyroid cancers also produce procalcitonin, and specialists may use it as an adjunct when calcitonin is difficult to interpret. However, infection can raise procalcitonin, so the tests are not interchangeable.
Next Steps After Your Results
A result outside the reference range should lead to a structured review rather than a conclusion based on the red flag alone.
- Confirm the context. Check why the test was ordered, whether a thyroid nodule or prior cancer is present, and whether there is a family history of medullary thyroid cancer or MEN2.
- Verify the laboratory details. Note the assay, units, reference interval, and whether the result was repeated on dilution or with an alternative method.
- Review possible confounders. Discuss kidney function, smoking, proton pump inhibitors, biotin, recent illness, pregnancy, and other relevant conditions.
- Repeat when appropriate. A mildly abnormal result is often repeated under comparable, controlled conditions. Markedly abnormal results may move directly to specialist assessment while confirmation is arranged.
- Combine biochemical and anatomical information. Thyroid and neck ultrasound, cytology, calcitonin washout, CEA, RET testing, and cross-sectional imaging may be appropriate depending on the value and clinical setting.
- Track trends after treatment. Use the same assay when possible and calculate doubling time only from enough reliable data points.
Seek prompt medical assessment for a rapidly enlarging neck mass, new trouble breathing or swallowing, persistent hoarseness, severe unexplained diarrhea with dehydration, or symptoms that could suggest pheochromocytoma in a person with MEN2 risk, such as episodic pounding headaches, sweating, palpitations, and very high blood pressure. These symptoms do not diagnose medullary thyroid cancer, but they should not wait for routine follow-up.
Questions to bring to an appointment include:
- How far above this laboratory’s reference limit is my result?
- Could my medicines, supplements, smoking, or kidney function affect it?
- Should the sample be repeated at the same laboratory or checked with another assay?
- Do I need a thyroid ultrasound, biopsy review, CEA, or RET genetic testing?
- If I have treated medullary thyroid cancer, what are my calcitonin and CEA doubling times?
- Which change in symptoms or test results should trigger earlier contact?
A calcitonin result is most useful when it is connected to the clinical reason for testing. Mild abnormalities often require careful confirmation. Persistent or substantial elevations deserve evaluation by an endocrinologist, endocrine surgeon, or thyroid cancer team experienced with medullary disease.
References
- Diagnostic tests for medullary thyroid carcinoma: an umbrella review 2023 (Systematic Review)
- 2023 European Thyroid Association Clinical Practice Guidelines for thyroid nodule management 2023 (Guideline)
- Determinants of circulating calcitonin value 2024
- Serum Biochemical Markers for Medullary Thyroid Carcinoma: Current Approach and Future Perspectives 2024 (Review)
- Calcitonin as Biomarker for the Medullary Thyroid Carcinoma 2025 (Review)
- Current Guidelines for Management of Medullary Thyroid Carcinoma 2021 (Review)
Disclaimer
Calcitonin results require interpretation with the specific assay, clinical history, imaging, and reason for testing. A high value does not by itself diagnose medullary thyroid cancer, and a normal value cannot rule out every thyroid condition. Discuss abnormal or changing results with a qualified clinician rather than changing medicines or delaying recommended evaluation.