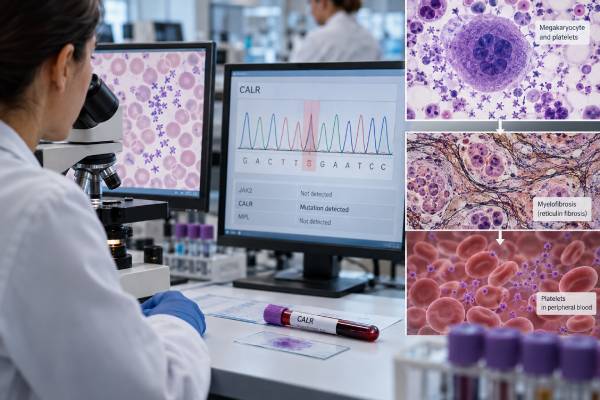
A CALR mutation test looks for acquired changes in the calreticulin gene that help diagnose and classify certain BCR::ABL1-negative myeloproliferative neoplasms, especially essential thrombocythemia (ET) and primary myelofibrosis (PMF). CALR mutations are usually found in blood-forming cells rather than inherited through families, and they are most often tested when a person has persistent thrombocytosis, bone marrow findings suggesting an MPN, or unexplained marrow fibrosis. A positive CALR result supports a clonal myeloid disorder, but it does not by itself establish ET or PMF; blood counts, bone marrow morphology, clinical features, and exclusion of other causes still matter. The two best-known mutation patterns are type 1, a 52-base-pair deletion, and type 2, a 5-base-pair insertion. Their prognostic associations differ somewhat between ET and myelofibrosis. A negative CALR test also does not rule out an MPN because JAK2, MPL, or less common mutations may be present instead.
- A positive CALR mutation usually supports an MPN diagnosis when the clinical picture fits, particularly essential thrombocythemia or primary myelofibrosis.
- CALR is not a platelet-count test: the mutation is a molecular marker, while platelet numbers are measured separately on a complete blood count.
- Type 1 and type 2 CALR mutations are not identical: they have different biological and prognostic associations, especially in myelofibrosis.
- A negative result does not exclude an MPN: JAK2, MPL, and other clonal mutations may explain the disease.
- No fasting is usually needed: testing commonly uses peripheral blood, while bone marrow is often evaluated separately for diagnosis and classification.
Table of Contents
- What CALR testing measures
- Why CALR matters in myeloproliferative neoplasms
- When CALR testing is ordered
- How CALR testing is performed
- How to interpret a CALR result
- Prognosis and treatment implications
- Limitations and next steps
What CALR testing measures
CALR encodes calreticulin, a protein involved in protein folding and calcium handling inside the endoplasmic reticulum. In myeloproliferative neoplasms, the clinically important CALR variants are usually somatic frameshift mutations in exon 9. These changes create a new abnormal C-terminal portion of the protein and remove the normal KDEL retention signal.
Mutant CALR can bind to the thrombopoietin receptor MPL and drive persistent JAK-STAT signaling. That signaling promotes abnormal growth of megakaryocytes and other blood-forming cells, helping explain why CALR mutations are strongly associated with ET and PMF.
Two mutation patterns account for a large share of CALR-positive cases:
- Type 1: a 52-base-pair deletion, often written as c.1092_1143del or p.L367fs*46 depending on transcript notation.
- Type 2: a 5-base-pair insertion, often written as c.1154_1155insTTGTC or p.K385fs*47.
Many other exon 9 indels exist and are commonly grouped as “type 1-like” or “type 2-like” based on how they alter the protein’s charge and structure.
The test detects a clonal molecular abnormality; it does not directly measure platelet function, blood thickness, marrow fibrosis, or spleen size. Those features require other tests.
CALR testing is usually considered together with JAK2 V617F testing and MPL mutation testing. A broader myeloproliferative neoplasm panel can evaluate these driver genes and, when appropriate, additional myeloid genes.
Why CALR matters in myeloproliferative neoplasms
CALR is one of the three major driver genes in classical BCR::ABL1-negative MPNs, along with JAK2 and MPL. In ET and PMF, identifying one of these driver mutations provides strong evidence that abnormal blood production is clonal rather than simply reactive.
In essential thrombocythemia, persistent platelet elevation can have many causes. Iron deficiency, inflammation, infection, recent surgery, splenectomy, and some cancers can produce reactive thrombocytosis. A CALR mutation in the right clinical setting strongly favors an MPN over those secondary causes.
In primary myelofibrosis, CALR status helps confirm clonality and contributes to prognostic models. Bone marrow architecture remains critical because prefibrotic PMF can resemble ET in blood counts, yet its marrow morphology and long-term risks differ.
CALR mutations are generally mutually exclusive with the main JAK2 V617F and MPL driver mutations, although rare coexisting cases are reported. In routine practice, finding one canonical driver usually explains the core JAK-STAT activation.
CALR mutations are uncommon in polycythemia vera. PV is overwhelmingly associated with JAK2 alterations, including V617F or exon 12 mutations. Therefore, a CALR-positive result in a patient thought to have PV should prompt careful review of the diagnosis.
The absence of JAK2, CALR, and MPL is sometimes called triple-negative MPN. Triple-negative status does not automatically mean there is no clonal disease. Next-generation sequencing can identify other mutations that support clonality and may affect prognosis.
When CALR testing is ordered
CALR testing is often ordered when an MPN is suspected and JAK2 V617F is negative, especially in a patient with sustained thrombocytosis or features of myelofibrosis. Some laboratories test JAK2, CALR, and MPL together from the start.
Common clinical triggers include:
- platelets repeatedly above the reference range without a clear reactive cause;
- abnormal megakaryocytes or fibrosis on bone marrow biopsy;
- unexplained splenomegaly;
- constitutional symptoms such as night sweats or weight loss in an MPN-like picture;
- thrombosis or unusual-site thrombosis with suggestive blood findings; or
- an established ET or PMF diagnosis that needs molecular classification.
Testing should not be ordered solely because of one mildly elevated platelet count. Platelets can rise transiently after infection, inflammation, tissue injury, blood loss, or iron deficiency. Repeating the blood count and evaluating common secondary causes is often appropriate before extensive molecular workup.
The platelet level itself does not predict which driver mutation is present. CALR-mutated ET often has higher platelet counts on average than JAK2-mutated ET, but there is substantial overlap among patients.
In suspected ET or PMF, molecular testing does not replace a bone marrow biopsy. Current disease classifications use marrow morphology to distinguish ET, prefibrotic PMF, overt PMF, and other myeloid neoplasms.
How CALR testing is performed
Most CALR tests use DNA from peripheral blood leukocytes. A standard blood draw is usually sufficient, and fasting is not required. Bone marrow DNA can also be used, especially when a marrow specimen is already being collected for diagnosis.
Laboratories may use fragment analysis, PCR-based assays, Sanger sequencing, or next-generation sequencing. Because the classic variants are insertions and deletions in exon 9, the method must be validated to detect indels reliably.
A focused assay may identify common type 1 and type 2 variants efficiently, while broader sequencing can detect uncommon exon 9 changes and other myeloid mutations. The report may include:
- the exact DNA variant;
- the predicted protein change;
- whether it is type 1, type 2, or another CALR indel;
- variant allele frequency; and
- an interpretation such as pathogenic or disease-associated.
Variant allele frequency is not the same as disease percentage. It reflects the fraction of sequencing reads carrying the mutation and can be affected by sample composition, copy number, assay sensitivity, and clonal structure.
Unlike some inherited genetic tests, CALR MPN testing usually does not require family testing because the mutation is acquired in the blood-forming clone. Rare germline CALR variants exist, but the classic exon 9 frameshift mutations in ET and PMF are somatic.
How to interpret a CALR result
A positive CALR exon 9 frameshift mutation is a strong clonal marker for an MPN when the clinical picture is compatible. The result should be integrated with blood counts, marrow findings, and exclusion of BCR::ABL1-positive chronic myeloid leukemia and reactive causes.
| Result | General interpretation | What it does not prove |
|---|---|---|
| Pathogenic CALR exon 9 frameshift detected | Supports a clonal MPN, especially ET or PMF | Does not by itself distinguish ET from prefibrotic or overt PMF |
| Type 1 or type 1-like CALR | Common in PMF and ET; may carry favorable prognostic associations in PMF relative to some other molecular groups | Does not guarantee mild disease |
| Type 2 or type 2-like CALR | Common in ET and also seen in PMF | Does not determine thrombosis risk by itself |
| No CALR mutation detected | CALR-positive MPN is less likely | Does not rule out JAK2-, MPL-, or other mutation-positive MPN |
| Unusual CALR variant | May require expert classification to establish whether it creates the characteristic pathogenic frameshift | Not every CALR sequence change is an MPN driver |
A positive result is not equivalent to “cancer stage.” ET and PMF are chronic myeloid neoplasms, but their severity is determined by many factors beyond the driver mutation.
A negative result is especially important to interpret correctly. If JAK2 and CALR are both negative in suspected ET or PMF, MPL testing is usually considered. Broader myeloid sequencing may then identify mutations in genes such as ASXL1, TET2, DNMT3A, EZH2, SRSF2, U2AF1, IDH1, or IDH2. Some support clonality; others are more useful for prognosis than for establishing the primary driver.
Prognosis and treatment implications
CALR status provides prognostic information, but its meaning differs between ET and myelofibrosis.
In essential thrombocythemia, CALR-mutated patients are often younger and have higher platelet counts than JAK2-mutated patients. Several studies have found a lower thrombosis risk in CALR-mutated ET than in JAK2-mutated ET, particularly when traditional thrombotic risk factors are absent. Treatment decisions still depend heavily on age, prior thrombosis, cardiovascular risk, symptoms, bleeding risk, and platelet count.
In primary myelofibrosis, the exact CALR subtype matters more. Type 1 or type 1-like CALR mutations are often associated with a more favorable survival profile than unfavorable molecular groups, while type 2-like mutations generally do not carry the same favorable prognostic weight. Modern prognostic scores may incorporate driver mutation status plus high-molecular-risk mutations and chromosome findings.
CALR positivity does not mean a patient should automatically receive a JAK inhibitor, interferon, hydroxyurea, or stem cell transplant. Therapy targets the disease phenotype and risk. For ET, the main goal is often prevention of thrombosis and control of symptoms. For myelofibrosis, treatment may address splenomegaly, constitutional symptoms, anemia, disease progression, or transplant eligibility.
The presence of mutant CALR is also an active area of therapeutic research because the abnormal C-terminal sequence is specific to the malignant clone. Antibody and T-cell strategies designed to recognize mutant CALR are being studied, but they are not yet routine standard-of-care treatments.
Serial CALR allele burden testing is not universally required in stable ET or PMF. It may be used in research or selected clinical contexts, but routine disease monitoring still relies primarily on symptoms, examination, blood counts, marrow assessment when indicated, and other disease-specific measures.
Limitations and next steps
The most important limitation is that CALR is only one part of MPN diagnosis. A positive mutation confirms clonality but does not replace marrow morphology. A negative result does not rule out MPN. And a high platelet count does not automatically mean CALR testing will be positive.
Common interpretation mistakes include:
- assuming any CALR variant is pathogenic;
- equating mutation positivity with disease severity;
- using a CALR result alone to distinguish ET from prefibrotic PMF;
- forgetting that polycythemia vera is primarily a JAK2-driven disease; and
- treating a negative CALR result as a complete negative MPN workup.
After a positive result, the next steps usually include confirming the exact MPN diagnosis, reviewing marrow morphology, assessing thrombotic and bleeding risk, and deciding whether broader mutation testing adds prognostic value. In myelofibrosis, additional mutations and cytogenetics can meaningfully affect transplant discussions and risk scoring.
After a negative result in a patient with persistent unexplained thrombocytosis or marrow fibrosis, clinicians typically review JAK2 and MPL testing, assay sensitivity, secondary causes, and whether a broader myeloid panel is warranted.
A CALR test is therefore most useful as a piece of a diagnostic pattern. When the mutation, blood counts, marrow findings, and clinical features all point in the same direction, confidence in the diagnosis rises substantially.
Diagnostic certainty is different from disease risk
A CALR mutation can strongly support a clonal myeloproliferative neoplasm, but it does not by itself tell how aggressive that disease will be. Diagnosis and prognosis answer different questions. Diagnosis asks whether the blood-count and marrow abnormality represents an MPN rather than a reactive process. Prognosis asks about future risks such as thrombosis, bleeding, progression to myelofibrosis, transformation to acute leukemia, and overall survival. Those estimates require more than the driver mutation alone.
In essential thrombocythemia, CALR-mutated disease often has a different clinical pattern from JAK2-mutated disease. Patients may have very high platelet counts while having a lower thrombotic tendency on average than patients with JAK2 V617F. That average does not make an individual patient low risk. Age, prior thrombosis, cardiovascular factors, bleeding history, platelet level, and treatment context still matter. Extremely high platelet counts can also be associated with acquired von Willebrand dysfunction and bleeding, so the platelet number should not be interpreted as a simple measure of clot risk.
In primary myelofibrosis, CALR status is incorporated with clinical findings and other molecular abnormalities rather than used alone. Blood counts, circulating blasts, symptoms, spleen size, cytogenetics, and additional myeloid mutations can alter risk estimates substantially. This is why a report that says “CALR positive” is usually the beginning of risk assessment, not the end of it.
Type 1, type 2, and allele burden
Most pathogenic CALR alterations are exon 9 frameshift variants that create a new C-terminal protein sequence. They are often grouped as type 1 or type 1-like and type 2 or type 2-like variants. These groups can have different associations with MPN phenotype, particularly in myelofibrosis, but the exact prognostic effect depends on the disease category and the rest of the molecular profile. A laboratory may report the precise insertion or deletion, the predicted protein change, and sometimes a variant allele frequency.
Variant allele frequency estimates how much of the tested DNA carries the mutation. It can be influenced by the fraction of clonal blood cells, sample type, copy-number changes, and assay design. A higher value does not automatically mean a more advanced disease, and a lower value does not automatically mean an insignificant clone. Serial allele-burden measurements are not a universal substitute for routine blood counts, symptoms, marrow assessment, or validated response criteria.
A useful result review therefore separates three questions: Is the CALR alteration pathogenic? Does the overall clinical picture meet criteria for a specific MPN? What additional clinical, cytogenetic, or molecular features determine risk and management? Keeping those questions separate prevents overinterpreting a single molecular finding.
CALR is usually an acquired blood-cell mutation
Pathogenic CALR mutations in an MPN are generally somatic changes acquired in a hematopoietic stem or progenitor cell. They are not ordinarily inherited cancer-predisposition variants, so finding CALR in blood or marrow does not usually create a reason to test healthy relatives for the same mutation. Family history can still matter because familial clustering of MPN exists, but that is a separate question from the acquired CALR driver found in the patient’s clone.
When marrow findings and molecular results disagree
Discordance deserves review rather than forcing one result to fit the other. A CALR-positive blood test with atypical marrow morphology may reflect an early or unusual MPN, a small clonal population, or a separate hematologic process. A classic marrow pattern with negative driver testing may justify broader sequencing or repeat analysis if the original assay was limited. Expert hematopathology review can be especially helpful when the distinction between essential thrombocythemia, prefibrotic myelofibrosis, and reactive thrombocytosis would change prognosis or treatment.
References
- CALR-mutated myeloproliferative neoplasms 2025 (Review)
- Advances in Molecular Understanding of Polycythemia Vera, Essential Thrombocythemia, and Primary Myelofibrosis: Towards Precision Medicine 2024 (Review)
- Molecular diagnostic criteria of myeloproliferative neoplasms 2023 (Review)
- Genetic basis and molecular profiling in myeloproliferative neoplasms. 2022 (Review)
- Essential thrombocythemia: 2024 update on diagnosis, risk stratification, and management 2024 (Review)
- Myeloproliferative Neoplasms: Challenging Dogma. 2024 (Review)
Disclaimer
CALR mutation testing is one component of an MPN evaluation and should be interpreted with blood counts, bone marrow findings, and other molecular tests. A positive or negative result cannot by itself establish disease severity or determine treatment. This information is educational and should not replace assessment by a hematologist or hematopathologist.