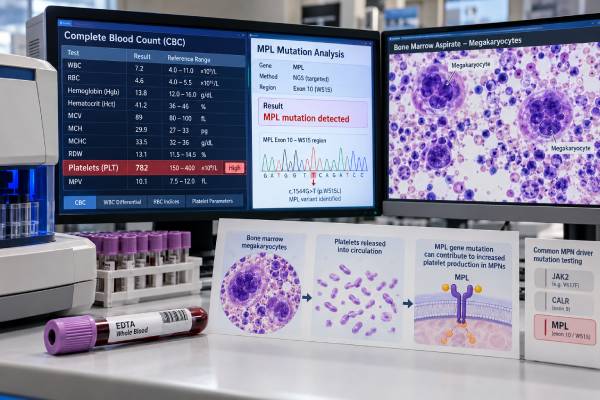
An MPL mutation test looks for acquired changes in the MPL gene, which encodes the thrombopoietin receptor that helps regulate platelet-producing megakaryocytes. Somatic MPL mutations are established driver abnormalities in Philadelphia chromosome–negative myeloproliferative neoplasms (MPNs), especially essential thrombocythemia (ET) and primary myelofibrosis (PMF). The test is most useful when a person has persistent unexplained thrombocytosis, marrow findings suspicious for an MPN, or a negative JAK2 and CALR workup that still leaves ET or PMF in the differential diagnosis.
A positive MPL result supports a clonal myeloid disorder, but it does not identify the exact MPN by itself. ET and PMF can share MPL mutations, so diagnosis still depends on blood counts, bone marrow morphology, exclusion of other myeloid neoplasms, and the clinical picture. The most familiar variants affect codon 515 in exon 10, including MPL W515L and W515K, although other activating variants occur. The report should be interpreted with the assay method, variant type, and variant allele frequency rather than as a simple positive/negative cancer test.
- What it measures: The test detects pathogenic or likely pathogenic variants in MPL, most often activating mutations affecting the thrombopoietin-receptor signaling pathway.
- What a positive result means: A pathogenic MPL mutation supports a clonal MPN, particularly ET or PMF, but marrow morphology is still needed to distinguish the disease type.
- What a negative result means: A negative MPL result does not exclude an MPN; many cases are driven by JAK2 or CALR, and some are “triple-negative.”
- When it is ordered: It is commonly used in persistent thrombocytosis or suspected myelofibrosis, often after or alongside JAK2 and CALR testing.
- Preparation: No fasting is usually required. Testing is generally performed on peripheral blood or bone marrow DNA.
Table of Contents
- What the MPL gene does
- When an MPL test is ordered
- What a positive MPL result means
- What a negative MPL result means
- MPL in essential thrombocythemia and myelofibrosis
- How MPL testing is performed and reported
- Limitations and next steps
What the MPL gene does
MPL encodes the receptor for thrombopoietin, a hormone that stimulates megakaryocytes and supports platelet production. When thrombopoietin binds MPL, intracellular signaling pathways—including JAK-STAT signaling—tell blood-forming cells to survive, proliferate, and mature in a controlled way.
An activating MPL mutation can make this pathway signal abnormally even without normal external control. That persistent signaling gives the mutated stem-cell clone a growth advantage and can contribute to the overproduction or abnormal behavior of megakaryocytes seen in ET and PMF.
The classic disease-associated MPL variants are found around codon 515, especially W515L and W515K. Other pathogenic variants, including less common exon 10 changes, are increasingly identified by next-generation sequencing. Not every MPL variant has the same clinical significance, so a report may classify a finding as pathogenic, likely pathogenic, a variant of uncertain significance, likely benign, or benign.
MPL is one of three major MPN driver genes. The others are JAK2 and CALR. These driver mutations are usually mutually exclusive in classic MPNs, although rare co-occurrence can be detected with sensitive sequencing methods.
A JAK2, CALR, and MPL MPN panel evaluates these major drivers together. When the clinical pattern strongly suggests polycythemia vera, a JAK2 V617F test is generally more informative because JAK2 abnormalities dominate in PV.
When an MPL test is ordered
The most common reason for MPL testing is persistent thrombocytosis that cannot be explained by a reactive cause. A platelet count of at least 450 × 10⁹/L is part of the diagnostic framework for ET, but the count alone does not distinguish ET from iron deficiency, inflammation, infection, recent surgery, malignancy, splenectomy, or other reactive conditions.
Testing may also be ordered when a patient has features suggestive of PMF, such as:
- unexplained anemia;
- leukoerythroblastosis on the blood smear;
- splenomegaly;
- constitutional symptoms such as night sweats or weight loss;
- elevated lactate dehydrogenase;
- marrow fibrosis or atypical megakaryocytes; or
- unexplained blood-count abnormalities in a pattern consistent with an MPN.
The usual molecular sequence varies by laboratory. Some centers start with JAK2 V617F and add CALR and MPL if JAK2 is negative. Others use a multiplex MPN panel from the start. If all three major drivers are negative but suspicion remains high, broader next-generation sequencing may look for other clonal myeloid mutations.
The purpose is not merely to “find a mutation.” Molecular testing helps establish clonality. This is especially useful when blood counts could reflect either a reactive process or an MPN.
A CALR mutation test is particularly relevant in JAK2-negative ET or PMF because CALR mutations are more common than MPL mutations in those settings.
What a positive MPL result means
A pathogenic MPL mutation strongly supports a clonal myeloproliferative neoplasm when the blood counts and marrow findings fit. It is not, however, specific for one disease. The same driver can occur in ET, prefibrotic PMF, and overt PMF.
This distinction matters because those diseases differ in natural history and management. A person with platelets of 800 × 10⁹/L and an MPL mutation cannot be diagnosed with ET from the mutation and platelet count alone. Bone marrow morphology must distinguish the mature enlarged megakaryocytes typical of ET from the atypical clustered megakaryocytes and granulocytic proliferation characteristic of prefibrotic PMF.
A positive report should be read for several details:
- exact variant: such as MPL W515L or W515K;
- classification: pathogenic or likely pathogenic versus uncertain;
- variant allele frequency (VAF): the proportion of sequence reads carrying the variant;
- specimen: blood or marrow; and
- method: targeted PCR, allele-specific testing, or NGS.
What variant allele frequency means
VAF estimates how much of the sampled DNA contains the variant. A VAF of 25% does not mean 25% of blood cells are cancer cells. Blood cells contain two gene copies, cell mixtures differ, and copy-number changes can alter the relationship between VAF and clone size.
VAF can still be useful context. A clear pathogenic variant at a convincing allele burden supports clonality. Very low-level findings require more caution because they may reflect a small clone, technical limits, or an early clonal state rather than established symptomatic MPN.
Does MPL positivity determine treatment?
Usually not by itself. Treatment decisions in ET depend mainly on thrombosis risk, age, prior clotting history, cardiovascular factors, symptoms, and overall disease features. In PMF, therapy and transplant decisions are driven by clinical risk models, symptoms, blood counts, cytogenetics, and additional mutations.
MPL status contributes to diagnosis and biological classification, but it is not a stand-alone instruction to start a specific drug.
What a negative MPL result means
A negative MPL result means the assay did not detect an MPL alteration within the regions and sensitivity it was designed to assess. It does not mean there is no myeloproliferative neoplasm.
Most classic MPNs with a driver mutation are caused by JAK2 or CALR rather than MPL. In ET, roughly four-fifths of patients have one of the three major drivers, with JAK2 most common, CALR second, and MPL representing a smaller minority. PMF shows a similar three-driver framework, though the proportions differ by cohort.
When JAK2, CALR, and MPL are all negative, the case is often called triple-negative. Triple-negative status is not a final diagnosis. The clinician must ask whether:
- marrow morphology truly supports ET or PMF;
- an alternative myeloid neoplasm is present;
- the abnormal blood count is reactive;
- the assay covered noncanonical driver variants; and
- broader sequencing identifies another clonal marker.
A negative result also depends on analytic sensitivity. A low-burden clone can fall below the test’s detection threshold, especially with older targeted methods. NGS may identify noncanonical MPL variants that an assay limited to W515L/K would miss.
MPL in essential thrombocythemia and myelofibrosis
MPL mutations are most strongly associated with ET and PMF, two related but distinct MPNs.
| Condition | Role of MPL testing | What else is required |
|---|---|---|
| Essential thrombocythemia | Supports a clonal MPN in a patient with persistent thrombocytosis | Bone marrow morphology and exclusion of PV, PMF, CML, and reactive thrombocytosis |
| Prefibrotic primary myelofibrosis | Provides a clonal driver marker | Characteristic megakaryocyte morphology, marrow cellularity pattern, clinical minor criteria |
| Overt primary myelofibrosis | Supports clonality and JAK-STAT pathway activation | Marrow fibrosis, megakaryocyte atypia, clinical and laboratory criteria |
| Polycythemia vera | Not a typical driver | JAK2 mutation testing, erythrocytosis assessment, marrow findings, erythropoietin |
| Reactive thrombocytosis | Usually absent | Evaluate iron deficiency, inflammation, infection, malignancy, surgery, and other causes |
MPL and essential thrombocythemia
ET is a clonal thrombocytosis defined by more than a high platelet count. Marrow shows increased numbers of enlarged mature megakaryocytes, and clinicians exclude other myeloid neoplasms. A driver mutation supports the diagnosis but does not replace morphology.
MPL-mutated ET may have somewhat different clinical characteristics from CALR-mutated or JAK2-mutated ET, but individual thrombosis management should not be reduced to the driver alone. Current risk assessment still emphasizes age, thrombosis history, and JAK2 status in established models.
MPL and primary myelofibrosis
PMF is characterized by abnormal megakaryocytic proliferation and can progress to marrow fibrosis, anemia, splenomegaly, constitutional symptoms, and extramedullary hematopoiesis. JAK2, CALR, or MPL mutations are expected in most patients, but none is mandatory if other evidence establishes a clonal myeloid process.
MPL positivity does not tell whether fibrosis is prefibrotic or overt. That distinction is made by marrow morphology and reticulin/collagen fibrosis grading.
A blood-cancer LDH test may be part of the clinical assessment because LDH can rise with increased cell turnover, but it is nonspecific.
How MPL testing is performed and reported
MPL testing usually uses DNA from peripheral blood leukocytes or bone marrow. No fasting or special diet is typically required. Blood is often sufficient for a chronic MPN workup because the clonal myeloid population circulates.
Laboratories may use:
- allele-specific PCR: highly sensitive for a small set of known variants;
- targeted PCR or probe-based assays: focused on common exon 10 hotspots; or
- next-generation sequencing: surveys a broader region and often tests many myeloid genes simultaneously.
NGS is useful when the common-driver screen is negative or when clinicians also need prognostic information from genes such as ASXL1, SRSF2, U2AF1, EZH2, IDH1/2, or others relevant to myeloid neoplasms.
A typical result may read “MPL p.W515L detected, VAF 18%, pathogenic.” The interpretation should then connect the finding to the clinical context: the mutation supports an MPN but cannot independently distinguish ET from PMF.
A “variant of uncertain significance” is different from a pathogenic driver. It means current evidence is insufficient to say whether the variant causes disease. Such a finding should not be treated as equivalent to W515L or another established activating mutation.
Limitations and next steps
The main limitation of an MPL test is that it answers only one part of the MPN diagnosis. Even a clearly pathogenic result cannot show marrow architecture, exclude BCR::ABL1-positive chronic myeloid leukemia, or prove that thrombocytosis is caused by ET rather than prefibrotic PMF.
After a positive or negative MPL result, common next steps include:
- reviewing serial complete blood counts rather than a single platelet value;
- checking iron studies and inflammatory causes of reactive thrombocytosis;
- examining the peripheral blood smear;
- completing JAK2 and CALR testing if not already done;
- performing BCR::ABL1 testing when CML is in the differential;
- obtaining a bone marrow biopsy when formal MPN classification is needed; and
- using broader cytogenetic or NGS testing when PMF or another myeloid neoplasm is suspected.
The most important practical distinction is clonal versus reactive. A pathogenic MPL mutation makes a clonal process much more likely, but the final disease label still comes from integrated hematopathology.
Ask your clinician: What exact MPL variant was detected? Was it pathogenic? What was the VAF? Are JAK2 and CALR known? Does my marrow favor ET, prefibrotic PMF, or overt PMF? Were iron deficiency and other reactive causes excluded? Those questions turn the molecular result into a clinically meaningful diagnosis.
Why thrombocytosis still needs a non-molecular workup
Even when MPL testing is ordered, the platelet count should be interpreted in context. Reactive thrombocytosis can be substantial and may persist for weeks or months when the underlying trigger continues. Iron deficiency is especially important because it can raise platelets and can coexist with an MPN. C-reactive protein or other inflammatory markers, ferritin and iron studies, recent surgery or infection, malignancy history, and spleen status can all help explain a high count.
A pathogenic MPL mutation makes a purely reactive explanation much less likely, but it does not erase coexisting conditions. Someone can have an MPN and iron deficiency at the same time. Correcting iron deficiency or inflammation may change the count without eliminating the underlying clonal disorder.
Why the distinction between ET and prefibrotic PMF matters
ET and prefibrotic PMF can both present with thrombocytosis and either can carry MPL. The distinction is made mainly from marrow morphology and accompanying clinical findings, not from the mutation itself. In ET, megakaryocytes are typically enlarged and mature appearing with relatively little granulocytic or erythroid disturbance. Prefibrotic PMF shows a different pattern of megakaryocyte atypia and marrow proliferation and may be accompanied by anemia, leukocytosis, splenomegaly, or elevated LDH.
The difference matters because the diseases have different expected courses and may be approached differently in long-term risk assessment. A report that says “MPL mutation detected” should therefore lead to the next diagnostic question—what MPN does the marrow support?—rather than being treated as synonymous with ET.
Somatic MPL mutations versus hereditary thrombocytosis
Most MPL testing in an MPN workup is designed to identify somatic mutations acquired by the blood-forming clone. Rare inherited MPL variants can cause familial or hereditary thrombocytosis, which is a different clinical problem. A variant found at an allele fraction near 50% can sometimes raise the question of a germline change, but VAF alone cannot prove inheritance.
Family history, age at onset, the exact variant, and testing of a non-blood tissue may be needed when hereditary thrombocytosis is suspected. This distinction matters because an inherited thrombopoietin-receptor variant should not automatically be interpreted as the same event as a classic somatic MPL W515 driver in ET or PMF.
Another limitation is that driver mutations can be detected in small clones before a person clearly meets criteria for an overt MPN. A low-level MPL finding is less common than age-related mutations such as TET2 or DNMT3A, but the same principle applies: molecular clonality must be matched with persistent blood-count abnormalities and marrow findings. If the phenotype is weak or atypical, follow-up counts and expert review may be more appropriate than assigning a disease label from the sequence result alone.
If symptoms or blood counts evolve over time, the diagnosis should be revisited. MPN classification can become clearer as marrow findings, splenomegaly, anemia, leukocytosis, or fibrosis emerge, and repeat molecular testing may be useful when the original assay was narrow or technically limited.
References
- Essential thrombocythemia: 2024 update on diagnosis, risk stratification, and management 2024 (Review)
- Advances in Molecular Understanding of Polycythemia Vera, Essential Thrombocythemia, and Primary Myelofibrosis: Towards Precision Medicine 2024 (Review)
- Molecular diagnostic criteria of myeloproliferative neoplasms 2023 (Review)
- Primary myelofibrosis: 2023 update on diagnosis, risk-stratification, and management 2023 (Review)
- International Consensus Classification of myeloid and lymphoid neoplasms: myeloproliferative neoplasms 2023 (Review)
- Genetic alterations in myeloproliferative and myelodysplastic/myeloproliferative neoplasms – a practical guide to WHO-HAEM5 2024 (Review)
Disclaimer
This article is for general education and does not diagnose a myeloproliferative neoplasm. MPL results must be interpreted with blood counts, marrow morphology, other molecular tests, and clinical findings by a qualified hematology team. Seek urgent care for symptoms of a serious clot or bleeding event, including sudden chest pain, shortness of breath, one-sided weakness, severe new headache, or uncontrolled bleeding.