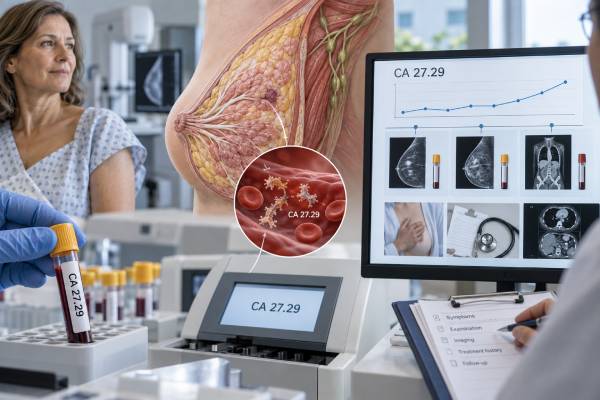
Cancer antigen 27.29, or CA 27.29, is a blood tumor marker that measures a circulating portion of MUC1, a protein commonly overexpressed and abnormally processed by breast cancer cells. The test is used mainly as an adjunct for monitoring selected people with known breast cancer, especially metastatic disease. It is not accurate enough to screen healthy people, diagnose a breast lump, or routinely look for distant recurrence in an otherwise asymptomatic person after curative treatment. Many laboratories use an upper reference limit close to 38 U/mL, but the exact cutoff is assay-specific. Benign liver disease, pregnancy, endometriosis, ovarian conditions, and other noncancer causes can raise CA 27.29, and other cancers can raise it as well. When the marker is useful, its value comes from a sustained trend compared with that patient’s baseline and interpreted with symptoms, examination, and imaging. A single elevated or rising CA 27.29 result should not by itself establish recurrence or trigger a treatment change.
- CA 27.29 measures a circulating MUC1-related antigen: it is closely related to, but not numerically interchangeable with, CA 15-3.
- A common upper reference limit is around 38 U/mL: always use the laboratory’s stated range.
- The test is mainly used to follow selected patients with advanced breast cancer: it may track disease burden and treatment response.
- CA 27.29 is not recommended as a general breast cancer screening test: early cancers can have normal values and benign disease can cause elevations.
- Routine marker-only surveillance after early breast cancer treatment is not standard: confirmed trends must be interpreted with clinical findings and imaging.
Table of Contents
- What CA 27.29 Measures
- Normal Range and High CA 27.29 Levels
- CA 27.29 in Breast Cancer
- Monitoring Treatment in Metastatic Breast Cancer
- Recurrence and Surveillance After Early Breast Cancer
- Benign Causes, Other Cancers, and Assay Limitations
- What to Do After a High or Rising CA 27.29
What CA 27.29 Measures
MUC1 is a large transmembrane glycoprotein found on the surface of many epithelial cells. In normal tissue it helps create a protective mucous barrier. In breast cancer and several other cancers, MUC1 can be overexpressed, lose its normal cell polarity, and acquire abnormal patterns of glycosylation. Portions of the protein are shed into the circulation.
CA 27.29 is an assay-defined antigen on circulating MUC1. It is not a separate cancer-specific molecule produced only by breast tumors. This explains why it can rise in other cancers and in some benign conditions.
CA 15-3 is closely related. Both tests detect MUC1-derived material but use different antibodies and assay designs. Older laboratory studies show that they measure overlapping rather than perfectly identical antigen populations. For practical monitoring, a patient should generally remain on one assay rather than switching back and forth between CA 27.29 and CA 15-3.
The amount of circulating antigen tends to increase with breast cancer burden. This makes the test more likely to be abnormal in metastatic disease than in a small localized tumor. It also makes serial measurement potentially useful when a known cancer has already demonstrated that it produces the marker.
The marker does not identify breast cancer subtype. It cannot tell whether a cancer is estrogen receptor-positive, progesterone receptor-positive, HER2-positive, or triple-negative. Those features are determined from tissue or validated molecular tests because they directly affect treatment.
The test also does not tell where metastatic disease is located. A high CA 27.29 may occur with bone, liver, lung, or other metastases, but imaging is required to define the sites and complications of disease.
Normal Range and High CA 27.29 Levels
A frequently used upper reference limit is about 38 U/mL, but some laboratories use slightly different thresholds. The result should always be compared with the reference range printed on the report.
There is no universal level that proves metastatic breast cancer. A borderline value just above the upper limit may reflect normal variation, benign disease, or analytical differences. Higher levels are more common with greater tumor burden, but substantial overlap exists.
Interpretation depends strongly on the testing context.
A person with no known cancer
An isolated elevated CA 27.29 is not a breast cancer diagnosis. It should not be used as a reason to bypass standard breast evaluation. If there is a breast lump, nipple change, or abnormal screening study, diagnostic mammography, ultrasound, and biopsy when appropriate are the decisive tests.
If there are no breast findings, the clinician may review liver disease, pregnancy status, gynecologic conditions, autoimmune or inflammatory disease, and whether another malignancy is already known. Mild unexpected elevations are often repeated before extensive investigation.
A breast cancer survivor without known metastatic disease
A new elevated result can be concerning, but the marker is not recommended as routine surveillance by itself in an otherwise asymptomatic patient. A confirmed sustained rise may justify clinical review and targeted imaging, especially if symptoms or examination findings are present.
A patient with metastatic breast cancer
Here CA 27.29 may be useful. A baseline value is established, and later results are compared during systemic treatment. The most meaningful pattern is a clear, repeated change that agrees with the broader disease course.
A value should not be interpreted only as “normal” or “abnormal.” In metastatic monitoring, moving from 220 to 90 U/mL can be clinically encouraging even though the result remains above the reference range. Conversely, a rise from 20 to 32 U/mL remains technically normal in many laboratories but may deserve attention if it is part of a reproducible trend in a patient whose marker historically tracked disease.
CA 27.29 in Breast Cancer
CA 27.29 was developed as a serum marker for MUC1-expressing breast cancer. It has been studied for detecting recurrence and monitoring advanced disease for decades. Its modern role is narrower than the phrase “breast cancer blood test” might suggest.
The test has limited sensitivity in early-stage disease. Many stage I and stage II breast cancers do not release enough antigen to move the blood concentration outside the reference range. This makes CA 27.29 unsuitable for breast cancer screening.
It is also not specific enough for diagnosis. A person with a high result may have no breast cancer, while a person with a biopsy-proven breast cancer may have a normal result. Mammography and other breast imaging detect structural abnormalities; pathology establishes whether cells are malignant. The serum marker cannot replace either step.
The marker becomes more useful after metastatic breast cancer is established. In that setting, physicians are not asking whether cancer exists. They are asking whether a known cancer appears to be increasing, stable, or responding to therapy. A serial blood marker can add a low-burden data point between imaging assessments.
CA 27.29 does not dictate which treatment to use. Modern metastatic breast cancer therapy depends on receptor status and molecular features such as HER2, ESR1, PIK3CA, BRCA1/2, PD-L1 in selected disease, and other actionable biomarkers. MUC1 serum antigen is mainly a monitoring signal.
CEA may also be elevated in some patients with metastatic breast cancer. Using the CEA blood test as an adjunct can be reasonable when it was clearly abnormal at baseline, but adding multiple markers indiscriminately does not guarantee better monitoring.
The most useful marker is the one that has already shown it tracks that individual’s disease. If CA 27.29 remained normal at diagnosis despite widespread metastases, it is unlikely to become a dependable response measure later.
Monitoring Treatment in Metastatic Breast Cancer
Systemic treatment for metastatic breast cancer may include endocrine therapy, CDK4/6 inhibitors, chemotherapy, HER2-targeted therapies, antibody-drug conjugates, PARP inhibitors, immunotherapy in selected settings, or other targeted agents. Response is evaluated using symptoms, examination, laboratory tests, and imaging. CA 27.29 can supplement this process when the tumor produces it.
When the value falls
A sustained decrease can support evidence that treatment is controlling disease. The interpretation is strongest when symptoms improve and imaging shows stable or shrinking lesions. The marker does not have to return to the normal range to indicate benefit.
When the value remains stable
A relatively stable CA 27.29 can be consistent with stable disease, particularly in someone whose marker previously changed with tumor burden. However, some metastatic sites may progress without much marker movement, so stability is not a substitute for scheduled imaging.
When the value rises
A repeated upward trend can indicate progression. The oncology team may review adherence, symptoms, liver tests, recent imaging, and the timing of the next scan. A large sustained increase generally carries more weight than a small one-time fluctuation.
Treatment should not usually be changed solely because of one marker result. Tumor markers can transiently rise after a new therapy, and noncancer conditions can alter the concentration. Historical breast cancer marker guidance has specifically cautioned against acting on serum markers without supporting clinical evidence.
The same-laboratory principle is important. Commercial MUC1 assays are not perfectly harmonized. If a patient moves between health systems, a new baseline may be needed before small percentage changes are interpreted as biological.
The marker may be especially helpful when some disease sites are difficult to measure radiographically, such as diffuse bone metastases. Even then, pain, alkaline phosphatase, imaging, and other clinical factors remain necessary because bone response can be complex.
Recurrence and Surveillance After Early Breast Cancer
CA 27.29 can sometimes become elevated months before distant breast cancer recurrence is diagnosed clinically. That lead time is the reason the test has attracted interest for surveillance. However, detecting recurrence earlier is only valuable if the earlier detection improves meaningful outcomes and does not cause excessive harm from false positives.
Current breast cancer follow-up guidelines emphasize history, physical examination, and mammographic surveillance after primary treatment. The 2026 ASCO guideline update addresses blood-based biomarkers but continues to place routine survivorship follow-up around evidence-based clinical assessment rather than automatic serum tumor-marker testing in all asymptomatic survivors.
This approach reflects several limitations. Not all recurrences elevate CA 27.29. Benign conditions can cause false alarms. A rising marker may lead to repeated CT, PET, or bone imaging that finds incidental abnormalities. Most importantly, evidence has not shown that initiating treatment solely because of an earlier asymptomatic marker rise improves survival enough to justify routine use.
A survivor who develops symptoms should be evaluated regardless of the marker. Persistent focal bone pain, unexplained cough or shortness of breath, neurologic symptoms, abdominal swelling, jaundice, unexplained weight loss, or a new breast/chest-wall finding can justify diagnostic imaging and laboratory evaluation.
Risk of recurrence is not the same for every patient. Stage, tumor biology, nodal status, response to neoadjuvant therapy, genomic features, and time from diagnosis all matter. High-risk patients may receive more individualized follow-up, but that does not automatically make CA 27.29 a validated routine surveillance test.
Emerging technologies such as circulating tumor DNA can detect molecular residual disease earlier in some studies, but the same principle applies: a biomarker becomes a standard surveillance tool only when evidence shows that using it to guide care improves patient outcomes.
Benign Causes, Other Cancers, and Assay Limitations
CA 27.29 is not breast-specific. MUC1-related antigen can rise in other epithelial cancers, including ovarian, lung, pancreatic, colon, liver, and other malignancies. Therefore, the result cannot determine the primary site of an unknown cancer.
Benign elevations have been reported with liver disease, benign breast conditions, pregnancy, endometriosis, ovarian cysts, and some inflammatory or autoimmune disorders. The list varies among laboratory references because not every association is equally strong.
Liver function deserves particular attention because circulating glycoproteins are metabolized and cleared partly through the liver. Chronic hepatitis or cirrhosis can complicate interpretation, and metastatic breast cancer itself may involve the liver.
Pregnancy alters many epithelial and hormonal proteins and can increase MUC1-related markers. Tumor-marker testing in pregnancy should be ordered only for a clear indication and interpreted by specialists familiar with physiologic changes.
Analytical interference is uncommon but possible. Heterophile antibodies can disrupt immunoassays and produce a result that does not fit the rest of the clinical picture. When an unexplained persistent elevation would lead to invasive testing or treatment, repeating the assay or using an alternative method can be appropriate.
CA 27.29 and CA 15-3 should not be compared as though they share the same normal range. One result of 38 U/mL on CA 27.29 and 30 U/mL on CA 15-3 does not mean the markers are “equal.” They are different MUC1 assay systems.
Another limitation is biologic heterogeneity. Metastatic breast cancer can evolve under treatment. A tumor that secreted large amounts of MUC1 at one point may later behave differently, and different metastatic clones can have different expression patterns. This is one reason imaging and tissue or liquid-biopsy molecular testing remain important when disease changes.
What to Do After a High or Rising CA 27.29
If CA 27.29 was ordered without a known cancer diagnosis and comes back mildly high, start with confirmation and clinical context rather than assuming cancer. Review the laboratory range, pregnancy possibility, liver function, benign gynecologic or breast conditions, and whether normal breast screening is up to date.
A breast symptom or imaging abnormality should be evaluated through the standard breast diagnostic pathway, not through repeated tumor-marker testing. A biopsy, when indicated, provides the diagnosis.
For a person previously treated for early breast cancer, discuss a confirmed rise with the oncology team. The clinician will determine whether the size and persistence of the change, recurrence risk, symptoms, physical examination, and other laboratory findings justify imaging. One borderline value alone generally provides weak evidence.
For a patient with metastatic disease, compare the new number with prior values obtained on the same assay. A sustained rise that matches increasing symptoms or radiographic disease can support progression and help frame a treatment discussion. A discordant rise should be repeated and investigated before therapy is changed.
Do not use CA 27.29 to self-adjust endocrine therapy, chemotherapy, targeted treatment, or scan timing. The marker is an adjunct to oncology care, not a stand-alone treatment command.
Seek urgent medical attention for new weakness or numbness, loss of bladder or bowel control, severe shortness of breath, confusion, jaundice with fever, severe unremitting pain, or other rapidly worsening symptoms. These may signal complications requiring immediate care regardless of the tumor-marker result.
The best interpretation of CA 27.29 asks whether the patient has a known MUC1-producing breast cancer, whether the assay is consistent over time, whether the change is sustained, and whether clinical evidence points in the same direction. Used that way, the marker can add useful monitoring information without creating false certainty.
References
- Breast Cancer Follow-Up and Surveillance After Primary Treatment: ASCO Guideline Update 2026 (Practice Guideline)
- Mucin-1: a promising pan-cancer therapeutic target 2025 (Review)
- Salivary Transmembrane Mucins of the MUC1 Family (CA 15-3, CA 27.29, MCA) in Breast Cancer: The Effect of Human Epidermal Growth Factor Receptor 2 (HER2) 2024
- Early breast cancer: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up 2024 (Practice Guideline)
- Factors influencing blood tumor marker concentrations in the absence of neoplasia 2024 (Review)
- MUC1 gene-derived glycoprotein assays for monitoring breast cancer (CA 15-3, CA 27.29, BR): are they measuring the same antigen? 2004 (Laboratory Study)
Disclaimer
CA 27.29 cannot diagnose, screen for, or exclude breast cancer by itself. It is most useful as an adjunct for selected patients with known advanced disease, and benign conditions or other cancers can also raise the result. A high or rising value should be interpreted by a qualified clinician with symptoms, examination, imaging, treatment timing, and prior results from the same assay.