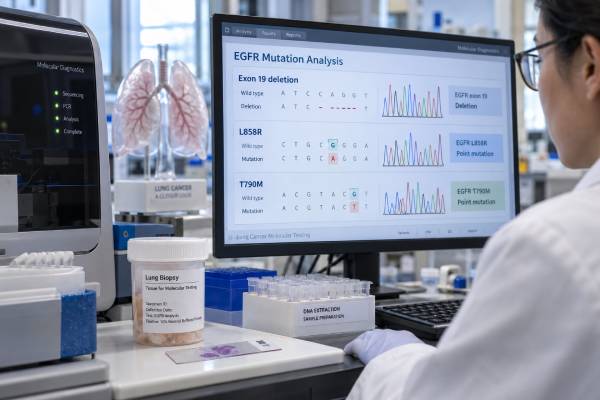
An EGFR mutation test looks for changes in the epidermal growth factor receptor gene that can guide treatment in non-small cell lung cancer (NSCLC), especially lung adenocarcinoma. The most common sensitizing EGFR alterations are exon 19 deletions and the exon 21 L858R substitution. These findings can identify tumors that are likely to benefit from EGFR tyrosine kinase inhibitors. Other EGFR variants, including exon 20 insertions and uncommon mutations such as G719X, L861Q, and S768I, have different treatment implications. T790M is best known as an acquired resistance mutation after first- or second-generation EGFR inhibitors, although it can rarely be present before treatment or in the germline. Modern testing may use tumor tissue, cytology specimens, or circulating tumor DNA from blood. A negative liquid-biopsy result does not always rule out an EGFR mutation because some tumors shed little DNA. The exact variant—not merely “EGFR positive”—is essential for interpretation.
- Exon 19 deletions and L858R are classic sensitizing EGFR mutations and are major predictors of response to EGFR-targeted therapy in NSCLC.
- T790M is primarily a resistance mutation associated with earlier-generation EGFR inhibitors; its importance depends on treatment history and timing.
- Exon 20 insertions are different from exon 19 deletions: they usually have lower sensitivity to traditional EGFR TKIs and require variant-specific treatment planning.
- A negative blood liquid biopsy can be falsely negative: tissue testing may still be needed when clinical suspicion remains high.
- No fasting is usually required: the main issue is obtaining enough high-quality tumor DNA or circulating tumor DNA for the assay.
Table of Contents
- What EGFR testing measures
- Which EGFR mutations matter
- When testing is ordered
- Tissue versus liquid biopsy
- How to interpret results
- T790M and acquired resistance
- Treatment and next steps
What EGFR testing measures
EGFR encodes a receptor tyrosine kinase that sits on the cell surface and sends growth signals when activated. Certain mutations keep the receptor active even without normal signaling, creating an oncogenic driver that the tumor depends on.
Clinically relevant mutations cluster mainly in exons 18 through 21, which encode the tyrosine kinase domain. Testing may use PCR, next-generation sequencing, or another validated molecular method. Broad NGS is increasingly favored because it can identify common and uncommon EGFR variants while also testing other actionable lung-cancer genes.
The test should identify the exact variant. “EGFR mutation detected” is incomplete because exon 19 deletion, L858R, exon 20 insertion, T790M, and C797S have different meanings.
EGFR testing is often part of a broader lung molecular panel that also evaluates ALK, ROS1, BRAF, MET, RET, KRAS, ERBB2, NTRK, and other targets. Related testing may include an ALK fusion test, ROS1 fusion testing, or RET fusion testing.
Which EGFR mutations matter
Exon 19 deletions and L858R in exon 21 account for the large majority of common sensitizing EGFR mutations. They are strongly associated with response to EGFR TKIs and are treated as major actionable drivers.
Exon 20 insertions are a separate group. Their structure often prevents effective inhibition by traditional first- and second-generation EGFR TKIs. Newer drugs and antibody-based approaches have improved treatment options, but management is not the same as for exon 19 deletion or L858R.
Uncommon sensitizing mutations include G719X, L861Q, and S768I. Their sensitivity varies by drug and by whether multiple EGFR mutations occur together.
T790M changes the kinase domain at threonine 790. It increases affinity for ATP and reduces the effectiveness of earlier-generation TKIs. Osimertinib was specifically developed to inhibit sensitizing EGFR mutations plus T790M and later became a major therapy across multiple disease settings.
C797S can emerge after third-generation EGFR inhibition and can reduce osimertinib binding. Resistance is often more complex than one mutation and may include MET amplification, HER2 alterations, histologic transformation, or other bypass mechanisms.
When testing is ordered
Molecular testing is standard for patients with advanced nonsquamous NSCLC and is also relevant in selected earlier-stage disease because EGFR status can affect adjuvant treatment decisions. Testing should not be restricted by smoking history, sex, or ethnicity when clinical guidelines recommend molecular profiling.
Testing may be performed:
- at initial diagnosis of advanced NSCLC;
- after surgery in settings where adjuvant targeted therapy is being considered;
- at progression on EGFR-targeted therapy to look for resistance mechanisms; or
- when a prior small panel was incomplete and broader profiling could reveal a target.
A pathologist should preserve enough tissue for molecular testing because small lung biopsies may also be needed for histology and PD-L1 assessment.
Tissue versus liquid biopsy
Tissue testing remains highly informative because it confirms tumor histology and provides DNA directly from cancer cells. Formalin-fixed biopsy or surgical material is commonly used.
Liquid biopsy analyzes circulating tumor DNA in plasma. It can return results quickly, avoid another invasive procedure, and capture DNA from several metastatic sites. It is especially useful when tissue is insufficient or difficult to obtain.
Its main limitation is sensitivity. A tumor may shed very little DNA into blood, particularly when disease burden is low or confined to certain sites. Therefore, a negative plasma result does not reliably exclude an actionable mutation. If blood is negative and a targetable driver is still clinically plausible, tissue testing should be considered when feasible.
A related EGFR T790M liquid biopsy focuses specifically on resistance testing in circulating tumor DNA.
How to interpret results
| Result | General meaning | Key caution |
|---|---|---|
| Exon 19 deletion | Classic sensitizing EGFR driver | Exact disease setting still determines therapy |
| L858R | Classic sensitizing EGFR driver | Co-mutations may influence outcomes |
| Exon 20 insertion | Actionable but biologically distinct EGFR subgroup | Do not assume sensitivity to standard EGFR TKIs |
| T790M after earlier EGFR TKI | Supports acquired on-target resistance | Current treatment history matters |
| C797S after osimertinib | Potential third-generation TKI resistance mechanism | Allelic context and co-resistance mechanisms can matter |
| No EGFR mutation detected | No reportable EGFR alteration found by that assay | Does not exclude other drivers or a false-negative liquid biopsy |
Variant allele frequency is not a tumor stage or a direct percentage of cancer cells. It is affected by tumor purity, copy number, blood DNA contribution, and assay design.
A rare finding should be interpreted using variant-specific evidence. Not every EGFR sequence change is oncogenic or treatment-sensitive.
T790M and acquired resistance
T790M became a landmark resistance biomarker because it was frequently detected after progression on first-generation agents such as gefitinib or erlotinib and second-generation inhibitors such as afatinib. It changes the kinase pocket so those drugs bind less effectively.
Today, the clinical role of T790M testing depends on the treatment era and sequence. Osimertinib is commonly used earlier in therapy, so T790M is less often the dominant resistance mechanism after first-line treatment than it was when older TKIs were standard.
A T790M finding before any cancer treatment deserves special attention. Most such findings are somatic, but rare germline T790M variants have been associated with inherited lung-cancer susceptibility. If the allele fraction, personal history, or family history raises concern, germline evaluation may be appropriate.
At progression on osimertinib, repeat NGS may reveal C797S, MET amplification, HER2 changes, BRAF or KRAS pathway alterations, fusions, or transformation to small-cell lung cancer. Tissue biopsy can be particularly valuable when transformation is suspected because DNA testing alone cannot fully classify histologic change.
Treatment and next steps
For classic exon 19 deletion or L858R NSCLC, EGFR-targeted therapy is a core treatment approach. The exact regimen depends on stage, prior treatment, brain metastases, comorbidities, and current clinical guidelines.
For uncommon EGFR mutations, treatment should be matched to the specific variant rather than generalized from the common mutations. Exon 20 insertions have dedicated therapeutic strategies and should be reported precisely.
At progression, the next step is often to identify why the cancer escaped therapy. Repeat tissue or plasma profiling can guide clinical trials, targeted combinations, or a switch to systemic therapy with a different mechanism.
Patients should not change treatment based solely on a molecular report without oncology review. A mutation can be actionable yet not appropriate for a particular stage or treatment line.
EGFR testing matters in both early and advanced disease
EGFR testing is most strongly associated with metastatic non-small cell lung cancer, where the result can determine first-line targeted therapy. It can also matter in resected, earlier-stage EGFR-mutated lung cancer because adjuvant targeted treatment may be considered for eligible patients after surgery. The clinical meaning of the same mutation therefore depends on stage, surgery, prior therapy, and the treatment setting. A report should always be interpreted with those details.
EGFR mutations are more frequent in lung adenocarcinoma, never-smokers, women, and people with East Asian ancestry, but those associations should not be used to deny testing to an otherwise eligible patient. People outside those demographic groups can have actionable EGFR mutations. Testing decisions should follow tumor type and current clinical guidelines rather than stereotypes about who “looks like” an EGFR-positive patient.
Exon 19 deletion and L858R are common sensitizing mutations, but not identical
Exon 19 deletions and the exon 21 L858R substitution account for most classic sensitizing EGFR mutations. Both can predict benefit from EGFR tyrosine kinase inhibitors, but they are not biologically identical. Outcomes can differ among mutation subtypes, treatment regimens, and clinical settings. Co-mutations such as TP53 alterations may also influence prognosis without necessarily eliminating the predictive value of EGFR.
The report should name the exact variant rather than simply saying “EGFR positive.” This is particularly important for uncommon mutations, compound mutations, and exon 20 insertions. Some uncommon EGFR alterations are sensitive to selected inhibitors, while others have less certain or different drug sensitivity. Exon 20 insertions are a distinct group and should not be managed as if they were ordinary exon 19 deletions.
Testing method can change what is found
Modern next-generation sequencing panels can examine EGFR alongside other lung-cancer genes and can detect many uncommon variants. Targeted PCR assays can be rapid and sensitive for predefined hotspots, but a narrow assay may miss variants outside its design. The choice of method matters most when the clinical question extends beyond the common exon 19, L858R, and T790M alterations.
A negative result is only as complete as the assay. The report should be checked for which exons and variant classes were covered, the limit of detection, and whether the specimen had enough tumor. A “wild-type” call from an adequate broad assay is more informative than a negative result from a small specimen tested with a limited hotspot method.
Plasma and tissue answer overlapping but different questions
Circulating tumor DNA can provide a rapid, minimally invasive way to detect an EGFR mutation, particularly when tissue is unavailable or repeat biopsy would be difficult. A positive plasma result for a well-established actionable mutation is often highly informative because the DNA detected is tumor derived. The major limitation is sensitivity: some tumors shed little DNA into the bloodstream, especially when disease burden is low or disease is confined to certain sites.
For that reason, a negative plasma test does not exclude an EGFR mutation. If the result is negative or uninformative and tissue can be obtained safely, tissue testing is often appropriate. At progression, plasma can sample DNA released from multiple disease sites, while a tissue biopsy can provide histology and detect transformations that a blood test cannot show. The two specimen types are therefore complementary.
Resistance after osimertinib is more complex than T790M
T790M became a classic resistance biomarker because it commonly emerged after first- or second-generation EGFR inhibitors and predicted sensitivity to third-generation osimertinib. In patients receiving osimertinib as initial therapy, however, resistance is more diverse. Mechanisms can include additional EGFR alterations, MET amplification, other bypass signaling changes, and histologic transformation such as small-cell transformation.
This matters because a progression biopsy is not merely a repeat of the original test. The goal is to identify the current resistance mechanism. A broad tissue or plasma panel may be more useful than a test restricted to T790M. If transformation is suspected, tissue is particularly valuable because morphology cannot be determined from ctDNA alone.
Central nervous system disease also deserves separate attention. EGFR-mutated lung cancer has a clinically important risk of brain metastases, and treatment selection can be influenced by a drug’s activity in the central nervous system. Molecular status is one factor in that decision, but brain imaging, symptoms, prior radiation, and extent of systemic disease remain essential.
What “EGFR negative” should trigger next
In an eligible nonsquamous NSCLC, an EGFR-negative result should generally lead to review of the broader molecular profile rather than the conclusion that targeted therapy is impossible. Other oncogenic drivers can include ALK, ROS1, RET, MET, BRAF, KRAS, ERBB2, and NTRK alterations, depending on the tumor and testing panel. Broad profiling reduces the chance that sequential single-gene testing will consume a small biopsy before all important biomarkers are assessed.
If the sample was inadequate, low in tumor cells, or tested by a narrow assay, repeating molecular testing on a better specimen may be more useful than accepting an uncertain negative. The pathology report and molecular quality-control section should explain whether the result is technically reliable.
EGFR and immunotherapy are separate biomarker questions
PD-L1 expression and EGFR mutation status provide different information. A tumor can have high PD-L1 expression and still be driven by an actionable EGFR mutation. In advanced EGFR-mutated NSCLC, targeted therapy strategy is generally considered before treating the cancer as though PD-L1 alone defines the best first-line approach. This is another reason to complete molecular testing before committing to a treatment plan when the clinical situation allows.
Treatment sequencing also requires attention to toxicity. Certain combinations or close sequencing of targeted therapy and immune checkpoint inhibitors can have clinically important adverse effects. The oncology team should integrate the full biomarker profile, prior therapies, disease urgency, and current guidelines rather than selecting treatment from a single line of the report.
Variant allele frequency is not a direct measure of response
A sequencing report may list the percentage of reads carrying an EGFR mutation. That variant allele frequency is influenced by tumor purity, copy-number changes, the amount of normal tissue in the specimen, and the fraction of circulating tumor DNA in plasma. It should not be interpreted as a simple percentage of cancer cells or as a stand-alone predictor of how much a tumor will shrink.
In serial plasma testing, falling or rising ctDNA can provide biologic information in selected settings, but routine treatment decisions still rely on imaging, symptoms, clinical examination, and validated response criteria. A single allele-frequency change should not prompt a medication change without oncology interpretation.
References
- EGFR mutations in non-small cell lung cancer: Classification, characteristics and resistance to third-generation EGFR-tyrosine kinase inhibitors (Review) 2025 (Review)
- Updates on the treatment of epidermal growth factor receptor-mutant non-small cell lung cancer. 2025 (Review)
- Personalized care for patients with EGFR-mutant nonsmall cell lung cancer: Navigating early to advanced disease management 2025 (Review)
- EGFR exon20 insertion mutations in non-small cell lung cancer: Clinical implications and recent advances in targeted therapies 2023 (Review)
- Recommendations for reporting tissue and circulating tumour (ct)DNA next-generation sequencing results in non-small cell lung cancer 2024 (Guideline)
- Molecular Testing Guideline for the Selection of Patients With Lung Cancer for Treatment With Targeted Tyrosine Kinase Inhibitors: American Society of Clinical Oncology Endorsement of the College of American Pathologists/International Association for the Study of Lung Cancer/Association for Molecular Pathology Clinical Practice Guideline Update 2018 (Guideline)
Disclaimer
EGFR mutation results should be interpreted by an oncology team together with tumor type, stage, prior therapy, sample source, and other biomarkers. A negative plasma test may require tissue testing, and uncommon variants need variant-specific interpretation. This article is educational and does not replace individualized lung-cancer treatment advice.