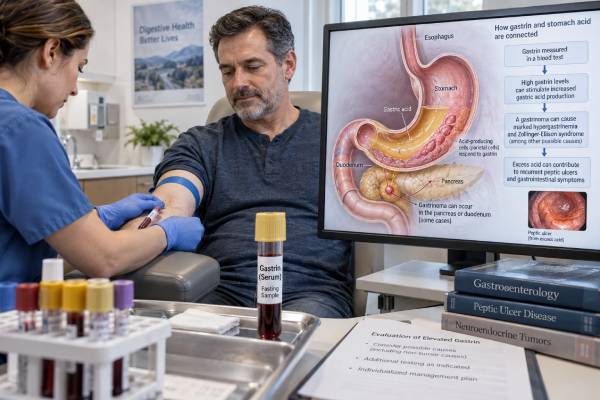
A gastrin blood test measures gastrin, a hormone that signals the stomach to make acid. It is most often ordered when a clinician suspects unusually high acid production, especially Zollinger-Ellison syndrome (ZES), which is caused by a gastrin-secreting neuroendocrine tumor called a gastrinoma. A high gastrin result does not automatically mean a tumor. Proton pump inhibitors (PPIs), low stomach acid from autoimmune or atrophic gastritis, Helicobacter pylori–related changes, kidney dysfunction, and several other conditions can also raise gastrin. The key diagnostic question is whether the gastrin level is appropriate for the amount of stomach acid present. In classic ZES, gastrin is elevated even though the stomach remains strongly acidic. Because acid-suppressing medicines can both raise gastrin and protect people with ZES from serious ulcer complications, medication changes for testing must be planned by a specialist rather than done on your own.
- Gastrin stimulates stomach acid production; the test measures how much gastrin is circulating in blood.
- High gastrin is common with PPIs and low-acid states, so an elevated result alone does not diagnose gastrinoma.
- A fasting gastrin more than 10 times the assay’s upper limit together with gastric pH ≤2 strongly supports Zollinger-Ellison syndrome.
- If gastrin is elevated less than 10-fold while gastric pH is ≤2, a secretin stimulation test or other specialized evaluation may be needed.
- Do not stop a PPI for gastrin testing unless the clinician managing the evaluation gives a safe, specific plan.
Table of Contents
- What the Gastrin Blood Test Measures
- Why a Gastrin Test Is Ordered
- Causes of High Gastrin Levels
- Gastrinoma and Zollinger-Ellison Syndrome
- How Gastrin Results Are Interpreted
- Fasting, PPIs, and Test Preparation
- What Happens After a High Gastrin Result
What the Gastrin Blood Test Measures
Gastrin is a digestive hormone made mainly by G cells in the lower part of the stomach. After food enters the stomach, gastrin helps coordinate digestion by stimulating acid secretion and supporting growth and function of the stomach lining. When the stomach becomes acidic enough, normal feedback mechanisms suppress further gastrin release.
That feedback loop explains most gastrin test results. When stomach acid is low, gastrin normally rises in an effort to stimulate more acid. When stomach acid is already high, gastrin should usually be suppressed. Therefore, high gastrin can mean two very different things:
- an appropriate response to reduced or absent stomach acid, or
- inappropriate gastrin secretion despite an already acidic stomach.
The second pattern raises concern for a gastrinoma and ZES.
Most laboratories report fasting serum gastrin in pg/mL or an equivalent unit. Reference intervals vary by laboratory and assay. Many assays have an upper reference limit around 100 pg/mL, but that number should not be treated as universal. The correct comparison is the upper limit printed on the specific laboratory report.
Gastrin circulates in several molecular forms, and different laboratory assays do not measure all forms identically. This can produce meaningful differences between methods. If a result is inconsistent with the clinical picture, clinicians may repeat the test with a reliable assay or involve a center experienced in ZES diagnosis.
Meals naturally raise gastrin, particularly protein-containing foods, which is why a fasting specimen is preferred for diagnostic work. The timing also helps separate a baseline abnormality from a normal post-meal response. A nonfasting result that is only mildly elevated may need to be repeated correctly before anyone draws conclusions about disease.
A gastrin test is different from more general neuroendocrine tumor markers. For example, chromogranin A can also rise with neuroendocrine tumors and with PPI use, but it does not establish that a tumor is secreting gastrin. Gastrin testing is specifically tied to the physiology of gastric acid and gastrinoma.
Why a Gastrin Test Is Ordered
Clinicians usually order fasting gastrin when symptoms or findings suggest excessive gastric acid secretion or when they need to investigate unexplained hypergastrinemia.
ZES may be considered in people with:
- recurrent, severe, or difficult-to-treat peptic ulcers;
- ulcers in unusual locations or multiple ulcers;
- severe gastroesophageal reflux that is unusually resistant to standard treatment;
- chronic watery diarrhea, especially when it improves with acid suppression;
- prominent thickening of stomach folds on endoscopy;
- ulcer complications despite treatment;
- a known pancreatic or duodenal neuroendocrine tumor; or
- a personal or family history suggesting multiple endocrine neoplasia type 1 (MEN1).
Diarrhea is an important clue because extreme acid delivery into the small intestine interferes with digestive enzymes and nutrient handling. Some people with gastrinoma present mainly with diarrhea rather than classic ulcer pain.
A clinician may also measure gastrin when investigating very low stomach acid. Autoimmune atrophic gastritis, including the stomach changes associated with pernicious anemia, can markedly raise gastrin because acid-producing parietal cells are damaged. In that setting, high gastrin is a feedback response to low acid rather than evidence of ZES.
The test is not designed as a general cancer screen. Gastrinoma is uncommon, while medication-related and benign causes of high gastrin are much more frequent. Testing works best when there is a specific clinical reason and the result can be interpreted together with medication history, gastric acidity, endoscopy findings, and other laboratory data.
Causes of High Gastrin Levels
The most common explanation for high gastrin is not necessarily a gastrinoma. A useful first step is to divide causes into low-acid states and high-acid states.
High gastrin because stomach acid is low
If acid production falls, the body removes a normal brake on gastrin secretion. Gastrin then rises appropriately.
Common causes include:
- Proton pump inhibitors. Omeprazole, esomeprazole, pantoprazole, lansoprazole, rabeprazole, and related medicines strongly reduce acid and commonly increase gastrin.
- H2-receptor blockers. Medicines that reduce acid through histamine H2 receptors can also increase gastrin, usually less dramatically than PPIs.
- Autoimmune or chronic atrophic gastritis. Loss of acid-producing parietal cells can cause profound hypochlorhydria or achlorhydria and substantial hypergastrinemia.
- Pernicious anemia. Autoimmune destruction of parietal cells can impair vitamin B12 absorption and reduce acid secretion, leading to high gastrin.
- Some Helicobacter pylori patterns. H. pylori infection can alter gastrin regulation and acid physiology, although the direction and magnitude depend on the pattern of gastritis.
In these situations, a high gastrin level can be physiologically appropriate because the stomach is not very acidic.
High gastrin despite high stomach acid
This is the pattern that raises greater concern for ZES. A gastrinoma releases gastrin autonomously, driving the stomach to produce excess acid even though normal feedback should have suppressed gastrin.
Other less common hypergastrinemic, acid-producing states can complicate the differential diagnosis. Previous stomach surgery that leaves a retained antrum, antral G-cell hyperfunction, and certain anatomical disorders may be considered based on history.
Other factors
Reduced renal clearance can contribute to increased gastrin in kidney dysfunction. Prior vagotomy, gastric outlet obstruction, and major small-bowel surgery are other recognized causes or confounders in selected patients.
This is why “gastrin = high” is not enough. The combination of gastrin concentration, gastric pH, medication exposure, clinical history, and assay quality is far more informative than the blood value by itself.
Gastrinoma and Zollinger-Ellison Syndrome
A gastrinoma is a gastrin-secreting neuroendocrine tumor, usually arising in the duodenum or pancreas. The resulting condition—high gastrin plus excessive gastric acid secretion—is called Zollinger-Ellison syndrome.
The excess acid can cause recurrent peptic ulcers, reflux disease, abdominal pain, bleeding, strictures, and chronic diarrhea. Potent acid-suppressing therapy has greatly reduced acid-related complications, but that treatment also makes biochemical diagnosis more difficult because PPIs themselves raise gastrin.
Gastrinomas can occur sporadically or as part of MEN1, an inherited tumor syndrome involving endocrine organs. In MEN1, a person may have multiple duodenal gastrinomas as well as parathyroid and pituitary disease. Calcium and parathyroid hormone testing are often relevant when MEN1 is suspected.
A gastrinoma is a type of functional neuroendocrine tumor because it produces a hormone that causes a recognizable syndrome. Other hormone-producing pancreatic neuroendocrine tumors include insulinomas, glucagonomas, VIPomas, and somatostatinomas. A pancreatic polypeptide test may be encountered in broader neuroendocrine evaluations, but it is not a substitute for gastrin testing in suspected ZES.
Biochemical confirmation should generally come before aggressive tumor localization because an incidental neuroendocrine-appearing lesion plus an elevated gastrin on PPI therapy does not necessarily prove gastrinoma. Conversely, very small duodenal gastrinomas can be difficult to see on conventional imaging.
Once ZES is biochemically established or strongly suspected, localization may involve contrast-enhanced CT or MRI, endoscopic ultrasound, and somatostatin-receptor imaging such as gallium-68 DOTATATE PET/CT. The exact sequence depends on availability, whether MEN1 is present, and whether the goal is surgery, staging, or treatment planning.
How Gastrin Results Are Interpreted
The safest way to interpret gastrin is to ask two questions: How high is it relative to the assay’s upper limit, and is the stomach acidic at the same time?
Mild or moderate elevation
A modest increase is common and nonspecific. PPIs, atrophic gastritis, H. pylori–related disease, kidney dysfunction, and other causes can all produce results that overlap with ZES. In fact, many patients with confirmed gastrinoma have fasting gastrin levels less than 10 times the upper limit, so the amount of elevation alone may not settle the diagnosis.
More than 10 times the upper limit with gastric pH 2 or lower
The classic biochemical pattern that strongly establishes ZES is fasting serum gastrin greater than 10 times the upper limit of normal together with gastric pH ≤2, after other rare mimics are considered. If an assay has an upper limit near 100 pg/mL, this is often described as gastrin above about 1,000 pg/mL, but using the assay-specific multiple is more accurate.
Gastric pH is crucial. A gastrin of 1,200 pg/mL with an acidic stomach has a very different meaning from 1,200 pg/mL in a person with achlorhydria from autoimmune gastritis.
Elevated less than 10-fold with gastric pH 2 or lower
When gastrin is elevated but below the classic 10-fold threshold and gastric pH confirms acid production, additional specialized testing may be required. A secretin stimulation test is one established option. Gastrinoma cells respond paradoxically to secretin by releasing more gastrin. A rise of at least about 120 pg/mL above baseline has been used as a highly specific criterion in appropriately tested patients.
Secretin testing also has limitations. Severe hypochlorhydria or achlorhydria can produce false-positive responses, and PPIs complicate interpretation. Availability varies, and some centers use alternative diagnostic approaches because gastric acid analysis and secretin are not universally accessible.
| Finding | What it may suggest | Typical next consideration |
|---|---|---|
| High gastrin + high gastric pH | Low-acid state such as PPI effect or atrophic gastritis | Identify cause of reduced acid |
| >10× upper limit + gastric pH ≤2 | Strong biochemical evidence for ZES | Specialist confirmation and tumor localization |
| <10× upper limit + gastric pH ≤2 | ZES remains possible | Secretin testing or specialized acid-output evaluation |
Fasting, PPIs, and Test Preparation
Gastrin is normally affected by food, so diagnostic testing is usually performed after an overnight fast according to the laboratory’s instructions. Water may be permitted, but the ordering clinician or laboratory should provide the exact preparation requirements.
The most important preparation issue is acid-suppressing medication. PPIs can markedly increase gastrin and can make it difficult to distinguish drug-related hypergastrinemia from ZES. Older diagnostic protocols often called for stopping PPIs before fasting gastrin and gastric acid testing. That sounds straightforward but can be dangerous in a person who truly has ZES.
In untreated ZES, acid secretion can rebound quickly and severely. Abrupt loss of acid suppression may lead to painful ulcers, bleeding, perforation, or other complications. For that reason:
Do not stop a PPI simply because a gastrin test is scheduled.
A specialist may decide that medication adjustment is necessary, but the plan depends on the person’s ulcer history, current symptoms, PPI dose, endoscopy findings, and access to rapid follow-up. Some expert protocols temporarily substitute a shorter-acting H2 blocker and perform carefully timed testing, but this should be medically supervised.
Tell the clinician about all acid-related medicines, including prescription PPIs, over-the-counter omeprazole or similar drugs, H2 blockers, antacids, and potassium-competitive acid blockers. Also report previous stomach surgery, kidney disease, known autoimmune gastritis, B12 deficiency, and H. pylori history.
If medication withdrawal is unsafe or impractical, referral to a center experienced in ZES can be especially useful. Modern diagnosis sometimes combines biochemical evidence, gastric pH when obtainable, endoscopy, somatostatin-receptor imaging, and pathology rather than relying on a single rigid testing pathway.
What Happens After a High Gastrin Result
A high gastrin result usually triggers cause-finding, not an immediate cancer diagnosis. The next steps depend on the degree of elevation, stomach acidity, symptoms, medicines, and prior testing.
A clinician may first confirm that the sample was truly fasting and review medications. If the result is only mildly elevated while the patient is taking a PPI, the medication effect may be the most likely explanation, but that should still be considered alongside the original reason the test was ordered.
If low stomach acid is suspected, evaluation may include endoscopy, gastric biopsies, vitamin B12 studies, iron studies, antibodies associated with autoimmune gastritis, or H. pylori testing. The specific workup depends on symptoms and other laboratory findings.
If ZES remains a concern, gastric pH or acid output assessment can establish whether hypergastrinemia is inappropriate for the acid level. A secretin stimulation test may help when fasting gastrin is elevated but not diagnostic. MEN1 evaluation may include calcium, parathyroid hormone, family history review, and genetic counseling or testing when indicated.
Once biochemical evidence supports gastrinoma, imaging is used to locate and stage the tumor. Small duodenal gastrinomas can be challenging to identify, so a negative first scan does not necessarily exclude ZES. Endoscopic ultrasound and somatostatin-receptor PET imaging can add information in selected cases.
Treatment has two goals: control the dangerous acid hypersecretion and treat the tumor. PPIs remain central for acid control. Surgery may offer cure in selected patients with localized sporadic gastrinoma. MEN1-associated disease, multifocal tumors, and metastatic disease require individualized multidisciplinary management using surgery, somatostatin analogs, targeted therapy, peptide receptor radionuclide therapy, chemotherapy, liver-directed treatment, or other neuroendocrine tumor strategies as appropriate.
Seek urgent medical attention for vomiting blood, black tarry stools, fainting, sudden severe abdominal pain, or symptoms of major dehydration. These can indicate ulcer bleeding, perforation, or severe diarrhea-related complications and should not wait for routine gastrin follow-up.
References
- Current Medical Controversies in Zollinger-Ellison Syndrome 2026 (Review)
- All you need to know about gastrinoma today | Gastrinoma and Zollinger-Ellison syndrome: A thorough update 2023 (Review)
- Contemporary Approaches to the Surgical Management of Pancreatic Neuroendocrine Tumors 2024 (Review)
- Secretin Stimulation Test and Early Diagnosis of Gastrinoma in MEN1 Syndrome: Survey on the MEN1 Florentine Database 2022
- Gastrinoma and Zollinger Ellison syndrome: A roadmap for the management between new and old therapies 2021 (Review)
- Diagnosis of Zollinger-Ellison syndrome in the era of PPIs, faulty gastrin assays, sensitive imaging and limited access to acid secretory testing 2018 (Review)
Disclaimer
This article is for general education and is not a diagnosis or a substitute for care from a gastroenterologist, endocrinologist, or other qualified clinician. High gastrin has many causes, and suspected Zollinger-Ellison syndrome requires careful interpretation of acid levels, medications, and specialized testing. Never stop a proton pump inhibitor or other prescribed acid-suppressing medicine for testing unless the clinician managing the evaluation gives you a safe plan.