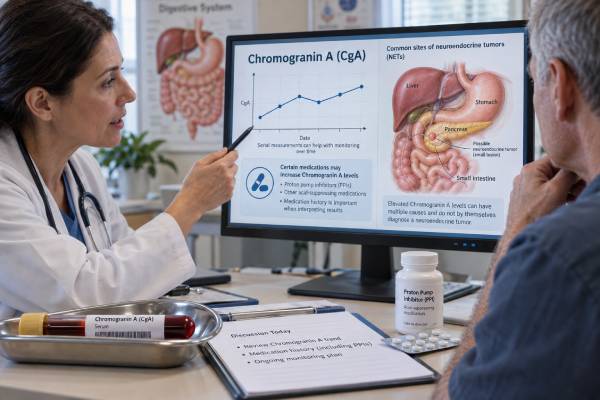
Chromogranin A (CgA) is a protein stored and released by neuroendocrine cells, so a blood test for CgA can be useful in selected people with neuroendocrine tumors (NETs). The test has an important limitation: high CgA is not specific for cancer. Proton pump inhibitors used for acid reflux, chronic atrophic gastritis, kidney impairment, heart disease, liver disease, inflammation, and several other conditions can raise the level. Different laboratories also use different assays and reference ranges, making one universal “normal” number impossible. CgA is therefore most useful when clinicians already know or strongly suspect a well-differentiated NET and can interpret serial results alongside imaging, pathology, symptoms, and tumor-specific hormones. A falling CgA may support treatment response when it was elevated at baseline, while a sustained rise may prompt further evaluation. Before testing, medication review—especially acid-suppressing drugs—is essential because a false elevation can be large enough to resemble tumor-related disease.
- There is no universal normal CgA range: use the reference interval and assay listed on your laboratory report.
- Proton pump inhibitors can substantially raise CgA; clinicians often consider pausing them for about 1–2 weeks when medically safe before repeat testing.
- Kidney impairment and chronic atrophic gastritis are major non-cancer causes of high CgA.
- CgA cannot diagnose a neuroendocrine tumor by itself; pathology and imaging remain central to diagnosis and staging.
- Serial CgA is most informative when the same assay is used and the marker was clearly elevated before treatment.
Table of Contents
- What the Chromogranin A Test Measures
- Chromogranin A Normal Range and High Levels
- Medication Effects and Non-Cancer Causes
- How CgA Is Used in Neuroendocrine Tumors
- Preparation, Testing, and Repeat Measurements
- Monitoring Treatment and Reading Trends
- CgA Compared With Other Neuroendocrine Tests
- Limitations and What to Do With a High Result
What the Chromogranin A Test Measures
Chromogranin A is an acidic protein packaged inside secretory granules of neuroendocrine cells. These cells are distributed throughout the gastrointestinal tract, pancreas, lungs, adrenal system, and other organs. When neuroendocrine cells release hormones or signaling molecules, they can also release CgA or fragments derived from it.
A blood CgA assay measures circulating chromogranin A-related material, usually in serum or plasma. The exact antibody and calibration system vary by manufacturer, which is one reason results from different laboratories may not be directly comparable.
CgA is considered a general neuroendocrine marker, not a hormone tied to one specific syndrome. A functioning NET may release a characteristic hormone, while a nonfunctioning tumor may not cause a classic hormonal syndrome at all. Depending on symptoms, clinicians may therefore order CgA together with more targeted tests such as 5-HIAA, serotonin, gastrin, insulin, glucagon, or other peptides.
CgA can be elevated in many well-differentiated gastroenteropancreatic and bronchopulmonary NETs, but not every tumor produces it. Poorly differentiated neuroendocrine carcinomas may behave differently and can have normal or only modest CgA values despite aggressive disease. Tissue diagnosis, including neuroendocrine markers and tumor grade, remains far more definitive than a blood CgA result.
The test is best viewed as a context-dependent activity marker. It may reflect neuroendocrine cell mass, secretion, treatment effect, or a non-cancer process that stimulates neuroendocrine cells. That broad biology explains both its usefulness and its tendency to generate false-positive results.
Chromogranin A Normal Range and High Levels
CgA does not have one standard reference range. Laboratories may report values in ng/mL, µg/L, nmol/L, or assay-specific units, and the upper limit can differ substantially from one method to another. The only appropriate “normal” range is the one printed on the report from the laboratory that performed the test.
This makes online comparisons particularly risky. A result of 120 in one assay might be normal or only slightly high, while the same number in another system could be clearly abnormal.
| Result pattern | Possible meaning | What matters next |
|---|---|---|
| Within the assay reference range | Does not exclude a neuroendocrine tumor | Symptoms, pathology, imaging, and tumor-specific hormones |
| Mild elevation | Common with medication effects or benign disease | Review PPIs, kidney function, stomach disease, and assay factors |
| Marked elevation | Can occur with substantial NET burden but also with major confounders | Confirm context before attributing the value to cancer |
| Falling serial values | May support treatment response if CgA tracked disease at baseline | Compare with imaging and clinical course |
| Persistent serial rise | May indicate progression or recurrence | Exclude medication/organ-function changes and consider imaging |
There is no CgA concentration that proves a NET is present. Extremely high values may occur with metastatic well-differentiated NETs, but proton pump inhibitors, severe kidney dysfunction, and hypergastrinemic gastric conditions can also cause large increases.
The fold change relative to the assay’s upper limit can sometimes be more useful than the raw number. For example, “three times the upper limit” communicates severity across laboratories better than comparing two incompatible numeric scales. Even then, the result still needs clinical context.
Medication Effects and Non-Cancer Causes
The most important preventable cause of a false high CgA is proton pump inhibitor (PPI) therapy. Drugs such as omeprazole, esomeprazole, pantoprazole, lansoprazole, and rabeprazole suppress stomach acid. The body responds by increasing gastrin, which stimulates enterochromaffin-like cells in the stomach and can increase CgA production.
The effect can be substantial and may develop even without a tumor. If a CgA result is unexpectedly high, clinicians commonly review PPI use before ordering advanced imaging. When it is medically appropriate, they may ask the patient to stop the PPI or switch temporarily to another acid-control strategy and repeat CgA after roughly 1–2 weeks. Acid-suppressing medication should never be stopped without guidance when it is needed for conditions such as severe esophagitis, ulcer bleeding prevention, or other high-risk indications.
Other important causes include:
- Chronic atrophic gastritis and pernicious anemia. Loss of acid-producing stomach cells causes persistent hypergastrinemia and neuroendocrine-cell stimulation.
- Kidney impairment. Reduced renal clearance can markedly increase circulating CgA; advanced kidney disease is a major confounder.
- Heart failure and cardiovascular disease. CgA can rise with neurohumoral stress and may correlate with illness severity.
- Liver disease. Impaired metabolism and systemic illness can influence levels.
- Inflammatory bowel disease and other gastrointestinal inflammation. Some patients show elevations unrelated to neoplasia.
- Endocrine disorders and physiologic stress. Several non-neoplastic states can change neuroendocrine secretion.
- Other cancers. CgA or related fragments may increase in some non-NET malignancies, further reducing specificity.
The combination of PPI therapy and reduced kidney function can be especially misleading. A very high number in that setting should not automatically be interpreted as a metastatic neuroendocrine tumor.
Because benign causes are so common, CgA generally performs poorly as a first-line screening test in people with vague symptoms. A clinician should start with the symptom pattern and use targeted biochemical testing rather than ordering a broad marker in isolation.
How CgA Is Used in Neuroendocrine Tumors
CgA may add useful information in well-differentiated neuroendocrine tumors, particularly gastroenteropancreatic NETs. It can be measured at diagnosis to establish a baseline and then repeated if the level appears to track the disease.
Diagnosis requires more than a blood marker
A neuroendocrine tumor is usually confirmed by tissue pathology. Imaging defines tumor location and extent, while pathology determines differentiation and grade, often using markers such as chromogranin, synaptophysin, and Ki-67 in tumor tissue. Blood CgA cannot replace these steps.
If symptoms suggest a functioning NET, a syndrome-specific biochemical test is often more valuable. Flushing and secretory diarrhea may lead to serotonin-related testing; recurrent ulcers and severe acid hypersecretion may lead to gastrin testing; hypoglycemia may require glucose, insulin, C-peptide, and proinsulin measurements. The general CgA marker can support the picture but rarely identifies the syndrome by itself.
Tumor burden and prognosis
In some well-differentiated NET populations, higher CgA correlates with greater disease burden, liver metastases, or a higher likelihood of progression. Recent literature on nonfunctioning pancreatic NETs also supports an association between CgA and disease extent or recurrence.
These are population-level associations, not fixed rules for an individual. A small tumor may produce large amounts of CgA, while another patient with extensive disease may have a normal marker. The biological behavior of the tumor and the assay both matter.
Other markers may be considered depending on tumor type. For pancreatic NETs, pancreatic polypeptide has historical use in selected settings, while high-grade neuroendocrine disease may prompt consideration of neuron-specific enolase. None of these markers should be used as a stand-alone diagnostic test.
Preparation, Testing, and Repeat Measurements
Preparation rules vary by laboratory. Some laboratories prefer a fasting sample because food and gastrointestinal stimulation can influence neuroendocrine secretion, while others do not require fasting. Follow the instructions from the ordering clinician or laboratory rather than applying a generic rule.
Before the blood draw, make sure the care team knows about:
- Proton pump inhibitors and other acid-suppressing drugs
- Kidney disease or recent changes in kidney function
- Chronic gastritis, pernicious anemia, or prior stomach surgery
- Heart or liver disease
- Recent major illness or inflammatory disease
- Any prior CgA results and the laboratory that measured them
For serial monitoring, consistency improves interpretability. Using the same laboratory and assay reduces the chance that a technical method change will look like a biological change. If a new result is dramatically different and no clinical change explains it, repeating the test may be appropriate before making major decisions.
If medication withdrawal is planned, timing should be documented. A CgA drawn while taking a PPI should not be compared casually with a later result obtained after stopping the drug, because the difference may reflect medication effect rather than tumor response.
Monitoring Treatment and Reading Trends
CgA can be useful for follow-up when three conditions are met: the patient has a confirmed NET, the marker was clearly elevated before treatment, and major confounders are stable or controlled.
A sustained fall after surgery, somatostatin analog therapy, peptide receptor radionuclide therapy, targeted therapy, or other effective treatment may support a response. A rising series can raise concern for progression or recurrence. However, treatment decisions should not be based on CgA alone.
Consider two contrasting examples. A patient with metastatic small-bowel NET has stable kidney function, no PPI use, and CgA that falls from eight times the upper limit to twice the upper limit during therapy while imaging also shows shrinkage. That is a coherent treatment-response pattern. Another patient’s CgA triples after starting omeprazole while scans and symptoms remain unchanged. The medication effect is a much more plausible explanation than sudden progression.
Imaging remains critical. Cross-sectional CT or MRI and somatostatin-receptor imaging can directly assess tumor burden in ways a blood marker cannot. Modern reviews increasingly emphasize that CgA has only moderate sensitivity and specificity and lacks standardization across assays.
A practical rule is to ask whether a CgA change is confirmed, clinically consistent, and free of new confounders. If not, repeat measurement and contextual review may be more appropriate than immediate treatment escalation.
CgA Compared With Other Neuroendocrine Tests
CgA is easy to order, but it should not be treated as the universal blood test for every neuroendocrine neoplasm. Different tests answer different clinical questions. Tumor tissue establishes the diagnosis and grade. Imaging shows location and extent. Hormone tests determine whether a functioning tumor is producing a specific secretory syndrome. CgA sits between these categories as a broad, imperfect marker that may help with longitudinal monitoring.
For suspected carcinoid syndrome, serotonin metabolism is more directly assessed with 5-HIAA, often in urine and in some settings in plasma. For suspected gastrinoma, fasting gastrin and gastric-acid context are essential because both PPIs and low stomach acid can produce hypergastrinemia. For insulinoma, glucose, insulin, C-peptide, and proinsulin measured during hypoglycemia are central. These targeted tests are more physiologically connected to the symptoms than CgA.
Newer blood-based approaches are being studied because CgA’s sensitivity, specificity, and assay standardization are limited. Multianalyte transcript assays and circulating tumor DNA methods can capture more than one biological feature, but their routine role varies by country and tumor type, and many remain investigational or selectively used. They do not make conventional imaging and pathology obsolete.
The distinction between blood CgA and chromogranin A staining in tissue is also important. Pathologists commonly use chromogranin immunohistochemistry as one marker of neuroendocrine differentiation in a biopsy or surgical specimen. A tumor can show chromogranin staining in tissue even when the patient’s circulating CgA is normal. Conversely, a high blood CgA from PPI use or kidney disease does not mean a tumor specimen would demonstrate malignant neuroendocrine cells.
Finally, the best marker can change over the course of care. A patient may begin with several abnormal biochemical tests, but only one may track reliably with tumor burden. Follow-up is therefore individualized rather than based on a standard panel repeated indefinitely. Clinicians generally gain more information from a small number of well-chosen, reproducible measurements than from repeatedly ordering every available neuroendocrine marker.
Limitations and What to Do With a High Result
The central limitation of CgA is that it is neuroendocrine-associated but not tumor-specific. It can be normal in real NETs and high in people without cancer. That makes it unsuitable as a general screening blood test.
Another limitation is that a percentage change can look impressive when the baseline value is near the assay cutoff. A rise from 90 to 140 may be numerically large but still require cautious interpretation if the laboratory’s upper limit is close to those values and the patient recently changed medications. Trends are strongest when the marker starts clearly abnormal, moves consistently across several samples, and agrees with objective disease assessment.
If you have no known NET and the result is high, the next step is usually not to assume cancer. A clinician may first check medication use, kidney function, gastrin-related stomach conditions, liver and cardiac disease, and the magnitude of elevation. If a reversible confounder is identified, repeating the test under better-controlled conditions can prevent unnecessary procedures.
If symptoms strongly suggest a neuroendocrine syndrome, evaluation should target the suspected hormone excess and include appropriate imaging. Severe flushing with wheezing, persistent watery diarrhea with dehydration, recurrent unexplained hypoglycemia, or refractory ulcer symptoms should be assessed clinically rather than managed through repeated CgA testing alone.
For someone with a confirmed NET, contact the oncology or endocrine team about a sustained rise, especially if accompanied by new pain, weight loss, worsening diarrhea or flushing, jaundice, or other changes. Urgent medical care is appropriate for severe dehydration, fainting, major breathing difficulty, uncontrolled low blood sugar, gastrointestinal bleeding, or other acute symptoms.
CgA is most useful when it answers a focused question: Does this marker reliably track this person’s known neuroendocrine tumor under consistent testing conditions? When the answer is yes, serial values can add meaningful information. When confounders dominate, imaging, pathology, and tumor-specific biochemical tests deserve more weight.
References
- Rethinking chromogranin A: unveiling gastrointestinal factors beyond neuroendocrine neoplasms-a narrative review 2025 (Review)
- Circulating Chromogranin A Is Associated With Disease Extent, Progression, and Recurrence in Patients With Nonfunctioning Pancreatic Neuroendocrine Tumor 2025 (Review)
- Established and novel circulating neuroendocrine tumor biomarkers for diagnostic, predictive and prognostic use 2023 (Review)
- Diagnostic work-up and advancement in the diagnosis of gastroenteropancreatic neuroendocrine neoplasms 2023 (Review)
- European Neuroendocrine Tumour Society (ENETS) 2023 guidance paper for nonfunctioning pancreatic neuroendocrine tumours 2023 (Guideline)
Disclaimer
This article provides general educational information and cannot diagnose a neuroendocrine tumor or interpret an individual chromogranin A result. CgA is strongly affected by medications, kidney function, stomach conditions, and assay method. Discuss an abnormal or changing result with the clinician who ordered the test before changing medication or assuming cancer progression.