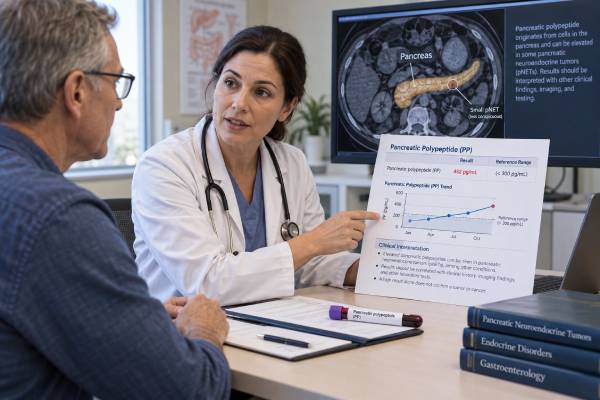
A pancreatic polypeptide (PP) test measures pancreatic polypeptide in blood, usually plasma. PP is a hormone released mainly by specialized cells in the pancreas, and its concentration can rise after eating, during low blood sugar, and with vagal nerve stimulation. Some pancreatic neuroendocrine tumors (PanNETs) also produce or are associated with increased PP. For that reason, clinicians may order the test as one part of an evaluation for a suspected pancreatic endocrine tumor or, less commonly, to follow a previously abnormal marker. A high result does not prove that a neuroendocrine tumor is present. Age, a nonfasting sample, diabetes, kidney disease, gastrointestinal conditions, and other factors can raise PP. The test also has limited sensitivity, so a normal result does not exclude a PanNET. Interpretation is strongest when the result is considered with symptoms, imaging, tumor-specific hormones, pathology, and other neuroendocrine markers.
- What it measures: Pancreatic polypeptide, a peptide hormone released mainly from PP cells in the pancreas.
- Preparation: Many laboratories require an 8-hour fast because eating can substantially raise pancreatic polypeptide.
- High result: May occur with pancreatic neuroendocrine tumors, but also with noncancer causes such as diabetes, kidney disease, gastrointestinal disorders, and nonfasting collection.
- Normal result: Does not rule out a pancreatic neuroendocrine tumor because pancreatic polypeptide has limited diagnostic sensitivity.
- Best use: As a supporting biomarker interpreted with symptoms, imaging, hormone tests, pathology, and the clinical setting rather than as a stand-alone cancer screen.
Table of Contents
- What the Pancreatic Polypeptide Test Measures
- Why the Test Is Ordered
- Preparation and Reference Ranges
- What High Pancreatic Polypeptide Levels Mean
- Pancreatic Polypeptide and Pancreatic Neuroendocrine Tumors
- Limitations and Other Tests Used With PP
- What Happens After the Result
What the Pancreatic Polypeptide Test Measures
Pancreatic polypeptide is a 36-amino-acid peptide hormone produced primarily by PP cells, also called gamma or F cells, in the pancreatic islets. These cells are especially abundant in parts of the pancreatic head. Smaller amounts of related peptide activity can also arise from the gastrointestinal tract.
PP secretion is closely connected to the autonomic nervous system and digestion. Levels normally increase after food intake and can also rise with hypoglycemia and vagal stimulation. This physiology is important because a test drawn under the wrong conditions can look abnormal even when no tumor is present.
The exact everyday role of PP is still not fully defined. It appears to influence pancreatic exocrine secretion, gastrointestinal motility, appetite-related signaling, and gallbladder function. In clinical practice, however, PP testing is used less to study normal physiology and more as a specialized endocrine or neuroendocrine marker.
A pancreatic polypeptide test is typically performed on plasma from a blood sample. It is different from tests for pancreatic enzymes such as lipase and amylase, and it is also different from markers used mainly in pancreatic adenocarcinoma. A clinician evaluating a suspected neuroendocrine tumor may consider PP along with a chromogranin A blood test or hormone tests selected according to the patient’s symptoms.
Pancreatic neuroendocrine tumors arise from hormone-producing neuroendocrine cells. Some are functioning tumors, meaning they release enough of a biologically active hormone to create a recognizable syndrome. Others are nonfunctioning tumors, which do not produce a classic hormone syndrome even though they may still release neuroendocrine proteins or peptides. PP has historically been used as a general marker that can be abnormal in either group, but its performance is not strong enough for it to be a stand-alone diagnostic test.
Why the Test Is Ordered
A clinician may order pancreatic polypeptide when a pancreatic endocrine or neuroendocrine tumor is part of the differential diagnosis. The test is most useful when there is already a clinical reason to suspect such a tumor, not as a routine check in people without symptoms or imaging findings.
Possible reasons for testing include:
- A pancreatic mass with features suggesting a neuroendocrine tumor
- Symptoms that raise concern for a functional pancreatic neuroendocrine tumor
- A known PanNET for which PP was elevated at diagnosis and may provide an additional trend marker
- Evaluation in a specialist neuroendocrine tumor program where several biomarkers are being interpreted together
- Assessment of vagal nerve function in specialized testing protocols involving meal or sham feeding
The choice of blood tests should match the suspected hormone syndrome. For example, recurrent fasting hypoglycemia may prompt testing for insulin and related markers rather than relying on PP. Severe peptic ulcer disease with marked acid hypersecretion may lead to a gastrin blood test. Profuse watery diarrhea with electrolyte loss can lead to a VIP test. These hormone-specific tests are usually more informative when a classic functional syndrome is present.
PP testing is sometimes described as a marker for nonfunctioning PanNETs because these tumors lack a dominant hormone syndrome. That description should not be interpreted to mean that PP reliably detects them. Contemporary studies and reviews consistently emphasize that the sensitivity and specificity of older single-analyte neuroendocrine markers are limited.
PP also should not be used as a population screening test for pancreatic cancer. Pancreatic adenocarcinoma and pancreatic neuroendocrine tumors are biologically different diseases. A person with unexplained weight loss, jaundice, persistent abdominal pain, a pancreatic mass, or other concerning findings needs a diagnostic evaluation appropriate to the clinical picture rather than a PP test alone.
Preparation and Reference Ranges
Preparation matters more for pancreatic polypeptide than for many routine blood tests because food itself stimulates PP release. Mayo Clinic Laboratories, for example, requires 8 hours of fasting before collection. Patients should follow the instructions from the laboratory that is actually performing their test because specimen requirements and assay methods can differ.
Some laboratories also require special handling. PP may be measured in EDTA plasma, with rapid cooling, separation, and freezing after collection. These preanalytic details help preserve a reliable specimen.
A current Mayo Clinic Laboratories reference interval is age-dependent:
| Age | Reference value |
|---|---|
| 0–19 years | Not established |
| 20–29 years | <228 pg/mL |
| 30–39 years | <249 pg/mL |
| 40–49 years | <270 pg/mL |
| 50–59 years | <291 pg/mL |
| 60–69 years | <312 pg/mL |
| 70–79 years | <332 pg/mL |
| 80 years and older | Not established |
These numbers are assay-specific, not universal targets. A result should be compared with the reference interval printed on the patient’s own report. Units also matter; a value in pg/mL should not be compared directly with a range reported in another unit without proper conversion.
Age is clinically relevant because normal PP values tend to rise as people get older. A mild elevation in an older adult may therefore have a different meaning from the same concentration in a younger adult.
Factors that can distort the result
Food is one of the most important. Eating can cause a significant and prolonged increase, which is why a nonfasting specimen can produce a false impression of abnormality. If a result is unexpectedly high and the patient was not fasting, repeating the test under correct conditions may be more useful than immediately assuming tumor progression.
The laboratory should also know about special circumstances that can interfere with its method. For example, some radioimmunoassays have precautions for patients who recently received diagnostic or therapeutic radioisotopes. The treating team or laboratory can determine whether collection needs to be delayed.
What High Pancreatic Polypeptide Levels Mean
A high PP concentration means that more pancreatic polypeptide than expected was detected under the conditions of that assay. It does not reveal the cause by itself.
Potential explanations include:
- Pancreatic neuroendocrine tumors. Some insulinomas, glucagonomas, PP-secreting tumors, and other PanNETs can be associated with marked PP elevation.
- A nonfasting sample. Food is a normal physiologic stimulus and can substantially raise PP.
- Diabetes. Abnormal PP concentrations can occur in people with diabetes and altered autonomic or pancreatic function.
- Chronic kidney disease. Reduced clearance and broader metabolic changes can contribute to higher values.
- Gastrointestinal or inflammatory conditions. Diarrheal illnesses, gut inflammation, and other gastrointestinal disorders have been reported as causes of nonspecific elevation.
- Older age. Reference values tend to increase with age.
- Other pancreatic disease. Pancreatitis, extensive pancreatic injury, and some pancreatic exocrine tumors can alter PP physiology, although patterns vary by condition and disease extent.
The degree of elevation can add context, but there is no single PP concentration that reliably separates cancer from noncancer. A dramatic and reproducible elevation in a fasting patient with a pancreatic mass is more concerning than a borderline result after eating, yet neither scenario can establish the diagnosis without other evidence.
A low PP value is usually less important in tumor assessment. Very low basal levels or a lack of the expected rise after sham feeding can be relevant in specialized evaluation of vagal nerve damage or extensive pancreatic destruction. That is a different clinical question from using PP as a tumor-associated marker.
Trends may be useful when a patient’s tumor clearly produced PP before treatment. If the value falls after surgery or systemic therapy and later rises consistently, the pattern may support further evaluation. However, variation from fasting status, assay changes, kidney function, medications, or other illnesses should be considered before calling a change tumor progression.
Pancreatic Polypeptide and Pancreatic Neuroendocrine Tumors
Pancreatic neuroendocrine tumors are uncommon and biologically diverse. Their behavior ranges from small, slow-growing well-differentiated tumors to aggressive high-grade neuroendocrine carcinomas. Blood biomarkers cannot capture that complexity on their own.
Older studies suggested that PP could be elevated in a substantial fraction of PanNETs, particularly when disease was metastatic. More recent reviews still recognize PP as a traditional circulating neuroendocrine marker but emphasize its modest sensitivity. Published estimates vary by population and tumor type; one recent comprehensive review summarized sensitivity around the mid-50% range overall and roughly 60% for pancreatic tumors in data it reviewed. Other studies have found different values.
That variability has a practical consequence: a normal PP test cannot safely exclude a PanNET. Even a patient with proven metastatic disease may have a normal marker. Conversely, high PP does not establish that a pancreatic mass is neuroendocrine because several nonmalignant conditions can raise it.
Evidence from hereditary surveillance also illustrates the limitation. In a 2025 long-term study of people with multiple endocrine neoplasia type 1 (MEN1), annual pancreatic polypeptide and chromogranin A measurements performed poorly for detecting PanNETs and did not change clinical management during follow-up. The authors concluded that these markers were not useful as screening tools in that setting. That finding should not be generalized to every clinical scenario, but it reinforces why biomarker testing cannot replace appropriate imaging in high-risk patients.
Tumor diagnosis and grading depend on tissue when biopsy or surgery is appropriate. Pathologists use tumor architecture, mitotic activity, Ki-67 proliferation index, and neuroendocrine markers such as synaptophysin and chromogranin. Imaging defines location and extent, while somatostatin-receptor imaging can help characterize many well-differentiated NETs and guide treatment decisions.
The result therefore has its greatest value as supporting evidence. A PP-producing tumor may give clinicians another measurable signal, but the marker should be connected to a documented tumor phenotype rather than treated as a universal PanNET detector.
Limitations and Other Tests Used With PP
The main limitation of pancreatic polypeptide is the combination of limited sensitivity and limited specificity. It can miss tumors and can be elevated when no neuroendocrine malignancy is present. This is why many modern NET guidelines and reviews place greater emphasis on clinical presentation, imaging, histology, and syndrome-specific hormone tests.
Common companion tests include:
- Chromogranin A (CgA): A traditional neuroendocrine marker that can be elevated in many well-differentiated NETs, but proton pump inhibitors, kidney disease, gastric conditions, and other factors can cause false positives.
- Neuron-specific enolase (NSE): More often informative in poorly differentiated or higher-grade neuroendocrine disease than in many well-differentiated PanNETs. The NSE blood test also has important preanalytic limitations, including false elevation from hemolysis.
- Tumor-specific hormones: Insulin, proinsulin, C-peptide, gastrin, glucagon, VIP, or somatostatin are selected when symptoms suggest a functional tumor.
- 5-HIAA: More closely associated with serotonin-producing NETs and carcinoid syndrome than with most pancreatic tumors; testing may use blood or urine depending on the situation.
- Imaging: Multiphasic CT, MRI, endoscopic ultrasound, and somatostatin-receptor PET imaging may be used depending on the tumor question.
- Pathology: Biopsy or surgical tissue establishes tumor type and grade when tissue sampling is indicated.
No blood marker can determine by itself whether a pancreatic neuroendocrine tumor is localized, resectable, well differentiated, or aggressive. Those decisions depend on imaging and pathology.
Why newer biomarker research matters
Research is moving toward multianalyte blood tests, molecular signatures, circulating tumor DNA, circulating tumor cells, RNA-based assays, and protein panels. A 2022 study of multiple plasma proteins, for example, showed that a machine-learning panel could distinguish PanNET cases from controls with high accuracy in its research cohort. Such findings are promising, but they do not make a new test ready for routine care automatically. Independent validation, standardized methods, clinically useful thresholds, and proof that the test improves patient management are required.
This broader trend helps explain why a single older biomarker such as PP should be interpreted cautiously. The future of neuroendocrine tumor monitoring may rely on combinations of clinical, imaging, molecular, and biochemical information rather than any one circulating peptide.
What Happens After the Result
The next step depends on why PP was ordered and what else is known about the patient.
If the result is only mildly high, the clinician may first verify whether the patient fasted correctly and review kidney function, diabetes, gastrointestinal illness, and other potential explanations. Repeating the test under standardized conditions can be reasonable when a preanalytic issue is likely.
If the value is clearly elevated and there are symptoms or imaging findings that suggest a PanNET, additional evaluation may include:
- Confirming the result and laboratory reference range.
- Ordering hormone-specific tests based on symptoms.
- Reviewing or obtaining dedicated pancreatic imaging such as contrast-enhanced CT or MRI.
- Considering endoscopic ultrasound when detailed pancreatic assessment or tissue sampling is needed.
- Using somatostatin-receptor imaging in appropriate suspected or confirmed neuroendocrine tumors.
- Referring to endocrinology, gastroenterology, oncology, surgery, or a multidisciplinary neuroendocrine tumor team.
- Obtaining pathology when biopsy or surgery is clinically indicated.
For a patient with a known PanNET, clinicians may continue PP monitoring if it was clearly elevated and clinically informative at baseline. Trends should be measured with similar preparation and, when possible, the same assay. A rising marker should generally trigger clinical review rather than an automatic change in treatment.
A normal result does not close the evaluation when symptoms or imaging remain concerning. For example, recurrent documented hypoglycemia, severe refractory ulcers, unexplained secretory diarrhea, jaundice, progressive weight loss, or a suspicious pancreatic lesion requires appropriate diagnostic workup regardless of PP.
Patients can ask: Was I fasting long enough? Is my value being compared with an age-appropriate range? Could kidney disease or diabetes explain the result? Was PP elevated when my tumor was first diagnosed? Which imaging or hormone test is more important for my specific symptoms? These questions keep the result in its proper clinical context.
Urgent care is based on symptoms, not on the PP number alone. Severe hypoglycemia with confusion or loss of consciousness, dehydration from relentless diarrhea, vomiting with inability to keep fluids down, new jaundice with fever, or severe worsening abdominal pain can require prompt medical assessment.
References
- HPP – Overview: Pancreatic Polypeptide, Plasma 2026 (Laboratory Reference)
- Pancreatic neuroendocrine neoplasms (pNENs): Genetic and environmental biomarkers for risk of occurrence and prognosis 2025 (Review)
- Biochemical Markers for Neuroendocrine Tumors: Traditional Circulating Markers and Recent Development—A Comprehensive Review 2024 (Review)
- Diagnostic and prognostic biomarkers for pancreatic neuroendocrine neoplasms 2024 (Review)
- Plasma protein biomarkers for the detection of pancreatic neuroendocrine tumors and differentiation from small intestinal neuroendocrine tumors 2022
- Chromogranin a and pancreatic polypeptide are not suitable for the screening of pancreatic neuroendocrine tumors in MEN1 – a long-term follow-up study 2025
Disclaimer
This article provides general information about pancreatic polypeptide testing and is not a diagnosis of a pancreatic neuroendocrine tumor or other disease. Reference ranges and specimen requirements vary by laboratory, and PP results should be interpreted with fasting status, age, kidney function, symptoms, imaging, and other tests. A normal PP level does not exclude a pancreatic neuroendocrine tumor, and a high level does not prove cancer.