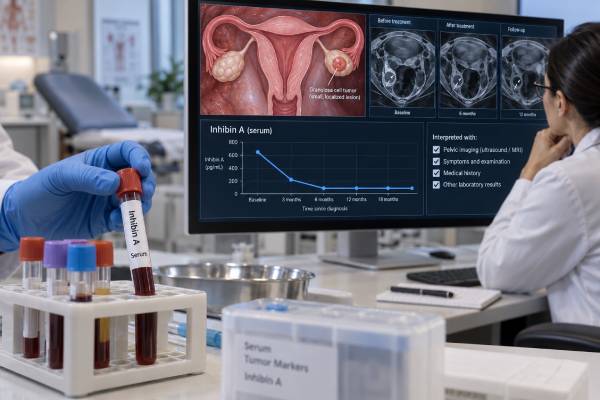
The inhibin A tumor marker test measures inhibin A, a hormone made mainly by ovarian granulosa cells. It can be useful when a granulosa cell tumor is suspected or when a person with a known granulosa cell tumor is being followed after treatment. Inhibin A is not a general ovarian cancer screening test, and an elevated result does not prove that cancer is present. Levels vary with age, menstrual-cycle phase, pregnancy, menopause, and the laboratory method used. Granulosa cell tumors can release inhibin A, but some produce little or none, so a normal result cannot rule them out. Inhibin B and anti-Müllerian hormone (AMH) are often measured because they may be more sensitive markers in many granulosa cell tumors. The most useful pattern is a marker that was elevated before treatment, fell after successful therapy, and is then followed over time. A rising value during surveillance can prompt clinical review and imaging, especially because these tumors may recur years after the original diagnosis.
- What it measures: Inhibin A is a granulosa-cell hormone reported most often in pg/mL and can act as a tumor marker for some ovarian sex cord-stromal tumors.
- High levels: An elevated result may occur with a granulosa cell tumor, but pregnancy, normal reproductive cycling, and other ovarian conditions can also raise inhibin A.
- Typical reference values: One current tumor-marker assay lists <98 pg/mL for premenopausal females and <5 pg/mL after menopause, but the laboratory’s own range should be used.
- Best use: Inhibin A is most useful for monitoring when the tumor was known to produce it at diagnosis; trends are more informative than a single value.
- Important limitation: A normal inhibin A result does not exclude granulosa cell tumor, and inhibin B or AMH may be more informative in some patients.
Table of Contents
- What Inhibin A Is and Why Tumors Can Raise It
- Why the Inhibin A Test Is Ordered
- Normal and High Inhibin A Levels
- How Testing Is Done and How to Prepare
- Inhibin A in Granulosa Cell Tumors
- Monitoring After Treatment and Recurrence
- Inhibin A vs. Inhibin B, AMH, and Other Markers
What Inhibin A Is and Why Tumors Can Raise It
Inhibin A is a protein hormone in the transforming growth factor-beta family. It is built from one alpha subunit and one beta-A subunit. In the normal reproductive system, ovarian granulosa cells produce inhibins as part of the hormonal feedback system that helps regulate follicle-stimulating hormone, or FSH.
In people who menstruate, inhibin A changes during the menstrual cycle. It is usually lower in the early follicular phase and rises later in the cycle, particularly around ovulation and during the luteal phase. Pregnancy can produce much higher concentrations because the placenta also contributes inhibin A. After menopause, ovarian follicular activity falls sharply, so inhibin A should be very low.
That normal biology explains why inhibin A can function as a tumor marker. Granulosa cell tumors arise from ovarian granulosa cells and can retain the ability to secrete reproductive hormones. A tumor may therefore produce measurable or elevated inhibin A even when the normal ovary would not be expected to produce much.
The test measures serum inhibin A, not inhibin staining in a tumor biopsy. These are related but different concepts. Pathologists may use inhibin immunohistochemistry on tumor tissue to help identify sex cord-stromal differentiation, while the blood test measures circulating hormone that may reflect tumor activity.
Inhibin A is not specific enough to diagnose a tumor by itself. It is a biologic clue that becomes more useful when combined with symptoms, imaging, pathology, other markers, and the patient’s reproductive status.
Why the Inhibin A Test Is Ordered
Clinicians mainly use inhibin A in two situations: evaluating a suspected granulosa cell tumor and following a known tumor over time. It may be ordered before surgery to establish a baseline, after treatment to see whether a previously elevated level falls, and during surveillance to look for a meaningful rise.
A clinician may consider the test when an ovarian mass occurs with features that suggest a sex cord-stromal tumor, such as abnormal uterine bleeding, estrogen-related endometrial changes, pelvic pain, abdominal enlargement, or a hormonally active ovarian mass. Granulosa cell tumors can produce estrogen, so some patients present with postmenopausal bleeding, irregular periods, or endometrial thickening rather than with symptoms typically associated with epithelial ovarian cancer.
In children or adolescents, juvenile granulosa cell tumors can cause signs of early estrogen exposure. Evaluation in younger patients is specialized because normal hormone ranges change with age and pubertal stage.
Inhibin A may also be ordered with other markers rather than alone. For example, a clinician evaluating a possible granulosa cell tumor may add inhibin B testing because inhibin B is elevated in a higher proportion of granulosa cell tumors in many series. The AMH tumor marker test can provide another independent measure of granulosa-cell activity.
The test is not recommended as a population screening test for ovarian cancer. Most ovarian cancers are epithelial tumors, and inhibin A is not sensitive or specific enough to screen people without a known mass or clinical indication. A normal result also cannot reassure against ovarian cancer in general.
Normal and High Inhibin A Levels
There is no single universal inhibin A cutoff that applies to every laboratory, age, menstrual phase, and clinical purpose. Different immunoassays can produce different values, so the reference range printed on the actual laboratory report is the correct comparison.
One current U.S. tumor-marker assay uses the following reference limits:
| Group | Example reference value | Interpretive point |
|---|---|---|
| Premenopausal females | <98 pg/mL | Cycle phase can substantially affect the result |
| Postmenopausal females | <5 pg/mL | Persistent measurable elevation is more unusual after menopause |
| Males | <5 pg/mL | Detectable elevations require clinical interpretation |
Other laboratories use more detailed menstrual-phase ranges. For that reason, a result that looks “high” compared with one website may still fall inside the performing laboratory’s interval.
What can cause a high inhibin A result?
A granulosa cell tumor is an important cause in the right clinical setting, particularly after menopause or in a person already known to have an inhibin A-producing tumor. However, other explanations include:
- Normal menstrual-cycle variation
- Pregnancy
- Some other ovarian sex cord-stromal tumors
- A subset of epithelial ovarian tumors, especially certain mucinous tumors
- Assay interference or method-related variation
A high result should therefore trigger interpretation, not an automatic cancer diagnosis.
Why menopause changes the meaning
Postmenopausal levels are normally very low because ovarian follicles are no longer active in the same way. As a result, a clear increase can be more conspicuous and potentially more informative after menopause than during reproductive years. In premenopausal patients, timing within the menstrual cycle can create a wider physiologic range and more overlap with abnormal values.
If serial monitoring is planned, using the same laboratory and method whenever possible reduces avoidable variation. A change caused by switching assays can look like a biological change even when the patient’s disease is stable.
A borderline elevation deserves special caution. For example, a modest result in a menstruating patient may reflect normal luteal-phase production, while the same number in a postmenopausal patient could be more unusual. Clinicians may repeat the test, review cycle timing, compare with older results, and look at inhibin B or AMH before deciding that the change is tumor-related. In a patient who has already had both ovaries removed, persistent or newly rising inhibin A is also interpreted differently because normal ovarian production should no longer be contributing.
There is no validated “doubling time” rule for inhibin A comparable to some other disease markers. A result should not be labeled progression simply because it increased by a certain percentage. The useful pattern is a sustained rise that is biologically plausible for that patient and consistent with the overall clinical picture.
How Testing Is Done and How to Prepare
The inhibin A tumor marker test uses a blood sample drawn from a vein. The specimen is processed as serum, and the laboratory measures inhibin A with an immunoassay. Some laboratories require the serum to be separated and frozen promptly, so specimen handling is more specialized than for a routine chemistry test.
Fasting is generally not required for inhibin A itself. If other blood tests are being drawn at the same visit, follow any instructions for those tests. Do not stop medicines or hormones unless the ordering clinician specifically advises it.
Before testing, it helps to tell the clinician or laboratory about:
- Pregnancy or the possibility of pregnancy
- Menstrual status and, when relevant, cycle timing
- Menopause status
- Hormonal therapies
- Prior removal of one or both ovaries
- A history of granulosa cell tumor or other ovarian tumor
- Previous inhibin A values and the laboratory that performed them
The result is usually reported in pg/mL. For tumor monitoring, the direction and magnitude of change over time often matter more than whether one value is slightly above a reference limit.
Laboratory immunoassays can occasionally be affected by heterophile antibodies or other analytical interference. If a result is dramatically inconsistent with symptoms, imaging, or previous values, clinicians can ask the laboratory to investigate possible interference or repeat the test using another approach.
Inhibin A in Granulosa Cell Tumors
Granulosa cell tumors are rare ovarian sex cord-stromal tumors. Most are the adult type, while juvenile granulosa cell tumors account for a smaller proportion and usually occur at younger ages. These tumors differ from the much more common epithelial ovarian cancers in biology, pathology, natural history, and marker patterns.
Adult granulosa cell tumors often carry a characteristic FOXL2 molecular alteration, while juvenile tumors have different molecular features. Diagnosis depends on pathology, not on serum inhibin A. Tissue appearance, immunohistochemical markers, and molecular findings can help pathologists distinguish granulosa cell tumors from other ovarian neoplasms.
Serum inhibin A is elevated in a substantial but incomplete proportion of patients. Current laboratory guidance cites elevation in roughly 70% of granulosa cell tumors, which means the test can be useful but is not sensitive enough to rule out disease when normal. Inhibin B is elevated more often in many studies.
The marker becomes especially informative when three conditions are met:
- The patient has a pathologically confirmed granulosa cell tumor.
- Inhibin A was clearly elevated before treatment.
- The value falls after effective surgery or therapy.
In that setting, the patient has an individualized biochemical marker that can be followed alongside symptoms and imaging.
A high inhibin A level does not tell the exact tumor size, stage, location, or whether surgery is possible. It also does not replace pathology. Two people with the same tumor burden can have very different hormone levels because tumors vary in how strongly they secrete inhibin.
Monitoring After Treatment and Recurrence
Long-term follow-up matters in granulosa cell tumors because recurrence can occur years or even decades after the first treatment. A marker that reflects an individual patient’s tumor can help clinicians decide when closer evaluation is needed.
After tumor removal, an elevated inhibin A level often falls. A persistently elevated value may raise concern for residual disease, but the timing of the blood draw, normal reproductive hormone production, and the patient’s menopausal status must be considered.
During surveillance, clinicians look for a trend rather than reacting to one minor fluctuation. A reproducible rise from a stable baseline is more concerning than a small isolated change. If inhibin A rises meaningfully, the next step may include repeat testing, pelvic examination, ultrasound, CT, MRI, or another imaging study chosen for the clinical situation.
Historical studies found that inhibin elevations can precede clinically apparent recurrence in some patients. This does not mean every rise predicts recurrence, and there is no universal number of months by which the marker will lead imaging. The practical value is that a rising marker can serve as an early signal to investigate.
Surveillance plans are individualized according to tumor stage, surgery, pathology, age, fertility goals, previous recurrence, and which markers were informative at diagnosis. Because late recurrence is a recognized feature, follow-up may continue for many years.
A stable low value is most reassuring when it matches the patient’s post-treatment baseline. If a person started with very high inhibin A and the level became undetectable after surgery, later reappearance can be clinically meaningful even before symptoms develop. By contrast, if inhibin A was never elevated at diagnosis, a normal result during follow-up provides limited reassurance because the tumor has already shown that it may not secrete this marker.
Treatment response can also be followed with the marker when disease is measurable and inhibin A is informative. Falling concentrations during systemic therapy can support evidence of response, while a sustained rise may prompt reassessment. Marker changes should still be checked against imaging because hormone production can change independently of tumor size, and no serum marker can show exactly where recurrent disease is located.
Patients should report new pelvic or abdominal pain, increasing abdominal size, unexplained bleeding, early satiety, or other persistent symptoms even when tumor markers are normal. A marker is an added surveillance tool, not a replacement for clinical assessment.
Inhibin A vs. Inhibin B, AMH, and Other Markers
Inhibin A is one part of a marker strategy for granulosa cell tumors. Its main advantage is biological relevance: granulosa cells naturally make inhibins. Its main disadvantage is that normal ovarian function can raise it and not every tumor secretes enough for detection.
| Marker | Potential role in granulosa cell tumors | Key limitation |
|---|---|---|
| Inhibin A | Diagnosis support and serial monitoring when elevated at baseline | Lower sensitivity than inhibin B in many cohorts; varies with reproductive state |
| Inhibin B | Often the most frequently elevated inhibin marker in granulosa cell tumors | Also varies with ovarian function and is not cancer-specific |
| AMH | Independent granulosa-cell marker useful for some patients during follow-up | Strongly influenced by ovarian reserve in premenopausal patients |
| CA-125 | May be measured when evaluating an adnexal mass | Not a specific granulosa cell tumor marker and often reflects peritoneal irritation |
The CA-125 blood test is much more closely associated with epithelial ovarian cancer evaluation and monitoring. It should not be assumed to replace inhibin or AMH when pathology shows a granulosa cell tumor.
A practical approach is to identify which marker or combination was abnormal at diagnosis and then follow the most informative marker consistently. If inhibin A was normal while inhibin B or AMH was high, there is little reason to expect inhibin A alone to become a sensitive surveillance test later.
When reviewing a result, ask four questions: Is the value truly above this laboratory’s reference range? Is the person premenopausal, postmenopausal, or pregnant? Was inhibin A previously elevated with known tumor? And is the current change confirmed by a repeat or supported by symptoms, examination, or imaging? Those questions turn a raw number into clinically useful information.
References
- INHA – Overview: Inhibin A, Tumor Marker, Serum 2026
- Current status of treatment for malignant ovarian sex cord-stromal tumors 2024 (Review)
- Immunohistochemical markers of prognosis in adult granulosa cell tumors of the ovary – a review 2023 (Review)
- Relevance of Molecular Pathology for the Diagnosis of Sex Cord–Stromal Tumors of the Ovary: A Narrative Review 2023 (Review)
- Update on Ovarian Sex Cord-Stromal Tumors 2023 (Review)
- Inhibin as a marker for granulosa-cell tumors 1989
Disclaimer
This article provides general information about inhibin A testing and does not diagnose or exclude a granulosa cell tumor. Inhibin A varies with menstrual status, pregnancy, laboratory method, and tumor biology, so results should be interpreted by a clinician together with pathology, imaging, and other markers. New or worsening pelvic symptoms, abnormal bleeding, or a rising marker during cancer follow-up should be discussed promptly with the treating team.