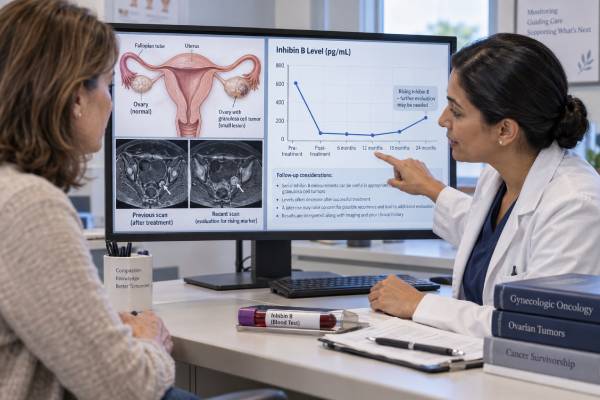
The inhibin B tumor marker test measures a hormone made mainly by ovarian granulosa cells. It is one of the most useful blood markers for adult granulosa cell tumors because many of these tumors continue to produce inhibin B even when normal ovarian hormone production should be low. The test can support the evaluation of an ovarian mass, establish a baseline before treatment, and help monitor for residual or recurrent disease after surgery. A high result does not by itself diagnose cancer, and a normal result does not completely exclude a granulosa cell tumor. Age, menstrual-cycle phase, menopause, ovarian reserve, pregnancy status, and the laboratory method all affect interpretation. Inhibin B is especially informative when it was elevated at the original diagnosis and then fell after treatment. During long-term surveillance, a sustained rise from that patient’s baseline can prompt repeat testing and imaging because granulosa cell tumors may recur many years after initial therapy. Clinicians often pair inhibin B with anti-Müllerian hormone (AMH) and, in some cases, inhibin A.
- What it measures: Inhibin B is a granulosa-cell hormone usually reported in pg/mL and can serve as a serum marker for some ovarian sex cord-stromal tumors.
- High levels: A high value can occur with granulosa cell tumors, but normal ovarian function and some other ovarian tumors can also raise inhibin B.
- Reference ranges vary: One current assay lists <224 pg/mL for women ages 13–41 in the follicular phase, <80 pg/mL in the luteal phase, and <12 pg/mL after age 51 and menopause.
- Recurrence monitoring: Inhibin B can rise before recurrent disease is clinically obvious in some patients, making serial trends useful when the tumor secreted it at baseline.
- Key limitation: A normal result cannot rule out granulosa cell tumor; AMH, imaging, pathology, and clinical findings remain important.
Table of Contents
- What Inhibin B Measures
- Why Inhibin B Is Ordered
- Inhibin B Reference Ranges and High Results
- How the Test Is Performed
- Granulosa Cell Tumors and Inhibin B
- Recurrence and Long-Term Monitoring
- Inhibin B vs. Other Tumor Markers
What Inhibin B Measures
Inhibin B is a dimeric protein hormone made from an alpha subunit and a beta-B subunit. In females, it is produced primarily by granulosa cells in developing ovarian follicles. It participates in feedback to the pituitary gland, where it helps suppress follicle-stimulating hormone, or FSH.
Because normal granulosa cells make inhibin B, tumors that arise from granulosa cells may also produce it. Adult granulosa cell tumors are the most common malignant ovarian sex cord-stromal tumors, and inhibin B is often measurable when these tumors are active. This is the biological basis for using the hormone as a tumor marker.
The blood test measures the concentration of inhibin B circulating in serum. It is different from tissue staining for inhibin, which pathologists may use on a biopsy or surgical specimen. A blood level can help monitor disease activity; tissue staining helps classify the tumor itself.
Inhibin B is not a general marker for all ovarian cancers. Most ovarian cancers are epithelial tumors, and their biology differs from granulosa cell tumors. Some epithelial tumors, particularly certain mucinous tumors, can also produce inhibin, which is one reason the test is not diagnostic on its own.
Normal inhibin B also changes across life. Levels are influenced by childhood development, puberty, ovarian reserve, the menstrual cycle, and menopause. This makes the patient’s age and reproductive status essential parts of interpretation.
Why Inhibin B Is Ordered
Inhibin B is most commonly ordered when a clinician suspects a granulosa cell tumor or is monitoring a patient with a known granulosa cell tumor. It may be measured before surgery, soon after treatment, and repeatedly during follow-up.
Possible reasons to order the test include:
- An ovarian mass with features suggesting a sex cord-stromal tumor
- Abnormal uterine bleeding associated with suspected estrogen production
- Postmenopausal bleeding with an ovarian mass
- Precocious puberty or estrogenic effects in a child with a suspected juvenile granulosa cell tumor
- A known granulosa cell tumor before treatment, to establish whether the tumor secretes inhibin B
- Monitoring after tumor removal
- Evaluation for possible recurrence when symptoms, imaging, or another marker becomes concerning
A baseline value is particularly useful. If inhibin B is markedly elevated before surgery and then falls to a low or undetectable level after complete resection, the patient has an individualized biochemical marker that can be followed over time.
Clinicians often order AMH testing for granulosa cell tumors at the same time because AMH is also produced by granulosa cells and can provide complementary information. Inhibin A may also be checked, although inhibin A testing is less sensitive than inhibin B in many granulosa cell tumor cohorts.
The test should not be used as a stand-alone screening test for ovarian cancer in people without a clinical indication. A low-risk patient with no symptoms and no ovarian mass does not gain a reliable cancer screen from measuring inhibin B.
Inhibin B Reference Ranges and High Results
Inhibin B does not have one universal normal range. Reference intervals differ by age, sex, menstrual phase, and assay. Values from different laboratories should not be assumed to be directly interchangeable.
One current laboratory method uses the following female reference limits:
| Group | Example reference value | Interpretation issue |
|---|---|---|
| Age 13–41, follicular phase | <224 pg/mL | Normal follicular activity can produce measurable inhibin B |
| Age 42–51, follicular phase | <108 pg/mL | Levels generally fall as ovarian reserve declines |
| Age 13–51, luteal phase | <80 pg/mL | Cycle phase matters when interpreting a single result |
| Postmenopausal, age >51 | <12 pg/mL | Persistent elevation is more unusual when normal follicular production has ceased |
Other laboratories may use different cutoffs, including a postmenopausal threshold near 17 pg/mL. The correct range is the one printed on the report from the performing laboratory.
What can cause a high inhibin B level?
A high result can be associated with:
- Adult or juvenile granulosa cell tumor
- Some other ovarian sex cord-stromal tumors
- A subset of mucinous epithelial ovarian tumors
- Normal reproductive ovarian function, depending on age and cycle phase
- Fertility-related changes in ovarian follicular activity
- Analytical interference in uncommon cases
The same numerical value can therefore have different significance in different patients. A level of 40 pg/mL may be entirely compatible with normal ovarian activity in a premenopausal woman but more notable after menopause or after both ovaries have been removed.
A small isolated increase should usually be interpreted cautiously. Clinicians often repeat the test, compare it with previous values, verify whether the same assay was used, and consider AMH or imaging before concluding that disease has returned.
Premenopausal interpretation is harder because healthy follicles produce inhibin B. A single value may change with cycle timing or with changes in ovarian reserve. In someone who still has a functioning ovary after fertility-sparing surgery, the surveillance baseline may therefore be measurable rather than nearly zero. The clinician is looking for a reproducible change outside that person’s expected pattern, not simply for any detectable result.
Postmenopausal interpretation is often cleaner. Once natural follicular activity has ended, inhibin B should be low. This is why studies of postmenopausal patients have been able to evaluate relatively low cutoffs for recurrence. Even then, a laboratory-specific range and the patient’s previous trend remain more important than adopting one published threshold without context.
Tumor marker results can also be affected by treatment timing. A sample obtained immediately after surgery may not represent the final nadir because circulating hormone needs time to decline. Conversely, a marker checked many months apart can miss the shape of a gradual rise. The treating team chooses the testing interval based on stage, recurrence risk, symptoms, and prior marker behavior.
How the Test Is Performed
Inhibin B is measured from a venous blood sample. Most laboratories test serum using an enzyme-linked immunoassay or another immunometric method. The blood draw itself takes only a few minutes.
Fasting is usually not required. If several tests are ordered at the same time, follow any preparation instructions for those tests. Patients should not stop prescribed hormones or other medicines unless their clinician specifically tells them to do so.
For the most useful interpretation, the clinician should know:
- Whether the patient is premenopausal, perimenopausal, or postmenopausal
- Menstrual-cycle timing if relevant
- Whether one or both ovaries have been removed
- Whether the patient is pregnant or undergoing fertility treatment
- The date and treatment status of any known granulosa cell tumor
- Previous inhibin B values and which laboratory performed them
Consistency is especially important for serial monitoring. Tumor marker values can shift when laboratories use different assays, calibration systems, or reference intervals. Whenever practical, long-term follow-up is easier to interpret when the same laboratory method is used.
An unexpected result that conflicts with the rest of the clinical picture may need confirmation. Immunoassays can rarely be affected by heterophile antibodies or other interfering substances. Laboratories can sometimes perform dilution studies, blocking procedures, or testing with another method when interference is suspected.
Granulosa Cell Tumors and Inhibin B
Granulosa cell tumors arise from ovarian sex cord-stromal cells and make up a small fraction of ovarian malignancies. The adult type is far more common than the juvenile type. Most adult granulosa cell tumors are diagnosed at an early stage, but they have a distinctive tendency to recur late.
Pathology establishes the diagnosis. Adult granulosa cell tumors often show a characteristic FOXL2 mutation, and pathologists use morphology, immunohistochemistry, and sometimes molecular testing to separate them from other ovarian tumors. Inhibin B supports the clinical assessment but cannot replace tissue diagnosis.
Among serum markers, inhibin B has strong evidence for granulosa cell tumors. Older cohort data found it elevated in about 89% of patients at diagnosis and about 85% at recurrence, compared with lower rates for inhibin A. Current laboratory references cite elevation in roughly 89% to 100% of granulosa cell tumors, depending on the population and assay.
Those percentages do not mean the test has 100% diagnostic accuracy. Study populations are often small because the disease is rare, and a marker can be elevated in conditions other than granulosa cell tumor. More importantly, an individual patient’s tumor may not secrete inhibin B at all.
The most clinically useful pattern is therefore patient-specific:
- Inhibin B is elevated when active tumor is present.
- The value drops after effective treatment.
- The patient reaches a stable post-treatment baseline.
- A later sustained rise is evaluated for recurrent disease.
This pattern turns inhibin B from a nonspecific laboratory value into a personalized surveillance marker.
Recurrence and Long-Term Monitoring
Granulosa cell tumors require unusually long follow-up because recurrence can occur many years after the first diagnosis. Serum inhibin B is valuable in this setting because biochemical changes may appear before a recurrence becomes obvious on examination or imaging.
A study of postmenopausal patients found that an inhibin B cutoff of 7 pg/mL was strongly associated with the presence or absence of recurrent disease, with high sensitivity and good specificity in that specific cohort. The researchers also found that higher levels were associated with a greater probability of an abnormal CT scan. Those numbers are useful research findings, but they should not be treated as universal cutoffs for every patient or laboratory.
Other cohort work has shown that rising inhibin B can precede recognized recurrence by months. That lead time can be clinically useful, especially if it prompts imaging while disease burden is still limited. However, not every rise means recurrence, and not every recurrence causes a measurable increase.
A typical follow-up strategy may combine:
- Clinical history and pelvic examination
- Serial inhibin B if it was informative at baseline
- AMH when useful
- Imaging based on stage, symptoms, marker trends, and the treating team’s surveillance plan
- Long-term follow-up rather than stopping surveillance after only a few years
A marker should not be the sole trigger for major treatment decisions. If a result rises, clinicians often confirm the trend and correlate it with imaging. If the marker remains normal but symptoms such as new pelvic pain, abdominal enlargement, unexplained bleeding, or early satiety develop, evaluation should proceed anyway.
The reverse situation matters too: imaging can detect recurrence while inhibin B remains normal. This is most likely when the tumor was never a strong inhibin B producer or when recurrent tumor biology has changed. For that reason, surveillance plans are not usually reduced to blood testing alone. Clinical review and appropriate imaging remain part of long-term care.
When a rise is confirmed, the next step is often targeted rather than automatic. The clinician may repeat inhibin B in the same laboratory, add AMH, review prior scans, and then choose ultrasound, CT, or MRI based on where recurrence is most likely and what symptoms are present. The goal is to use the marker to make imaging more informative, not to let the marker substitute for imaging.
Treatment can also change the marker. Falling inhibin B during therapy may support a response, whereas a consistent rise may suggest progression. Imaging remains necessary because the blood level cannot show where disease is located or whether a lesion is technically resectable.
Inhibin B vs. Other Tumor Markers
Inhibin B is often the most informative inhibin marker for granulosa cell tumors, but it works best as part of a broader clinical picture.
| Marker | Strength | Main limitation |
|---|---|---|
| Inhibin B | Frequently elevated in granulosa cell tumors and useful for recurrence monitoring | Varies with ovarian function and is not tumor-specific |
| AMH | Useful granulosa-cell marker with similar monitoring performance in several studies | Influenced by ovarian reserve in reproductive-age patients |
| Inhibin A | Can support diagnosis and monitoring when elevated at baseline | Elevated in fewer granulosa cell tumors than inhibin B in many cohorts |
| Estradiol | May reflect hormone production and explain estrogenic symptoms | Does not consistently track tumor burden |
| CA-125 | Useful in many epithelial ovarian cancer settings | Not a specific marker for granulosa cell tumors |
For a patient with an adnexal mass, the CA-125 blood test may be part of the evaluation, but a normal or high CA-125 does not answer the same question as inhibin B. Likewise, a multivariable ovarian mass assessment such as the OVA1 test is designed for a different clinical purpose and does not replace granulosa-cell markers.
When looking at a result, focus on five points: the laboratory’s reference interval, menopausal or menstrual status, whether the tumor previously secreted inhibin B, the direction of the serial trend, and whether symptoms or imaging support the same conclusion. That approach is far more reliable than treating one cutoff as a diagnosis.
References
- Cancer of the ovary, fallopian tube, and peritoneum: 2025 update 2025 (Review)
- Advanced Granulosa Cell Tumors of the Ovary: A Review with a Focus on Current and Novel Therapeutic Approaches 2024 (Review)
- Adult-type granulosa cell tumor of the ovary 2022 (Review)
- Recurrent Granulosa Cell Tumor in a Postmenopausal Woman: A Case Report and Literature Review 2023 (Review)
- INHAB – Overview: Inhibin A and B, Tumor Marker, Serum 2026
- Role of inhibin B in detecting recurrence of granulosa cell tumors of the ovary in postmenopausal patients 2021
Disclaimer
This article provides general information about inhibin B testing and cannot diagnose or exclude a granulosa cell tumor. Results depend on reproductive status, assay method, tumor biology, and the clinical setting, so they should be interpreted with pathology, imaging, and other markers. Contact the treating clinician about a sustained marker rise, new pelvic or abdominal symptoms, or abnormal bleeding during follow-up.