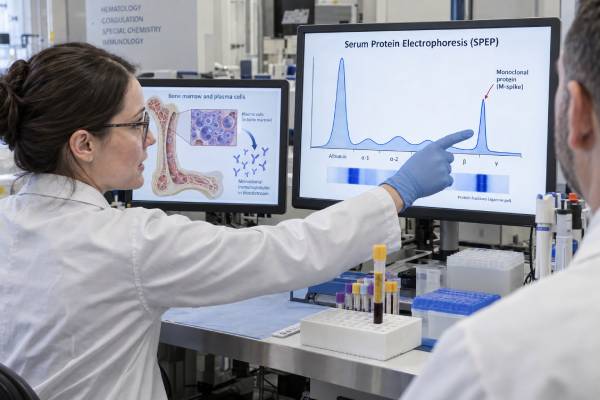
An M protein blood test looks for a monoclonal immunoglobulin made by one clone of plasma cells or B cells. The abnormal protein is also called a monoclonal protein, M-spike, paraprotein, or monoclonal gammopathy. It is most often detected and measured with serum protein electrophoresis (SPEP), then characterized with immunofixation and serum free light-chain testing. Finding an M protein does not automatically mean multiple myeloma. Small monoclonal proteins are common in monoclonal gammopathy of undetermined significance (MGUS), especially in older adults, and they can also occur with smoldering myeloma, Waldenström macroglobulinemia, AL amyloidosis, and other clonal disorders. Doctors interpret the amount and type of M protein together with the free light-chain ratio, blood counts, kidney function, calcium, symptoms, imaging, and sometimes bone marrow results. In a person with known myeloma, the M protein can be a useful marker of treatment response and relapse, but some myelomas make little or no measurable M protein.
- What it measures: SPEP detects and often quantifies a monoclonal protein, usually reported in g/dL; immunofixation identifies its immunoglobulin type.
- A positive M protein is not automatically cancer: MGUS is a common non-cancerous precursor state, while larger or changing M proteins may require evaluation for myeloma or related disorders.
- Measurable myeloma protein: Current myeloma reviews commonly define measurable serum M protein as at least 1 g/dL and urine M protein as at least 200 mg per 24 hours for response monitoring.
- Normal SPEP does not exclude myeloma: Light-chain-only and rare nonsecretory forms may require serum free light chains, immunofixation, urine studies, imaging, and bone marrow testing.
- The trend matters: In known secretory myeloma, a falling M protein usually supports response, while a confirmed rise can signal relapse or progression.
Table of Contents
- What M Protein Is
- How M Protein Is Tested
- Understanding M Protein Results
- M Protein and Multiple Myeloma
- Other Causes of a Monoclonal Protein
- Monitoring M Protein Over Time
- What to Do After an Abnormal Result
What M Protein Is
M protein is an abnormal immunoglobulin produced by a single clone of plasma cells or, in some disorders, another mature B-cell population. Normal immune cells make many different antibodies, creating a broad polyclonal mixture. A clonal population makes large numbers of identical or nearly identical immunoglobulin molecules, creating a narrow monoclonal pattern.
An intact immunoglobulin has a heavy chain—usually IgG, IgA, or IgM—and a light chain, either kappa or lambda. A report may therefore describe an IgG kappa, IgA lambda, or IgM kappa monoclonal protein. Some plasma-cell disorders make mainly free light chains rather than complete immunoglobulins.
“M protein” is a category, not one specific cancer marker. The same laboratory finding can occur across a spectrum from a low-risk precursor condition to active malignancy. The quantity, immunoglobulin type, free light-chain pattern, bone marrow findings, organ effects, and change over time determine its significance.
The M protein itself can sometimes cause organ damage even when the clonal cell population is small. Certain monoclonal proteins can injure kidneys, nerves, skin, or other tissues, or form amyloid deposits. This is why a small M-spike is not always clinically insignificant.
How M Protein Is Tested
There is no single test called “the M protein test” in every laboratory. Clinicians usually use a group of complementary tests.
Serum protein electrophoresis
Serum protein electrophoresis (SPEP) separates blood proteins into fractions. A monoclonal immunoglobulin often appears as a narrow spike, usually in the gamma region but sometimes in the beta region. The laboratory can estimate the concentration of a measurable spike, commonly in g/dL.
SPEP is good at quantifying a clearly visible M protein but is less sensitive for very small proteins and free light chains.
Immunofixation
Serum immunofixation is more sensitive for small monoclonal proteins and identifies the heavy-chain and light-chain type. It is mainly qualitative rather than the preferred method for measuring the size of an M-spike.
Serum free light chains
The serum free light-chain test measures free kappa and lambda chains and calculates their ratio. It is especially important when a plasma-cell disorder produces mostly light chains that may not form a clear SPEP spike.
Urine testing
Monoclonal free light chains can pass into urine. A 24-hour urine protein electrophoresis test with immunofixation may be used in diagnosis or follow-up, depending on the disorder and clinical setting.
Using SPEP, immunofixation, and free light chains together detects substantially more monoclonal gammopathies than SPEP alone.
Understanding M Protein Results
M protein results are best interpreted by answering four questions: Is a monoclonal protein present? How much is present? What immunoglobulin type is it? Are there signs that the clonal process is causing organ damage or meeting criteria for a malignancy?
| Result | General meaning | Important next context |
|---|---|---|
| No M-spike on SPEP | No clearly measurable monoclonal spike | Small or light-chain-only disease can still be present |
| Small M protein | Often compatible with MGUS, but not diagnostic by size alone | Immunofixation type, FLC ratio, blood counts, kidney function, calcium |
| Larger M protein | Raises concern for greater clonal burden | Assess for smoldering or active myeloma and related disorders |
| Rising M protein | Can indicate increasing clonal activity | Confirm trend and compare with disease-specific response criteria |
| Falling M protein during therapy | Often supports treatment response | Depth of response also depends on immunofixation, FLC, marrow, and imaging |
There is no universal M protein value that proves multiple myeloma. A person may have a measurable monoclonal protein and never develop myeloma, while another person can have clinically important myeloma with only a small spike.
For treatment-response purposes, contemporary myeloma reviews often define a measurable serum M protein as at least 1 g/dL or a measurable urine M protein as at least 200 mg per 24 hours. These are response-assessment thresholds, not diagnostic cutoffs.
The exact measurement can also be technically difficult when an IgA protein migrates in the beta region, when several proteins overlap, or when therapeutic monoclonal antibodies appear on electrophoresis. In specialized settings, mass spectrometry can help separate treatment-related antibodies from the patient’s own monoclonal protein.
M Protein and Multiple Myeloma
Most patients with multiple myeloma produce a detectable monoclonal immunoglobulin or free light chain, but an M protein is only one part of the diagnosis. Active myeloma requires evidence of a clonal plasma-cell disorder plus one or more myeloma-defining events.
Classic myeloma-related organ injury is often summarized as CRAB:
- C: Hypercalcemia
- R: Renal impairment
- A: Anemia
- B: Bone lesions
Modern diagnostic criteria also include certain biomarkers that identify an extremely high risk of progression even before classic CRAB damage develops, such as very high bone marrow clonal plasma-cell percentage, a markedly abnormal involved-to-uninvolved free light-chain ratio meeting specified conditions, or more than one focal lesion on MRI.
This explains why the size of an M-spike cannot diagnose or stage myeloma by itself. A patient with a 2 g/dL M protein might have MGUS, smoldering myeloma, or active myeloma depending on marrow and organ findings.
A multiple myeloma test panel therefore includes monoclonal protein studies alongside blood counts, creatinine, calcium, imaging, and usually bone marrow evaluation when indicated.
What if there is no M protein?
A normal SPEP does not exclude myeloma. Light-chain myeloma may produce free light chains that are rapidly cleared from the blood and do not create a large spike. Serum free light-chain testing and urine studies improve detection.
True nonsecretory myeloma is uncommon, representing only a small percentage of modern myeloma cases. These patients have no measurable monoclonal protein in serum or urine and may also lack an abnormal serum free light-chain signal. Diagnosis then depends heavily on bone marrow, imaging, and clinical findings.
The distinction among MGUS, smoldering multiple myeloma, and active multiple myeloma illustrates why M protein quantity cannot be read in isolation. MGUS generally involves a smaller clonal burden and no myeloma-defining organ injury or biomarker event. Smoldering myeloma has a higher clonal burden than MGUS but still lacks a myeloma-defining event. Active myeloma is diagnosed when the plasma-cell disorder has caused qualifying organ damage or meets a validated myeloma-defining biomarker threshold. The M-spike contributes to this assessment, but it does not make the diagnosis by itself.
Risk also depends on the type of monoclonal protein. IgM monoclonal proteins often lead clinicians to consider lymphoplasmacytic disorders such as Waldenström macroglobulinemia, while IgG or IgA proteins are more typical of plasma-cell gammopathies. An abnormal serum free light-chain ratio adds another dimension because it can signal clonal light-chain production even when the intact immunoglobulin M-spike is small.
Kidney injury deserves particular attention. Monoclonal free light chains can damage renal tubules or deposit in kidney tissue, and a small circulating M protein can occasionally be associated with clinically important monoclonal gammopathy of renal significance. A creatinine rise, new proteinuria, or unexplained decline in kidney function should therefore not be dismissed simply because the M-spike is modest.
The report may also show a polyclonal increase rather than a monoclonal spike. A broad-based rise in the gamma region is more often associated with inflammation, infection, liver disease, or immune activation. Immunofixation helps distinguish this broad polyclonal pattern from a discrete clonal immunoglobulin.
Other Causes of a Monoclonal Protein
A monoclonal protein can occur in several disorders other than active multiple myeloma.
MGUS is the most common. It is an asymptomatic precursor condition with a clonal immunoglobulin but without myeloma-defining organ damage or other criteria for an overt lymphoid malignancy. Many people with MGUS never progress, but follow-up is recommended because risk persists over time.
Smoldering multiple myeloma has a larger plasma-cell or M-protein burden than MGUS but lacks active myeloma-defining events. Its progression risk is higher than MGUS and varies substantially by risk factors.
Waldenström macroglobulinemia is a lymphoplasmacytic lymphoma that usually produces an IgM monoclonal protein. IgM MGUS can precede it.
AL amyloidosis results when a clonal plasma-cell population produces abnormal light chains that misfold and deposit in organs. The circulating monoclonal protein can be very small, so serum and urine immunofixation plus serum free light chains are important.
Monoclonal gammopathy of clinical significance describes situations in which a relatively small clone causes organ injury, such as certain kidney or nerve disorders, despite not meeting conventional myeloma or lymphoma criteria.
Transient or low-level bands can occasionally appear in other settings, and therapeutic monoclonal antibodies can mimic an M protein on laboratory testing. The patient’s medication list matters when interpreting a new band during cancer treatment.
M protein can also matter when the clone causes problems that do not fit classic myeloma. AL amyloidosis may involve a small plasma-cell clone but produce light chains that form amyloid deposits in the heart, kidneys, nerves, liver, or other tissues. Other monoclonal gammopathies can damage kidneys or nerves through antibody activity or protein deposition. In these disorders, the clinical effect of the protein can be more important than the size of the SPEP spike.
For that reason, symptoms and organ findings should shape the workup. Unexplained nephrotic-range protein loss, restrictive cardiomyopathy, peripheral neuropathy, enlarged tongue, easy bruising, or unexplained autonomic symptoms can prompt testing beyond a routine SPEP. The goal is to identify whether the monoclonal protein is merely present or is biologically responsible for disease.
Monitoring M Protein Over Time
In secretory multiple myeloma, the M protein is one of the most practical markers for following treatment. If the tumor clone produces a measurable immunoglobulin, its concentration often falls as treatment reduces the number of malignant plasma cells.
Response categories use standardized criteria rather than a simple “lower is better” rule. The percentage reduction in serum or urine M protein, disappearance on immunofixation, free light-chain results, bone marrow findings, and sometimes imaging all contribute to defining partial response, very good partial response, complete response, and deeper states.
A confirmed increase after response can indicate biochemical relapse or progression, but the clinical meaning depends on the amount of rise and disease-specific criteria. Doctors also look for new anemia, kidney injury, high calcium, bone lesions, symptoms, or other evidence of clinical progression.
M protein is less useful as disease becomes very small because conventional electrophoresis has limited sensitivity. More sensitive bone marrow minimal residual disease methods and emerging mass-spectrometry blood tests can detect disease below the level of standard SPEP and immunofixation.
Serial tests should ideally use the same laboratory and method. Switching techniques can create apparent changes that reflect assay differences rather than biology.
The type of measurable protein can also change what is followed. A patient with a clear intact-immunoglobulin M-spike may be monitored mainly with SPEP, while a patient whose disease produces predominantly free light chains may need the free light-chain assay to carry more of the monitoring burden. Urine studies remain useful in selected patients, especially when light-chain excretion or kidney involvement is a concern. This is why two people with multiple myeloma may have different-looking laboratory follow-up plans even when both are responding well.
Treatment itself can complicate interpretation. Some therapeutic monoclonal antibodies can appear as small bands in the same region assessed by electrophoresis or immunofixation. Laboratories and treating teams may use the medication history, band location, specialized methods, or follow-up patterns to distinguish a drug-related band from the patient’s original clone. A new faint band during therapy therefore does not automatically mean relapse.
What to Do After an Abnormal Result
A newly detected M protein usually leads to risk assessment rather than an immediate cancer diagnosis. The clinician may order or review:
- SPEP quantification and serum immunofixation
- Serum free kappa and lambda light chains with ratio
- Quantitative immunoglobulin levels
- Complete blood count
- Creatinine or estimated kidney function
- Serum calcium and albumin
- Urine protein studies when indicated
- Imaging and bone marrow testing when the risk profile or symptoms justify them
Referral to hematology is common when the M protein is clearly monoclonal, the amount is substantial, the free light-chain ratio is significantly abnormal, or there are concerning symptoms or laboratory abnormalities.
Symptoms that deserve prompt evaluation include new severe or persistent bone pain, unexplained fractures, worsening weakness, shortness of breath from significant anemia, confusion or dehydration with high calcium, reduced urine output, or rapidly declining kidney function.
For a small incidental M protein with otherwise reassuring findings, the outcome may simply be MGUS with periodic follow-up. The useful questions to ask are: What type of M protein do I have? How large is it? Is my free light-chain ratio abnormal? Are my hemoglobin, calcium, and kidney function normal? Do I need imaging or bone marrow testing? And when should the laboratory studies be repeated?
References
- Multiple Myeloma: 2024 update on Diagnosis, Risk-stratification and Management 2024 (Review)
- Diagnosis and Management of Monoclonal Gammopathy of Undetermined Significance: A Review 2025 (Review)
- Multiple Myeloma: A Structured and Multidisciplinary Approach to Diagnosis 2026 (Review)
- Recent Updates in the Diagnosis and Management of Kidney Diseases in Multiple Myeloma 2024 (Review)
- Advances in multiple myeloma blood-based monitoring and its clinical applications 2025 (Review)
- Interference of therapeutic monoclonal antibodies with electrophoresis and immunofixation of serum proteins: state of knowledge and systematic review 2025 (Systematic Review)
Disclaimer
This article provides general information about M protein testing and does not diagnose MGUS, multiple myeloma, or another plasma-cell disorder. Monoclonal protein results must be interpreted with free light chains, blood counts, kidney function, calcium, symptoms, imaging, and sometimes bone marrow testing. Seek timely medical review for significant bone pain, fractures, worsening anemia, kidney dysfunction, confusion, or other concerning symptoms.