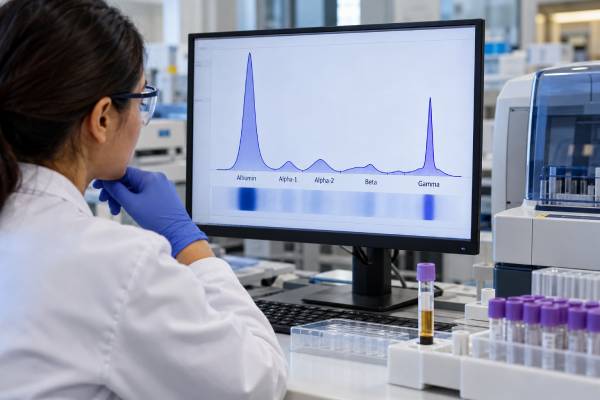
Serum protein electrophoresis, or SPEP, separates proteins in blood into recognizable fractions and can reveal a monoclonal protein, often called an M protein, M spike, or paraprotein. The test is widely used when doctors are evaluating multiple myeloma, monoclonal gammopathy of undetermined significance (MGUS), smoldering myeloma, Waldenström macroglobulinemia, AL amyloidosis, and other conditions that produce abnormal immunoglobulins. A sharp restricted peak is more suspicious for a monoclonal gammopathy than a broad increase caused by inflammation, but SPEP alone cannot identify the exact immunoglobulin type or determine whether a person has cancer. The size and location of the peak also matter: some M proteins are too small to quantify, some migrate in the beta region, and light-chain disease can produce little or no visible M spike. For that reason, SPEP is usually interpreted with serum immunofixation, serum free light chains, quantitative immunoglobulins, blood counts, kidney function, calcium, and the clinical picture.
- An M spike on SPEP means a restricted protein is present and should be characterized, usually with serum immunofixation; it is not automatically a myeloma diagnosis.
- M-protein concentration is commonly reported in g/dL or g/L, and serial change is often more useful than a single value when monitoring known disease.
- A normal SPEP does not exclude myeloma, especially light-chain, low-secretory, or nonsecretory disease.
- Broad gamma-region elevation is usually polyclonal rather than monoclonal and can occur with infection, inflammation, autoimmune disease, or liver disease.
- No fasting is usually needed for routine SPEP, although the laboratory’s collection instructions should be followed.
Table of Contents
- What SPEP Measures
- Why SPEP Is Ordered
- How to Read an SPEP Report
- M Spike Meaning and Amount
- SPEP in MGUS, Smoldering Myeloma, and Myeloma
- Limits and Common Pitfalls
- Monitoring and Next Steps
What SPEP Measures
SPEP separates serum proteins according to their physical properties. The result is displayed as bands on a gel or as an electropherogram with several major fractions: albumin, alpha-1, alpha-2, beta, and gamma. Albumin normally forms the largest peak. Most immunoglobulins migrate in the gamma region, although some—especially IgA monoclonal proteins—can migrate in the beta region.
The test is designed to recognize patterns rather than one single chemical. In a healthy polyclonal immune system, many different antibodies create a broad gamma region. When one plasma-cell or B-cell clone makes large amounts of one immunoglobulin, that protein may produce a narrow, sharp peak. Laboratories often call this an M spike or monoclonal peak.
SPEP can do two important things:
- detect a suspicious restricted protein pattern; and
- estimate the concentration of a measurable M protein by integrating the area under the peak and relating it to total serum protein.
SPEP does not determine the heavy-chain and light-chain identity by itself. A suspicious band is typically characterized with a serum immunofixation test, which can identify patterns such as IgG-kappa or IgA-lambda. Serum free light chain testing adds sensitivity when the clonal protein consists mainly of unbound kappa or lambda chains.
The exact appearance depends on the instrument and method. Laboratories may use agarose gel electrophoresis or capillary zone electrophoresis. Reference ranges for the protein fractions also vary, so the report’s own intervals should be used rather than applying a universal set of numbers.
Why SPEP Is Ordered
SPEP is commonly ordered when symptoms or routine laboratory findings suggest a plasma cell or other monoclonal gammopathy. The test may also be part of ongoing follow-up after an M protein has already been identified.
Reasons for an initial SPEP can include unexplained anemia, bone pain, recurrent fractures, high calcium, reduced kidney function, elevated total protein, unexplained neuropathy, recurrent infections, or a high globulin level. It may also be used in the evaluation of suspected AL amyloidosis or a monoclonal protein that may be damaging the kidneys, nerves, skin, or other organs.
SPEP is only one component of a sensitive screening strategy. A multiple myeloma test panel commonly combines SPEP with serum immunofixation and serum free light chains. That combination matters because not every clinically important clone produces a large intact immunoglobulin peak.
The test is also useful after diagnosis because a measurable M protein can act as a disease marker. If treatment is working, the M-protein concentration usually falls. If the same protein begins rising again, it may signal biochemical progression before symptoms change. However, clinicians use formal response criteria and the full clinical picture rather than judging response from one SPEP value.
Preparation is simple. SPEP generally requires only a standard venous blood sample and usually does not require fasting. Severe lipemia, recent infusions, or therapeutic monoclonal antibodies can sometimes complicate patterns, so medication and treatment history should be available to the interpreting team.
How to Read an SPEP Report
An SPEP report may list each protein fraction, the total protein, a descriptive interpretation, and—when present—the amount of a monoclonal peak. The report may use g/dL or g/L, so units must be checked before comparing values.
| Pattern | Typical appearance | Common interpretation |
|---|---|---|
| Normal pattern | Expected albumin and globulin fractions without a restricted peak | No obvious serum M spike, though low-level or light-chain disease can still be present |
| Monoclonal peak | Narrow, sharp restricted peak, often in gamma or beta region | Possible monoclonal gammopathy; confirm/type with immunofixation |
| Polyclonal hypergammaglobulinemia | Broad-based gamma elevation | Often infection, inflammation, autoimmune disease, or liver disease |
| Hypogammaglobulinemia | Reduced gamma fraction | Reduced immunoglobulins; can have immune, treatment-related, or hematologic causes |
| Beta-region restriction | Abnormal narrow feature among beta proteins | Can represent an M protein, often requiring immunofixation because quantification is harder |
A report may say “restricted band,” “possible monoclonal protein,” or “M spike too small to quantify.” These phrases do not all mean the same thing. “Too small to quantify” generally means the laboratory can see a suspicious or confirmed component but cannot measure it reliably enough to give a precise concentration.
The gamma fraction itself is not equivalent to the M protein. It contains a mixture of immunoglobulins, and some M proteins migrate outside it. Likewise, a high total protein does not prove monoclonality. Dehydration and polyclonal immune activation can raise total protein without a clonal plasma-cell disorder.
M Spike Meaning and Amount
An M spike represents a concentration of electrophoretically similar monoclonal protein. The amount is clinically useful, but there is no single M-spike cutoff that separates “benign” from “cancer.” The same value can have different implications depending on bone marrow findings, free light chains, symptoms, organ function, imaging, and whether the level is stable or changing.
For a clearly measurable peak, the laboratory commonly reports the M protein in g/dL or g/L. Because 1 g/dL equals 10 g/L, a result of 1.5 g/dL is the same concentration as 15 g/L. Comparing values requires consistent units and, ideally, the same laboratory method.
The location matters. A classic IgG M protein often appears in the gamma region and can be measured relatively cleanly. IgA frequently migrates in the beta region, where transferrin and complement proteins also occur. That overlap can make direct densitometric measurement less reliable. In such cases, the laboratory may use alternative approaches or the clinician may follow quantitative immunoglobulin levels as additional context.
Very small peaks also create uncertainty because analytical variation becomes more important near the detection and quantification limits. A change from “faint band” to “0.1 g/dL” is not necessarily a major biological change unless the full serial pattern supports it.
When monitoring a known M protein, the questions that matter most are:
- Is this the same monoclonal protein as before?
- Is the concentration rising, falling, or stable over repeated measurements?
- Are serum free light chains moving in the same direction?
- Are hemoglobin, calcium, kidney function, symptoms, or imaging changing?
- Has treatment introduced a drug-related band that can mimic the patient’s protein?
This trend-based approach reduces overreaction to small fluctuations and helps connect the laboratory marker with actual disease activity.
SPEP in MGUS, Smoldering Myeloma, and Myeloma
SPEP can detect an M protein in several conditions, and the diagnosis depends on more than the electrophoresis pattern.
MGUS is a precursor condition in which a monoclonal protein is present but the person does not meet criteria for multiple myeloma or another related malignancy. MGUS becomes more common with age. Many people remain stable for years, but follow-up is recommended because some cases progress. Risk assessment considers the M-protein amount, immunoglobulin type, free light chain ratio, and other factors.
Smoldering multiple myeloma has a greater clonal plasma-cell burden than MGUS but no myeloma-defining event requiring treatment. SPEP is useful for following a measurable M protein over time, while bone marrow findings and additional biomarkers determine risk and diagnosis.
Active multiple myeloma is diagnosed when a clonal plasma-cell disorder is accompanied by myeloma-defining events. These can include organ damage such as hypercalcemia, renal impairment, anemia, or bone lesions, as well as specific validated biomarkers of near-term progression. A large M spike can support the workup but is neither required nor sufficient by itself.
Light-chain myeloma illustrates SPEP’s limitation. A patient can have substantial clonal free light chain production with little or no intact immunoglobulin peak. The serum free light chain test is therefore important when SPEP is unrevealing but clinical suspicion remains.
AL amyloidosis can also involve a small M protein despite serious organ disease. In this setting, the clinical impact of the clone is more important than the size of the SPEP peak. A faint monoclonal component should not be dismissed when there are compatible heart, kidney, nerve, gastrointestinal, or soft-tissue findings.
Limits and Common Pitfalls
SPEP is useful because it combines pattern recognition with M-protein quantification, but it has important blind spots.
A normal SPEP does not exclude a plasma cell disorder. Low-level monoclonal proteins, pure light-chain disease, and nonsecretory myeloma can escape detection. Serum immunofixation and free light chain analysis increase sensitivity, and urine studies may be useful in selected cases.
Not every narrow feature is a malignant M protein. Fibrinogen from an incompletely clotted specimen, hemolysis-related changes, radiographic contrast, some medications, and therapeutic monoclonal antibodies can create unusual peaks or bands. Laboratories use pattern location, clinical information, immunofixation, and repeat testing to resolve uncertain findings.
Treatment antibodies can mimic disease. Daratumumab and isatuximab are monoclonal immunoglobulins and may appear on SPEP/IFE. This can complicate assessment of complete response, especially when the patient’s original protein is also IgG-kappa. Drug-specific assays or mass spectrometry may help distinguish the signals.
Inter-method variation matters. Agarose and capillary methods may not measure a small or beta-migrating M protein identically. Serial monitoring is easier when the same laboratory and platform are used.
Inflammation can look dramatic without being monoclonal. A broad polyclonal gamma increase can be substantial in autoimmune disease, chronic infection, or liver disease. Immunofixation is useful when the pattern is uncertain.
Mass spectrometry is becoming an important complementary or alternative approach in some centers. It can detect lower-level monoclonal proteins than conventional SPEP/IFE and can sometimes distinguish therapeutic antibodies from endogenous M proteins. It does not eliminate the need for clinical interpretation or bone marrow MRD testing when those are indicated.
Monitoring and Next Steps
What happens after SPEP depends on whether the result is normal, newly abnormal, or part of follow-up for known disease.
For a new M spike, clinicians usually confirm the isotype with immunofixation and obtain serum free light chains. They also review complete blood count, creatinine or eGFR, calcium, albumin, quantitative immunoglobulins, symptoms, and prior values. Depending on the findings, urine protein studies, bone marrow biopsy, and skeletal imaging may follow.
If MGUS is diagnosed, the first goal is to define risk rather than to treat the SPEP number. A repeat assessment is often performed to establish stability. Longer-term follow-up then depends on risk category, age, health, and symptoms. A stable low-risk M protein may need relatively infrequent monitoring; a higher-risk pattern requires closer review.
During myeloma treatment, clinicians usually track the same measurable marker at regular intervals. A falling M spike supports response, while a confirmed rise can meet biochemical progression criteria depending on the magnitude and context. In light-chain or oligosecretory disease, free light chains may be the more informative blood marker. Deep response may also be assessed with myeloma MRD testing, which measures residual clonal cells at a sensitivity far beyond routine SPEP.
Seek timely medical review rather than waiting for the next routine SPEP if new symptoms suggest organ complications—for example, severe or focal bone pain, a suspected fracture, increasing weakness or breathlessness, confusion, significant dehydration, markedly reduced urine output, or symptoms associated with high calcium. The M-protein trend is valuable, but it is only one part of deciding how active a plasma cell disorder is and whether treatment is needed.
SPEP can also show changes in proteins that are not the M spike. Albumin may fall with inflammation, liver disease, kidney protein loss, or poor nutrition. Alpha fractions can rise during acute inflammation. A low gamma region may reflect reduced normal immunoglobulins, which is common in some plasma-cell and lymphoid disorders. These background patterns can help explain the report but should not be mistaken for direct measurements of the malignant clone.
A particularly important monitoring issue is immunoparesis, the suppression of normal uninvolved immunoglobulins. A patient with an IgG monoclonal protein may have low IgA and IgM, for example. SPEP can suggest this through a reduced background gamma region, while quantitative immunoglobulins measure it more directly. Immunoparesis can contribute to infection risk and is part of the broader disease picture even though it is not the M spike itself.
Small serial changes should be interpreted cautiously. Hydration, laboratory variation, a beta-migrating protein, and the exact way the peak is integrated can all affect a low-level measurement. Formal myeloma response and progression criteria use specified absolute and relative changes rather than any upward movement. When a previously stable M spike rises, clinicians usually confirm the trend and check free light chains, blood counts, calcium, creatinine, and symptoms before concluding that treatment needs to change.
SPEP is also not designed to screen the general population for myeloma without a clinical reason. Because MGUS becomes common with age, indiscriminate testing can identify small stable M proteins that require follow-up but never cause disease. Testing has the highest value when symptoms, laboratory abnormalities, or a known monoclonal gammopathy create a clear clinical question.
When an M protein is first found, the clinician may repeat SPEP after a defined interval to establish whether it is stable. A true rising trend over several measurements carries more weight than one isolated difference between laboratories. Keeping units consistent and noting whether the sample was analyzed on the same platform makes those comparisons more reliable.
References
- Recommendations for the study of monoclonal gammopathies in the clinical laboratory. A consensus of the Spanish Society of Laboratory Medicine and the Spanish Society of Hematology and Hemotherapy. Part I: Update on laboratory tests for the study of monoclonal gammopathies 2023 (Consensus)
- A review of clinical guidelines, laboratory recommendations and external quality assurance programs for monoclonal gammopathy testing 2023 (Review)
- Multiple Myeloma: A Structured and Multidisciplinary Approach to Diagnosis 2026 (Review)
- Unraveling the Possibilities of Monoclonal Protein Migration, Identification, and Characterization in SPEP on Capillary Zone Electrophoresis 2022
- Impact of M-protein detection on the response evaluations of patients undergoing treatment with the IgG-κ monoclonal antibodies daratumumab or isatuximab, and discrepancies between immunofixation electrophoresis (IFE) systems and reagents 2024
- Clinical applications of mass spectrometry in multiple myeloma 2025 (Review)
Disclaimer
SPEP is a laboratory tool, not a stand-alone diagnosis. M-protein results need interpretation with immunofixation, free light chains, blood counts, kidney function, calcium, symptoms, imaging, and other findings when appropriate. Discuss a new or changing M spike with the clinician who can interpret it in your specific clinical context.