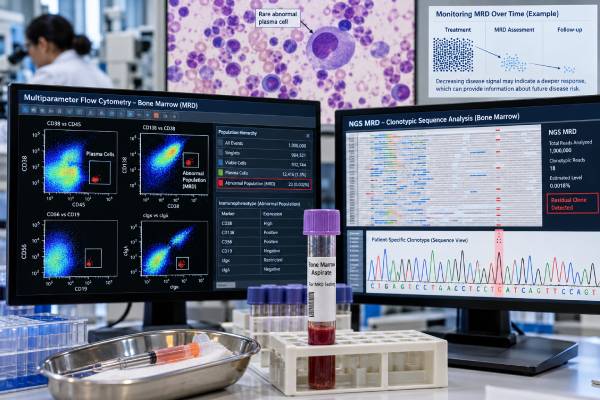
A measurable residual disease (MRD) test for multiple myeloma looks for very small numbers of abnormal plasma cells that remain after treatment, even when standard blood and urine tests show a deep response. MRD is usually assessed in bone marrow with next-generation flow cytometry or next-generation sequencing (NGS). These methods can detect approximately one myeloma cell among 100,000 cells and, in optimized assays, one among 1,000,000 cells. A negative result is associated with a lower risk of progression and longer survival than a positive result, but MRD does not by itself prove cure or determine exactly when an individual patient will relapse.
Myeloma is patchy in the marrow and can also exist outside the marrow, so an MRD result is only one part of response assessment. Clinicians combine it with M protein, immunofixation, serum free light chains, imaging, marrow findings, treatment history, and cytogenetic risk. The most informative result includes the method, assay sensitivity, specimen adequacy, and whether negativity is sustained on later testing.
- What it measures: Myeloma MRD detects residual clonal plasma cells in bone marrow after treatment using highly sensitive flow cytometry or NGS.
- What MRD negative means: No myeloma was found above the assay’s validated detection limit; this predicts better outcomes but does not guarantee that all disease is gone.
- What MRD positive means: Residual myeloma was detected; higher or rising levels generally indicate greater recurrence risk than sustained MRD negativity.
- Typical sensitivity: Validated marrow assays commonly target at least 10⁻⁵ sensitivity, and some reach 10⁻⁶ when enough high-quality cells or DNA are analyzed.
- Why repeat testing matters: Sustained MRD negativity over time is generally more informative than one isolated negative result.
Table of Contents
- What myeloma MRD measures
- MRD by flow cytometry
- MRD by next-generation sequencing
- MRD-negative and MRD-positive results
- When MRD is tested
- Recurrence risk and treatment decisions
- Limitations and practical questions
What myeloma MRD measures
MRD testing measures the depth of response beyond conventional complete response. Standard myeloma response testing may show no measurable M protein on electrophoresis, negative immunofixation, normalized free light chains, and fewer than 5% plasma cells by routine marrow examination. Even then, small numbers of clonal plasma cells can remain.
Highly sensitive MRD assays count or identify those cells. Sensitivity is expressed as a power of ten:
- 10⁻⁵ means the assay can detect roughly 1 abnormal cell among 100,000 cells under adequate conditions.
- 10⁻⁶ means roughly 1 abnormal cell among 1,000,000 cells.
The result is meaningful only if the specimen contains enough evaluable material. A laboratory cannot credibly claim 10⁻⁶ sensitivity if too few marrow cells or DNA molecules were available.
MRD is different from routine monoclonal protein monitoring. A multiple myeloma test panel evaluates the secreted protein produced by plasma cells and the clinical effects of disease. MRD directly searches for residual clonal plasma cells in marrow. These methods answer related but different questions.
Because myeloma can become oligosecretory or nonsecretory, deep marrow assessment may identify disease when the M protein is no longer informative. Conversely, serum markers may reveal progression between marrow assessments. That is why MRD does not replace serum free light-chain testing, SPEP, immunofixation, or imaging.
MRD by flow cytometry
Next-generation flow cytometry distinguishes normal plasma cells from myeloma plasma cells using combinations of surface and intracellular markers. Common panels examine CD38, CD138, CD45, CD19, CD56, CD27, CD81, CD117, cytoplasmic kappa and lambda, and additional markers selected by the laboratory.
Normal plasma cells have a recognizable range of antigen patterns. Myeloma plasma cells often show aberrancies such as loss of CD19, abnormal CD56 or CD117 expression, altered CD45 or CD81, and light-chain restriction. No single marker defines myeloma; the abnormal combination is what matters.
How sensitivity is achieved
High-sensitivity flow requires acquisition of a very large number of cells. A routine diagnostic flow panel that analyzes tens of thousands of cells is not automatically an MRD assay. MRD laboratories use standardized specimen preparation, optimized antibody panels, strict quality control, and acquisition of millions of events when feasible.
The report may state that MRD was not detected at a sensitivity of 10⁻⁵ or 10⁻⁶. If disease is detected, the laboratory may report a percentage, such as 0.003% clonal plasma cells. That equals 3 × 10⁻⁵, or approximately three abnormal cells per 100,000 analyzed cells.
Advantages of flow MRD
Flow cytometry is widely applicable because it does not require a stored diagnostic DNA sequence. It can also distinguish clonal plasma cells from normal plasma cells by phenotype and provides same-sample information about cell quality and marrow composition.
Flow-specific pitfalls
Bone marrow hemodilution is a major concern. The first aspirate pull generally contains the highest concentration of marrow particles; later pulls may be increasingly diluted with peripheral blood. A diluted specimen can contain too few plasma cells and produce an apparently negative result that is less reassuring.
Targeted therapy can also alter antigen expression. Anti-CD38 therapy, for example, can complicate CD38-based detection if the assay is not designed for treated patients. Experienced laboratories use alternative markers or validated strategies to avoid this problem.
MRD by next-generation sequencing
NGS MRD takes a molecular approach. It first identifies a unique immunoglobulin gene rearrangement associated with the patient’s myeloma clone, usually from a pretreatment blood or marrow specimen. Later samples are sequenced deeply to look for that same clonal sequence.
A clonal-sequence MRD test is one example of this strategy. The key advantage is specificity: once the patient-specific sequence is established, the assay searches for the same molecular fingerprint after treatment.
NGS can often reach 10⁻⁶ sensitivity if enough DNA is available. It also avoids some immunophenotypic changes caused by treatment because it tracks DNA rather than surface proteins.
When NGS cannot be used optimally
NGS usually requires a trackable baseline clone. In a minority of patients, the diagnostic sample may not yield an adequate clonotype, or no suitable pretreatment material may be available. DNA quantity and quality also matter.
NGS and flow can disagree. A sample may be NGS positive and flow negative because NGS reached greater sensitivity, because patchy disease was represented differently in the aliquots, or because one method encountered technical limitations. The reverse can also occur. Discordance should be interpreted in the context of the assay limits rather than assuming one result is automatically wrong.
| Feature | Next-generation flow | NGS |
|---|---|---|
| Target | Abnormal plasma-cell phenotype | Patient-specific clonal DNA sequence |
| Common specimen | Fresh bone marrow aspirate | Bone marrow DNA |
| Potential sensitivity | Often 10⁻⁵ to 10⁻⁶ | Often 10⁻⁵ to 10⁻⁶ |
| Needs baseline clone? | No molecular clonotype required | Usually yes |
| Main vulnerability | Cell viability, hemodilution, antigen changes | Baseline clonotype availability, DNA amount, sampling |
MRD-negative and MRD-positive results
MRD negative means the assay did not detect clonal myeloma above its validated limit of detection. It does not mean there are literally zero myeloma cells in the body. Disease may exist below the detection threshold, outside the sampled marrow area, or in an extramedullary site.
The phrase is therefore incomplete unless the sensitivity is stated. “MRD negative at 10⁻⁶” conveys a deeper tested response than “MRD negative at 10⁻⁴,” assuming both specimens were adequate.
MRD positive means residual clonal disease was detected. A positive result can range from a very small signal near the detection limit to a clearly quantifiable population. Prognosis is influenced by the level and trajectory, not just the word “positive.”
Why sustained MRD negativity matters
Myeloma can recur after an MRD-negative result, so repeated assessments provide more information. Sustained negativity—negative results at separated time points—indicates that deep disease control has persisted. Clinical studies consistently show that patients with sustained MRD negativity have particularly favorable outcomes compared with patients who remain positive or become positive again.
“MRD resurgence” or conversion from negative to positive can precede standard biochemical progression in some patients. That finding is important, but treatment is not automatically changed based on one low-level result. Confirmation, trend, imaging, serologic markers, and the treatment setting matter.
A serum protein electrophoresis test and serum immunofixation remain useful for tracking secreted monoclonal protein even when marrow MRD is being measured.
When MRD is tested
There is no single universal schedule for every patient. MRD is frequently measured in clinical trials and increasingly used in practice when a deep response has been achieved and the result can clarify prognosis or a treatment decision.
Common time points include:
- after induction and autologous stem cell transplantation;
- after consolidation;
- during maintenance therapy;
- when a conventional complete response is documented;
- after cellular or bispecific-antibody therapy in selected protocols; and
- at later time points to assess sustained MRD negativity.
The exact timing depends on the treatment regimen and reason for testing. An early MRD result measures speed and depth of response. A later result during maintenance tests durability. A pre- and post-transplant comparison can show whether treatment further reduced disease.
MRD is not usually the first diagnostic test for myeloma. At diagnosis, the priority is confirming a clonal plasma-cell disorder, measuring monoclonal protein, identifying myeloma-defining events, assessing kidney function and calcium, imaging the skeleton, and obtaining marrow cytogenetics. MRD becomes relevant after therapy has substantially reduced disease.
Recurrence risk and treatment decisions
MRD is one of the strongest prognostic markers in myeloma. Across many studies and treatment settings, MRD-negative patients have longer progression-free and overall survival than MRD-positive patients. Deeper negativity and sustained negativity generally identify the most favorable groups.
However, MRD is prognostic, not a perfect personal forecast. A high-risk cytogenetic patient who becomes MRD negative may still carry more relapse risk than a standard-risk patient with the same MRD result. Similarly, two patients with detectable MRD may have very different outcomes depending on disease biology and response trend.
Risk assessment therefore combines MRD with factors such as:
- del(17p), 1q gain/amplification, and high-risk translocations;
- baseline disease stage and LDH;
- depth of serologic response;
- imaging findings;
- treatment received and duration of response; and
- whether MRD negativity is sustained.
A beta-2 microglobulin test for myeloma contributes to staging but measures a different dimension of disease than MRD.
Does MRD determine whether therapy should stop?
Not routinely in every clinical setting. Trials are testing MRD-guided escalation, de-escalation, and discontinuation strategies, and these approaches are becoming more important. Yet the safest interpretation is still regimen- and trial-specific. A patient should not stop maintenance or other therapy simply because one MRD test is negative unless the treating team is following a validated protocol or individualized plan.
Likewise, one positive result does not automatically require immediate treatment intensification. The clinician considers how positive it is, whether it is rising, whether conventional markers are changing, and whether the patient has high-risk biology.
Limitations and practical questions
The central limitation is sampling. Myeloma grows in patches, and a marrow aspirate from one site may miss a nearby focus. Extramedullary disease can also persist outside the marrow. Imaging therefore remains complementary, particularly when there was prior PET-avid or focal disease.
Other limitations include hemodilution, low cell counts, treatment-related antigen changes, an unavailable baseline sequence for NGS, and differences in laboratory validation. These factors explain why a report should describe sample quality and assay sensitivity rather than only “positive” or “negative.”
Useful questions to ask about a result include:
- Was the bone marrow sample adequate and not significantly hemodiluted?
- Was MRD measured by flow, NGS, or both?
- What sensitivity did the assay actually achieve in this sample?
- If positive, what was the measured level?
- How does this compare with my previous result?
- Are my M protein, immunofixation, free light chains, and imaging also improving?
- Does my cytogenetic risk change the meaning of MRD?
- Will the result change treatment now, or is it mainly prognostic?
- When should MRD be repeated?
The most accurate interpretation treats MRD as a depth-of-response marker within a broader myeloma picture. A high-quality negative result is encouraging; a positive result is informative; neither should be interpreted without the assay sensitivity, sample quality, and the rest of the disease data.
Why a marrow MRD result may miss disease elsewhere
Myeloma can be patchy within the bone marrow and can also persist outside the sampled marrow site. A negative aspirate from one iliac crest therefore cannot guarantee that every focus of disease has disappeared. This is one reason highly sensitive marrow MRD is often interpreted together with imaging when a patient previously had focal bone lesions or extramedullary disease.
Sample quality is critical. The first pull of a marrow aspirate generally contains the highest concentration of marrow cells; later pulls can be diluted by peripheral blood. Laboratories may use cellular composition or other quality checks to judge whether the specimen is representative. A technically negative result from a markedly diluted specimen deserves more caution than a negative result from an adequate sample analyzed to the intended sensitivity.
Sustained MRD negativity is stronger than one negative test
A single negative test is encouraging, but repeated negativity over time gives more information about durability of response. Clinical studies consistently show that deeper and sustained responses are associated with better progression outcomes at the group level. This does not mean relapse is impossible after MRD negativity, nor that every MRD-positive patient will relapse immediately.
The practical question is whether the result should change treatment. Outside defined protocols or trials, that decision depends on treatment phase, transplant status, side effects, cytogenetic risk, imaging, conventional response markers, and the specific MRD assay. Patients should ask not only “Was MRD negative?” but also “What sensitivity was reached, was the sample adequate, and will this result change what we do next?”
What 10⁻⁵ and 10⁻⁶ sensitivity mean
Myeloma MRD sensitivity is often described as 10⁻⁵ or 10⁻⁶. A sensitivity of 10⁻⁵ means the assay is designed to detect roughly one abnormal plasma cell among 100,000 tested cells under adequate conditions; 10⁻⁶ reaches roughly one among 1,000,000. Achieving the stated sensitivity requires enough high-quality cells and a validated method. A report should therefore state both the result and the sensitivity actually reached, because “MRD negative” at 10⁻⁶ is a deeper tested level than “MRD negative” at 10⁻⁵.
MRD results should also be separated from the older concept of complete response. A patient can meet conventional complete-response criteria yet still have detectable clonal plasma cells by a highly sensitive marrow assay. Conversely, an MRD-negative marrow does not replace standard monitoring of monoclonal protein, symptoms, organ function, and imaging when indicated. Each method observes a different layer of the disease.
That context is essential for comparing results over time.
References
- Measurable Residual Disease and Decision-Making in Multiple Myeloma 2024 (Review)
- Flow Cytometry in Diagnosis, Prognostication, and Monitoring of Multiple Myeloma and Related Disorders 2023 (Review)
- Evaluation of measurable residual disease in multiple myeloma by multiparametric flow cytometry: Current paradigm, guidelines, and future applications 2021 (Review)
- Minimal residual disease in multiple myeloma: defining the role of next generation sequencing and flow cytometry in routine diagnostic use 2021 (Review)
- Advancing MRD Detection in Multiple Myeloma: Technologies, Applications, and Future Perspectives 2025 (Review)
- Molecular Diagnostics of Plasma Cell Neoplasms 2023 (Review)
Disclaimer
This article is for general educational purposes and does not replace individualized care from a hematologist. Myeloma MRD results depend on the testing method, bone marrow quality, assay sensitivity, timing, disease distribution, and prior treatment. Do not change or stop myeloma therapy based on an MRD result without discussing it with the treating team.