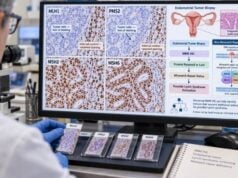
Mismatch repair immunohistochemistry, or MMR IHC, is a tumor-tissue test that checks whether four DNA-repair proteins—MLH1, PMS2, MSH2, and MSH6—are present in endometrial cancer cells. Loss of one or more proteins suggests mismatch repair deficiency, or dMMR. This finding is important for several reasons: it helps classify the tumor molecularly, can identify cancers that should be evaluated for Lynch syndrome, and may affect eligibility for immune checkpoint inhibitor treatment. An abnormal MMR IHC result does not automatically mean Lynch syndrome. The most common abnormal pattern in endometrial cancer is loss of MLH1 and PMS2, which is often caused by acquired MLH1 promoter methylation rather than an inherited mutation. The staining pattern guides the next test, such as MLH1 methylation analysis or germline genetic testing. A complete interpretation therefore requires the specific proteins lost, internal staining controls, clinical and family history, and any follow-up molecular testing.
- MMR IHC tests MLH1, PMS2, MSH2, and MSH6 proteins in endometrial tumor tissue; loss of staining can indicate mismatch repair deficiency.
- Loss of MLH1 and PMS2 usually triggers MLH1 promoter methylation testing because many cases are sporadic rather than Lynch syndrome.
- Loss of MSH2/MSH6, isolated MSH6 loss, or isolated PMS2 loss commonly prompts genetic evaluation for Lynch syndrome.
- dMMR is a tumor biomarker and is not identical to Lynch syndrome; inherited and acquired causes must be separated.
- MMR status also helps define endometrial cancer molecular subtype and can influence immunotherapy decisions.
Table of Contents
- What Mismatch Repair IHC Measures
- How MMR IHC Is Performed
- Interpreting MMR Protein Loss Patterns
- MMR IHC and Lynch Syndrome
- MMR Status and Endometrial Molecular Subtype
- Limitations and Discordant Results
- What Happens After an Abnormal MMR Test
What Mismatch Repair IHC Measures
DNA mismatch repair is a proofreading system. When cells copy DNA, small errors can occur, such as a wrong base or a short insertion or deletion. MMR proteins recognize and repair many of these mistakes.
The four proteins most often tested in endometrial cancer are MLH1, PMS2, MSH2, and MSH6. They function as pairs: MLH1 partners with PMS2, and MSH2 partners with MSH6. This pairing explains the characteristic loss patterns seen on IHC.
MMR IHC uses antibodies to stain tumor tissue. If a protein is functioning and produced at detectable levels, tumor-cell nuclei generally show staining. If the protein is absent because the corresponding pathway is disrupted, tumor nuclei can lose staining.
The test is performed on the cancer, not on blood. It is therefore a tumor screening biomarker, not a direct inherited genetic test. A tumor can lose MMR function because of an acquired event that is present only in the cancer.
MMR deficiency can lead to accumulation of errors in short repetitive DNA sequences called microsatellites. This produces microsatellite instability, or MSI. MMR IHC and MSI testing are related but different approaches. In endometrial cancer, MMR IHC is widely used because it identifies which protein pair is abnormal and can guide Lynch syndrome workup.
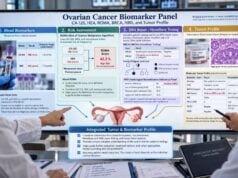
A broader endometrial cancer biomarker panel places MMR alongside POLE and p53 findings for modern molecular classification.
How MMR IHC Is Performed
MMR IHC can usually be performed on an endometrial biopsy, curettage, or hysterectomy specimen. A pathologist selects a block containing viable tumor and applies antibodies against the four repair proteins.
Interpretation requires internal positive controls. Normal stromal cells, lymphocytes, or non-neoplastic glands in the same tissue should retain nuclear staining. If both tumor and normal control cells fail to stain, the test may be technically uninterpretable rather than truly abnormal.
A typical report may state one of the following:
- intact nuclear expression of all four proteins;
- loss of MLH1 and PMS2;
- loss of MSH2 and MSH6;
- isolated loss of MSH6;
- isolated loss of PMS2;
- another unusual or indeterminate pattern.
Some centers have studied two-antibody screening strategies using PMS2 and MSH6 first because these proteins can act as sentinels for the two functional pairs. If one is lost, additional stains can clarify the pattern. Four-antibody testing remains common because it provides the full result directly and avoids some interpretive complexity.
Pre-analytic factors matter. Poor fixation, cautery, scant tumor, or weak staining can produce patchy or equivocal patterns. A pathologist may repeat the stain on another block if the internal controls are inadequate or if the loss pattern is unusual.
MMR testing is increasingly performed universally in newly diagnosed endometrial cancer rather than only in patients selected by age or family history. Universal testing identifies Lynch syndrome cases that would be missed by clinical criteria alone and simultaneously supplies a clinically useful tumor biomarker.
Testing the initial biopsy can be advantageous because the result may be available before definitive surgery and can prompt genetic counseling early. A hysterectomy specimen may provide more tumor if the biopsy is scant or technically difficult. If both specimens have been tested and the results differ, the pathology team may review fixation, tumor heterogeneity, and whether treatment occurred between samples.
The report may also use terms such as “intact,” “retained,” “loss,” “deficient,” or “proficient.” These words describe protein expression, not mutation status. “Intact MMR” means the four proteins show expected nuclear staining; it does not mean that every MMR gene has been sequenced or that hereditary cancer risk has been ruled out by genetics.
Interpreting MMR Protein Loss Patterns
Because MMR proteins work in pairs, the pattern of IHC loss provides clues about the underlying gene or epigenetic event.
| IHC pattern | Common interpretation | Typical follow-up |
|---|---|---|
| All four retained | Mismatch repair proficient, or pMMR | No reflex Lynch workup from IHC alone unless clinical suspicion remains |
| MLH1 and PMS2 lost | MLH1 pathway abnormality; often sporadic promoter methylation | MLH1 promoter methylation testing |
| MSH2 and MSH6 lost | Possible MSH2 or EPCAM-related Lynch syndrome | Genetic counseling and germline testing |
| MSH6 lost alone | Possible MSH6-related Lynch syndrome | Genetic counseling and germline testing |
| PMS2 lost alone | Possible PMS2-related Lynch syndrome or less commonly MLH1-related mechanism | Genetic counseling and targeted germline evaluation |
Why MLH1 and PMS2 disappear together
PMS2 is unstable without MLH1. If MLH1 is not produced, PMS2 is often lost as a secondary effect. That is why MLH1/PMS2 dual loss usually points first to the MLH1 pathway.
Why MSH2 and MSH6 disappear together
MSH6 depends on MSH2 for stability. Loss of MSH2 commonly causes secondary loss of MSH6, producing a paired pattern.
Isolated partner loss
A pathogenic MSH6 variant can cause isolated MSH6 loss because MSH2 may still pair with another protein. Similarly, a PMS2 defect can produce isolated PMS2 loss while MLH1 remains detectable.
The pattern is a screening clue, not the final genetic diagnosis. Germline sequencing and deletion/duplication analysis are required to identify an inherited pathogenic variant.
MMR IHC and Lynch Syndrome
Lynch syndrome is an inherited cancer-predisposition condition caused by pathogenic variants in mismatch repair genes or certain EPCAM deletions. It increases the risk of endometrial and colorectal cancer and can also raise the risk of ovarian, gastric, urinary tract, and other cancers.
Endometrial cancer may be the first cancer diagnosed in a person with Lynch syndrome, which makes tumor screening particularly valuable.
The most important point is that dMMR does not equal Lynch syndrome. Many endometrial tumors lose MLH1 and PMS2 because the tumor has acquired methylation of the MLH1 promoter. Methylation shuts down MLH1 expression without an inherited mutation.
For MLH1/PMS2 loss, the usual next step is therefore MLH1 promoter methylation testing. If the tumor is methylated, the abnormality is usually considered sporadic, although unusual clinical situations can still require genetics review. If MLH1 is not methylated, the likelihood of an inherited or other pathogenic MLH1 mechanism rises and germline testing is generally indicated.
MSH2/MSH6 loss, isolated MSH6 loss, and isolated PMS2 loss are more directly suspicious for Lynch syndrome and typically lead to genetic counseling and germline testing.
Family history remains useful even with universal screening. Early colorectal or endometrial cancers, multiple Lynch-associated cancers, or several affected relatives can strengthen the need for genetics evaluation. Conversely, a person can have Lynch syndrome without an obvious family history because families are small, relatives may be young, or the variant may have been inherited through a branch with few cancers.
A gynecologic hereditary cancer gene panel may be used when the clinical history suggests more than one hereditary syndrome.
MMR Status and Endometrial Molecular Subtype
MMR is not only a Lynch syndrome screen. It is also one of the major molecular classifiers in endometrial cancer.
Modern classification recognizes groups including POLE-mutated tumors, mismatch repair-deficient tumors, p53-abnormal tumors, and tumors with no specific molecular profile. These categories can provide prognostic information and increasingly influence treatment decisions.
A tumor with loss of one or more MMR proteins is generally classified in the MMRd group unless another higher-priority classifier such as a pathogenic POLE exonuclease-domain mutation changes the integrated assignment according to the molecular algorithm being used.
The POLE mutation test identifies a distinct ultramutated group that often has a favorable prognosis despite high-grade histology. The p53 test helps identify p53-abnormal cancers, a group that includes many serous and other aggressive tumors.
MMR status also has predictive treatment value. dMMR and MSI-high cancers tend to generate many mutations and abnormal proteins that can make them visible to the immune system. Immune checkpoint inhibitors have important roles in advanced or recurrent endometrial cancer, and MMR/MSI status can help guide their use depending on the treatment setting and regimen.
That treatment implication is independent of whether the dMMR is hereditary. A sporadic MLH1-methylated tumor can still be biologically MMR-deficient and clinically relevant for immunotherapy.
MMR status can matter at more than one point in treatment. In advanced or recurrent disease, it can help determine whether a checkpoint inhibitor is appropriate as monotherapy or as part of a combination, depending on current approvals and prior treatment. In newly diagnosed disease, molecular subtype increasingly contributes to adjuvant risk discussions as clinical trials and guidelines incorporate molecular classification. A biomarker should therefore be available in a form that is easy for both pathologists and oncologists to interpret.
Patients sometimes assume that dMMR automatically predicts a dramatic immunotherapy response. The association is strong at the population level, but individual tumors can still fail to respond or later develop resistance. Stage, symptoms, treatment history, and other tumor features remain important.
Limitations and Discordant Results
MMR IHC is highly useful but not perfect.
Retained staining does not absolutely exclude Lynch syndrome
Some pathogenic missense variants produce a protein that is still recognized by the antibody even though it does not function normally. Rare Lynch syndrome cases can therefore show retained IHC.
Staining can be subclonal or heterogeneous
Some tumors show loss in only part of the cancer. This may reflect true biological heterogeneity, treatment effects, or technical issues. The pathologist may recommend repeat testing or additional molecular analysis.
Technical failure can mimic loss
If normal internal control cells are also negative, the stain cannot be trusted. Repeat IHC on another section or block may be necessary.
IHC and MSI can disagree
Most dMMR tumors are MSI-high, but discordant results occur. Endometrial cancer can show unusual MSH6 patterns after certain treatments, and some tumors have biologic or technical reasons for mismatch between methods.
Methylation testing has its own limitations
MLH1 promoter methylation strongly supports a sporadic mechanism in most endometrial cancers, but unusual hereditary or constitutional epigenetic situations exist. Very young age or a striking family history may justify genetics review even when the usual reflex algorithm suggests a sporadic tumor.
Tumor testing is not germline testing
An IHC pattern can point toward a gene, but only germline testing can determine whether a pathogenic variant is inherited and present throughout the body.
When the laboratory result conflicts with the clinical history, pathology review, MSI testing, tumor sequencing, or genetics consultation can help resolve the discrepancy.
What Happens After an Abnormal MMR Test
The next step depends on the exact protein-loss pattern.
If MLH1 and PMS2 are lost, ask whether MLH1 promoter methylation testing was performed. A methylated result usually supports a sporadic tumor mechanism. An unmethylated result generally leads to genetic counseling and germline testing.
If MSH2/MSH6, MSH6 alone, or PMS2 alone is lost, referral for Lynch syndrome evaluation is typically appropriate. Germline testing may include sequencing and deletion/duplication analysis of the relevant genes, often as part of a multigene panel.
If a germline pathogenic variant confirms Lynch syndrome, the result affects more than the endometrial cancer. The patient may need tailored colorectal and other cancer surveillance, and adult relatives can consider cascade testing for the known family variant.
If germline testing is negative despite unexplained dMMR, tumor sequencing can sometimes identify two acquired mutations that explain the abnormal IHC. These cases are often called double-somatic or Lynch-like tumors and may reduce concern for an inherited syndrome, although interpretation belongs with genetics professionals.
For the cancer itself, the oncology team uses MMR status with stage, histology, POLE, p53, HER2 in selected tumors, and other clinical factors. A separate HER2 test can be relevant in uterine serous and other selected high-grade cancers, but it answers a different treatment question.
Patients can ask for the complete pathology result rather than only “MMR abnormal.” The specific proteins lost determine what happens next. Useful questions include:
- Which MMR proteins were retained and which were lost?
- Were internal controls adequate?
- If MLH1/PMS2 were lost, was MLH1 methylation tested?
- Do I need genetic counseling or germline testing?
- Does my MMR result affect systemic treatment now or if the cancer recurs?
A clear answer to those questions turns an IHC pattern into a coordinated hereditary-risk and treatment plan.
If Lynch syndrome is confirmed, relatives do not need to repeat the patient’s tumor IHC. Instead, they can have targeted germline testing for the known family variant after appropriate counseling. Relatives who test negative for that familial variant generally do not carry the Lynch risk from that mutation, while those who test positive can begin syndrome-specific prevention and surveillance. This is one of the major reasons it is important to distinguish a sporadic methylated tumor from an inherited MMR defect.
If the IHC is abnormal but germline testing is negative, the case should not simply be labeled “Lynch negative” without considering the tumor explanation. Paired tumor-germline analysis can sometimes show two somatic hits in the same MMR gene, clarifying that the repair defect arose within the cancer. That distinction can reduce unnecessary hereditary surveillance for relatives while preserving the tumor’s dMMR treatment implications.
References
- Universal testing in endometrial cancer in Sweden 2024
- Simplifying Mismatch Repair Deficiency Screening in Endometrial Adenocarcinoma: Immunohistochemistry with Two-Antibody Panel (PMS2 and MSH6) 2024
- A simplified two-marker immunohistochemistry strategy for Lynch syndrome screening in endometrial cancer patients 2023
- Mismatch Repair and Microsatellite Instability Testing for Immune Checkpoint Inhibitor Therapy: ASCO Endorsement of College of American Pathologists Guideline 2023 (Guideline)
- Endometrial cancer: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up 2022 (Guideline)
Disclaimer
MMR IHC is a tumor screening and treatment biomarker, not a direct diagnosis of Lynch syndrome. The specific protein-loss pattern, MLH1 promoter methylation testing, germline testing, and clinical history determine whether an inherited syndrome is likely. Results should be reviewed with the treating oncology team and, when indicated, a genetics professional.