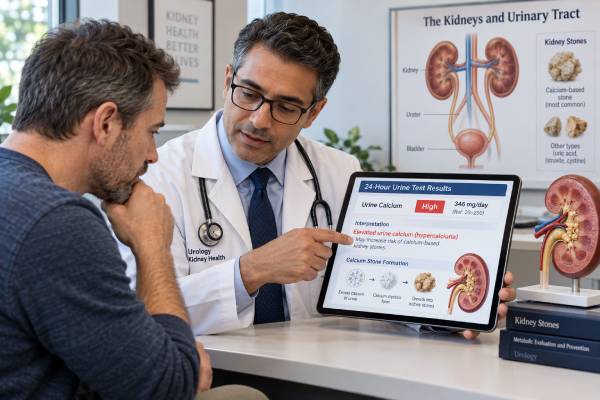
A urine calcium test measures how much calcium is excreted into the urine and helps identify hypercalciuria, one of the most common metabolic risk factors for calcium kidney stones. The most useful version for recurrent stone evaluation is usually a 24-hour urine collection because it measures total daily calcium and allows the result to be interpreted with urine volume, sodium, oxalate, citrate, pH, creatinine, and supersaturation. A high urine calcium result does not automatically mean that blood calcium is high, and it does not prove a parathyroid disorder. Many stone formers have idiopathic hypercalciuria with completely normal serum calcium. Stone risk also rises gradually rather than at one perfect cutoff, so a result just below a laboratory limit can still matter when urine volume is low or oxalate is high. The goal of testing is to identify the pattern causing calcium crystallization and then reduce that risk without unnecessarily restricting normal dietary calcium.
- High urine calcium is called hypercalciuria: it raises calcium oxalate and calcium phosphate stone risk, especially when urine is concentrated.
- A 24-hour urine test is preferred for metabolic stone evaluation: it measures total calcium excretion and shows related factors such as sodium, oxalate, citrate, and volume.
- Urine calcium and blood calcium are different tests: high urine calcium can occur with normal blood calcium, while high blood calcium may require a parathyroid evaluation.
- There is no single universal cutoff: common thresholds include more than 250 mg/day in women or 300 mg/day in men in some clinical frameworks, while laboratories may use different reference ranges.
- Do not routinely eliminate dietary calcium because urine calcium is high: normal calcium intake with meals can reduce intestinal oxalate absorption and may lower calcium oxalate risk overall.
Table of Contents
- What a urine calcium test measures
- What counts as high urine calcium
- Common causes of hypercalciuria
- How urine calcium raises kidney stone risk
- Collection and interpretation with other urine markers
- What happens after a high result
- Follow-up and common mistakes
What a urine calcium test measures
A urine calcium test measures calcium that has been filtered by the kidneys and excreted into urine. For kidney stone prevention, clinicians usually want the total amount excreted over 24 hours rather than the concentration in a single spot sample.
The 24-hour result is reported in units such as mg/24 hr or mmol/day. It is often part of a broader metabolic panel that also measures urine volume, oxalate, citrate, uric acid, sodium, pH, creatinine, magnesium, phosphorus, and urea nitrogen. Many stone laboratories also calculate calcium oxalate and calcium phosphate supersaturation.
This broader context matters because calcium does not form a stone by itself. Calcium oxalate crystals require oxalate, and calcium phosphate risk is strongly influenced by urine pH. Citrate can bind calcium and inhibit crystallization, while higher urine volume dilutes all of these solutes.
A spot urine calcium-to-creatinine ratio can be useful in selected situations, especially in children or when a 24-hour collection is impractical. It is not a direct substitute for a complete adult 24-hour stone evaluation because spot results vary with time of day, meals, hydration, age, and body size.
The test also differs from a blood calcium test for kidney stones. Serum calcium is tightly regulated and may remain normal even when urinary calcium is excessive. That is why a normal blood result does not rule out hypercalciuria.
What counts as high urine calcium
There is no single threshold that perfectly separates low-risk from high-risk urine. Large studies suggest that stone risk increases progressively as urine calcium rises rather than suddenly changing at one cutoff.
Several reference points are commonly used:
- The 2022 primary hyperparathyroidism guidelines use more than 250 mg/24 hr in women and more than 300 mg/24 hr in men as hypercalciuria criteria in that specific endocrine context.
- European urolithiasis guidance lists calcium excretion above about 8 mmol/day, roughly 320 mg/day, as a level that can warrant treatment attention in some calcium-stone pathways.
- Some specialized laboratories use sex-specific reference ranges that are lower. Litholink’s 2026 adult ranges list 30–200 mg/24 hr for women and 40–250 mg/24 hr for men.
- Weight-based values such as more than 4 mg/kg/day are also used in some settings.
These numbers are not interchangeable treatment rules. A laboratory reference range describes how that laboratory reports the test, while a guideline threshold may be designed for a specific decision, such as evaluating primary hyperparathyroidism or selecting medication.
What if urine calcium is low?
A low 24-hour urine calcium result is usually less directly important for calcium stone risk than a high result, but it can still provide useful clues. It may reflect low dietary calcium intake, reduced intestinal calcium absorption, vitamin D deficiency, chronic kidney disease, thiazide treatment, or an incomplete urine collection. In patients with bowel disease or malabsorption, low urine calcium can coexist with high urine oxalate because unabsorbed fatty acids bind intestinal calcium and leave more oxalate free for absorption.
That combination is important: a patient can have low urine calcium and still form calcium oxalate stones if oxalate is high, citrate is low, or urine volume is low. The clinician therefore avoids assuming that “low calcium” means “low stone risk.” Creatinine excretion, dietary history, and the other 24-hour urine values help determine whether the result is physiologic or simply reflects a missed portion of the collection.
A result of 240 mg/day may be clinically important in a small woman with repeated calcium stones, high oxalate, low citrate, and low urine volume. A value of 310 mg/day may carry a different risk when urine volume is high, citrate is abundant, and supersaturation is controlled. The urine supersaturation result helps integrate these factors.
Total calcium excretion should also be distinguished from calcium concentration. A person can excrete the same 300 mg of calcium on two days but have very different crystal risk if one day produces 1.2 L of urine and the other 2.8 L. The laboratory’s 24-hour total helps identify hypercalciuria, while volume and supersaturation show how concentrated that calcium becomes in the actual urine.
Urine sodium adds another useful layer. Because sodium and calcium handling in the kidney are linked, a high sodium result can explain why urinary calcium remains elevated despite otherwise reasonable dietary calcium intake. If both fall on a repeat collection after sodium reduction, that paired response supports the dietary explanation more strongly than either number alone.
Common causes of hypercalciuria
Most recurrent calcium stone formers with high urine calcium do not have one dramatic endocrine disease. Idiopathic hypercalciuria, meaning elevated urinary calcium without another obvious systemic cause, is common and often has a genetic component.
Important causes and contributors include:
High sodium intake
Sodium and calcium handling are linked in the kidney. When sodium intake and urinary sodium are high, urinary calcium often rises as well. This is why a high urine sodium result is clinically useful rather than merely a dietary curiosity. The urine sodium test for kidney stones can show whether salt exposure is likely contributing.
Primary hyperparathyroidism
High blood calcium together with elevated or inappropriately normal PTH raises concern for primary hyperparathyroidism. The condition can increase urinary calcium and calcium stone risk. A PTH test for kidney stones is therefore important when serum calcium is repeatedly high or the clinical pattern suggests a parathyroid cause.
High calcium or vitamin D exposure
Excessive calcium supplements, especially when taken outside meals in susceptible patients, can increase urine calcium. High vitamin D intake can also raise calcium absorption and urinary excretion. Normal food-based calcium is different and should not automatically be restricted.
Diet and acid load
Very high animal-protein intake can increase acid load and may raise urinary calcium while lowering citrate in some people. Diet usually acts together with sodium, fluid, and other factors rather than as a single cause.
Granulomatous disease and other medical causes
Sarcoidosis and certain other granulomatous diseases can increase active vitamin D production and calcium absorption. Hyperthyroidism, prolonged immobilization, some medications, and rare inherited tubular disorders can also produce hypercalciuria. The medical history and blood tests determine whether these less common causes need investigation.
Older labels such as “absorptive,” “renal leak,” and “resorptive” hypercalciuria are less central to modern routine stone management because the mechanisms often overlap and treatment is usually guided by the current urine pattern and systemic cause rather than by assigning one historic subtype.
How urine calcium raises kidney stone risk
Higher urinary calcium increases the chance that calcium will combine with oxalate or phosphate and exceed the solubility of those salts. Once urine becomes supersaturated, crystals can nucleate and grow.
For calcium oxalate stones, four variables often dominate the chemical risk: calcium, oxalate, citrate, and volume. Recent cohort analysis of 24-hour urine chemistries found higher calcium and oxalate associated with greater stone risk, while higher urine volume and citrate were strongly protective. The relationships were largely continuous, supporting the idea that there is no magic “safe” calcium cutoff.
The effect of oxalate is especially important because small changes in oxalate can markedly alter calcium oxalate supersaturation. A person with moderately high calcium and high oxalate may therefore have more risk than someone with a higher calcium number but low oxalate. The urine oxalate test should be interpreted alongside calcium rather than after it.
For calcium phosphate stones, urine pH becomes more important. A higher pH increases the proportion of phosphate species that combine with calcium. This is one reason over-alkalinization with citrate therapy can be problematic in selected calcium phosphate stone formers even though citrate itself is protective.
Low urine volume amplifies both pathways by increasing concentration. Hydration can therefore reduce supersaturation even when the total calcium excretion does not change dramatically.
Collection and interpretation with other urine markers
A 24-hour urine calcium result is only reliable when the collection is reasonably complete. Missing several voids can make the daily calcium total look falsely low, while collecting far beyond 24 hours can make it look falsely high.
For a typical collection, the first urine at the start time is discarded, every subsequent void is collected, and the final urine at the same time the next day is included. Follow the laboratory’s specific preservative and storage instructions.
The baseline test should usually reflect the patient’s ordinary diet and fluid intake. Deliberately cutting salt, avoiding all calcium, or drinking unusually large volumes just for the collection can hide the pattern the clinician needs to treat.
Creatinine excretion helps assess completeness, although it varies with muscle mass, age, sex, and body size. If two 24-hour collections differ greatly, the clinician may look at creatinine, volume, sodium, and the collection history before deciding which is representative.
Day-to-day variation is another reason one collection should not be treated as a permanent label. Restaurant meals, unusually salty foods, intense exercise, heat exposure, and changes in supplement use can shift calcium excretion. In recurrent or high-risk stone formers, two baseline collections may give a more reliable picture. A repeat collection after treatment is also more useful when it is compared with the same laboratory’s method and interpreted alongside the change in sodium, volume, and supersaturation.
Urine calcium should be read with:
| Related marker | Why it changes the meaning of urine calcium |
|---|---|
| Urine volume | Low volume raises calcium salt concentration and supersaturation |
| Urine sodium | High sodium often contributes to higher calcium excretion |
| Urine oxalate | Raises calcium oxalate supersaturation when elevated |
| Urine citrate | Citrate binds calcium and inhibits crystallization |
| Urine pH | Higher pH can increase calcium phosphate risk |
| Serum calcium and PTH | Help identify systemic causes such as primary hyperparathyroidism |
The urine citrate result is particularly useful because two patients with the same urine calcium may have very different crystallization risk depending on how much citrate is present.
What happens after a high result
The first step is usually to confirm that the collection was valid and look for reversible causes. A high urine calcium value with very high urine sodium often leads to a focused sodium reduction plan. A high urine calcium result with hypercalcemia leads to blood-based evaluation for a parathyroid or other systemic disorder.
General prevention usually includes enough fluid to produce more than about 2–2.5 L of urine daily, adjusted for climate and activity. Sodium reduction is often emphasized because it can lower urine calcium and also supports blood pressure control.
Normal dietary calcium should generally be maintained, commonly around 1,000–1,200 mg/day for adults unless another medical condition requires a different target. Calcium from food taken with meals binds oxalate in the intestine and can reduce oxalate absorption. Severe calcium restriction can therefore lower urine calcium yet paradoxically increase urinary oxalate and calcium oxalate risk.
Calcium supplements are more individualized. A patient who needs a supplement for bone health may be advised to take it with food, particularly if oxalate is high. Dose and timing should be discussed with the clinician rather than stopped automatically.
Thiazide and thiazide-like diuretics lower urinary calcium and have long been used in recurrent calcium stone prevention. Recent evidence has complicated the picture. The 2023 NOSTONE trial did not show a clear dose-response reduction in the composite of symptomatic or radiologic recurrence with hydrochlorothiazide compared with placebo, and adverse effects were more common. Subsequent reviews have emphasized uncertainty about the overall benefit of routine thiazide monotherapy.
This does not mean thiazides never have a role. Guidelines still consider them for selected patients with persistent hypercalciuria and recurrent calcium stones, particularly when diet and sodium reduction are insufficient. The decision should weigh blood pressure, potassium, glucose, uric acid, kidney function, skin-cancer history where relevant, and the patient’s actual recurrence risk.
Follow-up and common mistakes
A repeat 24-hour urine collection can show whether treatment changed the chemistry in the intended direction. If sodium falls but calcium remains high, the clinician may look for another driver. If calcium falls but citrate also falls, the net supersaturation result may not improve as much as expected.
European guidance suggests repeating 24-hour urine testing around 8–12 weeks after starting pharmacologic prevention, then periodically once the values are stable. Diet-only changes may also be reassessed when the initial abnormality is substantial or recurrence risk is high.
Common mistakes include:
- Cutting dietary calcium too aggressively. This can increase oxalate absorption and may worsen calcium oxalate risk.
- Ignoring sodium. A patient may focus on dairy while high salt intake continues to drive calciuria.
- Treating the cutoff instead of the pattern. A value just under a reference limit can still matter if supersaturation remains high.
- Assuming high urine calcium means high blood calcium. The two are related but not interchangeable.
- Assuming all calcium stones require a thiazide. Medication should be based on recurrence, urine chemistry, comorbidities, and current evidence.
- Using an incomplete 24-hour collection. Missing urine can create a falsely reassuring result.
A high result is therefore best viewed as a modifiable risk marker, not a diagnosis by itself. The practical question is why calcium excretion is high and whether reducing sodium, improving urine volume, correcting a systemic cause, or using selected medication lowers calcium salt supersaturation over time.
For that reason, clinicians often care more about the direction of change than about forcing the value below one universal number. A drop from 360 to 250 mg/day may be meaningful if calcium oxalate supersaturation also falls and the patient remains stone-free. Conversely, a small fall in calcium may not be enough if urine volume remains low or oxalate stays high. The treatment target is the whole stone-risk profile, not merely the calcium line on the report.
References
- Metabolic Evaluation and Recurrence Prevention – EAU Guidelines on Urolithiasis – Uroweb 2026 (Guideline)
- Metabolic evaluation for prevention of kidney stones – CARI Guidelines 2025 (Guideline)
- 24-Hour Urinary Chemistries and Kidney Stone Risk 2024
- Hydrochlorothiazide and Prevention of Kidney-Stone Recurrence 2023 (RCT)
- Thiazides for kidney stone recurrence prevention 2024 (Review)
Disclaimer
This article is for general education and does not diagnose the cause of hypercalciuria or recommend a specific medication. Urine calcium must be interpreted with collection quality, blood calcium, kidney function, sodium, oxalate, citrate, pH, and stone history. Seek urgent medical care for severe stone symptoms with fever, inability to urinate, or persistent vomiting.