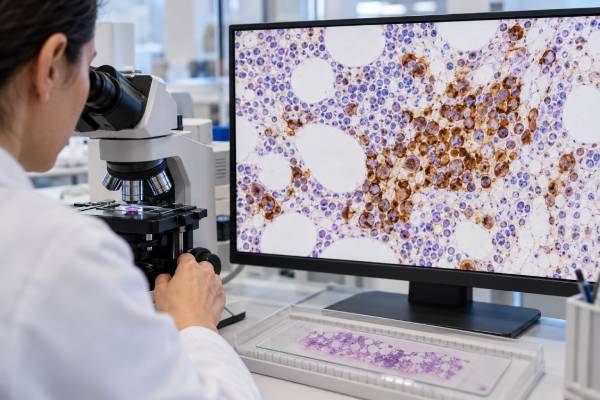
A CD138 test helps pathologists identify plasma cells in bone marrow or tissue, especially when multiple myeloma or another plasma cell disorder is being considered. CD138, also called syndecan-1, is a protein found strongly on most mature plasma cells. In a bone marrow biopsy, staining for CD138 can make plasma cells much easier to see and can show whether they are scattered normally or form an abnormal, dense infiltrate. The test does not diagnose myeloma by itself. Normal plasma cells can be CD138-positive, and some non-blood cancers can also express CD138. Pathologists therefore interpret the stain together with the percentage and pattern of plasma cells, kappa/lambda light-chain restriction, flow cytometry, blood and urine protein studies, imaging, and genetic testing. For someone reviewing a pathology report, the key question is not simply whether CD138 is “positive,” but what cells are positive, how many there are, whether they are clonal, and how the finding fits the full myeloma workup.
- CD138 positivity usually identifies plasma cells, not cancer by itself. Normal, reactive, and myeloma plasma cells can all stain positive.
- In bone marrow biopsies, CD138 is useful for estimating plasma-cell burden and infiltration pattern. It can reveal patchy disease that an aspirate sample may underrepresent.
- There is no universal “normal CD138 level.” Results are usually described as staining present or absent and as the proportion and distribution of CD138-positive plasma cells.
- Clonality matters. Kappa/lambda studies, flow cytometry, and other tests help distinguish a reactive plasma-cell increase from a neoplastic plasma-cell population.
- CD138 must be interpreted with the complete myeloma assessment. A positive stain alone cannot establish multiple myeloma or determine treatment.
Table of Contents
- What the CD138 Test Measures
- How CD138 Testing Is Done
- How to Interpret CD138 Results and Positive Staining
- CD138 in Multiple Myeloma and Plasma Cell Disorders
- Bone Marrow Plasma-Cell Percentage and Pattern
- Limits, Pitfalls, and Treatment Effects
- What Happens After a CD138 Result
What the CD138 Test Measures
CD138 testing detects syndecan-1 protein on cells and is mainly used in hematopathology to highlight plasma cells. Plasma cells are mature B-lineage cells that produce antibodies. They normally make up only a small fraction of bone marrow cells, although their number can rise with infection, inflammation, autoimmune disease, and other immune stimulation.
CD138 is a transmembrane heparan sulfate proteoglycan. In practical terms, that means it is a cell-surface protein with roles in cell adhesion and interactions with the surrounding tissue. Mature plasma cells usually express CD138 strongly, which makes the marker useful when those cells are difficult to count on routine hematoxylin-and-eosin staining alone.
A pathologist may order or review CD138 staining when the clinical question includes:
- multiple myeloma;
- smoldering multiple myeloma;
- monoclonal gammopathy of undetermined significance (MGUS);
- plasmacytoma;
- lymphoplasmacytic or other B-cell neoplasms with plasmacytic differentiation;
- an unexplained increase in plasma cells in a marrow biopsy; or
- assessment of plasma-cell distribution after treatment.
CD138 is primarily a lineage and localization marker, not a stand-alone malignancy marker. It tells the pathologist, “these cells show plasma-cell differentiation.” It does not by itself answer whether the plasma cells are reactive or clonal. That distinction often requires morphology plus light-chain studies and a broader immunophenotypic panel.
This is why CD138 testing commonly appears beside tests such as the serum free light chain test, serum protein electrophoresis, immunofixation, cytogenetics, and imaging. Each test answers a different part of the diagnostic question.
How CD138 Testing Is Done
The most common CD138 test in a myeloma workup is immunohistochemistry on a bone marrow core biopsy. The laboratory applies an antibody that binds CD138 to a thin tissue section. A detection system creates visible staining where the protein is present, allowing the pathologist to identify the positive cells under a microscope.
Bone marrow evaluation usually includes two related specimens. The aspirate is liquid marrow used for cell counts, morphology, flow cytometry, chromosome testing, FISH, and molecular studies. The core biopsy preserves tissue architecture, so it can show whether plasma cells are diffuse, clustered, nodular, interstitial, or patchy. CD138 is especially helpful on the core because it outlines plasma cells clearly against other marrow cells.
The test generally requires no special preparation beyond the preparation for the bone marrow procedure itself. Local anesthetic is typically used for a marrow biopsy, most often from the back of the pelvic bone. The stain is performed after tissue processing; the patient does not receive CD138 antibody as an injection for routine pathology testing.
CD138 can also be assessed by flow cytometry. Flow laboratories often identify plasma cells through combinations that include bright CD38, CD138, CD45, CD19, CD56, CD27, CD81, CD117, and cytoplasmic kappa/lambda. The exact panel varies by laboratory and by whether the goal is diagnosis or measurable residual disease assessment.
A tissue CD138 stain and a flow-cytometry result are therefore related but not interchangeable. The biopsy shows architecture and can be more representative when disease is patchy. Flow cytometry can characterize many markers on individual cells and establish abnormal immunophenotypes, but the aspirate can be diluted with peripheral blood or may undersample a focal lesion. For a broader view of plasma-cell testing, the multiple myeloma test panel combines these marrow findings with monoclonal protein and staging studies.
How to Interpret CD138 Results and Positive Staining
A “CD138-positive” result means the tested cells express CD138; it does not automatically mean multiple myeloma. In marrow, the next questions are the percentage of plasma cells, their pattern, their appearance, and whether they are clonal.
There is no single laboratory reference range comparable with a blood sodium or glucose level. Reports may use wording such as “CD138 highlights approximately 5% plasma cells” or “CD138 highlights sheets of plasma cells involving 70% of marrow cellularity.” Some reports also describe intensity as weak, moderate, or strong, but intensity alone is rarely the central diagnostic issue.
| Finding | What it can mean | What is usually needed next |
|---|---|---|
| Few scattered CD138-positive plasma cells | May be within a normal or reactive pattern | Clinical context and clonality studies if concern remains |
| Increased CD138-positive plasma cells | Can occur in reactive conditions or plasma-cell neoplasms | Kappa/lambda assessment, flow cytometry, serum/urine studies |
| Clusters, nodules, or sheets of CD138-positive cells | Raises concern for a clonal plasma-cell process, depending on morphology and other findings | Full plasma-cell neoplasm workup |
| CD138-positive cells with light-chain restriction | Supports a clonal plasma-cell population | Correlate with myeloma-defining criteria and genetics |
| CD138-negative or weak suspected plasma cells | Possible technical issue, antigen loss, unusual phenotype, or non-plasma-cell process | Use alternative markers and morphology |
Clonality is often assessed by showing that the abnormal plasma cells produce predominantly one immunoglobulin light chain, kappa or lambda. This can be tested by in situ hybridization, immunohistochemistry, or flow cytometry. A clonal population is important evidence of a plasma-cell neoplasm, but even clonality does not by itself distinguish MGUS, smoldering myeloma, active myeloma, or plasmacytoma.
The safest way to read a pathology report is to treat the CD138 line as one part of a combined interpretation rather than as a yes/no cancer test.
CD138 in Multiple Myeloma and Plasma Cell Disorders
In multiple myeloma, CD138 usually highlights the malignant plasma-cell population and helps estimate how much of the marrow it occupies. Most myeloma plasma cells express CD138, often strongly, but the marker is not unique to myeloma.
A diagnosis of active multiple myeloma depends on a clonal plasma-cell disorder plus defined disease features. In standard criteria, the marrow generally contains at least 10% clonal plasma cells, or there is a biopsy-proven plasmacytoma, together with one or more myeloma-defining events. These can include classic organ damage—hypercalcemia, kidney impairment, anemia, or bone lesions—or specific biomarkers associated with a very high risk of progression, such as very high marrow clonal plasma-cell burden, a markedly abnormal involved-to-uninvolved free light-chain ratio under the required conditions, or more than one focal lesion on MRI.
That means a CD138 estimate may contribute directly to an important diagnostic threshold, but the pathologist still has to determine that the plasma cells are clonal and the clinical team must integrate the rest of the criteria.
CD138 also helps in conditions that sit on the same biological spectrum:
- MGUS: a monoclonal protein is present, but the clonal plasma-cell burden and clinical findings do not meet criteria for myeloma.
- Smoldering multiple myeloma: clonal plasma cells or monoclonal protein burden is higher than in MGUS, but myeloma-defining events are absent.
- Plasmacytoma: a localized mass of clonal plasma cells may show CD138 positivity, with evaluation needed to determine whether systemic myeloma is also present.
- Other lymphoid neoplasms: some lymphomas contain a plasmacytic component that may be CD138-positive.
For the protein side of the workup, serum immunofixation identifies the immunoglobulin type of a monoclonal protein, while marrow immunophenotyping evaluates the cells producing it.
Bone Marrow Plasma-Cell Percentage and Pattern
CD138 staining can give a more dependable visual estimate of plasma-cell burden when marrow involvement is uneven or the aspirate is diluted. Multiple myeloma often does not spread uniformly through the marrow. One area may contain many abnormal plasma cells while another contains relatively few.
This sampling issue explains why the plasma-cell percentage on an aspirate smear can differ from the percentage estimated on a CD138-stained core biopsy. A “dry tap,” hemodilution, fibrosis, or simply drawing from a less involved area can lower the apparent plasma-cell percentage in the aspirate. Conversely, a core biopsy preserves the relationship between cells and tissue and can expose dense focal aggregates.
Pathologists look at more than a raw percentage. They may describe patterns such as:
- interstitial: plasma cells are dispersed among other marrow cells;
- small clusters or nodules: groups of plasma cells are concentrated in defined areas;
- diffuse or sheet-like: plasma cells replace a substantial portion of normal marrow;
- paratrabecular or focal patterns: localization may contribute to the differential diagnosis depending on the full morphology.
The percentage is also not interpreted in isolation from marrow cellularity. “Thirty percent plasma cells” means plasma cells are estimated to represent about 30% of nucleated marrow cells in the evaluated area; it is not the same as saying 30% of all cells in the body are malignant.
When biopsy and aspirate estimates disagree substantially, clinicians often give significant weight to the higher, better-supported estimate, especially when the core clearly shows patchy or dense involvement. The final interpretation may also incorporate imaging because marrow-based sampling can miss disease elsewhere in the skeleton.
Genetic testing on the clonal plasma cells adds another layer. FISH can identify abnormalities that influence risk classification and treatment planning. CD138-positive cell enrichment is sometimes used before FISH to increase the proportion of plasma cells in a sample, which can improve detection when tumor burden is low.
Limits, Pitfalls, and Treatment Effects
The biggest limitation of CD138 is that it identifies plasma-cell differentiation more reliably than it identifies malignancy. A positive result must be interpreted in context.
Several pitfalls matter:
- Reactive plasmacytosis can be CD138-positive. Infection, inflammation, autoimmune disease, and recovery after marrow injury can increase normal plasma cells.
- CD138 is not exclusive to blood cells. Some epithelial and other nonhematologic tumors can express it. Tissue type and morphology determine whether the stain is being used as a plasma-cell marker.
- Antigen expression can vary. Some neoplastic plasma cells may show reduced or heterogeneous CD138, particularly with biological change, specimen handling, or unusual differentiation.
- Aspirate quality affects flow cytometry. Hemodilution can reduce apparent plasma-cell numbers and may make residual disease look lower than it is.
- Therapy can change marker patterns. Targeted treatments can alter or interfere with some immunophenotypic markers. This is especially relevant for CD38 after anti-CD38 therapy, so laboratories use alternative combinations to identify plasma cells accurately.
CD138 itself can also be shed from the cell surface into the surrounding environment. Soluble syndecan-1 has been studied as a biomarker in myeloma, but that is different from routine CD138 immunohistochemistry and should not be confused with the pathology stain.
Another common mistake is treating a post-treatment CD138 estimate as equivalent to modern measurable residual disease testing. A biopsy showing no obvious plasma-cell infiltrate is encouraging, but highly sensitive MRD methods can detect disease far below the level visible by routine microscopy. The MRD test for myeloma uses standardized flow cytometry or next-generation sequencing to look for very small residual clonal populations.
What Happens After a CD138 Result
The next step depends on whether the CD138-positive plasma cells are increased, clonal, and accompanied by other evidence of a plasma-cell disorder. The report is usually interpreted alongside blood counts, chemistry results, monoclonal protein testing, free light chains, imaging, flow cytometry, and cytogenetic or molecular studies.
If CD138 shows only a small number of scattered plasma cells and clonality studies are negative, the finding may be reactive. If the stain shows a substantial or abnormal infiltrate, the clinical team will usually confirm the nature of the population and determine whether diagnostic criteria for MGUS, smoldering myeloma, active myeloma, plasmacytoma, or another lymphoid disorder are met.
Useful questions to ask about the report include:
- What percentage of marrow cells were estimated to be plasma cells?
- Was the infiltrate scattered, clustered, nodular, or diffuse?
- Were the plasma cells kappa- or lambda-restricted?
- What did flow cytometry show about CD19, CD38, CD45, CD56, CD117, or other markers?
- Were myeloma FISH or molecular studies performed?
- How do the marrow findings compare with SPEP, immunofixation, free light chains, calcium, creatinine, hemoglobin, and imaging?
A related CD38 test may appear in the same flow-cytometry panel, but CD38 and CD138 serve overlapping rather than identical roles. CD38 is very bright on plasma cells and is also a treatment target in myeloma, while CD138 is especially useful for identifying and mapping plasma cells in tissue.
Urgent medical attention is not triggered by CD138 positivity alone. Urgency comes from the clinical situation—for example, severe anemia, kidney failure, high calcium, infection, neurologic symptoms from spinal compression, or symptomatic hyperviscosity. A pathology result should therefore be discussed with the hematology team in the context of symptoms and the entire diagnostic picture.
When comparing results over time, use caution with small percentage changes. A marrow reported as 12% plasma cells on one biopsy and 8% on another is not automatically proof of a biologically important response or progression. Sampling location, hemodilution, tissue quality, staining, and counting method can all shift the estimate. Trends are most meaningful when the same disease markers, response criteria, laboratory methods, and clinical context are considered together. In treated myeloma, clinicians usually rely on the complete response framework rather than CD138 percentage alone: monoclonal protein measurements, serum free light chains when applicable, marrow clonality, MRD testing, and imaging may each contribute. This broader approach prevents a visually reassuring biopsy from being overinterpreted when residual disease is detectable by a more sensitive method, and it also prevents a small reactive plasma-cell population from being mistaken for relapse.
References
- Advances in estimating plasma cells in bone marrow: A comprehensive method review 2024 (Review)
- Targeted therapy for multiple myeloma: an overview on CD138-based strategies 2024 (Review)
- Evaluation of an innovative new method for quantitation of plasma cells on CD138 immunohistochemistry 2023
- Understanding the Bioactivity and Prognostic Implication of Commonly Used Surface Antigens in Multiple Myeloma 2022 (Review)
- CD138/syndecan-1: a useful immunohistochemical marker of normal and neoplastic plasma cells on routine trephine bone marrow biopsies 1999
Disclaimer
This article is for general education and cannot diagnose or exclude multiple myeloma or another plasma-cell disorder. CD138 findings must be interpreted by a qualified clinician or pathologist together with marrow morphology, clonality studies, laboratory results, imaging, and the patient’s clinical history. Seek prompt medical care for severe weakness, confusion, breathing difficulty, uncontrolled bleeding, new neurologic symptoms, or other acute illness.