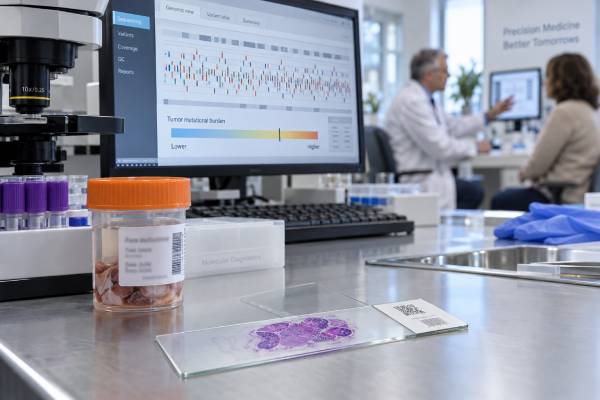
A tumor mutational burden (TMB) test estimates how many acquired mutations are present across a defined amount of tumor DNA, usually reported as mutations per megabase (mut/Mb). TMB is most often generated from next-generation sequencing of a tumor sample and is used as one piece of evidence when considering immune checkpoint inhibitor therapy. A higher TMB can increase the chance that a tumor produces abnormal proteins, or neoantigens, that the immune system may recognize. However, TMB is not a direct measurement of immune activity and does not guarantee that immunotherapy will work. Results depend on the assay, genes and genomic territory analyzed, specimen quality, tumor purity, germline filtering, bioinformatics, and the cutoff used. In the United States, an FDA tumor-agnostic pembrolizumab indication uses TMB-high at 10 or more mutations/Mb under specific clinical and assay conditions, but that threshold should not be treated as a universal biological boundary for every cancer or every platform.
- TMB is a genomic mutation-density score, usually expressed as mutations per megabase, not a count of every mutation in the entire tumor genome.
- A TMB-high result can support immunotherapy consideration in some settings, but it does not guarantee response and must be interpreted with tumor type, treatment line, and other biomarkers.
- The 10 mut/Mb cutoff is clinically important but not universal. Different assays and cancer types can produce different TMB distributions and predictive value.
- TMB is not the same as MSI, mismatch-repair deficiency, or PD-L1. These biomarkers can overlap but measure different tumor and immune features.
- A low TMB result does not prove immunotherapy will fail. Some low-TMB cancers respond because immune sensitivity depends on more than mutation quantity.
Table of Contents
- What Tumor Mutational Burden Measures
- How TMB Is Tested and Calculated
- What a TMB-High Result Means
- TMB and Immunotherapy Decisions
- TMB Versus MSI and PD-L1
- Limitations and Assay Differences
- How to Read Your TMB Report
What Tumor Mutational Burden Measures
TMB is an estimate of the density of somatic mutations in cancer DNA. Somatic mutations are changes acquired by tumor cells rather than variants inherited in every cell of the body. A result might be reported as 4 mut/Mb, 10 mut/Mb, 25 mut/Mb, or another value depending on how many qualifying mutations the assay finds and how much genomic territory it evaluates.
The biological idea behind TMB is straightforward. Mutations can change the amino-acid sequence of proteins. Some altered proteins are processed into neoantigens that the immune system may recognize as foreign. A tumor with many mutations may therefore offer more potential targets for activated T cells. Immune checkpoint inhibitors can remove inhibitory signals that normally restrain those T cells, making high mutation burden a plausible marker of treatment sensitivity.
But TMB is only a proxy. Not every DNA mutation creates a protein change. Not every protein change produces a neoantigen. Not every neoantigen is presented to T cells, and even a highly antigenic tumor can suppress immune cells through other mechanisms. This is why two tumors with the same numerical TMB can behave differently on immunotherapy.
TMB also reflects different underlying mutational processes. Tobacco exposure can produce a high mutation load in some lung cancers. Ultraviolet radiation can drive very high TMB in melanoma and certain skin cancers. Defective DNA proofreading caused by pathogenic POLE or POLD1 alterations can produce an ultramutated phenotype. Mismatch-repair deficiency can also increase the number of mutations, which creates overlap between TMB and microsatellite instability testing.
The score is therefore best understood as a summary biomarker rather than a diagnosis. It does not identify the tumor’s origin, stage, or complete set of actionable alterations. A broad solid-tumor NGS panel may report TMB alongside specific mutations, gene fusions, copy-number changes, MSI status, and other molecular findings. Those individual findings can be more immediately actionable than the TMB score in some cancers.
How TMB Is Tested and Calculated
The historical research standard for TMB is whole-exome sequencing, which examines the protein-coding portion of the genome. In routine oncology, most TMB results come from large targeted NGS panels because they require less DNA, are faster, and can simultaneously identify treatment-relevant mutations and fusions.
A targeted panel samples a defined amount of genomic territory. The laboratory counts qualifying somatic mutations within that region and normalizes the count to the number of megabases successfully analyzed. In simplified form, if an assay finds 20 qualifying mutations across two megabases of adequately sequenced DNA, the estimated TMB would be about 10 mut/Mb. Real laboratory calculations are more complicated because filters determine which variants are included.
Different assays may count different categories of mutations. Some methods include only nonsynonymous coding substitutions and small insertions or deletions. Others use synonymous mutations as part of the estimate because they can improve statistical precision even though synonymous variants do not directly change protein sequence. Laboratories also differ in how they handle known driver mutations, sequencing artifacts, low-VAF calls, and genomic regions with difficult coverage.
Germline filtering is critical. Inherited variants should not inflate a somatic TMB score. Tumor-normal sequencing can directly compare tumor DNA with constitutional DNA from blood or another source. Tumor-only panels instead use population databases and computational methods to remove likely germline variants. Imperfect filtering can push TMB upward.
Specimen quality matters as well. Formalin-fixed tissue can contain damaged DNA. Very low tumor purity can make true somatic variants harder to detect and may lower the estimate. Poor sequencing quality can either reduce sensitivity or create artifacts if quality controls are inadequate. Laboratories should therefore validate minimum DNA input, coverage, tumor content, and acceptable specimen conditions.
Panel size is another source of variability. A small genomic footprint produces a noisier estimate because each counted mutation changes the final mut/Mb value more dramatically. Modern consensus recommendations emphasize transparent assay validation and reporting so clinicians know what genomic territory, variant types, and filters were used.
TMB can also be estimated from circulating tumor DNA in plasma, often called blood TMB. Blood and tissue TMB should not automatically be treated as interchangeable because tumor DNA shedding, panel design, sequencing depth, and filtering differ. A ctDNA mutation panel can be valuable when tissue is limited, but its TMB interpretation must follow validation for that specific assay and clinical setting.
What a TMB-High Result Means
“TMB-high” is a category assigned when a score meets or exceeds a defined cutoff. The most recognized U.S. cutoff is 10 mutations/Mb because it was used for an FDA-approved tumor-agnostic pembrolizumab indication and its companion diagnostic. That regulatory threshold is important, but it is not a universal law of tumor biology.
The FDA indication applies to adult and pediatric patients with unresectable or metastatic TMB-high solid tumors, as determined by an FDA-approved test, whose disease has progressed after prior treatment and who have no satisfactory alternative treatment options. The original accelerated approval was based on a biomarker analysis of KEYNOTE-158. In that analysis, patients with TMB of at least 10 mut/Mb had a higher objective response rate to pembrolizumab than patients below the threshold.
That finding does not mean that every patient at 10 mut/Mb will respond or that a patient at 9 mut/Mb will not. TMB is continuous, while a treatment decision often requires a categorical cutoff. The biology near that boundary is not suddenly different by one mutation per megabase. Laboratory measurement uncertainty also matters, especially when a result sits close to the threshold.
Tumor type changes the interpretation. Mutation burdens vary greatly among cancers. A score that is unusually high for one tumor type may be ordinary for another. The relationship between TMB and checkpoint-inhibitor benefit is also stronger in some cancers than others. Certain malignancies can have many mutations but remain poorly immunogenic because of antigen-presentation defects or an immune-suppressive microenvironment.
The underlying reason for high TMB can provide useful context. MSI-high/mismatch-repair-deficient tumors, POLE/POLD1 proofreading-deficient tumors, UV-associated cancers, and tobacco-associated cancers may have distinctive mutation patterns. When TMB is very high, clinicians may look for an explanatory molecular mechanism because that mechanism can carry its own diagnostic, hereditary, or treatment implications.
A report that says “TMB-high” should therefore identify the actual numerical score and the laboratory cutoff. The category is more informative when the reader knows whether the value is barely above the threshold or extremely elevated and whether the assay is validated for the proposed clinical use.
TMB and Immunotherapy Decisions
Immune checkpoint inhibitors target proteins such as PD-1, PD-L1, or CTLA-4 that normally help regulate immune responses. TMB can contribute to the decision to use these drugs because a highly mutated tumor may produce more recognizable neoantigens. Still, immunotherapy response depends on an entire cancer-immune system, not just mutation count.
The strongest way to use TMB is within the exact clinical context supported by evidence or a treatment guideline. For a patient meeting the FDA tumor-agnostic TMB-high indication, the score can create a pembrolizumab option when prior therapy has failed and no satisfactory alternatives remain. In a cancer with its own established first-line immunotherapy regimen, TMB may not be needed to justify treatment. In another cancer, TMB may be considered investigational or only one factor among several.
The KEYNOTE-158 biomarker analysis illustrates both the value and the limits of TMB. Using a prespecified threshold of at least 10 mut/Mb, objective responses were seen more often in the TMB-high group. However, most TMB-high patients still did not have an objective response, and some patients below the threshold did respond. TMB is therefore an enrichment biomarker, not a guarantee.
Treatment decisions also consider PD-L1 expression, MSI/MMR status, tumor histology, stage, prior therapy, autoimmune disease, organ transplant history, performance status, and the expected toxicity and benefit of alternative treatments. Some targeted therapies should take priority when a strong oncogenic driver is present. In lung cancer, for example, comprehensive driver mutation and fusion testing can identify therapies whose relevance is independent of TMB.
TMB should not be used to persuade a patient that immunotherapy is certain to work. Checkpoint inhibitors can cause serious immune-related adverse events involving the bowel, lungs, liver, endocrine organs, skin, nervous system, heart, and other tissues. The potential benefit of a high TMB score must be weighed against these risks and against disease-specific treatment alternatives.
A low TMB value should also not automatically exclude immunotherapy. Some tumors respond through mechanisms not captured by mutation count, and several checkpoint-inhibitor indications are based on tumor type, PD-L1 status, MSI/MMR status, or treatment regimen rather than TMB. The relevant drug label and current oncology guideline should take precedence over a generic interpretation of the number.
TMB Versus MSI and PD-L1
TMB, MSI/MMR testing, and PD-L1 testing are often discussed together because all can help predict checkpoint-inhibitor benefit, but they measure different biology.
TMB measures the density of qualifying somatic mutations in tumor DNA. It is a genomic summary score.
MSI-high or mismatch-repair deficiency (dMMR) indicates failure of the DNA mismatch-repair system. This produces characteristic instability at repetitive DNA sequences and can cause a high overall mutation load. Many MSI-high tumors are TMB-high, but the two tests are not identical. A tumor can be TMB-high without being MSI-high, and the exact overlap depends on cancer type and assay.
PD-L1 is usually measured by immunohistochemistry and estimates expression of a checkpoint-ligand protein on tumor cells, immune cells, or both, depending on the scoring system. PD-L1 reflects aspects of the tumor immune environment rather than mutation quantity. A tumor can be PD-L1-high with low TMB or PD-L1-low with high TMB.
These differences explain why one biomarker cannot simply substitute for another. In colorectal and endometrial cancers, mismatch-repair status can carry diagnostic and hereditary implications in addition to immunotherapy relevance. In lung cancer, PD-L1 and driver mutations can strongly shape first-line treatment. TMB may add information, but its role varies with the disease.
The biomarkers can also be combined conceptually. A tumor with high TMB, strong PD-L1 expression, and an inflamed immune microenvironment may look more immunologically favorable than a tumor with high TMB but defective antigen presentation. Research increasingly examines composite markers because mutation burden alone captures only one stage of the cancer-immunity process.
When multiple biomarkers are reported, the correct interpretation is not “the highest one wins.” The oncologist should identify which biomarkers are validated for that cancer, which correspond to approved treatments, and whether a molecular finding points to a more effective targeted approach.
Limitations and Assay Differences
The greatest practical limitation of TMB is lack of perfect cross-assay equivalence. Two laboratories can test the same tumor and produce different numerical estimates because they sequence different genomic regions, use different mutation filters, require different minimum VAFs, and apply different germline-removal strategies.
Panel footprint matters. TMB is a statistical estimate derived from a sample of the genome. Larger well-validated panels generally provide more stable estimates than very small panels. The selected genes also matter because cancer-related panels are not a random sample of the genome; they are enriched for genes commonly mutated in tumors. Bioinformatics must account for this design to avoid systematic overestimation.
Preanalytic factors can change the score before sequencing even begins. Small biopsies may contain little tumor. Necrosis can reduce usable DNA. Formalin damage can create artifactual base changes. Decalcified bone specimens can perform poorly depending on the decalcification method. A report may therefore state that TMB is “not evaluable” even when some individual variants can still be reported.
Temporal and spatial heterogeneity can also matter. A metastatic lesion collected years after the primary tumor may have accumulated additional mutations, particularly after therapy. Different metastatic sites can contain related but not identical subclones. TMB from an old archival specimen may therefore not perfectly represent current disease.
Blood-based TMB adds another layer of uncertainty. A plasma sample with little circulating tumor DNA may underestimate the tumor mutation load. Blood cells can contribute clonal-hematopoiesis variants that must be distinguished from tumor-derived changes. Cutoffs validated for tissue should not be automatically copied to plasma without evidence.
Another limitation is biological: not all mutations are equally immunogenic. A frameshift that creates a novel protein sequence may have a different immune effect from a mutation that generates no presented neoantigen. HLA genotype, antigen processing, T-cell infiltration, interferon signaling, and immune-suppressive pathways can all modify response. A simple mutation count does not capture those variables.
These limitations do not make TMB useless. They explain why professional consensus recommendations emphasize assay validation, transparent reporting, and clinical context. TMB is most reliable when the laboratory has demonstrated analytic performance and when the treatment decision matches the assay and evidence base.
How to Read Your TMB Report
Start with the numerical value and units. A useful report should state TMB in mut/Mb and identify whether the laboratory classifies it as low, intermediate, high, or another category. The exact terms vary by assay, so the number and cutoff are more informative than the label alone.
Next, identify the specimen and method. Was the score generated from tissue or plasma? Was it calculated by a large validated NGS panel? Is the assay FDA-approved or otherwise validated for the treatment being considered? If a report gives a TMB category without explaining the method, the clinician may need the laboratory’s technical documentation.
Then ask whether the result sits near the cutoff. A value of 10 mut/Mb and a value of 80 mut/Mb may both be called TMB-high, but the degree of elevation is very different. Near-threshold values deserve particular attention to assay variability and the exact regulatory or guideline criteria.
Review the rest of the molecular report. An MSI-high result, POLE/POLD1 alteration, or characteristic driver mutation can help explain the mutation burden and may create additional treatment or hereditary implications. Conversely, a targetable fusion or driver mutation may direct treatment more strongly than TMB in that tumor type.
Check whether TMB is being used as a predictive biomarker or merely described. A report may list TMB because the assay calculates it routinely, even when the patient’s cancer has no validated TMB-based treatment decision at that stage. Clinical utility depends on tumor type, treatment setting, drug label, and guideline—not on the presence of the number alone.
Finally, interpret TMB as a probability modifier. High TMB can increase the likelihood of benefit from checkpoint blockade in selected populations, but it cannot predict an individual response with certainty. Low TMB can reduce that likelihood in some contexts, but it does not rule response out. The most useful discussion combines TMB with pathology, stage, prior treatments, other biomarkers, overall health, and the patient’s goals.
References
- Recommendations for Tumor Mutational Burden Assay Validation and Reporting: A Joint Consensus Recommendation of the Association for Molecular Pathology, College of American Pathologists, and Society for Immunotherapy of Cancer — 2024, consensus recommendation.
- Tumor mutational burden for the prediction of PD-(L)1 blockade efficacy in cancer: challenges and opportunities — 2024, review.
- Tumor mutational burden: why is it still a controversial agnostic immunotherapy biomarker? — 2025, review.
- Association of tumour mutational burden with outcomes in patients with advanced solid tumours treated with pembrolizumab: prospective biomarker analysis of the multicohort, open-label, phase 2 KEYNOTE-158 study — 2020, prospective biomarker analysis.
- FDA approves pembrolizumab for adults and children with TMB-H solid tumors — 2020, regulatory announcement.
Disclaimer
This article is for general educational purposes and does not replace individualized oncology advice. TMB values can vary by assay and specimen, and treatment eligibility depends on the cancer type, disease setting, current drug labeling, guideline recommendations, other biomarkers, and the patient’s health. A qualified oncology team should interpret the complete molecular report before treatment decisions are made.