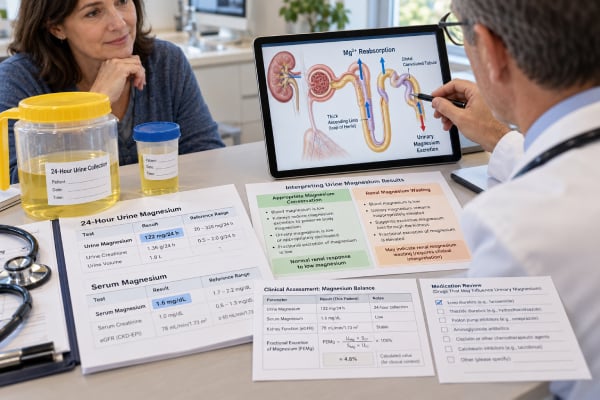
A urine magnesium test measures how much magnesium the kidneys are excreting. It is most useful when blood magnesium is low and the clinician needs to determine whether magnesium is being lost through the kidneys or somewhere else, such as the gastrointestinal tract. Testing may use a 24-hour urine collection, a random urine sample, or a calculation called the fractional excretion of magnesium, which combines urine and blood magnesium with urine and blood creatinine. A high urine magnesium result can indicate inappropriate renal wasting when serum magnesium is already low. A low urine magnesium result can instead show that the kidneys are appropriately conserving magnesium during deficiency. Interpretation changes when kidney function is reduced, after magnesium supplements or IV magnesium, and with medications that alter tubular handling. Because magnesium disturbances often travel with potassium and calcium abnormalities, urine magnesium is usually one part of a broader electrolyte evaluation rather than a stand-alone test.
- When blood magnesium is low, high urinary magnesium suggests kidney magnesium wasting; low urinary magnesium suggests the kidneys are appropriately conserving magnesium.
- A 24-hour urine magnesium test measures total daily excretion, while fractional excretion of magnesium adjusts for filtration and urine concentration.
- Many laboratories report a broad 24-hour reference range; one major laboratory uses 51–269 mg/24 hours for adults in its validated age range.
- Diuretics, cisplatin, aminoglycosides, calcineurin inhibitors, diabetes, alcohol use, and inherited tubule disorders can increase renal magnesium loss.
- Urine magnesium should be interpreted with serum magnesium, creatinine/eGFR, potassium, calcium, medications, and recent magnesium intake.
Table of Contents
- What the Urine Magnesium Test Measures
- When Urine Magnesium Is Ordered
- High and Low Urine Magnesium
- Fractional Excretion of Magnesium
- Causes of Renal Magnesium Wasting
- Collection, Preparation, and Limitations
- Follow-Up and Treatment Clues
- Practical Urine Magnesium Patterns
What the Urine Magnesium Test Measures
Magnesium is an essential mineral involved in nerve conduction, muscle contraction, energy metabolism, bone health, and electrical stability of the heart. Most body magnesium is inside cells or stored in bone, so serum magnesium represents only a small fraction of total stores. The kidneys play a central role in keeping magnesium balance stable by changing how much filtered magnesium is reabsorbed or allowed to leave in urine.
A urine magnesium test does not simply ask whether the urine contains “too much” or “too little” magnesium. It asks whether kidney excretion is appropriate for the blood magnesium level and the clinical situation.
When magnesium stores are low, healthy kidneys should conserve magnesium aggressively. Therefore, a low urine magnesium result can be an appropriate response. In contrast, if serum magnesium is low but urine magnesium remains relatively high, the kidneys may be wasting magnesium.
Testing can be performed in several ways:
- 24-hour urine magnesium: Measures the total amount excreted over a full day.
- Spot urine magnesium: Measures concentration at one moment, but is strongly affected by urine dilution.
- Fractional excretion of magnesium (FEMg): Uses paired blood and urine magnesium and creatinine measurements to estimate the fraction of filtered magnesium excreted.
- Urine magnesium-to-creatinine ratio: Sometimes used when a timed collection is impractical.
A 24-hour laboratory reference interval can be useful for general orientation. One large clinical laboratory reports 51–269 mg/24 hours for adults in its established age range. However, a value inside that interval can still be inappropriate during hypomagnesemia. If serum magnesium is low, the kidneys should usually be reducing magnesium excretion below what might be typical in magnesium-replete people.
When Urine Magnesium Is Ordered
The most common reason to measure urinary magnesium is unexplained or persistent hypomagnesemia. Serum magnesium may stay low despite replacement because magnesium is still being lost through the kidneys or gastrointestinal tract. Urine testing helps separate those mechanisms.
Clinicians may order the test when there is:
- recurrent low serum magnesium;
- low potassium that is difficult to correct;
- low calcium associated with magnesium deficiency;
- chronic diarrhea or malabsorption, where gastrointestinal loss is possible;
- use of medications known to cause renal magnesium wasting;
- suspected Gitelman or Bartter syndrome;
- unexplained muscle cramps, tremor, weakness, seizures, or arrhythmias with low magnesium;
- kidney stone evaluation in selected metabolic urine profiles;
- concern about magnesium balance in chronic kidney disease.
Magnesium is tightly linked to potassium. Severe or persistent magnesium deficiency can make hypokalemia difficult to correct because renal potassium losses may continue until magnesium is restored. That is why a blood potassium test and serum magnesium are often interpreted together.
Calcium can also fall when magnesium deficiency impairs parathyroid hormone secretion or action. In a patient with low magnesium plus low calcium, the urine magnesium pattern can help identify whether the primary magnesium problem is renal loss or extrarenal depletion.
Urine magnesium is less commonly used as a stand-alone kidney stone marker. Magnesium can inhibit calcium crystal growth, but low urinary magnesium in isolation is not considered a dominant stone cause. A full 24-hour urine stone risk profile is more informative because calcium, oxalate, citrate, sodium, urine volume, and pH usually have stronger established roles.
High and Low Urine Magnesium
The meaning of a high or low urine magnesium result depends first on the serum magnesium concentration.
| Blood magnesium | Urine magnesium pattern | Likely interpretation |
|---|---|---|
| Low | Low | Kidneys are appropriately conserving magnesium; consider low intake, diarrhea, malabsorption, or redistribution |
| Low | Inappropriately high | Renal magnesium wasting is likely |
| Normal | High | May reflect high intake, supplements, recent IV magnesium, medications, or renal handling differences |
| High | Low or modest | Reduced kidney excretion may be contributing, especially with impaired GFR |
Low urine magnesium
Low urinary magnesium is often appropriate during deficiency. If serum magnesium is low and the kidneys are conserving magnesium, the cause is more likely outside the kidney. Chronic diarrhea, inflammatory bowel disease, pancreatic disease, malabsorption, bariatric surgery, poor intake, and proton pump inhibitor-associated magnesium deficiency can all produce this pattern.
A low 24-hour result can also be caused by an incomplete urine collection. That possibility becomes especially important when other 24-hour analytes are unexpectedly low as well.
High urine magnesium
High urinary magnesium is most informative when serum magnesium is low. In that context, the kidney is failing to conserve magnesium as expected. Renal wasting can result from drugs, tubule disorders, endocrine conditions, or recovery from certain kidney injuries.
If serum magnesium is normal or high, high urine excretion may simply be the normal renal response to a magnesium load from food, supplements, antacids, laxatives, or IV therapy. The result is not automatically a sign of kidney disease.
Fractional Excretion of Magnesium
Fractional excretion of magnesium, or FEMg, is often more useful than a random urine magnesium concentration because it accounts for urine creatinine and serum values. It estimates what percentage of filtered magnesium is ultimately excreted.
A commonly used formula is:
FEMg (%) = 100 × (urine magnesium × serum creatinine) ÷ (0.7 × serum magnesium × urine creatinine)
The factor of 0.7 approximates the fraction of serum magnesium that is ultrafilterable. Laboratories and references may present slightly different conventions, so clinicians should use the method validated for their setting.
In a person with hypomagnesemia and reasonably preserved kidney function, an FEMg above roughly 3–4% supports renal magnesium wasting, while a lower result suggests appropriate renal conservation and an extrarenal source of loss. Some references use lower cutoffs, especially around 2%, so the value should not be treated as an absolute boundary.
Recent reviews also describe 24-hour excretion thresholds in magnesium-depleted patients. Very low daily excretion, such as less than roughly 10 mg/day, supports appropriate renal conservation, whereas persistent excretion above about 10–30 mg/day despite hypomagnesemia can support renal wasting. Again, these are physiologic guides rather than universal laboratory reference intervals.
Reduced GFR complicates FEMg interpretation. When filtration is low, fractional excretion can rise as surviving nephrons adapt, and the usual cutoffs may not apply cleanly. A current eGFR should therefore be reviewed before labeling an FEMg result abnormal.
Causes of Renal Magnesium Wasting
Many conditions can cause the kidneys to lose more magnesium than they should.
Medications
Drug-related renal magnesium wasting is common enough that medication review is essential. Important examples include:
- loop and thiazide diuretics;
- cisplatin and some other platinum chemotherapy drugs;
- aminoglycoside antibiotics;
- amphotericin B;
- calcineurin inhibitors such as tacrolimus and cyclosporine;
- some epidermal growth factor receptor-targeting therapies.
The timing can be important. Cisplatin, for example, can produce tubular magnesium wasting that persists long after treatment.
Gitelman and Bartter syndromes
Inherited salt-transport disorders can present with renal magnesium loss. Gitelman syndrome typically causes hypokalemic metabolic alkalosis, low or normal blood pressure, hypomagnesemia, and low urine calcium. Bartter syndromes usually involve the loop of Henle and often produce hypercalciuria or normal urinary calcium depending on the subtype.
The combination of urine magnesium, urine calcium, potassium, chloride, blood pressure, and acid-base status helps distinguish these disorders. A urine chloride test is often high in ongoing renal salt-wasting states despite metabolic alkalosis.
Diabetes and osmotic diuresis
Poorly controlled diabetes can increase urinary magnesium losses through osmotic diuresis and altered tubular handling. Glycosuria also increases urine osmolality and flow, so serum glucose and urine glucose may be relevant when magnesium wasting is unexplained.
Alcohol-related loss
Heavy alcohol use can contribute through poor intake, diarrhea, pancreatitis, and direct renal magnesium wasting. Multiple mechanisms may coexist, so urine magnesium can help identify whether the kidney component is substantial.
Endocrine and calcium-related disorders
Hypercalcemia, hyperaldosteronism, and other hormonal states can alter magnesium handling. Because magnesium, calcium, and potassium are interdependent, an apparently isolated magnesium abnormality may be part of a broader mineral or endocrine disorder.
Collection, Preparation, and Limitations
For a 24-hour urine test, collect every urine void during the instructed period. Usually, the first void at the start time is discarded, all urine after that is collected, and the final void at the same time the next day is included. Storage and preservative instructions vary by laboratory.
Do not stop magnesium supplements or prescribed medications unless instructed. The clinician may want to know your magnesium handling under your usual treatment. However, recent IV magnesium or a large supplement dose can substantially increase urinary excretion, so timing should be documented.
Important limitations include:
- incomplete 24-hour collection;
- large changes in diet or supplement intake during the collection;
- reduced kidney function;
- very dilute or concentrated spot urine;
- recent IV fluids or magnesium therapy;
- acute kidney injury, which can change tubular handling quickly;
- mixed renal and gastrointestinal losses.
Urine creatinine is commonly measured with a 24-hour collection to assess plausibility. A urine creatinine test can flag a suspicious collection, but expected creatinine varies with muscle mass, age, sex, and body size, so it is not a perfect completeness check.
Follow-Up and Treatment Clues
The next step after an abnormal urine magnesium result depends on whether the body is magnesium deficient, magnesium overloaded, or simply adapting normally.
For renal wasting, clinicians may review or change a causative medication when possible, correct associated potassium or calcium disorders, and use oral or IV magnesium depending on severity. Some patients with persistent renal wasting benefit from strategies that reduce urinary magnesium loss, but treatment must be individualized to blood pressure, kidney function, and the underlying cause.
For extrarenal depletion, attention shifts toward intake, chronic diarrhea, malabsorption, gastrointestinal disease, or medications such as proton pump inhibitors. Treating the source of loss is important because repeated replacement alone may not maintain normal levels.
Hypermagnesemia is a different problem. It occurs most often when kidney function is markedly reduced and magnesium exposure is high, such as from magnesium-containing antacids, laxatives, supplements, or IV therapy. In that setting, urinary excretion may be insufficient even if the fraction excreted is increased.
Urgent evaluation is appropriate for severe weakness, reduced reflexes, confusion, seizures, fainting, or heart rhythm symptoms in the setting of a significant magnesium abnormality. Severe hypomagnesemia can cause arrhythmias and seizures, while severe hypermagnesemia can depress neuromuscular and cardiac function.
A urine magnesium test is therefore most valuable as a mechanism test: it tells the clinician whether the kidneys are conserving magnesium appropriately, wasting it, or failing to excrete a load because filtration is impaired.
Practical Urine Magnesium Patterns
Common clinical patterns can make the meaning of urinary magnesium easier to see.
Low serum magnesium with diarrhea and very low urinary magnesium: This is an appropriate renal response. The kidneys are conserving magnesium, so gastrointestinal loss or poor absorption is more likely than a primary renal wasting disorder. Replacing magnesium may still be necessary, but durable correction depends on treating the diarrhea or malabsorption.
Low serum magnesium with a high FEMg after cisplatin: Persistent renal magnesium wasting is common after tubular injury from platinum chemotherapy. Even if the treatment ended months earlier, the urine can show continued inappropriate loss. Oral magnesium may be limited by diarrhea, making replacement challenging and requiring individualized follow-up.
Low magnesium, low potassium, metabolic alkalosis, and low urine calcium: This pattern raises concern for Gitelman physiology, especially when blood pressure is normal or low and diuretic use is excluded. The magnesium result becomes more meaningful because it fits a broader tubular transport pattern rather than standing alone.
Low magnesium, high urine calcium, and salt wasting: Bartter-type physiology or a loop-diuretic effect becomes more plausible. Measuring urine calcium alongside magnesium, potassium, and chloride helps localize the tubular pattern.
High serum magnesium in advanced kidney disease: A person taking magnesium-containing laxatives may develop hypermagnesemia because filtration is reduced. Urine magnesium concentration could still look substantial, but total excretory capacity is inadequate relative to the magnesium load. The clinical issue is impaired clearance, not renal wasting.
Normal serum magnesium with suspected total-body depletion: Serum magnesium can remain normal until deficiency is significant because only a small fraction of total body magnesium is extracellular. Urinary testing is sometimes helpful, but there is no single urine result that reliably measures total body stores in every patient. Symptoms and associated potassium or calcium abnormalities still matter.
Magnesium replacement can also change the diagnostic picture quickly. A urine sample obtained soon after IV magnesium may show high excretion because filtered delivery suddenly increased. When the goal is to diagnose chronic renal wasting, the clinician should interpret the sample relative to the timing and route of replacement.
Finally, a urinary magnesium value should not be used to justify unsupervised high-dose supplementation. Magnesium products can cause diarrhea, interact with medications, and accumulate when kidney function is impaired. The test is best used to identify the mechanism of imbalance so treatment can target the cause.
When results are borderline, repeating paired serum and urine measurements after the acute illness has stabilized can be more informative than relying on one sample. Fever, IV fluids, changing kidney function, diarrhea, and recent replacement can all shift magnesium handling within hours. A stable outpatient sample obtained before the next supplement dose may better represent chronic renal handling than a sample collected during aggressive inpatient replacement.
The same principle applies to inherited tubule disorders: diagnosis is based on a reproducible biochemical pattern and the clinical setting, not on one FEMg percentage. Genetic testing may be appropriate when lifelong symptoms, family history, characteristic urine calcium findings, or persistent salt wasting make an inherited disorder plausible.
References
- Hypomagnesemia: A Clinical and Nutritional Update 2026 (Review)
- Physiology of a Forgotten Electrolyte-Magnesium Disorders 2023 (Review)
- Measuring magnesium – Physiological, clinical and analytical perspectives 2022 (Review)
- Acquired Disorders of Hypomagnesemia 2023 (Review)
- Understanding Renal Tubular Function: Key Mechanisms, Clinical Relevance, and Comprehensive Urine Assessment 2025 (Review)
- MAGU – Overview: Magnesium, 24 Hour, Urine 2026
Disclaimer
This article is for general education and cannot determine the cause of an individual magnesium disorder. Urine magnesium must be interpreted with serum magnesium, kidney function, other electrolytes, medications, and the collection method. Severe weakness, seizures, fainting, or heart rhythm symptoms with an abnormal magnesium level require prompt medical care.