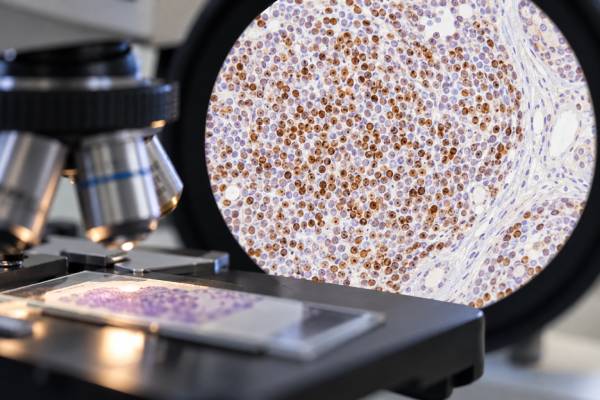
A cyclin D1 test helps pathologists decide whether an abnormal B-cell population has the molecular pattern expected in mantle cell lymphoma (MCL). The test is usually performed by immunohistochemistry on a lymph node, bone marrow, or other tissue biopsy and looks for excess cyclin D1 protein inside the nuclei of tumor cells. In most conventional MCL, a chromosome rearrangement involving the CCND1 gene drives this overexpression, so strong nuclear cyclin D1 staining is an important diagnostic clue. It is not, however, a stand-alone cancer test. A pathologist interprets the staining together with the cell appearance, other immunophenotypic markers, and often a genetic test for a CCND1 rearrangement. A negative result also does not completely exclude MCL because a small minority of cases use other cyclin genes instead. The practical meaning of a cyclin D1 result therefore depends on the staining pattern and the rest of the lymphoma workup.
- Positive cyclin D1 staining strongly supports mantle cell lymphoma when the tumor also has the expected B-cell and CD5-positive phenotype.
- The clinically important pattern is nuclear staining in the abnormal lymphoid cells; a laboratory may report intensity and the percentage of positive cells rather than a universal numeric cutoff.
- Most MCL is cyclin D1 positive because of an IG::CCND1 rearrangement, commonly t(11;14), but rare cyclin D1-negative MCL exists.
- A positive cyclin D1 result is not specific to MCL by itself because other neoplasms, including some plasma cell tumors and occasional large B-cell lymphomas, can show CCND1 abnormalities or cyclin D1 expression.
- No special patient preparation is usually needed; the test is performed on biopsy material that has already been collected.
Table of Contents
- What Cyclin D1 Testing Measures
- How the Test Is Performed
- What a Positive Result Means
- Negative and Equivocal Results
- How Cyclin D1 Fits the MCL Workup
- Important Pitfalls and Differential Diagnosis
- What Happens After the Result
What Cyclin D1 Testing Measures
The cyclin D1 test used in lymphoma diagnosis most often measures cyclin D1 protein expression in tissue. Cyclin D1 is a cell-cycle regulatory protein encoded by the CCND1 gene. Its normal job is to help cells move from the G1 phase into the S phase of the cell cycle. In MCL, the CCND1 gene is commonly placed next to an immunoglobulin gene regulatory region by a chromosomal rearrangement. That abnormal positioning causes persistent cyclin D1 production and gives the lymphoma a growth advantage.
The classic genetic event is t(11;14)(q13;q32), which usually creates an IGH::CCND1 fusion. Modern classifications recognize that the essential biology is the CCND1 rearrangement and overexpression, not simply the visual presence of a particular chromosome swap. A dedicated CCND1/IGH FISH test can demonstrate the rearrangement directly when the diagnosis is uncertain or confirmation is important.
Cyclin D1 immunohistochemistry answers a different question from FISH. Immunohistochemistry asks, “Are these cells making excess cyclin D1 protein?” FISH asks, “Is the CCND1 locus genetically rearranged in the expected way?” The two tests usually agree in conventional MCL, but they are not interchangeable in every case.
MCL is a mature B-cell lymphoma. In its conventional form, the tumor cells are usually small to medium in size and express B-cell markers such as CD20 and PAX5 along with CD5. They are typically negative for CD23 or express it only weakly or variably. The pathologist does not diagnose MCL from cyclin D1 alone; the diagnosis comes from the combined pattern of morphology, immunophenotype, and genetics.
A useful way to think about cyclin D1 is as a high-value piece of evidence rather than a binary cancer marker. Strong staining in the right B-cell population may make MCL very likely. The same staining in a different cellular context can mean something else.
How the Test Is Performed
Cyclin D1 is usually tested by immunohistochemistry (IHC) on formalin-fixed tissue. Common specimens include an excised lymph node, a core needle biopsy, bone marrow clot or core material, gastrointestinal biopsy tissue, spleen, or another involved organ. The pathology laboratory applies an antibody that binds cyclin D1 and uses a detection system that makes positive cells visible under a microscope.
The expected MCL signal is nuclear because cyclin D1 functions in the nucleus. The pathologist evaluates several features:
- whether the abnormal lymphoid cells stain at all;
- whether the staining is nuclear rather than nonspecific background staining;
- how strong the staining is;
- how widespread it is through the tumor population; and
- whether internal control cells stain as expected.
There is no single patient-facing “normal range” such as 0–10 mg/dL. This is a tissue marker, not a blood chemistry measurement. Laboratories may report results as positive or negative, or may describe staining as weak, moderate, or strong and focal or diffuse. Some reports include an estimated percentage of positive tumor cells. Interpretation depends on the antibody platform, tissue quality, controls, and the overall pathologic picture.
No special fasting, medication hold, or timing is needed specifically for cyclin D1 IHC. Preparation is determined by the biopsy procedure itself. Once tissue is obtained, fixation quality matters. Overfixation, decalcification of bone marrow material, scant tumor cells, crush artifact, or poorly preserved tissue can reduce staining quality and sometimes produce an equivocal result.
When IHC does not settle the question, the laboratory may add FISH, sequencing, or other immunostains. A lymphoma flow cytometry panel can define B-cell clonality and the broader immunophenotype, but flow cytometry does not usually replace tissue cyclin D1 staining because it answers a different set of diagnostic questions.
What a Positive Result Means
A positive cyclin D1 result strongly supports MCL when it occurs in a clonal mature B-cell lymphoma with compatible morphology and immunophenotype. In conventional MCL, cyclin D1 positivity is usually diffuse and clearly nuclear. Current lymphoma classifications describe IG::CCND1 as the genetic hallmark of the great majority of MCL cases.
A typical diagnostic pattern might look like this:
| Finding | Typical MCL pattern | What it contributes |
|---|---|---|
| Morphology | Small to medium atypical lymphocytes, sometimes with irregular nuclei | Shows a mature lymphoid neoplasm and its growth pattern |
| B-cell markers | CD20/PAX5 positive | Confirms B-cell lineage |
| CD5 | Usually positive | Helps narrow the differential diagnosis |
| Cyclin D1 | Usually strong nuclear positivity | Strongly supports CCND1-driven MCL |
| CCND1 rearrangement | Usually present | Provides genetic confirmation |
The report may use wording such as “cyclin D1 positive in the neoplastic B cells” or “diffuse strong nuclear cyclin D1 expression.” That finding is much more meaningful than occasional scattered positive cells, because many normal tissues contain some cyclin D1-positive cells.
A positive result does not tell you the stage of the lymphoma, whether it has spread to bone marrow, or how quickly it will behave. It also does not measure tumor burden in the way a quantitative blood marker might. Staging depends on clinical examination, imaging, blood tests, and bone marrow assessment when indicated.
Cyclin D1 positivity also should not be confused with a treatment target. It is primarily a diagnostic marker. Treatment decisions in MCL depend on the disease pattern, symptoms, age and fitness, stage, tumor burden, histologic variant, proliferation rate, and high-risk molecular features such as TP53 abnormalities. Cyclin D1 confirms a central biologic feature of the lymphoma, but its staining intensity alone is not a treatment score.
Negative and Equivocal Results
A negative cyclin D1 stain makes conventional MCL less likely, but it does not completely exclude MCL. A small subset of MCL lacks CCND1 rearrangement and cyclin D1 overexpression. These tumors can instead have rearrangements involving CCND2 or CCND3 and can otherwise resemble classic MCL.
This is where SOX11 becomes especially useful. SOX11 is a transcription factor expressed in many conventional MCL cases, including many cyclin D1-negative examples. A SOX11 immunohistochemistry test can therefore provide supportive evidence when morphology and immunophenotype still suggest MCL despite a negative cyclin D1 result. SOX11 is not perfectly specific, so the result still needs to be integrated with genetic findings.
A truly cyclin D1-negative suspected MCL may prompt testing for CCND2 or CCND3 rearrangements, depending on the laboratory and clinical setting. This is particularly important when the tumor has the classic CD5-positive mature B-cell phenotype but lacks the expected CCND1 result.
An equivocal result is different from a clearly negative one. Equivocal situations include weak staining, staining in only a small fraction of questionable cells, poor tissue preservation, or uncertainty about whether the stained cells are actually the tumor cells. In those cases, repeating the stain on better tissue or adding FISH may be more useful than forcing a positive/negative interpretation.
Several technical issues can create false reassurance or confusion. Decalcified bone marrow cores may lose antigenicity. Small biopsies may not contain enough lymphoma. Strong background staining can obscure the nuclear pattern. A prior treatment may also change the abundance or appearance of tumor cells. Pathologists account for these limitations before interpreting the result.
The key point is that “cyclin D1 negative” means the expected protein overexpression was not demonstrated in that specimen. It does not automatically mean “no lymphoma,” and it does not by itself identify an alternative diagnosis.
How Cyclin D1 Fits the MCL Workup
MCL diagnosis is an integrated process. Cyclin D1 is usually ordered because the pathologist has already seen a lymphoid population whose morphology or initial immunophenotype raises the possibility of MCL. The test is then combined with other markers to establish lineage and distinguish MCL from look-alike disorders.
A common workup includes CD20 or another B-cell marker, CD5, CD23, cyclin D1, and sometimes SOX11. Additional stains such as LEF1, CD10, BCL6, or others may be added depending on the differential diagnosis. Flow cytometry can detect a light-chain-restricted B-cell population and show whether CD5, CD23, CD10, or other surface antigens are expressed. A CD20 result supports mature B-cell lineage but is not specific for MCL.
Genetic testing adds another layer. Demonstrating an IG::CCND1 rearrangement strongly supports conventional MCL in the proper context. If FISH is negative but the tumor is convincingly cyclin D1 positive, the pathologist may consider cryptic or uncommon CCND1 rearrangements that a standard probe set does not detect. Conversely, a CCND1 rearrangement found in an aggressive large B-cell tumor does not automatically prove MCL because secondary CCND1 events can occur in other lymphomas.
The broader diagnostic picture also separates conventional MCL from leukemic non-nodal MCL, a recognized biologic form that often presents with blood, bone marrow, and spleen involvement and little or no lymphadenopathy. Leukemic non-nodal disease is often SOX11 negative and can behave more indolently, although risk still varies from patient to patient.
The pathologist may also report Ki-67, a proliferation marker. A high Ki-67 index and blastoid or pleomorphic morphology can indicate more aggressive biology. These findings matter more for risk assessment than the mere fact that cyclin D1 is positive.
When reports seem to contain several “positive” markers, it helps to separate their roles: cyclin D1 helps identify the lymphoma type; markers such as Ki-67, TP53 status, morphology, and clinical variables contribute more directly to risk assessment; imaging and marrow studies establish disease distribution.
Important Pitfalls and Differential Diagnosis
The biggest interpretation mistake is treating cyclin D1 as if it were specific for MCL in every context. Cyclin D1 expression can occur outside MCL. The diagnostic question is therefore not “Is cyclin D1 positive?” but “Which cells are positive, what do those cells look like, and what other markers and genetic findings do they have?”
One common differential diagnosis is chronic lymphocytic leukemia/small lymphocytic lymphoma (CLL/SLL). Both MCL and CLL/SLL can be CD5-positive mature B-cell neoplasms. CLL/SLL is usually cyclin D1 negative and often CD23 and LEF1 positive, while MCL is usually cyclin D1 positive and typically has an IG::CCND1 rearrangement. Rare exceptions mean that the full panel still matters.
Plasma cell neoplasms are another important pitfall. A subset of myeloma has t(11;14) and can express cyclin D1. In that setting, the positive cells are plasma cells with a plasma-cell immunophenotype, not the small mature B-cell population typical of MCL. This is one reason tissue context is essential.
Occasional diffuse large B-cell lymphomas can also acquire CCND1 rearrangements or cyclin D1 expression. Modern classification systems caution against calling such cases MCL solely because CCND1 is abnormal. The pathologist looks for the complete MCL phenotype, underlying lymphoma architecture, SOX11 pattern, and other genetic features.
Hairy cell leukemia may show cyclin D1 expression, often weaker than classic MCL, but its morphology and marker profile are distinct. Some non-hematologic tumors also express cyclin D1, which is why a positive stain in an unknown tumor has no useful meaning without lineage markers.
Practical questions to ask when reviewing a report include:
- Does the report say the neoplastic B cells are cyclin D1 positive?
- Is the staining described as nuclear, diffuse, and strong or as weak/focal?
- Are CD5, CD20, CD23, SOX11, and other relevant markers reported?
- Was a CCND1 rearrangement test performed or recommended?
- Does the final integrated diagnosis explicitly say mantle cell lymphoma?
The final pathology diagnosis carries more weight than any single line in the immunostain table.
What Happens After the Result
When cyclin D1 positivity helps confirm MCL, the next steps focus on classification, staging, and risk assessment, not on repeating the stain. The clinician typically reviews blood counts, chemistry results, symptoms, physical findings, imaging, and the pathology report. Bone marrow evaluation may be used in selected patients to document involvement, especially when it will change staging or management.
The pathology report may also include the Ki-67 proliferation index and a morphologic subtype such as classic, blastoid, or pleomorphic. Molecular testing for TP53 abnormalities is increasingly important because TP53-mutated or otherwise TP53-disrupted MCL can behave aggressively and respond differently to standard approaches. Clinical risk tools such as the Mantle Cell Lymphoma International Prognostic Index incorporate factors including age, performance status, LDH, and white blood cell count.
A positive cyclin D1 stain usually remains positive over the course of a conventional MCL because it reflects a defining biologic driver. It is not normally used as a serial blood test to monitor response. Treatment response is assessed with clinical evaluation, imaging, blood and marrow findings when relevant, and sometimes molecular measurable residual disease approaches in specialized settings.
If the result conflicts with the rest of the case, further review is appropriate. Examples include a strongly suspected MCL that is cyclin D1 negative, a large B-cell tumor with unexpected cyclin D1 positivity, or a FISH result that does not match the IHC pattern. In these situations, an expert hematopathology review, repeat testing on another tissue block, broader FISH, or sequencing can resolve the discrepancy.
For patients, the most useful question is not simply “Was cyclin D1 positive?” but “How did cyclin D1 contribute to the final diagnosis, and what other findings determine my risk and treatment plan?” That framing prevents a diagnostic marker from being mistaken for a stage, prognosis score, or treatment-response measurement.
References
- The International Consensus Classification of Mature Lymphoid Neoplasms: a report from the Clinical Advisory Committee 2022 (Position Statement)
- The 5th edition of the World Health Organization Classification of Haematolymphoid Tumours: Lymphoid Neoplasms 2022 (Review)
- Mantle Cell Lymphoma Under the Scope of Personalized Medicine: Perspective and Directions 2024 (Review)
- Cyclin D1-negative mantle cell lymphoma 2025 (Review)
- The pathologic diagnosis of mantle cell lymphoma 2021 (Review)
Disclaimer
Cyclin D1 testing must be interpreted by a pathologist together with the biopsy appearance, immunophenotype, and genetic findings. A positive or negative stain alone cannot confirm or exclude mantle cell lymphoma in every case. Discuss the integrated pathology diagnosis and any recommended follow-up testing with your hematologist or oncologist.