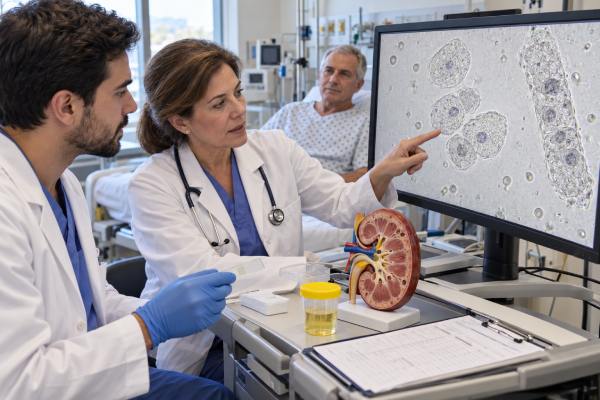
Renal tubular epithelial cells in urine can be an important sign of injury to the kidney tubules. These cells normally line the nephron, where they help reabsorb water, salts, glucose, and other substances from filtered fluid. A few cells may be shed, but increased numbers—especially when seen with granular casts, epithelial cell casts, rising creatinine, or reduced urine output—can support a diagnosis of acute tubular injury or another process affecting the kidneys. The finding is different from squamous epithelial cells, which usually come from the skin or genital tract and often reflect specimen contamination. It is also different from transitional, or urothelial, cells that line the bladder and collecting system. Because laboratories use different microscopy methods and reporting scales, there is no single universal cutoff that defines a dangerous renal tubular epithelial cell count. The result is most useful when interpreted with kidney function, urine output, medications, blood pressure, illness severity, and the rest of the urine sediment.
- Increased renal tubular epithelial cells suggest kidney tubule injury, but the result does not identify the cause by itself.
- Common settings include acute tubular injury from low blood flow, sepsis, toxins, medications, or severe systemic illness.
- Renal tubular epithelial cells are not the same as squamous cells; squamous cells more often reflect external contamination.
- Granular “muddy brown” casts or epithelial cell casts with these cells strengthen evidence of tubular injury.
- Rapidly rising creatinine, very low urine output, swelling, shortness of breath, confusion, or severe illness requires prompt medical evaluation.
Table of Contents
- What Renal Tubular Epithelial Cells Are
- Normal and Abnormal RTEC Results
- Causes of Increased Renal Tubular Epithelial Cells
- Microscopy Patterns That Support Tubular Injury
- How Clinicians Interpret the Finding
- Follow-Up and When Urgent Care Is Needed
What Renal Tubular Epithelial Cells Are
Renal tubular epithelial cells, often abbreviated RTECs, line the tubules of the nephron. The nephron is the kidney’s microscopic filtering unit. After blood is filtered through the glomerulus, the resulting fluid passes through the proximal tubule, loop of Henle, distal tubule, and collecting system. Tubular epithelial cells actively move water, electrolytes, glucose, amino acids, acids, and other substances between the tubular fluid and blood.
Because RTECs are attached to kidney tubules, finding increased numbers in urine suggests that tubular cells have been stressed, injured, detached, or shed. This can occur during acute kidney injury, especially acute tubular injury. The older term acute tubular necrosis is still widely used, but many cases involve reversible cell injury and detachment without widespread cell death, so “acute tubular injury” is often more accurate.
RTECs are one category within the broader group of epithelial cells in urine. Distinguishing the cell type matters:
- Squamous epithelial cells are large, flat cells that commonly come from the skin, distal urethra, or genital tract. Many squamous cells often suggest contamination.
- Transitional or urothelial cells line the renal pelvis, ureters, bladder, and part of the urethra. They can increase after instrumentation, inflammation, or other urothelial processes.
- Renal tubular epithelial cells originate within the kidney tubules and are more closely associated with renal parenchymal injury when present in increased numbers.
Under microscopy, RTECs are usually smaller than squamous cells and may have a relatively large, round nucleus. Their size and appearance vary depending on the nephron segment, cell degeneration, staining, and preparation method. Degenerating RTECs can accumulate lipid droplets or become difficult to distinguish from white blood cells or urothelial cells. Automated analyzers may classify them imperfectly, so manual review is valuable when the result will change clinical decisions.
The presence of RTECs is not a disease name. Instead, it is a clue that becomes useful when it matches the clinical picture and other urine findings. A report should also be read in light of specimen age and concentration, because cells degenerate after collection and may be harder to classify. When the laboratory specifically comments on RTECs or tubular casts, that detail is generally more informative than a nonspecific “epithelial cells present” entry.
The finding can be especially useful before the cause of AKI is clear. For example, a patient may have several possible contributors at once: infection, low blood pressure, diuretic use, an antibiotic with nephrotoxic potential, and urinary retention. RTECs and muddy brown casts make structural tubular injury more plausible, but they do not prove which exposure was responsible. The history and timing still matter. If creatinine began rising after prolonged hypotension, ischemic injury may be the leading explanation; if the change followed a new toxin or drug exposure, direct tubular toxicity may move higher on the list. This is how microscopy narrows the mechanism without replacing clinical reasoning.
Normal and Abnormal RTEC Results
Healthy kidneys continually replace cells, so occasional epithelial cells can appear in urine. However, there is no single universally accepted RTEC cutoff that applies to every laboratory. Some laboratories report “none seen,” “rare,” “few,” or “many,” while others count cells per high-power field or use automated measurements per microliter. Reference intervals depend on the method.
For this reason, the most important question is not whether the result is one cell above a printed range. It is whether the laboratory specifically identified increased renal tubular epithelial cells and whether the rest of the data support tubular injury.
An isolated report of “epithelial cells” is less specific because it may not distinguish squamous, transitional, and renal cells. If the clinical concern is acute kidney injury, the exact cell type and the presence of casts matter. A kidney-focused urine microscopy can provide this context.
RTECs are more meaningful when they appear with one or more of the following:
- a new rise in serum creatinine;
- reduced urine output;
- coarse granular or “muddy brown” casts;
- epithelial cell casts;
- a recent episode of low blood pressure, shock, major surgery, or sepsis;
- exposure to a medication or toxin that can injure tubules;
- electrolyte or acid-base abnormalities consistent with tubular dysfunction.
The number of cells also depends on timing. Tubular cells may shed early during injury and become less prominent later, even while creatinine remains elevated. A single urine sample therefore captures only one moment in an evolving process.
A normal or low RTEC count does not rule out acute kidney injury. Some causes of AKI, such as reduced kidney perfusion without structural damage, glomerulonephritis, urinary obstruction, or interstitial nephritis, may show a different sediment pattern. Even acute tubular injury can have a bland sediment in some cases. Urine microscopy is most useful as one piece of the diagnostic assessment rather than a stand-alone screening test.
Causes of Increased Renal Tubular Epithelial Cells
Increased RTECs can appear whenever the kidney tubules are directly injured or stressed. The most common clinical setting is acute tubular injury, but the trigger can vary.
Low blood flow and ischemia
Kidney tubules require a steady supply of oxygen. Severe dehydration, major bleeding, shock, cardiac surgery, prolonged low blood pressure, or severe heart failure can reduce renal perfusion enough to injure tubular cells. Early reductions in blood flow can be functional and reversible, but prolonged or severe ischemia can lead to structural tubular injury and cell shedding.
A patient who has been hypotensive during surgery or critical illness and then develops a rising creatinine plus RTECs and granular casts has a pattern strongly compatible with acute tubular injury.
Sepsis and systemic illness
Sepsis can damage the kidneys through a combination of altered blood flow, inflammation, endothelial dysfunction, and cellular stress. The urine sediment may show RTECs and granular casts, although the pattern is variable. Severe pancreatitis, burns, trauma, and other critical illnesses can produce similar multifactorial kidney injury.
Medications and toxins
Some medications can cause direct tubular toxicity, especially when exposure is high or the patient has additional risk factors. Examples include certain antibiotics, chemotherapy agents, contrast exposure in selected high-risk settings, and toxic substances such as ethylene glycol. Pigments released during severe muscle injury or massive hemolysis can also injure tubules.
Medication-associated AKI is not always tubular. Drugs can also cause allergic interstitial nephritis, alter kidney blood flow, produce crystals, or cause obstruction. That distinction matters because the urine sediment and treatment differ.
Other kidney diseases
RTECs can also be seen in proliferative glomerular diseases, interstitial inflammation, viral injury, transplant-related injury, and other renal disorders. Their presence indicates tubular involvement but does not prove that the tubules are the original site of disease.
A useful principle is that RTECs describe the location of cell shedding, not the mechanism. The cause must be determined from the patient’s history, hemodynamics, medications, blood tests, imaging, and other urine findings.
Microscopy Patterns That Support Tubular Injury
RTECs become more diagnostically useful when they occur in a characteristic sediment pattern. The classic pattern of acute tubular injury includes RTECs, renal tubular epithelial cell casts, and granular casts.
An epithelial cell cast forms when tubular epithelial cells become embedded in a protein matrix inside the nephron. Because casts form within kidney tubules, they localize the process to the kidney rather than the lower urinary tract. A cast containing recognizable RTECs supports tubular epithelial injury more strongly than free cells alone.
Granular casts form as cells and proteins degenerate within the tubular matrix. Coarse, dark granular casts are often called muddy brown casts. In the right clinical setting, granular casts in urine are a well-recognized clue to acute tubular injury.
| Urine sediment finding | What it may suggest | Important limitation |
|---|---|---|
| Free renal tubular epithelial cells | Tubular cell shedding or injury | Identification can be difficult and the finding is not cause-specific |
| Epithelial cell casts | Intrarenal tubular epithelial injury | Can occur in more than one kidney disease |
| Muddy brown granular casts | Acute tubular injury | Absence does not exclude AKI |
| RBC casts or many acanthocytes | Glomerular inflammation | Points away from isolated tubular injury |
| WBC casts with pyuria | Interstitial inflammation or pyelonephritis | Needs clinical correlation |
Urine microscopy can sometimes outperform a simple automated flag because experienced examination recognizes combinations of particles. However, microscopy is operator-dependent. Cell identification can change with centrifugation, staining, magnification, urine concentration, and how quickly the specimen is examined.
Lipids add another layer. Injured RTECs can contain fat droplets and may appear as oval fat bodies under polarized light. In heavy proteinuria, lipid-laden cells and fatty casts are more characteristic of nephrotic syndrome than of uncomplicated acute tubular injury.
The sediment should always be matched to the clinical syndrome. A patient with severe AKI and muddy brown casts has a different pattern from a patient with AKI, heavy proteinuria, dysmorphic red cells, and RBC casts. The latter raises much stronger concern for glomerulonephritis.
How Clinicians Interpret the Finding
When RTECs are reported, clinicians first ask whether there is actual acute kidney injury. AKI is diagnosed from changes in serum creatinine, urine output, or both—not from urine microscopy alone. The creatinine trend is especially important because a value that looks “normal” may still represent a major increase from a person’s baseline.
The next step is to identify the likely mechanism. A typical evaluation may include:
- recent blood pressure and fluid status;
- urine output over hours to days;
- serum creatinine and estimated GFR trend;
- electrolytes, bicarbonate, and sometimes creatine kinase if muscle injury is suspected;
- medication and contrast exposure history;
- evidence of infection, sepsis, bleeding, or heart failure;
- urinalysis for protein, blood, white cells, crystals, and casts;
- kidney or bladder imaging when obstruction is possible.
Tubular protein markers can sometimes provide additional information. Low-molecular-weight proteins are normally filtered and then reclaimed by proximal tubular cells. When those cells malfunction, urinary loss may increase. Tests such as urine beta-2 microglobulin or alpha-1 microglobulin can support selected evaluations of tubular dysfunction, but they are not routine replacements for creatinine and sediment examination.
A major interpretive challenge is separating prerenal AKI—reduced kidney perfusion without established structural injury—from acute tubular injury. Traditional urine chemistry indices can help in some settings, but diuretics, chronic kidney disease, sepsis, and other factors reduce their reliability. A sediment rich in RTECs and muddy brown casts supports structural tubular injury, while a bland sediment may fit a hemodynamic process. The categories can overlap, especially as prolonged low perfusion progresses to tubular damage.
Another challenge is distinguishing RTECs from contamination. Many squamous cells can make a specimen look “cellular,” but squamous contamination does not indicate kidney injury. If the report does not specify the epithelial cell type and the clinical stakes are high, laboratory clarification or repeat microscopy may be worthwhile.
Treatment is directed at the cause: restoring circulation when appropriate, treating sepsis, stopping or adjusting nephrotoxic exposures when clinically safe, relieving obstruction, and managing complications such as hyperkalemia or fluid overload. There is no medication that simply removes RTECs from urine.
The trend is often more informative than one snapshot. If creatinine rises after a period of shock and the first urine sample shows numerous RTECs and granular casts, later improvement in kidney function may occur even after those sediment findings fade. Conversely, a person can have ongoing injury despite a less dramatic second sediment. Clinicians therefore follow the patient rather than using disappearance of cells as a recovery target. The same principle applies when RTECs are found before creatinine has changed substantially: the sediment may raise suspicion, but kidney injury still has to be established and followed with standard clinical criteria.
Follow-Up and When Urgent Care Is Needed
An unexpected RTEC result should be interpreted promptly when kidney function is changing. If creatinine and urine output are stable and the finding is isolated, a clinician may review collection quality, repeat the urinalysis, or ask the laboratory to confirm the cell type. If AKI is present, the workup should focus on cause and severity rather than waiting for another microscopy result.
Follow-up often includes serial creatinine measurements and monitoring of urine output, potassium, bicarbonate, fluid balance, and blood pressure. The interval depends on severity: a hospitalized patient with rapidly changing kidney function may need measurements several times a day, while a stable outpatient with a mild abnormality may be rechecked over days under clinician guidance.
Nephrology consultation is particularly useful when AKI is severe, the diagnosis is uncertain, kidney function continues to worsen, there is substantial proteinuria or active glomerular sediment, or dialysis may be needed. Kidney biopsy is not routine for straightforward acute tubular injury, but it can be important when glomerulonephritis, interstitial nephritis, vasculitis, transplant disease, or another diagnosis cannot be established noninvasively.
Seek urgent medical evaluation for markedly reduced or absent urine output, rapidly increasing swelling, shortness of breath, chest symptoms, confusion, severe weakness, persistent vomiting, very low blood pressure, or a serious infection with worsening kidney function. Dangerous electrolyte abnormalities such as severe hyperkalemia can occur without obvious symptoms and may require emergency treatment.
People with diabetes, chronic kidney disease, heart failure, liver disease, a transplanted kidney, or recent major surgery have less reserve and may need earlier assessment. Avoid self-treating suspected kidney injury with large amounts of fluid, over-the-counter anti-inflammatory drugs, or unreviewed supplements; each can worsen certain forms of AKI.
The key message is that RTECs are most valuable as a microscopic marker of tubular stress or damage. They become clinically important when they fit a broader pattern of acute kidney injury, characteristic casts, recent exposures, or severe illness. Correctly identifying the cell type prevents both overcalling contamination and overlooking true kidney injury.
References
- Renal Tubular Epithelial Cells as Marker of Tubular Damage in Acute Kidney Disease 2025
- Flow-Cytometric Quantification of Urine Kidney Epithelial Cells Specifically Reflects Tubular Damage in Acute Kidney Diseases 2025
- Renal tubular epithelial cells as an easily accessible biomarker for diagnosing AKI post cardiac surgery 2025
- Renal tubular epithelial cells response to injury in acute kidney injury 2024 (Review)
- Urinary Sediment Microscopy and Correlations with Kidney Biopsy: Red Flags Not To Be Missed 2023
- The EFLM European Urinalysis Guideline 2023 2024 (Guideline)
Disclaimer
This article provides general information about renal tubular epithelial cells in urine and does not diagnose acute kidney injury or its cause. RTEC results should be interpreted with creatinine trends, urine output, medications, illness severity, and the complete urine sediment. Rapidly worsening kidney function, very low urine output, severe swelling, breathing difficulty, or serious systemic illness needs prompt medical care.