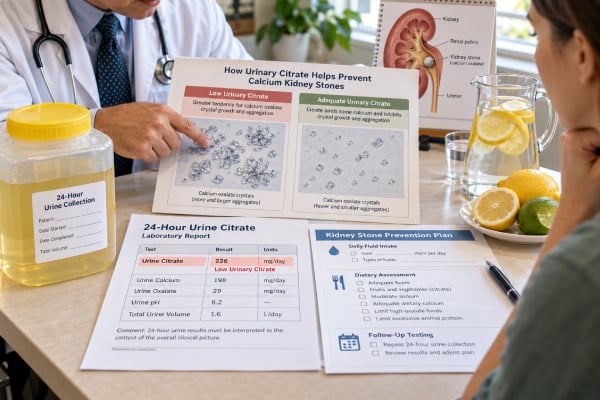
A urine citrate test measures citrate excreted by the kidneys, usually as part of a 24-hour urine evaluation for kidney stones. Citrate is protective because it binds calcium in urine and also interferes with crystal growth, making it harder for calcium oxalate and calcium phosphate stones to form. A low urine citrate level, called hypocitraturia, is therefore a modifiable stone-risk factor rather than simply an isolated laboratory abnormality. Urinary citrate can fall when the body is acid loaded, during low potassium states, with chronic diarrhea, some kidney tubular disorders, high animal-protein intake, and certain medications. It can also vary from day to day with diet and urine chemistry. Results are most useful when viewed together with urine volume, calcium, oxalate, sodium, uric acid, pH, and supersaturation values. Treatment often focuses on fluids and diet first, while potassium citrate or another alkali may be considered when low citrate persists or stone risk is high.
- Low urine citrate increases calcium stone risk because less citrate is available to bind calcium and inhibit crystal growth.
- A common traditional definition of hypocitraturia is less than 320 mg/day, but many labs use age-, sex-, or method-specific reference intervals and clinicians may target higher levels in stone formers.
- Chronic acid load, low potassium, diarrhea, distal renal tubular acidosis, and some high-protein dietary patterns can lower urine citrate.
- Potassium citrate can raise urine citrate and urine pH, but higher urine pH may increase calcium phosphate stone risk in some people.
- The citrate result should be interpreted with the rest of the 24-hour stone profile, especially urine volume, calcium, oxalate, pH, and sodium.
Table of Contents
- What a Urine Citrate Test Measures
- Why Citrate Affects Kidney Stone Risk
- Normal, Low, and High Urine Citrate
- Causes of Low Urine Citrate
- How the Test Is Collected and Interpreted
- Ways to Raise Urine Citrate
- When Results Need More Evaluation
- Practical Citrate Patterns in Stone Formers
What a Urine Citrate Test Measures
Citrate is an organic acid produced in normal metabolism. After citrate circulates in blood and is filtered by the kidneys, the renal tubules reabsorb a large portion of it. The amount left in urine reflects a balance between filtration, tubular reabsorption, acid-base status, potassium balance, and diet.
Urine citrate is usually measured in a 24-hour urine collection, because stone risk depends on total daily excretion and on the full-day urine environment. A random citrate-to-creatinine ratio can be used in selected settings, especially when a 24-hour collection is difficult, but adult kidney-stone evaluation commonly relies on timed testing.
The result may be reported in mg/24 hours, mmol/24 hours, or as a ratio to creatinine. Reference intervals vary substantially among laboratories. One major laboratory uses an age-specific adult lower limit that rises from 150 mg/24 hours at age 20 to more than 400 mg/24 hours in the late 50s, with an upper reference value of 1,191 mg/24 hours for much of that range. In contrast, many clinical discussions still use less than 320 mg/day as a practical definition of hypocitraturia. These are not conflicting ideas: one is a laboratory reference approach, while the other is a traditional stone-risk threshold.
For a person who forms stones, the key question is not simply whether citrate is inside a population reference interval. It is whether the citrate level is sufficiently protective given the person’s urine calcium, oxalate, pH, volume, and prior stone type.
A 24-hour urine kidney stone risk test often measures these variables together, which is much more useful than interpreting citrate in isolation.
Why Citrate Affects Kidney Stone Risk
Citrate reduces calcium stone formation through several complementary mechanisms. First, it binds free calcium to form soluble calcium-citrate complexes. That leaves less ionized calcium available to combine with oxalate or phosphate. Second, citrate can attach to growing crystal surfaces and slow crystal growth and aggregation. Third, increasing citrate through alkali therapy often changes urine pH and other aspects of urine chemistry.
Because stone formation depends on supersaturation rather than on one ingredient alone, the same citrate result can carry different risk in different people. Consider two examples:
- A person with modestly low citrate but excellent urine volume and low urine calcium may have a different risk profile from someone with the same citrate plus hypercalciuria and low urine volume.
- A person with calcium oxalate stones and low urine pH may benefit from urine alkalinization, while a person prone to calcium phosphate stones may require closer attention because pushing pH too high can increase calcium phosphate supersaturation.
This is why citrate treatment targets are individualized. “More citrate” is often useful, but “higher pH” is not automatically better in every stone former.
Urine citrate is particularly relevant to calcium oxalate stones, the most common stone type. It should be reviewed alongside a urine oxalate test and urine calcium because small shifts in calcium or oxalate can materially change calcium oxalate supersaturation.
Normal, Low, and High Urine Citrate
There is no universally optimal citrate value for every patient. Laboratories define reference intervals differently, and kidney-stone specialists often think in terms of risk reduction rather than a binary normal/abnormal cutoff.
| Result pattern | Typical interpretation | What to review next |
|---|---|---|
| Low citrate | Reduced protection against calcium crystallization; may reflect acid load, low potassium, diarrhea, renal tubular disease, or diet | Urine pH, potassium, calcium, oxalate, sodium, volume, medications, GI history |
| Borderline or “low-normal” citrate | May still matter in recurrent calcium stone formers, especially if other lithogenic factors are present | Stone type, supersaturation, recurrence history, total risk profile |
| Higher citrate | Generally protective against calcium stones | Check urine pH if using alkali, particularly with calcium phosphate stones |
A high urine citrate value by itself is rarely a disease marker. In stone prevention, it is usually favorable. The main caution arises when citrate has been raised with alkali therapy and urine pH becomes high enough to favor calcium phosphate crystallization. That is why clinicians may follow both citrate and pH rather than escalating citrate indefinitely.
A single low result also does not prove a permanent disorder. Diet, illness, collection quality, and day-to-day variation can affect 24-hour urine chemistry. Many stone programs use two collections when first characterizing recurrent stone risk because a second day can reveal whether the abnormality is consistent.
Causes of Low Urine Citrate
The kidney reabsorbs more citrate when the body needs to conserve base or respond to acid. As a result, many causes of hypocitraturia share a theme of systemic or intracellular acid load.
Dietary acid load and low alkali intake
Diets high in nondairy animal protein can generate more acid, while fruits and vegetables provide alkali precursors. A dietary pattern with high acid load and low plant intake can therefore reduce urinary citrate in susceptible people. High sodium intake can also worsen overall calcium stone risk by increasing urine calcium, even if its effect on citrate is less direct.
This does not mean everyone with a low citrate result needs an extreme alkaline diet. Stone-prevention diets should still provide adequate nutrition and generally maintain normal dietary calcium rather than restricting calcium indiscriminately.
Low potassium
Potassium depletion can promote intracellular acidosis in kidney tubular cells and increase citrate reabsorption, reducing urinary citrate. Low potassium may result from diarrhea, vomiting, diuretics, eating disorders, or renal losses. If serum potassium is low, correcting the underlying cause can be an important part of improving citrate handling.
Chronic diarrhea and malabsorption
Chronic diarrhea causes bicarbonate and potassium loss. The resulting acid-base and electrolyte changes can lower citrate. Some malabsorptive disorders also increase oxalate absorption, creating the particularly unfavorable combination of low citrate plus high oxalate.
Distal renal tubular acidosis
Distal renal tubular acidosis can cause alkaline urine, systemic metabolic acidosis, low potassium, hypocitraturia, nephrocalcinosis, and calcium phosphate stones. A persistently high urine pH does not rule out an acid problem; in distal RTA, the problem is precisely that the kidney cannot acidify urine appropriately. A urine pH test therefore needs to be interpreted with serum bicarbonate and potassium.
Medications and other conditions
Carbonic anhydrase inhibitors such as topiramate and acetazolamide can produce a renal tubular acidosis-like pattern, raise urine pH, and lower citrate, increasing calcium phosphate stone risk. Chronic kidney disease, fasting patterns, and some inherited metabolic conditions can also alter citrate excretion.
How the Test Is Collected and Interpreted
A 24-hour citrate test requires collecting all urine for the instructed period. Usually, you empty your bladder at the start time and discard that first urine, then collect every subsequent void for 24 hours, including the final void at the exact end time. The laboratory or collection kit may provide a preservative or specific storage instructions.
Follow the kit instructions exactly. Do not add supplements, change your diet dramatically, or deliberately drink excessive water unless your clinician asks you to. The goal is often to capture your usual chemistry. Tell the clinician about potassium citrate, sodium bicarbonate, calcium supplements, vitamin C, diuretics, topiramate, acetazolamide, and other medications that can influence stone risk.
The most useful interpretation asks several questions at once:
- Was the collection likely complete?
- Was urine volume adequate?
- Is citrate low relative to stone risk?
- Is urine calcium high?
- Is urine oxalate high?
- Is urine sodium high, suggesting high salt intake?
- What is the urine pH?
- Which supersaturation values are elevated?
Urine creatinine is often used to judge whether a timed collection is plausible. An unusually low total creatinine may suggest missed urine, while an unusually high value may reflect overcollection or simply high muscle mass. A 24-hour urine collection error can distort citrate and every other daily excretion result, so questionable collections are often repeated rather than overinterpreted.
Ways to Raise Urine Citrate
The treatment goal is to lower stone risk, not merely to move one number into range. The starting strategy often includes increasing urine volume, reducing excessive sodium intake, maintaining normal food calcium intake, and improving the balance between plant foods and excessive nondairy animal protein.
Fluids
Higher urine volume dilutes calcium, oxalate, uric acid, and other stone-forming solutes. For many recurrent stone formers, clinicians aim for enough fluid intake to produce at least about 2 to 2.5 liters of urine per day, although the target is individualized for body size, climate, heart or kidney disease, and other factors.
Fruits, vegetables, and dietary alkali
Fruits and vegetables can provide potassium and alkali precursors that may raise urine citrate. Citrus foods contain citrate, but the metabolic effect depends on the accompanying cation and the product. Lemon or lime juice may provide citrate, yet its effect is not identical to prescribed potassium citrate, and sugar-sweetened citrus drinks can add unwanted calories.
Potassium citrate
Potassium citrate is the main prescription alkali used for recurrent stones with hypocitraturia or persistently low urine pH. It can raise urinary citrate and pH and has evidence supporting recurrent stone prevention. The dose is adjusted to urine chemistry and clinical context.
Potassium citrate is not appropriate for everyone. It requires caution in people with advanced kidney disease, high blood potassium, or medications that raise potassium. It also can increase urine pH enough to worsen calcium phosphate supersaturation in susceptible patients. Follow-up urine testing is therefore part of treatment, not an optional extra.
Sodium bicarbonate or sodium citrate may be alternatives in selected patients, but added sodium can increase urine sodium and sometimes urine calcium, which may be undesirable in calcium stone formers.
When Results Need More Evaluation
A low citrate result deserves more attention when stones are recurrent, bilateral, occur at a young age, are accompanied by nephrocalcinosis, or appear alongside abnormal kidney function or unusual electrolyte findings. Persistent hypocitraturia with high urine pH and low serum bicarbonate can point toward distal renal tubular acidosis. Low citrate plus high oxalate may suggest chronic diarrhea, inflammatory bowel disease, pancreatic insufficiency, or a history of bariatric surgery.
A clinician may order serum electrolytes, bicarbonate, creatinine, calcium, phosphorus, uric acid, and sometimes parathyroid hormone depending on the stone pattern. Stone analysis is also valuable because treatment differs for calcium oxalate, calcium phosphate, uric acid, cystine, and infection stones. A kidney stone analysis can therefore make the urine citrate result more actionable.
Repeat 24-hour urine testing is often performed after dietary or medication changes to confirm that citrate, urine volume, and supersaturation have improved without creating a new problem such as excessively high urine pH. Kidney stone prevention is an iterative process: the best plan is the one that improves the whole urine profile and reduces recurrence risk over time.
Practical Citrate Patterns in Stone Formers
Citrate becomes more useful when interpreted as part of a pattern rather than as a lone cutoff.
Low citrate with high urine calcium: This combination increases calcium stone risk from two directions. Less citrate is available to bind calcium, while more calcium is present to form crystals. Sodium reduction, adequate dietary calcium, higher fluid intake, and treatment of persistent hypocitraturia may all be relevant. If urine sodium is high, reducing sodium can lower urine calcium and may improve the overall profile even if citrate itself changes little.
Low citrate with chronic diarrhea: Chronic gastrointestinal bicarbonate and potassium losses can lower urine citrate. If fat malabsorption is also present, urine oxalate may rise at the same time. This pattern is particularly important after some bariatric procedures or bowel disease because low volume, hyperoxaluria, and hypocitraturia can occur together. Treatment focuses on the gastrointestinal cause, fluid replacement, adequate calcium with meals, and correction of the acid and potassium deficit rather than citrate alone.
Low citrate with high urine pH: This combination deserves careful review. A persistently alkaline urine plus low citrate can be seen with distal renal tubular acidosis or with carbonic anhydrase inhibitor drugs such as topiramate. Calcium phosphate supersaturation may be elevated even though citrate is low. Simply pushing urine pH higher with more alkali can therefore be counterproductive unless the whole profile is being monitored.
Low-normal citrate with recurrent calcium oxalate stones: A value that technically falls inside a laboratory interval may still be worth addressing when stones continue and other risk factors are present. Stone prevention often uses individualized targets rather than treating the laboratory lower limit as a sharp boundary between safe and unsafe.
Citrate rises after treatment but stones still recur: The explanation may be elsewhere in the profile—low urine volume, persistent hypercalciuria, high oxalate, high sodium, uric acid abnormalities, or poor adherence on days not represented by the collection. A repeat urine supersaturation test can show whether the combined chemistry actually became less favorable for crystal formation.
The practical goal is not to maximize citrate at any cost. It is to create a urine environment with lower calcium oxalate or calcium phosphate supersaturation while maintaining safe potassium, kidney function, and urine pH.
References
- Prevention of Recurrent Kidney Stones: A CARI Guidelines Summary 2026 (Guideline)
- Citrate and calcium kidney stones 2025 (Review)
- Urine pH, citrate, and beyond: challenges of pharmaceutical stone management in daily urological practice 2025 (Review)
- The Multidisciplinary Approach in the Management of Patients with Kidney Stone Disease-A State-of-the-Art Review 2024 (Review)
- Ten tips on the work-up and management of CKD patients with nephrolithiasis 2025 (Review)
- CITR – Overview: Citrate Excretion, 24 Hour, Urine 2026
Disclaimer
This article is for general education and is not a diagnosis or a personal stone-prevention plan. Urine citrate should be interpreted with the full urine chemistry profile, stone type, kidney function, medications, and clinical history. Do not start potassium citrate or another alkali without medical guidance, especially if you have kidney disease or a history of high blood potassium.